Appendiceal Onlay / Interposition
The appendix is a pedicled tissue source for upper-tract reconstruction, used either as a tubular interposition conduit or as a spatulated onlay flap for ureteral augmentation. It has been used for selected right-sided proximal or mid-ureteral strictures where primary ureteroureterostomy would be under tension and ileal ureter substitution or renal autotransplantation would be excessive; selected pelvic ureteral substitutions have also been described.[1][2][3][4]
For oral mucosa alternatives, see Buccal Mucosa Graft Onlay (Ureter) and Augmented Anastomotic Ureteroureterostomy. For bowel substitution of long defects, see Ileal Ureter Substitution. For catheterizable-channel use of the appendix, see Continent Catheterizable Channels.
Why the Appendix Works
The appendix combines small caliber, close proximity to the right ureter, and a vascular pedicle through the mesoappendix.
| Property | Reconstructive Importance |
|---|---|
| Appendicular artery from the ileocolic artery | Makes the appendix a pedicled flap with intrinsic blood supply, unlike free oral mucosa grafts that require graft take from the recipient bed[1][2] |
| Ureter-like caliber | The lumen is often close enough to ureteral diameter for interposition or patch augmentation[2][3] |
| Mean length 8.21 cm in a 1932 post-mortem series of 4,680 specimens; individual length varies | Can bridge selected moderate right-sided defects, but short appendices limit use; cecal flap extension has been described for longer defects[2][4] |
| Mucus-producing columnar mucosa | Produces less mucus burden than ileal substitution[3] |
| Muscular wall | Permits pro-peristaltic orientation when used as a tubular conduit[3] |
| Right lower-quadrant location | Makes right proximal/mid-ureteral reconstruction natural; left-sided use is exceptional[2][4] |
Compared with buccal or lingual mucosa grafts, the appendix brings its own blood supply. Its limitation is location: it reaches the right ureter most readily.
Historical Position
Appendiceal ureteral substitution was described in the early 20th century but remained uncommon while ileal ureter substitution and standard reimplantation dominated long-segment reconstruction. Modern interest has returned for two reasons: robotic suturing makes intracorporeal appendiceal reconstruction feasible, and graft or flap ureteroplasty has created a reconstructive niche between short primary repair and ileal substitution.[1][2]
Yarlagadda et al. reported robotic intracorporeal appendiceal interposition for ureteral stricture disease in 2017, as an early case report of the robotic operation.[6]
Configurations
Appendiceal interposition
The appendix is harvested on its mesentery as a tubular conduit. The diseased ureteral segment is excised, and the appendix is interposed between healthy ureteral ends, or occasionally between ureter and renal pelvis or bladder depending on defect location.[6][7][8]
Interposition is a replacement operation: the appendix substitutes for the missing ureteral segment.
Appendiceal onlay flap
The appendix is harvested on its mesentery, opened longitudinally along the antimesenteric border, and laid as a pedicled patch over a longitudinal ureterotomy. The ureter is not fully replaced; the flap augments the narrowed ureteral plate.[5][8][9]
Onlay is an augmentation operation: the appendix widens a narrowed ureter while preserving native ureter continuity.
Augmented roof ureteroplasty
In the described augmented-roof variant, diseased mucosa was excised without transecting the ureteral backing, the posterior mucosal edges were reapproximated, and a pedicled appendiceal onlay completed the lumen. This differs from a transecting augmented-anastomotic repair.[5]
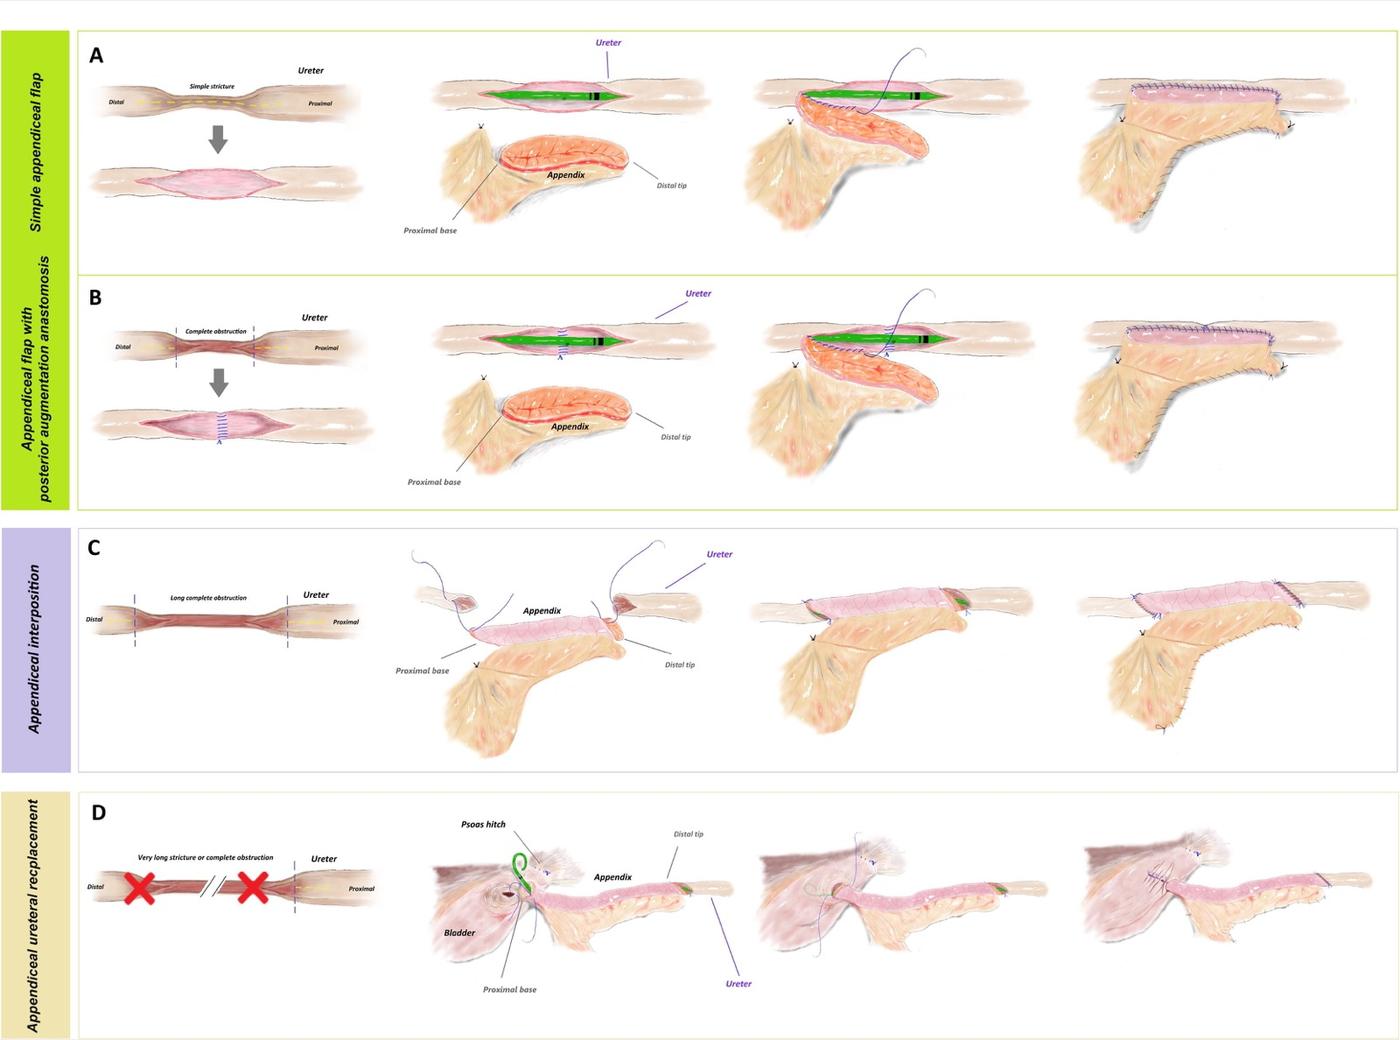
Robotic appendiceal ureteroplasty configurations. (A) Simple appendiceal onlay flap for a stricture without luminal obliteration. (B) Appendiceal flap with posterior augmentation anastomosis for short luminal obliteration or excision of a short diseased segment. (C) Appendiceal interposition for long luminal obliteration or long segmental excision when posterior augmentation is not feasible. (D) Appendiceal ureteral replacement with psoas hitch for a very long stricture or complete obstruction. From Yang K, et al. Eur Urol Open Sci. 2026;90:101-108, Fig. 3 (CC BY 4.0).[19]
Indications
Appendiceal ureteroplasty is considered when all of the following are favorable: right-sided disease, moderate defect length, usable appendix, and a need for vascularized tissue.[1][2][5][11]
| Indication | Why Appendix Is Attractive |
|---|---|
| Right proximal or mid-ureteral stricture; selected distal defect | Appendix is nearby for right-sided repair and can reach without bowel interposition; pelvic substitution has also been described when a well-perfused appendix reaches without tension.[4] |
| Defect about 2–8 cm for selected onlay or interposition repairs | Reported lengths vary by configuration; confirm usable appendiceal length, untwisted pedicle reach, and tension-free repair before choosing this approach.[3][19][20] |
| Failed balloon dilation or endoureterotomy | Moves from endoscopic treatment to tissue reconstruction |
| Post-stone-surgery or ureteroscopy stricture | Common right-sided benign indication in series |
| Radiation-induced or fibrotic stricture | Intrinsic blood supply may be useful, but superiority to free grafting is unproven |
| Need to avoid oral graft harvest | No second donor site |
| Need to avoid ileal ureter morbidity | Less mucus and metabolic burden than ileal substitution |
Published etiologies include nephrolithiasis, iatrogenic injury, failed pyeloplasty or ureteroscopy, radiation, and idiopathic strictures.[7][10][11]
Contraindications and Caution Zones
- prior appendectomy,
- diseased, fibrotic, atretic, inflamed, or ischemic appendix,
- left-sided ureteral disease unless an exceptional lengthening strategy is planned,
- appendix needed for Mitrofanoff appendicovesicostomy or MACE,
- a defect that remains longer than the usable appendix after safe bladder mobilization or psoas hitch; reported experience with this combined strategy is limited,[19]
- active appendiceal or cecal disease,
- extensive right lower-quadrant adhesions or mesenteric limitation,
- malignant ureteral disease requiring oncologic excision and margins.
In patients with neurogenic bladder, bladder augmentation, or anticipated continent catheterizable channel need, preserving the appendix for Mitrofanoff may be more valuable than using it for ureteral reconstruction.[12][16]
Preoperative Planning
Preoperative planning should define:
- Stricture length and location by CT urogram, MR urogram, retrograde or antegrade pyelography, and ureteroscopy when needed.
- Renal salvageability by renal scan, cortical thickness, symptoms, infection burden, and patient goals.
- Appendix availability from surgical history and intraoperative assessment.
- Competing appendix needs such as Mitrofanoff or MACE.
- Backup plan if the appendix is absent or unusable: buccal or lingual mucosa graft, Boari flap, ileal ureter, transureteroureterostomy, or renal autotransplantation.
Ureteroscopy and intraluminal ICG can help delineate the ureter; intravenous ICG may assess ureteral or appendiceal perfusion.[5]
Appendiceal Interposition Technique
- Expose the right ureter. Position and ports follow right upper or mid-ureteral reconstruction. Mobilize the ascending colon and ileocecal region as needed; for proximal or UPJ repair, confirm appendiceal reach without mesenteric tension.[19]
- Define the stricture. Use ureteroscopy, stent, ICG, and/or ureterotomy as needed.
- Excise the diseased segment. Debride to healthy ureteral mucosa and preserve periureteral blood supply.
- Harvest the appendix. Mobilize it on the mesoappendix while preserving the appendicular artery; divide from the cecum and close the cecal base.
- Prepare the appendiceal lumen. Open both ends, clear retained contents, confirm patency, and tailor length and caliber to the ureteral defect.[19]
- Orient without pedicle torsion. Confirm tension-free reach and blood supply before choosing which end faces proximally. Reports use differing orientations; a universal base-to-tip peristaltic rule should not override safe mesenteric geometry.[3][5]
- Perform proximal and distal anastomoses. Use fine absorbable sutures, typically 4-0 or 5-0, over a double-J stent; when a nephrostomy is present, gently irrigate to check patency and leakage.[19]
- Drain and follow. Stent removal is commonly around 6 weeks, individualized by tissue quality and leak risk.
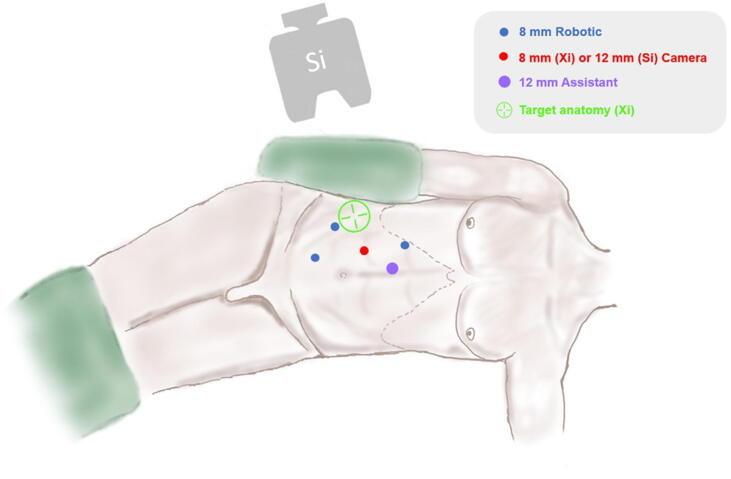
Patient position, port placement and robot docking for single-docking robotic appendiceal ureteroplasty. Blue circles mark 8 mm robotic ports; the red circle marks the camera port (8 mm robotic port on the da Vinci Xi or 12 mm port on the Si); the purple circle marks the 12 mm assistant port. The Xi target anatomy (green cross) lies between the ureteral stricture site and the cecum. From Yang K, et al. Eur Urol Open Sci. 2026;90:101-108, Fig. 1 (CC BY).[19]
Interposition suits a ureteral segment too diseased to preserve as a plate when the appendix is long enough to replace it.
Appendiceal Onlay Technique
- Expose the strictured right ureter.
- Open the ureter longitudinally across the stricture, preserving continuity whenever possible.
- Harvest the appendix on its mesentery. Divide it from the cecum, secure the cecal base, and preserve the mesoappendiceal blood supply.[21]
- Open the appendix longitudinally along the antimesenteric border to create a flat vascularized flap.
- Lay the appendiceal mucosa toward the ureteral lumen.
- Suture the flap to the ureterotomy edges as an anterior or ventral onlay.
- Place a double-J stent across the reconstruction.
- Confirm vascularity of the appendix and ureteral margins, using ICG if available.
Onlay suits a ureter that is narrowed but still worth preserving as a native plate. It is analogous to oral mucosa onlay ureteroplasty, but with a pedicled flap instead of a free graft.[5][9]
Cecal Flap Extension and Left-Sided Use
Appendiceal ureteroplasty is overwhelmingly right-sided. Komyakov et al. described a modification that uses a flap from the cecal dome to increase the appendiceal reach and anastomotic diameter, including 4 left-sided cases in a 26-patient series.[4]
Outcomes
| Series | N | Approach / Configuration | Stricture Length | Success |
|---|---|---|---|---|
| Yarlagadda et al. 2017 | 1 | Robotic interposition | 5 cm | Successful at 10 months[6] |
| Wang et al. 2020 | 9 | Robotic/laparoscopic onlay | 3-4.5 cm | 100% objective success (endoscopic and radiographic); 88.9% subjective success[9] |
| Burns et al. 2020 | 11 | Open (64%) or laparoscopic (36%) interposition | Not specified | No repeat intervention for recurrent stricture at median 363 days; 9/11 had an unobstructed renogram or improved hydronephrosis, and 2/11 retained poor renal function[7][20] |
| Jun et al. 2020 | 13 | Robotic; 62% onlay, 38% interposition | Mean 6.5 cm | 11/12 (92%) met the symptom-and-patency endpoint at mean 14.6 months; 1/12 required balloon dilation; 1/13 died from a cardiovascular event on postoperative day 0[10] |
| Komyakov et al. 2020 | 26 | Open (85%) or robot-assisted laparoscopic (15%) interposition; cecal flap extension in the last 22 cases | Long-segment | 22/26 initially favorable; 4 anastomotic strictures required intervention, with 25/26 favorable long-term results over 1-21 years[4][20] |
| Cho et al. 2024 | 14 | Robotic; 71% onlay, 29% interposition | Median 4.75 cm | 13/14 (92.9%) radiographic ureteral patency after stent removal; hydronephrosis improved without significant creatinine change[11] |
| Zhang et al. 2025 | 16 | Laparoscopic; 10 interposition, 6 onlay | 2–5 cm | 15/16 (93.8%) overall success at mean 14.9 months; no statistically significant difference was detected between configurations; equivalence was not assessed[8] |
Across reported appendiceal series, endpoints and follow-up vary: a 2026 review found 85–93% short-term success, while some individual cohorts report higher estimates; long-term durability remains uncertain and the evidence is concentrated in reconstructive centers.[1][8][10][11][19][20]
July 2026 update: Yang et al. reported 31 right-sided robotic operations, with prospectively collected perioperative and follow-up data. At median 28 months, 30/30 evaluable patients met the symptom-relief/radiographic-patency endpoint (100%; 95% CI 88.4–100%). The 100% estimate excludes one patient who later developed ovarian-tumor obstruction distal to the repair and required ongoing stent exchanges; it does not represent success in all 31 operations.[19]
Complications
| Complication | Notes |
|---|---|
| Recurrent stricture | Main failure mode; may require balloon dilation, endoureterotomy, stenting, re-anastomosis, or alternative reconstruction |
| UTI or pyelonephritis | Cho et al. reported UTI requiring readmission in 2/14 patients (14.3%) in the multi-institutional robotic experience[11] |
| Urinary leak | Managed with drainage, stent duration, nephrostomy, or reoperation depending on severity |
| Major complications | Burns et al. reported in-hospital Clavien–Dindo III complications in 3/11 patients (27%).[7] |
| Anastomotic stricture at appendiceal junction | Reported in long-term interposition experience[4] |
| Mucus | Usually far less clinically important than ileal substitution[3] |
Advantages
- Pedicled flap with intrinsic blood supply.
- No dependence on recipient-bed graft take.
- No oral donor site.
- Avoids ileal harvest, bowel anastomosis, and classic ileal ureter metabolic complications.
- Appropriate caliber for ureteral reconstruction.
- Less mucus burden than ileal substitution.
- Can be used as interposition, onlay, or augmented roof ureteroplasty.
- Same operative field for right-sided ureteral disease.
Limitations
- Usually right-sided only.
- Requires an intact, healthy, adequately long appendix.
- Competes with Mitrofanoff and MACE needs.
- Length is variable and sometimes inadequate.
- Evidence remains dominated by small observational cohorts, including a prospective-data series without a comparator.
- Once used, the appendix is no longer available for future channel construction or re-reconstruction.
- Left-sided use with cecal flap extension is exceptional.
Comparison With Alternatives
| Feature | Appendiceal Flap | Oral Mucosa Graft | Ileal Ureter |
|---|---|---|---|
| Tissue type | Pedicled vascularized flap | Free graft | Pedicled bowel segment |
| Laterality | Mostly right-sided | Bilateral | Bilateral |
| Best length range | Moderate, limited by appendix length | Moderate, usually up to about 8 cm | Long or pan-ureteral |
| Omental wrap | Usually not required for graft take | Strongly favored | Not a graft-take issue |
| Donor morbidity | Appendectomy/cecal closure | Oral pain, numbness, tightness | Bowel resection/anastomosis |
| Metabolic effects | Minimal | None | Acidosis, mucus, stones, B12/absorption issues depending on segment |
| Evidence maturity | Small series | Growing multi-institutional series | Larger historical experience |
A meta-analysis of 23 single-arm oral-graft and ileal-replacement studies found different pooled complication rates, but graft cohorts had much shorter strictures. It did not compare appendiceal reconstruction.[13]
Appendix in Other Urologic Reconstruction
Mitrofanoff appendicovesicostomy
The appendix is the classic conduit for a continent catheterizable channel from bladder to skin. This is often its most valuable reconstructive use in children and patients with neurogenic bladder, exstrophy, cloacal anomalies, or complex bladder reconstruction.[12][16]
Robot-assisted Mitrofanoff appendicovesicostomy is feasible, and large catheterizable-channel experience supports appendix as first-choice channel when available.[14][15][17][18]
Malone antegrade continence enema
The appendix can also be used for MACE or appendicostomy in patients with fecal incontinence or severe bowel-management needs. If a patient may need both urinary and bowel catheterizable channels, appendix allocation must be planned before using it for ureteral reconstruction.
Decision Framework
The appendix is favored when:
- the stricture is right-sided,
- the defect is moderate length,
- the appendix is intact and healthy,
- the patient does not need appendix for Mitrofanoff or MACE,
- a pedicled vascularized flap is preferable to a free graft,
- ileal substitution would be excessive.
An oral mucosa graft is favored when the appendix is absent, the stricture is left-sided, or a graft is more anatomically straightforward. Ileal ureter is favored when the defect is too long or complex for appendix or oral mucosa. Renal autotransplantation, transureteroureterostomy and substitution are selected according to anatomy, renal function, disease and patient priorities; no mandatory sequence applies.
Operative Pearls
- Inspect the appendix before committing; have a backup plan ready.
- Preserve the appendicular artery and mesoappendix.
- Do not sacrifice a future Mitrofanoff in a neurogenic-bladder patient without considering the channel need.
- Onlay suits a ureteral plate worth preserving.
- Interposition suits a diseased segment that should be removed.
- Prioritize a well-perfused, untwisted mesoappendix and tension-free anastomoses when selecting interposition orientation.
- Do not force left-sided reconstruction unless the appendix truly reaches without tension and the team has a mature plan.
Videos
References
1. Bello D, Van Shufflin M, Hofer MD. Expanding the armamentarium: perspectives on buccal mucosal grafts and appendiceal flaps in ureteral reconstructive surgery. J Clin Med. 2025;14(21):7681. doi:10.3390/jcm14217681.
2. O'Rourke TK, Gm M, Patel HV, et al. The urologist and the appendix: a review of appendiceal use in genitourinary reconstructive surgery. Urology. 2022;159:10-15. doi:10.1016/j.urology.2021.10.007.
3. Xiong S, Zhu W, Li X, et al. Intestinal interposition for complex ureteral reconstruction: a comprehensive review. Int J Urol. 2020;27(5):377-386. doi:10.1111/iju.14222.
4. Komyakov B, Ochelenko V, Guliev B, Shevnin M. Ureteral substitution with appendix. Int J Urol. 2020;27(8):663-669. doi:10.1111/iju.14268.
5. Gabrielson A, Li O, Cohen AJ. Robotic-assisted augmented roof ureteroplasty with appendiceal onlay flap. Urology. 2023;176:243-245. doi:10.1016/j.urology.2023.02.027.
6. Yarlagadda VK, Nix JW, Benson DG, Selph JP. Feasibility of intracorporeal robotic-assisted laparoscopic appendiceal interposition for ureteral stricture disease: a case report. Urology. 2017;109:201-205. doi:10.1016/j.urology.2017.08.017.
7. Burns ZR, Sawyer KN, Selph JP. Appendiceal interposition for ureteral stricture disease: technique and surgical outcomes. Urology. 2020;146:248-252. doi:10.1016/j.urology.2020.07.078.
8. Zhang B, Chen J, Chen X, et al. Laparoscopic ureteroplasty for the treatment of long ureteral strictures with appendiceal interposition and appendiceal onlay flap: technical description and initial experience. World J Urol. 2025;43(1):678. doi:10.1007/s00345-025-06048-8.
9. Wang J, Xiong S, Fan S, et al. Appendiceal onlay flap ureteroplasty for the treatment of complex ureteral strictures: initial experience of nine patients. J Endourol. 2020;34(8):874-881. doi:10.1089/end.2020.0176.
10. Jun MS, Stair S, Xu A, et al. A multi-institutional experience with robotic appendiceal ureteroplasty. Urology. 2020;145:287-291. doi:10.1016/j.urology.2020.06.062.
11. Cho EY, Chaudry AE, Puri D, et al. Outcomes of robot-assisted appendiceal ureteroplasty from a multi-institutional experience. Urology. 2024;192:136-140. doi:10.1016/j.urology.2024.07.042.
12. Cain MP, Casale AJ, King SJ, Rink RC. Appendicovesicostomy and newer alternatives for the Mitrofanoff procedure: results in the last 100 patients at Riley Children's Hospital. J Urol. 1999;162(5):1749-1752. doi:10.1016/s0022-5347(05)68230-4.
13. You Y, Gao X, Chai S, et al. Oral mucosal graft ureteroplasty versus ileal ureteric replacement: a meta-analysis. BJU Int. 2023;132(2):122-131. doi:10.1111/bju.15994.
14. Cerchia E, Serpentino M, Nguyen Duy V, et al. Minimally invasive Mitrofanoff in children: versatile laparoscopic strategies-from low-resource to non-robotic high-cost settings in an exploratory case series. J Clin Med. 2026;15(5):1954. doi:10.3390/jcm15051954.
15. Barashi NS, Rodriguez MV, Packiam VT, Gundeti MS. Bladder reconstruction with bowel: robot-assisted laparoscopic ileocystoplasty with Mitrofanoff appendicovesicostomy in pediatric patients. J Endourol. 2018;32(S1):S119-S126. doi:10.1089/end.2017.0720.
16. Sumfest JM, Burns MW, Mitchell ME. The Mitrofanoff principle in urinary reconstruction. J Urol. 1993;150(6):1875-1877. doi:10.1016/s0022-5347(17)35921-9.
17. Famakinwa OJ, Rosen AM, Gundeti MS. Robot-assisted laparoscopic Mitrofanoff appendicovesicostomy: technique and outcomes of extravesical and intravesical approaches. Eur Urol. 2013;64(5):831-836. doi:10.1016/j.eururo.2013.05.007.
18. Wille MA, Zagaja GP, Shalhav AL, Gundeti MS. Continence outcomes in patients undergoing robotic assisted laparoscopic Mitrofanoff appendicovesicostomy. J Urol. 2011;185(4):1438-1443. doi:10.1016/j.juro.2010.11.050.
19. Yang K, Li X, Xu L, et al. Robotic Appendiceal Ureteroplasty for Complex Right-sided Ureteral Strictures: Technical Approaches and Midterm Outcomes. Eur Urol Open Sci. 2026;90:101-108. Published online July 7, 2026. doi:10.1016/j.euros.2026.05.018.
20. Ditonno F, Costantino S, Treccani LP, et al. "Autologous Tissue Substitutes for Ureteral Reconstruction: A Systematic Review of Surgical Techniques and Outcomes." Eur Urol Open Sci. 2026;86:30-41. doi:10.1016/j.euros.2026.02.007
21. Wang J, Li Z, Fan S, et al. "Robotic ureteroplasty with appendiceal onlay flap: an update on the outcomes of 18-month follow-up." Transl Androl Urol. 2022;11(1):20–29. doi:10.21037/tau-21-840.