Boari Flap & Psoas Hitch
The psoas hitch and Boari flap are bladder-mobilization techniques used when distal ureteral reconstruction cannot be completed with a direct tension-free ureteral reimplantation. The psoas hitch brings the bladder cephalad to the ureter; the Boari flap converts a full-thickness bladder flap into a tubularized bladder-based ureteral substitute.[1][2][3]
The reconstructive rule is simple: move bladder before stretching ureter. Direct ureteroneocystostomy is used when the ureter reaches easily, psoas hitch when bladder fixation removes tension, and Boari flap when a longer bladder tube is needed to reach the mid or upper ureter.[1][3][4] AUA Urotrauma Statements 12a–12b (amended 2020) recommend repair where possible (Recommendation; Evidence Strength Grade C). Their discussion permits psoas hitch or Boari flap to obtain a tension-free acute repair and advises against bowel interposition or renal autotransplantation in that setting.[26] In its section on delayed-diagnosed ureteral injury, the EAU 2026 Urological Trauma guideline describes Boari flap for extensive mid-lower ureteral injury as time-consuming and unsuited to the acute setting.[32]
For the parent reimplantation framework, see Ureteral Reimplantation. For general upper-tract reconstruction rules, see Principles of Upper Tract Reconstruction. For distal stricture workup, see Ureteral Stricture.
Indications
Psoas hitch
Psoas hitch is the preferred bladder-based adjunct for lower and selected middle ureteral defects when direct reimplantation would be under tension.[1][3][5]
Common indications:
- iatrogenic distal ureteral injury during gynecologic, colorectal, urologic, vascular, or pelvic oncologic surgery,
- distal ureteral stricture from prior surgery, stones, endometriosis, radiation, ischemia, or retroperitoneal fibrosis,
- distal ureterectomy with bladder preservation,[27][28]
- failed prior ureteroneocystostomy,
- congenital distal ureteral anomalies in adults or older children,
- ureteral reimplantation where tension persists after routine bladder mobilization.[1][2][6]
Boari flap
Boari flap is used when the defect is too long for direct reimplantation or psoas hitch alone and the bladder has enough capacity and mobility to donate a flap.[4][7][8] For UTUC ureterectomy, AUA/SUO 2023 describes Boari flap or psoas hitch as adjuncts to tension-free reimplantation and calls for preoperative assessment of bladder capacity and function when more extensive reconstruction is anticipated (Statement 20 discussion). Complete distal ureter, intramural tunnel, and orifice excision with watertight closure is a Strong Recommendation (Grade B, Statement 22).[28] Eligible patients should receive one perioperative intravesical chemotherapy instillation to reduce bladder recurrence .[28]
Common indications:
- long distal or mid-ureteral loss,
- selected upper ureteral or lumbar-level defects when combined with psoas hitch or downward nephropexy,
- radiation-induced or ischemic distal or mid ureteral strictures,
- ureteral injury after pelvic surgery,
- distal ureterectomy for malignancy, including selected lower-ureter UTUC; for surgically eligible patients with high-risk or unfavorable low-risk UTUC endoscopically confined to the lower ureter in a functional renal unit, AUA/SUO 2023 prefers distal ureterectomy with reimplantation .[27][28]
- salvage after failed reimplantation when bladder tissue remains usable.[4][8][9]
In contemporary Boari flap series, a psoas hitch is commonly added first to stabilize the bladder and increase reach; one female reconstruction cohort used a concurrent psoas hitch in 62% of Boari flap cases.[8]
Contraindications and Caution Zones
| Problem | Why It Matters | Practical Response |
|---|---|---|
| Small-capacity or contracted bladder | Cannot reach or donate a useful flap without unacceptable storage morbidity | Consider augmentation, ileal ureter, TUU, or autotransplantation |
| Neurogenic high-pressure bladder | Reimplanting into hostile storage can threaten the kidney | Treat bladder storage first; consider augmentation or diversion |
| Frozen pelvis | Bladder cannot be mobilized safely | Delay after drainage, use alternate route, bowel substitution, or autotransplantation |
| Severe radiation injury to bladder | Flap may be ischemic, noncompliant, or too small | Assess cystoscopic capacity and tissue quality carefully |
| Bilateral long ureteral defects | A single bladder may not supply enough reach/capacity | Individualize; consider staged or bowel-based reconstruction |
| Active infection, large urinoma, or physiologic instability | Infection or poor physiology may preclude immediate definitive repair | Ensure urinary drainage; drain a large or infected collection and treat infection as indicated; choose immediate or staged repair according to patient stability, injury characteristics, and available expertise.[10] |
The bladder is the limiting organ.
Reconstruction Ladder
| Defect / Reach Problem | Usual Move | Approximate Reach Logic |
|---|---|---|
| Distal ureter reaches bladder easily | Direct ureteroneocystostomy | No adjunct needed |
| Distal ureter reaches only under tension | Psoas hitch | Bladder is fixed cephalad to remove tension |
| Mid-ureter defect or long distal loss | Boari flap +/- psoas hitch | Tubularized bladder flap bridges the gap |
| Upper ureter / lumbar-level reach | Boari flap + psoas hitch +/- downward nephropexy | Bladder tube plus kidney descent shortens both sides |
| Beyond bladder reach or hostile bladder | BMG ureteroplasty, ileal ureter, TUU, autotransplantation | Salvage ladder outside bladder-based repair |
Psoas Hitch
Concept
The psoas hitch mobilizes the bladder cephalad and anchors it to the ipsilateral psoas tendon or fascia. This brings a fixed, immobile bladder segment to the ureter and prevents the anastomosis from being pulled by a mobile bladder dome.[3][5][10]
Step-by-step technique
- Expose and stage the ureter. Identify the ureter proximal to the diseased segment, preserve periureteral adventitia, and debride back to healthy bleeding tissue.
- Spatulate the ureter. Spatulate the proximal ureter for 1-1.5 cm to create a broad mucosa-to-mucosa anastomosis.
- Mobilize the bladder. Develop the space of Retzius, divide lateral peritoneal attachments as needed, and mobilize the bladder enough that it reaches the ureter without stretch.
- Add length if needed. Partial or complete division of the contralateral bladder pedicle has been described to improve bladder reach when additional mobility is needed; preserve adequate blood supply to the mobilized bladder.[1][3][34]
- Choose the hitch point. Bring the bladder dome to the ipsilateral psoas tendon or fascia while confirming that the future ureteral course is straight.
- Protect the psoas nerves. The genitofemoral nerve runs on anterior psoas, while the femoral nerve may lie deeper. Identify nerve trajectories when possible and place superficial psoas bites if the nerves are not visible. Two reported pediatric cases of femoral palsy required re-exploration and suture removal.[33]
- Fix the bladder. Place two or three durable nonabsorbable or delayed-absorbable sutures from bladder wall to psoas tendon or fascia, incorporating the psoas minor tendon when present; avoid tying these sutures too tightly, since excessive tension on the fixation has been described as a cause of psoas muscle necrosis.[21]
- Create the reimplant. Use refluxing direct mucosa-to-mucosa anastomosis, intravesical antireflux tunnel, or extravesical Lich-Gregoir-style onlay depending on context.
- Stent, drain, and plan follow-up. Place a double-J stent, Foley catheter, and closed suction drain when appropriate. In one retrospective series of 24 adults, catheter removal followed a negative day-7 cystogram, the stent was removed at 4 weeks, and intravenous pyelography or CT at 3 months was followed by annual ultrasound and serum creatinine checks.[3]
- Close the bladder. If a cystotomy was used, close in two layers with absorbable suture and verify watertightness.
Technical rules
- The ureter should enter the bladder in a straight, non-kinked axis.
- The reimplant should sit in the fixed portion of bladder, not on a mobile dome under traction.
- The hitch should remove tension before the anastomosis is sewn; it is not a rescue stitch after a tight reimplant is already completed.
- Do not trade ureteral tension for bladder ischemia: preserve vesical blood supply unless extra reach truly requires pedicle division.
Outcomes
| Study | N | Approach | Key Result |
|---|---|---|---|
| Riedmiller 1984 | 181 | Open | Success rate 96.7% across broad indications, using a long submucosal antireflux tunnel[5] |
| Mathews & Marshall 1997 | 20 | Open | 17/20 needed no further intervention and kept normal renal function at mean 6 years (range 1–14)[11] |
| Manassero 2012 | 24 | Open | Contemporary long-term adult series; no reinterventions at mean 53 months[3] |
| Wenske 2013 | 58 psoas hitch cases | Open | Part of a 100-case series (24 primary ureteroneocystostomy, 58 psoas hitch, 18 Boari flap); hydronephrosis resolved in 81% overall, median follow-up 48.7 months[2] |
| Dell'Oglio 2021 | 37 robotic cases (30 psoas hitch, 7 Boari flap) | Robotic | Median OR time 180 min, EBL 100 mL, LOS 4 d; no open conversions; 27% had postoperative complications (5.4% Clavien-Dindo grade III); median follow-up 24 months[12] |
In a prospective series of 13 women with endometriosis-related hydronephrosis, psoas hitch with ureteroneocystostomy did not appear to affect urodynamic parameters adversely, and bladder capacity was normal at 3 months. Two women had transient stress incontinence.[13]
Boari Flap
Concept
The Boari flap creates a full-thickness anterior bladder wall flap, rotates it cranially, and tubularizes it into a bladder-based neo-ureter. The flap can bridge a much longer defect than psoas hitch alone, especially when combined with psoas hitch and selective downward nephropexy.[4][7][14]
Step-by-step technique
- Prepare the ureter. Mobilize only as much proximal ureter as needed, debride scarred or ischemic tissue, and spatulate the ureter.
- Fully mobilize the bladder. Release the bladder from the anterior pelvis and lateral attachments; decide whether contralateral superior vesical pedicle division is needed.
- Perform psoas hitch when useful. Hitching first stabilizes the bladder and shows the true residual gap.
- Design the flap. Mark a wide-based anterior bladder flap. A broad base preserves vascularity; narrow flaps risk ischemia and stricture. Reach can be estimated before marking by distending the bladder with saline (described variously as 200-300 mL or 250-300 mL through the Foley catheter) and bringing the healthy ureteral stump toward the bladder dome; one description adds using a tape measure at this point to gauge the ureter-to-posterior-bladder-wall distance.[22][23] After completing the anastomosis, the bladder is filled to test for leakage.[22][23]
- Open the bladder and raise the flap. Raise a full-thickness mucosa-plus-detrusor flap sized to reach the ureter without tension.
- Create the ureter-flap anastomosis. Anastomose the spatulated ureter to the cranial flap end over a stent, using fine absorbable suture.
- Add antireflux design selectively. A submucosal tunnel or mucosal flap modification can be used when reflux prevention is important and tissue geometry permits.
- Tubularize the flap. Close the flap around the stent with running or interrupted absorbable suture, avoiding narrowing or twisting.
- Close the bladder donor site. Close the bladder in two layers and test for watertight closure.
- Drain. Leave Foley catheter, ureteral stent, and a closed suction drain; many surgeons obtain cystography before catheter removal in large flaps or hostile fields.
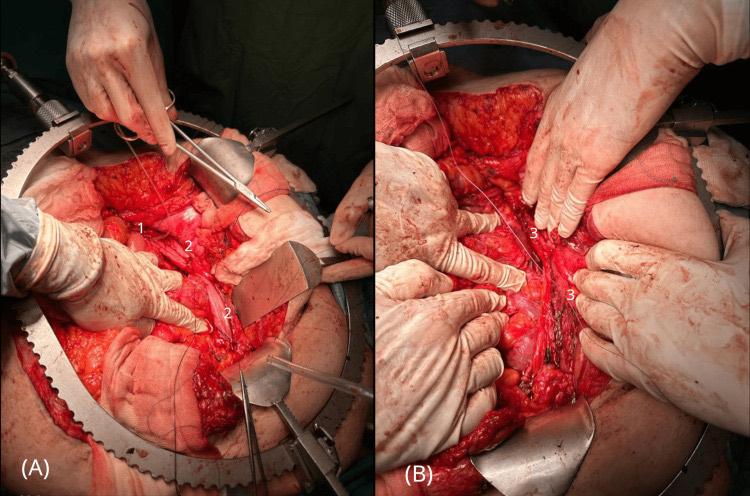
Open Boari flap reconstruction after injury to the proximal ureter. (A) The proximal ureter with a Nelaton stent in place (1) and the Boari flap before closure (2). (B) The Boari flap after closure (3). From Stępka JT, et al. Cureus. 2024;16(8):e66522, Figure 4 (CC BY 4.0).[31]
Flap design
The flap must be wide, well vascularized, and long enough before tubularization. Practical design rules:
- keep a generous base-to-length ratio,
- avoid a narrow distal flap tip,
- ensure the flap reaches the ureter before committing to tubularization,
- tubularize over a stent without twisting,
- preserve bladder capacity and avoid excessive anterior wall harvest,
- limit bladder dissection on the side where the flap is planned, to reduce ischemia risk before mapping the flap.
Reported numeric design values vary by author and are not a single validated rule: a base at least 4 cm wide and a tip at least 3 cm wide with a length-to-base ratio no greater than 3:1, adding 3-4 cm when a submucosal antireflux tunnel is planned, has been described independently in two chapters[22][24]; a separate description sizes the flap to about 1.5 times the estimated bridge length with a distal edge 4-5 cm wide, after preserving a 3-4 mm periureteral tissue sheath during ureteral mobilization[23]; and another chapter describes a length-to-base ratio of 2:1.[25]
Simmons and Gill described laparoscopic Boari modifications, including mucosal flaps to improve anastomotic circumference and support the suture line.[14]
Outcomes
| Study | N | Approach | Key Result |
|---|---|---|---|
| Wenske 2013 | 18 Boari cases | Open | The abstract reports outcomes for the whole 100-case series (hydronephrosis resolved in 81%), not the Boari subgroup[2] |
| Mauck 2011 | 20 Boari flaps among 29 procedures in 27 patients | Open | Failure was 17% in the proximal-third group versus 12% in the distal-two-thirds group, across reconstruction types. Nephropexy was used in 58% versus 12%; mean follow-up was 11.4 months.[7] |
| Dell'Oglio 2021 | 7 robotic Boari flaps within a 37-case series | Robotic | The retrospective series reports feasibility and perioperative morbidity for Boari flap and psoas hitch combined[12] |
| Corse 2023 | 50 | Robotic | Prospective multi-institutional database; 90% (45/50) success at median follow-up 15 months, all 5 failures within 2 months[15] |
| Hardesty 2024 | 29 women | Retrospective | 6.9% (2/29) developed ureteral stricture; 27.6% (8/29) had new-onset LUTS after Boari reconstruction; mean follow-up 22.3 months[8] |
| Xu 2025 | 76 mixed robotic reimplants with or without psoas hitch or Boari flap | Robotic | Overall, 94.5% met a composite of symptom relief, stable or improved hydronephrosis, and preserved renal function at median 13.9 months; the abstract gives no Boari-specific success rate. Eleven patients had reflux-related symptoms and none required secondary surgery.[16] |
Bladder Z-Plasty (Experimental)
Cormio and colleagues developed bladder Z-plasty to lengthen the bladder further than a psoas hitch can, for ureteric gaps a hitch alone will not bridge. The technique uses a Z-shaped incision of the bladder wall and was first tested on isolated pig bladders.[29]
In sheep, 6 animals underwent Z-plasty and 5 underwent psoas hitch. Z-plasty was as safe and gave a longer elongation, on average 5.8 cm more than the hitch, with no complications and no change in bladder capacity.[29][30] No human series has been published. The 2026 semi-live case under Videos shows the operation in a patient. Treat it as an investigational alternative to the Boari flap, supported by animal data only.
Downward Nephropexy
When Boari flap reach remains marginal, downward nephropexy mobilizes the kidney and secures it in a lower position, reducing the ureteral gap from above.[7][17]
Use cases:
- upper ureteral or lumbar-level defects,
- failed prior reconstruction with shortened ureter,
- Boari flap that reaches only under tension,
- reconstruction where renal pelvis dissection is hostile but kidney mobility is available.
Downward nephropexy can add several centimeters of reach, but it marks a higher-complexity reconstruction. In one single-surgeon series, proximal-third reconstructions, which more often included nephropexy (58% vs 12%), had longer hospital stay (8.0 vs 4.4 days) and greater blood loss (447 vs 224 mL) than reconstructions of the distal two-thirds of the ureter, with similar failure rates (17% vs 12%).[7]
Robotic Approach
Psoas hitch and Boari flap have been performed robotically. The demanding steps are deep pelvic suturing, bladder mobilization, tubularization, and ureterovesical anastomosis.[12][15][16]
Common robotic sequence:
- Identify the ureter and define healthy proximal margin.
- Mobilize the bladder and assess direct reach.
- Add psoas hitch if direct reach is tight.
- Decide whether Boari flap is required after the hitch.
- Use ICG selectively to define ureteral perfusion and flap viability.
- Complete stented ureterovesical or ureteroflap anastomosis.
- Close bladder or flap and test watertightness.
In robotic reconstruction, intraluminal ICG via a nephrostomy or retrograde catheter can aid ureteral localization, whereas intravenous ICG may help assess ureteral blood supply and perfusion of vascularized reconstructive tissue. ICG retained on the urothelium after intraluminal delivery can compromise later intravenous assessment of ureteral vascularity.[18]
Complications
| Complication | Mechanism / Pattern | Prevention |
|---|---|---|
| Anastomotic stricture | Ischemia, tension, narrow anastomosis, tight tunnel, radiated tissue | Preserve adventitia, debride to healthy ureter, spatulate, avoid tension |
| Urine leak / urinoma | Non-watertight closure, distal obstruction, stent malfunction | Stent, bladder drainage, watertight test, drain near repair |
| Persistent hydronephrosis | Edema, reflux, stricture, aperistalsis | Trend imaging; investigate worsening or symptomatic obstruction |
| UTI / pyelonephritis | Stent, reflux, residual obstruction, colonized urine | Pre-op culture strategy, stent removal, evaluate obstruction |
| Reflux symptoms | Refluxing adult reimplant or imperfect antireflux geometry | Counsel; treat only clinically meaningful cases |
| Genitofemoral neuralgia | Hitch suture or dissection on anterior psoas | Identify nerve trajectory; avoid nerve in hitch bites |
| Reduced bladder capacity / LUTS | Boari flap harvest, radiation, baseline bladder dysfunction | Pre-op bladder assessment; avoid excessive flap harvest |
| Flap ischemia | Narrow base, over-tension, radiated bladder | Broad base, perfusion assessment, alternate reconstruction if tissue poor |
Boari flap reconstruction is associated with new lower urinary tract symptoms. In a retrospective cohort of 29 women (urothelial carcinoma excluded), new-onset LUTS occurred in 27.6% and was managed with oral anticholinergics.[8] This belongs in preoperative counseling, particularly when the indication is benign.[8] A separate retrospective bladder-flap cohort analyzed 81 of 95 patients (median follow-up 2.3 years): 12/81 (15%) had new persistent bladder-medication use, 9/81 (11%) had flank pain related to reflux, and 56/81 (69%) completed the postoperative symptom survey.[35]
When Bladder-Based Reconstruction Is Not Enough
If psoas hitch, Boari flap, and downward nephropexy cannot create a durable tension-free repair, the surgeon should leave the bladder ladder rather than forcing it.[10][19][20]
Next options include:
- Buccal mucosa graft ureteroplasty for long strictures with a usable ureteral plate,
- appendiceal flap or appendiceal interposition for selected right-sided defects,
- transureteroureterostomy when the contralateral ureter is healthy and reachable,
- ileal ureter replacement for long-segment or full-length defects,
- renal autotransplantation when bowel is undesirable or anatomy demands pelvic relocation of the renal unit,
- nephrectomy when function is poor and reconstruction risk outweighs benefit.
Ileal ureter can also be combined with Boari flap-psoas hitch for full-length defects, using bladder reach to reduce bowel length and preserve upper-tract drainage.[19]
Operative Pearls
- Assess bladder before ureter. Capacity, compliance, mobility, and radiation history determine whether psoas hitch or Boari flap is even fair to the patient.
- Hitch before flap when the gap is borderline. The hitch shows how much defect remains.
- Never hitch across the genitofemoral nerve. Postoperative neuralgia is avoidable.
- Keep the ureter straight. A tension-free anastomosis can still fail if the ureter kinks at bladder entry.
- Make the Boari base generous. A narrow flap is a future ischemic stricture.
- Do not harvest a flap that the bladder cannot afford. Storage morbidity is a reconstructive complication.
- Use nephropexy deliberately. It is useful reach, but it signals a complex upper-ureter reconstruction.
- Escalate early when tissue is hostile. Radiated, infected, or multiply reoperative fields may be better served by delayed reconstruction or non-bladder substitution.
Videos
References
1. White C, Stifelman M. Ureteral reimplantation, psoas hitch, and Boari flap. J Endourol. 2020;34(S1):S25-S30. doi:10.1089/end.2018.0750
2. Wenske S, Olsson CA, Benson MC. Outcomes of distal ureteral reconstruction through reimplantation with psoas hitch, Boari flap, or ureteroneocystostomy for benign or malignant ureteral obstruction or injury. Urology. 2013;82(1):231-236. doi:10.1016/j.urology.2013.02.046
3. Manassero F, Mogorovich A, Fiorini G, et al. Ureteral reimplantation with psoas bladder hitch in adults: a contemporary series with long-term followup. ScientificWorldJournal. 2012;2012:379316. doi:10.1100/2012/379316
4. Andrade C, Narducci F, Bresson L, Leblanc E. Boari flap ureteroneocystostomy in an oncological patient. Gynecol Oncol. 2016;143(1):193. doi:10.1016/j.ygyno.2016.07.115
5. Riedmiller H, Becht E, Hertle L, Jacobi G, Hohenfellner R. Psoas-hitch ureteroneocystostomy: experience with 181 cases. Eur Urol. 1984;10(3):145-150. doi:10.1159/000463777
6. Middleton RG. Routine use of the psoas hitch in ureteral reimplantation. J Urol. 1980;123(3):352-354. doi:10.1016/S0022-5347(17)55931-5
7. Mauck RJ, Hudak SJ, Terlecki RP, Morey AF. Central role of Boari bladder flap and downward nephropexy in upper ureteral reconstruction. J Urol. 2011;186(4):1345–1349. doi:10.1016/j.juro.2011.05.086
8. Hardesty JK, Burns RT, Soyster ME, Jansen NE, Mellon M. Female bladder dysfunction following Boari bladder flap ureteral reconstruction. Urology. 2024;186:31-35. doi:10.1016/j.urology.2024.01.020
9. Sutherland RS, Pfister RR, Koyle MA. Endopyelotomy associated ureteral necrosis: complete ureteral replacement using the Boari flap. J Urol. 1992;148(5):1490-1492. doi:10.1016/S0022-5347(17)36946-X
10. de'Angelis N, Schena CA, Marchegiani F, et al. 2023 WSES guidelines for the prevention, detection, and management of iatrogenic urinary tract injuries during emergency digestive surgery. World J Emerg Surg. 2023;18(1):45. doi:10.1186/s13017-023-00513-8
11. Mathews R, Marshall FF. Versatility of the adult psoas hitch ureteral reimplantation. J Urol. 1997;158(6):2078-2082. doi:10.1016/S0022-5347(01)68160-6
12. Dell'Oglio P, Palagonia E, Wisz P, et al. Robot-assisted Boari flap and psoas hitch ureteric reimplantation: technique insight and outcomes of a case series with at least 1 year of follow-up. BJU Int. 2021;128(5):625-633. doi:10.1111/bju.15421
13. Carmignani L, Ronchetti A, Amicarelli F, et al. Bladder psoas hitch in hydronephrosis due to pelvic endometriosis: outcome of urodynamic parameters. Fertil Steril. 2009;92(1):35-40. doi:10.1016/j.fertnstert.2008.05.034
14. Simmons MN, Gill IS, Fergany AF, Kaouk JH, Desai MM. Technical modifications to laparoscopic Boari flap. Urology. 2007;69(1):175-180. doi:10.1016/j.urology.2006.10.023
15. Corse TD, Dayan L, Cheng N, et al. A multi-institutional experience utilizing Boari flap in robotic urinary reconstruction. J Endourol. 2023;37(7):775-780. doi:10.1089/end.2022.0618
16. Xu L, Yu X, Huang Y, et al. Robot-assisted laparoscopic ureteral reimplantation and Boari flap with anti-reflux technique: do postoperative reflux related symptoms matter? World J Urol. 2025;43(1):716. doi:10.1007/s00345-025-06096-0
17. Hofer MD, Aguilar-Cruz HJ, Singla N, et al. Expanding applications of renal mobilization and downward nephropexy in ureteral reconstruction. Urology. 2016;94:232-236. doi:10.1016/j.urology.2016.04.008
18. Drain A, Jun MS, Zhao LC. Robotic ureteral reconstruction. Urol Clin North Am. 2021;48(1):91-101. doi:10.1016/j.ucl.2020.09.001
19. Zhong W, Du Y, Yang K, et al. Ileal ureter replacement combined with Boari flap-psoas hitch to treat full-length ureteral defects: technique and initial experience. Urology. 2017;108:201-206. doi:10.1016/j.urology.2017.07.014
20. Knight RB, Hudak SJ, Morey AF. Strategies for open reconstruction of upper ureteral strictures. Urol Clin North Am. 2013;40(3):351-361. doi:10.1016/j.ucl.2013.04.005
21. Peard LM, Pope JC IV. Ureteroneocystostomy. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:276–291.
22. Lai A, Jones R, Chen G, Bowen D. Techniques of ureteral reimplantation. In: Martins FE, Holm HV, Sandhu JS, McCammon KA, eds. Female Genitourinary and Pelvic Floor Reconstruction. Springer; 2023:885–906.
23. Sabnis R, Patil A, Jain PS. Trauma of the ureter. In: Abdel-Gawad M, Ali-El-Dein B, Barry J, Stenzl A, eds. The Ureter: A Comprehensive Review. Springer; 2023:285–300.
24. Attalla K, Sfakianos JP. Injury repair of pelvic ureter. In: Hoffman M, Hull TL, Bochner BH, eds. Major Complications of Female Pelvic Surgery: A Multidisciplinary Approach. Springer; 2025:167–173.
25. Ali-El-Dein B. Ureteral strictures: etiology, diagnosis and treatment. In: Abdel-Gawad M, Ali-El-Dein B, Barry J, Stenzl A, eds. The Ureter: A Comprehensive Review. Springer; 2023:301–368.
26. Morey AF, Broghammer JA, Hollowell CMP, et al. Urotrauma Guideline 2020: AUA Guideline. J Urol. 2021;205(1):30–35. doi:10.1097/JU.0000000000001408. Full guideline, published 2014; amended April 2017 and August 2020.
27. National Comprehensive Cancer Network. NCCN Clinical Practice Guidelines in Oncology: Bladder Cancer. Version 3.2026. August 6, 2026. BL-B 4 of 4; UTT-3; Discussion MS-45 (distal ureterectomy and reimplantation). Guideline.
28. Coleman JA, Clark PE, Bixler BR, et al. Diagnosis and Management of Non-Metastatic Upper Tract Urothelial Carcinoma: AUA/SUO Guideline. J Urol. 2023;209(6):1071-1081. doi:10.1097/JU.0000000000003480
29. Cormio L, Crovace A, Lacalandra G, Di Bellò A, Selvaggi FP. Bladder Z-plasty for the repair of ureteric injuries. Experimental study in sheep. Br J Urol. 1993;71(6):667-671. doi:10.1111/j.1464-410x.1993.tb16062.x
30. Cormio L. Ureteric injuries. Clinical and experimental studies. Scand J Urol Nephrol Suppl. 1995;171:1-66. PubMed
31. Stępka JT, Konopka M, Olszewski M, et al. Reconstruction of the ureter using the Boari flap and psoas hitch techniques in a patient with damage to the proximal part of the ureter: a case report. Cureus. 2024;16(8):e66522. doi:10.7759/cureus.66522
32. European Association of Urology. EAU Guidelines on Urological Trauma. 2026 ed. Section 4.2.4.b.2.b, Distal ureteral injury. Guideline.
33. Crook TJ, Steinbrecher HA, Tekgul S, Malone PSJ. "Femoral nerve neuropathy following the psoas hitch procedure." J Pediatr Urol. 2007;3(2):145-147. doi:10.1016/j.jpurol.2006.06.009
34. Walasek A, Lin J, Zhao L. "Minimizing variability: Standardized approach to retroperitoneal single-port robot-assisted ureteral reconstruction." UroPrecision. 2024;2(3):82-93. doi:10.1002/uro2.67
35. Findlay BL, Fadel A, Miller AJ, et al. "Urinary quality of life outcomes following bladder flap reconstruction for ureteral strictures." Urology. 2026;211:102-106. doi:10.1016/j.urology.2026.02.017