Downward Nephropexy
Downward nephropexy is the deliberate caudal mobilization and fixation of the kidney as an adjunctive maneuver during upper-ureteral reconstruction to gain effective ureteral length and bridge a defect that would otherwise be too long for tension-free repair. It is conceptually opposite to the historical (upward) nephropexy performed for symptomatic nephroptosis: here the kidney is intentionally displaced lower than its native position.[1][2][3]
For the bladder-flap and psoas-hitch operations it is most often paired with, see Boari Flap & Psoas Hitch. For the upper-tract reconstruction decision matrix, see Upper Tract Reconstruction. For long-segment salvage when reach is inadequate, see Ileal Ureter and Renal Autotransplantation.
Concept
The kidney is mobilized sufficiently to permit caudal displacement and fixation to the posterior abdominal wall or psoas region. The extent of dissection is tailored to the required reach while protecting hilar and periureteral blood supply. The caudal shift shortens the distance from the renal pelvis (or ureteropelvic junction) to the bladder or distal ureteral stump, producing a tension-free anastomosis that would not otherwise be feasible.[1][2]
| Parameter | Value |
|---|---|
| Caudal displacement achieved | Mean 3.3 cm (range 3–5 cm)[1] |
| Use in Hofer cohort | 18/92 (19.6%) upper-tract reconstructions at one center, 2007–2015[1] |
| Approach | Open 83% / Laparoscopic 17%; robotic increasingly described[1][4] |
Indications
Downward nephropexy is reach-extending, used when ureteral length is insufficient for a tension-free anastomosis. Specific scenarios in the largest series:[1][2][4][5]
| Setting | Frequency of nephropexy use |
|---|---|
| Ureterocalicostomy | 71% of cases (5/7; Hofer)[1] |
| Ureteroureterostomy | 33% (4/12)[1] |
| Boari flap | 31% (8/26) in Hofer; in Mauck, nephropexy was added in 58% of proximal-third stricture repairs vs 12% of distal repairs[1][2] |
| Ileal ureter interposition | 8% (1/12)[1] |
| Iatrogenic ureteral avulsion / extensive loss | One case report describes a 15-cm avulsion managed with nephropexy, appendiceal interposition, calycostomy and psoas hitch;[4] renal mobilization with nephropexy and ureteropyelostomy has been described in a neonate with upper ureteral loss[5] |
| Redo reconstruction | ~ two-thirds of patients had a prior failed reconstruction[1] |
Downward nephropexy has been paired with Boari flap, ureterocalycostomy, and ureteroureterostomy for proximal reach problems.[2][3] In one 20-patient robotic series of proximal strictures at least 4 cm long, 2 of 4 ureteroureterostomies with nephropexy recurred within 3 months; this small subgroup warrants caution when choosing that pairing for a long proximal defect.[10]
Surgical Technique
- Renal mobilization. Release attachments needed to obtain reach while preserving the renal hilum, vascular pedicle and periureteral tissue. Routine stripping of all perirenal fat is not a prerequisite; dissection depends on the planned reconstruction.[1]
- Caudal displacement. Translocate the kidney inferiorly. Mean achievable shift is about 3.3 cm (3–5 cm).[1]
- Fixation (nephropexy). Secure the kidney in its lower position to the psoas region or posterior abdominal wall without tension or torsion on the vascular pedicle. A described robotic technique fixes the posterior renal capsule to psoas fascia with absorbable suture; small studies have not compared fixation materials.[1][10]
- Concomitant ureteral reconstruction. Complete the chosen reach-dependent operation (Boari flap, ureteroureterostomy, ureterocalicostomy, appendiceal interposition, or ileal ureter) with the additional length the nephropexy has provided.[1][2][4]
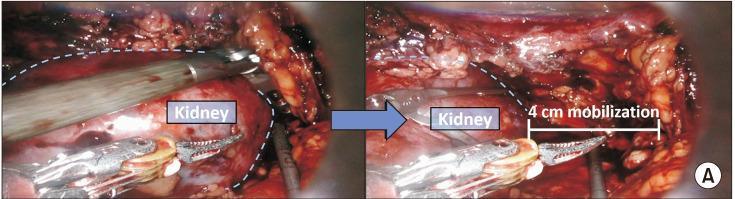
Robotic downward nephropexy: the kidney (outlined by the dashed line) before mobilization (left) and after 4 cm of downward mobilization (right), during reconstruction of a long proximal ureteral stricture. From Lee M, et al. Investig Clin Urol. 2021;62(1):65-71, Fig. 1A (CC BY-NC 4.0).[10]
Outcomes
| Series | n | Setting | Result |
|---|---|---|---|
| Hofer 2016[1] | 18 | Nephropexy with mixed ureteral reconstructions | 16/18 (88.9%) success (Methods: symptom resolution without further intervention; reported in Results as ureteral patency) at mean 50.4 months (range 3–87); 2/18 underwent later nephrectomy for failed reconstruction with persistent symptomatic hydronephrosis. |
| Mauck 2011[2] | 29 procedures in 27 patients; 20 used Boari flaps | 12 proximal vs 17 distal reconstructions; nephropexy in 7/12 vs 2/17 | Failure 17% vs 12% by stricture location at mean follow-up of 11.4 months, not by nephropexy use. Complications 75% vs 35% (p = 0.060) |
| Gn 2018[4] | 1 | Robotic appendiceal interposition + lower-pole calycostomy + downward nephropexy + psoas hitch for 15-cm iatrogenic avulsion | Stable renal function and no obstruction at 6 mo |
The principal trade-offs are renal-vascular safety and whether the additional reach permits durable, tension-free drainage.
Complications and Considerations
- Case complexity. One cohort reported more complications in proximal than distal reconstructions.[2]
- Vascular pedicle injury during renal mobilization is the principal intraoperative risk, so the renal artery and vein are handled gently and preserved.[1]
- Renal ischemia can result from kinking or stretching of the pedicle when the kidney is repositioned; confirm that renal perfusion and venous drainage remain satisfactory after fixation.
- Failure of fixation with cranial migration is a possible late problem; fixation must avoid pedicle tension, torsion and parenchymal injury.
- The available series support feasibility in selected complex reconstructions.[1][2]
Distinction from Traditional (Upward) Nephropexy
The historical operation called "nephropexy" was performed for symptomatic nephroptosis, usually defined radiographically as renal descent of at least 5 cm or two vertebral bodies from supine to upright position, when accompanied by flank pain or intermittent obstruction.[11] In that operation, the kidney is fixed upward toward its normal anatomic position against the posterior abdominal wall or psoas.[6][7][8][9]
Downward nephropexy is the conceptual opposite: the kidney is intentionally displaced caudally and fixed below its native position to facilitate ureteral reconstruction. The two operations share the technique of renal mobilization plus fixation but differ in direction, indication, and reconstructive context.[1][2]
Place in the Reach-Extension Toolkit
For a defect that exceeds primary tension-free anastomosis, the available adjuncts and alternatives include the following:[3]
- Bladder mobilization
- Psoas hitch
- Boari flap (± psoas hitch)
- Downward nephropexy (mean gain 3.3 cm, range 3–5 cm; used in 18/92 [19.6%] ureteral reconstructions in Hofer's cohort)[1]
- Transureteroureterostomy (selected cases)
- Graft repair or bowel reconstruction: Buccal mucosa onlay ureteroplasty for selected long strictures; appendiceal onlay for selected right-sided strictures; appendiceal interposition (right) or ileal ureter for segmental replacement.[4][12][13]
- Renal autotransplantation: for selected extensive ureteral loss or after multiple repair attempts, including when bowel interposition is unsuitable.[14]
Downward nephropexy can accompany the chosen reconstruction whenever renal mobilization safely resolves a reach problem, including redo reconstruction.[1][3]
Key Principles
- Downward nephropexy is a reach-extending adjunct, not a primary reconstruction. It achieves a mean downward renal movement of about 3.3 cm (range 3–5 cm), providing additional reach for ureteral reconstruction.[1]
- Most often paired with Boari flap, ureterocalicostomy, or ureteroureterostomy; less commonly with bowel interposition.[1][2]
- About two-thirds of patients in the largest series were undergoing redo reconstruction; nephropexy is a salvage maneuver in foreshortened anatomy.[1]
- Hofer 2016: 16/18 (88.9%) success, defined in Methods as symptom resolution without further intervention and reported in Results as ureteral patency, at mean 50.4 months (range 3–87); 2/18 underwent later nephrectomy for failed reconstruction.[1]
- Vascular-pedicle preservation during mobilization is the principal safety issue. The kidney is fixed to the psoas or posterior abdominal wall; the published series do not standardize the fixation material.[1]
- Conceptually the opposite of the upward nephropexy used historically for nephroptosis: same anatomic operation, opposite direction and indication.[6][7]
References
1. Hofer MD, Aguilar-Cruz HJ, Singla N, et al. Expanding applications of renal mobilization and downward nephropexy in ureteral reconstruction. Urology. 2016;94:232-236. doi:10.1016/j.urology.2016.04.008.
2. Mauck RJ, Hudak SJ, Terlecki RP, Morey AF. Central role of Boari bladder flap and downward nephropexy in upper ureteral reconstruction. J Urol. 2011;186(4):1345-9. doi:10.1016/j.juro.2011.05.086.
3. Knight RB, Hudak SJ, Morey AF. Strategies for open reconstruction of upper ureteral strictures. Urol Clin North Am. 2013;40(3):351-61. doi:10.1016/j.ucl.2013.04.005.
4. Gn M, Lee Z, Strauss D, Eun D. Robotic appendiceal interposition with right lower pole calycostomy, downward nephropexy, and psoas hitch for the management of an iatrogenic near-complete ureteral avulsion. Urology. 2018;113:e9-e10. doi:10.1016/j.urology.2017.12.005.
5. Redman JF, Lightfoot ML, Reddy PP. Extensive upper and mid ureteral loss in newborns: experience with reconstruction in 2 patients. J Urol. 2002;168(2):691-3. doi:10.1016/s0022-5347(05)64725-8
6. Fornara P, Doehn C, Jocham D. Laparoscopic nephropexy: 3-year experience. J Urol. 1997;158(5):1679-83. doi:10.1016/s0022-5347(01)64093-x.
7. Wyler SF, Sulser T, Casella R, Hauri D, Bachmann A. Retroperitoneoscopic nephropexy for symptomatic nephroptosis using a modified three-point fixation technique. Urology. 2005;66(3):644-8. doi:10.1016/j.urology.2005.03.046.
8. Plas E, Daha K, Riedl CR, Hübner WA, Pflüger H. Long-term followup after laparoscopic nephropexy for symptomatic nephroptosis. J Urol. 2001;166(2):449-52. doi:10.1016/s0022-5347(05)65961-7
9. Gözen AS, Rassweiler JJ, Neuwinger F, et al. Long-term outcome of laparoscopic retroperitoneal nephropexy. J Endourol. 2008;22(10):2263-7. doi:10.1089/end.2008.0365.
10. Lee M, Lee Z, Koster H, Jun M, Asghar AM, Lee R, et al. Intermediate-term outcomes after robotic ureteral reconstruction for long-segment (≥4 centimeters) strictures in the proximal ureter: a multi-institutional experience. Investig Clin Urol. 2021;62(1):65-71. doi:10.4111/icu.20200298.
11. Golab A, Slojewski M, Gliniewicz B, Sikorski A. "Retroperitoneoscopic nephropexy in the treatment of symptomatic nephroptosis with 2-point renal fixation." Surg Laparosc Endosc Percutan Tech. 2009;19(4):356-359. doi:10.1097/SLE.0b013e3181a86753
12. You Y, Gao X, Chai S, et al. "Oral mucosal graft ureteroplasty versus ileal ureteric replacement: a meta-analysis." BJU Int. 2023;132(2):122-131. doi:10.1111/bju.15994
13. Zhang B, Chen J, Chen X, et al. "Laparoscopic ureteroplasty for the treatment of long ureteral strictures with appendiceal interposition and appendiceal onlay flap: technical description and initial experience." World J Urol. 2025;43(1):678. doi:10.1007/s00345-025-06048-8
14. Waterloos M, et al. EAU Guidelines on Urological Trauma. European Association of Urology; limited update March 2026. Section 4.2.4.b.2.c, Long segment ureteral injury. Guideline.