Ileal Ureter
Ileal ureter replacement interposes a vascularized ileal segment between the proximal ureter or renal pelvis and the bladder to reconstruct long-segment ureteral loss. It is a salvage operation for defects that cannot be solved by ureteroureterostomy, ureteral reimplantation, Boari flap / psoas hitch, or oral-mucosa onlay reconstruction.[1][2][3]
Ileum is mobile, vascular, and tubular. Bowel mucosa in the urinary tract produces mucus, absorbs ammonium chloride, secretes bicarbonate, and can cause metabolic acidosis, stones, infection, and long-term nutritional problems.[1][4][5]
For the location-based ladder, see Principles of Upper Tract Reconstruction. For the disease workup, see Ureteral Stricture. For bowel physiology, see Bowel Anatomy, Mucus Management, Vitamin B12 Supplementation, and Urinary Acidifiers & Alkalinizers.
Indications
Ileal ureter is reserved for complex ureteral defects where a durable native repair would be under tension, ischemic, too narrow, or impossible.[1][2][6]
Common indications:
- long-segment or panureteral benign stricture,
- radiation-induced ureteral stricture,
- extensive iatrogenic ureteral injury,
- retroperitoneal fibrosis,
- ureteral loss after oncologic resection; for ureteral urothelial carcinoma, NCCN lists complete ureterectomy with ileal replacement for proximal or mid-ureteral tumors as a nephron-sparing option in highly selected cases, generally with low-grade disease; high-grade lesions are generally managed with nephroureterectomy.[27]
- failed prior pyeloplasty, reimplantation, Boari flap, or endoscopic management,
- bilateral extensive ureteral strictures,
- solitary kidney with a long ureteral stricture when salvage is worth the bowel burden,
- endemic infectious strictures such as tuberculosis or schistosomiasis where relevant.[1][2][3][7]
The threshold question
Before choosing ileal ureter, ask:
- Can the kidney be drained with a simpler native repair?
- Is renal function adequate enough to tolerate bowel in the urinary tract?
- Is usable, non-radiated ileum available?
- Is the bladder a safe low-pressure recipient?
- Would renal autotransplantation or diversion be better for this patient?
Contraindications and Caution Zones
| Problem | Why It Matters |
|---|---|
| Advanced renal insufficiency | Acidosis risk rises when renal acid excretion reserve is poor |
| Short bowel syndrome or major prior ileal resection | Nutritional and diarrheal morbidity may be unacceptable |
| Active inflammatory bowel disease involving ileum | Diseased bowel should not be used as urinary conduit |
| Radiation enteritis or irradiated ileum | High stricture, fistula, and leak risk |
| Uncontrolled UTI or urosepsis | Drain first; reconstruct electively after infection control |
| Small-capacity or high-pressure bladder | Distal implantation into hostile storage threatens the kidney. For selected long ureteral strictures with bladder contracture, simultaneous ileocystoplasty has been described; metabolic acidosis occurred in 10/20 women in one series (median follow-up 20.1 months).[33] |
| Severe hepatic dysfunction | Ammonium reabsorption can rarely contribute to encephalopathy |
| Poor surgical fitness for bowel anastomosis | Ileal ureter is a major abdominal reconstruction |
The 2026 EAU Urological Trauma guideline states that ileal interposition for long-segment ureteral injury should be avoided in patients with impaired renal function or known intestinal disease.[30] In a 36-patient Yang-Monti series, the authors considered eGFR <40 mL/min/1.73 m² a relative contraindication; this threshold is specific to that selected cohort.[8] The lower the eGFR and serum bicarbonate reserve, the stronger the case for shorter bowel length, a Yang-Monti configuration, renal autotransplantation, diversion, or nephrectomy when renal salvage is not worthwhile.[4][8] One chapter's more conservative selection guidance uses an overall GFR above 60 mL/min and, after nephrostomy decompression, an affected-kidney contribution of at least 20% of overall renal function as thresholds for choosing salvage over nephrectomy.[25]
Preoperative Planning
Preoperative planning defines the defect, the kidney, the bladder, and the bowel.
| Domain | Evaluation | Purpose |
|---|---|---|
| Renal function | Serum creatinine, eGFR, electrolytes, bicarbonate, MAG3 split function | Determines salvage value and metabolic reserve |
| Anatomy | CT urogram, MR urogram, antegrade/retrograde pyelography | Defines stricture length, laterality, renal pelvis target, and bladder reach |
| Drainage status | Nephrostomy, stent history, urine culture | Controls infection and lets inflammation settle before reconstruction |
| Bladder | Cystoscopy, capacity assessment, urodynamics selectively | Confirms safe distal reservoir |
| Bowel | Prior resections, radiation fields, IBD history, nutritional risk | Confirms usable non-radiated ileum |
| Metabolic baseline | Bicarbonate, chloride, potassium, B12 when relevant | Creates postoperative comparison |
Preoperative CT can estimate required ileal segment length, but final segment choice is made intraoperatively after the ureter is debrided to healthy tissue and the bladder and kidney are mobilized.[9]
Standard Ileal Ureter Technique
The standard operation uses a non-reconfigured ileal segment, usually 15-25 cm for unilateral reconstruction and longer for bilateral or panureteral defects.[1][2][5]
Step sequence
- Expose and stage the ureter. Identify the diseased segment, preserve any usable periureteral blood supply, and debride to healthy ureter or renal pelvis.
- Prepare the proximal target. Spatulate the proximal ureter or open the renal pelvis for a wide ileoureteral or ileopyelostomy anastomosis.
- Select ileum. Choose a mobile, well-vascularized ileal segment while preserving the terminal ileum when possible to protect bile-salt and B12 absorption.
- Harvest on mesentery. Isolate the segment on an intact mesenteric pedicle and confirm reach without twisting.
- Restore bowel continuity. Perform stapled or hand-sewn ileoileostomy and close the mesenteric defect. Some surgeons instead leave the mesenteric defect open as a matter of practice, including with the Yang-Monti segment; no comparative internal-hernia outcome has been reported for either approach, so closing the defect remains the safer default absent such data.[25]
- Orient isoperistaltically. Place the oral end proximally and the aboral end distally so intestinal peristalsis supports antegrade urine transport.
- Perform proximal anastomosis. Sew ileum to renal pelvis or proximal ureter with absorbable suture over a stent. An intraoperative leak check has been described: fill the renal pelvis with saline through the nephrostomy after completing the proximal anastomosis to look for extravasation.[25]
- Perform distal anastomosis. Implant the distal ileum into the bladder, usually refluxing unless antireflux reconstruction is specifically indicated. An analogous distal check fills the bladder with saline through the urethral or suprapubic catheter to check the distal anastomosis for leak.[25]
- Stent and drain. Provide intraluminal urinary drainage and Foley drainage; use an intra-abdominal drain according to the repair. No consensus device-removal schedule applies across reported series. In one robotic case report, the Foley catheter was removed on postoperative day 10 after a normal cystogram and a single intraluminal 15 Ch drain was removed endoscopically at four weeks; no intra-abdominal drain was placed.[24]
- Retroperitonealize when possible. Route the ileal ureter along the natural ureteral course while avoiding mesenteric tension, kinking, and internal hernia.
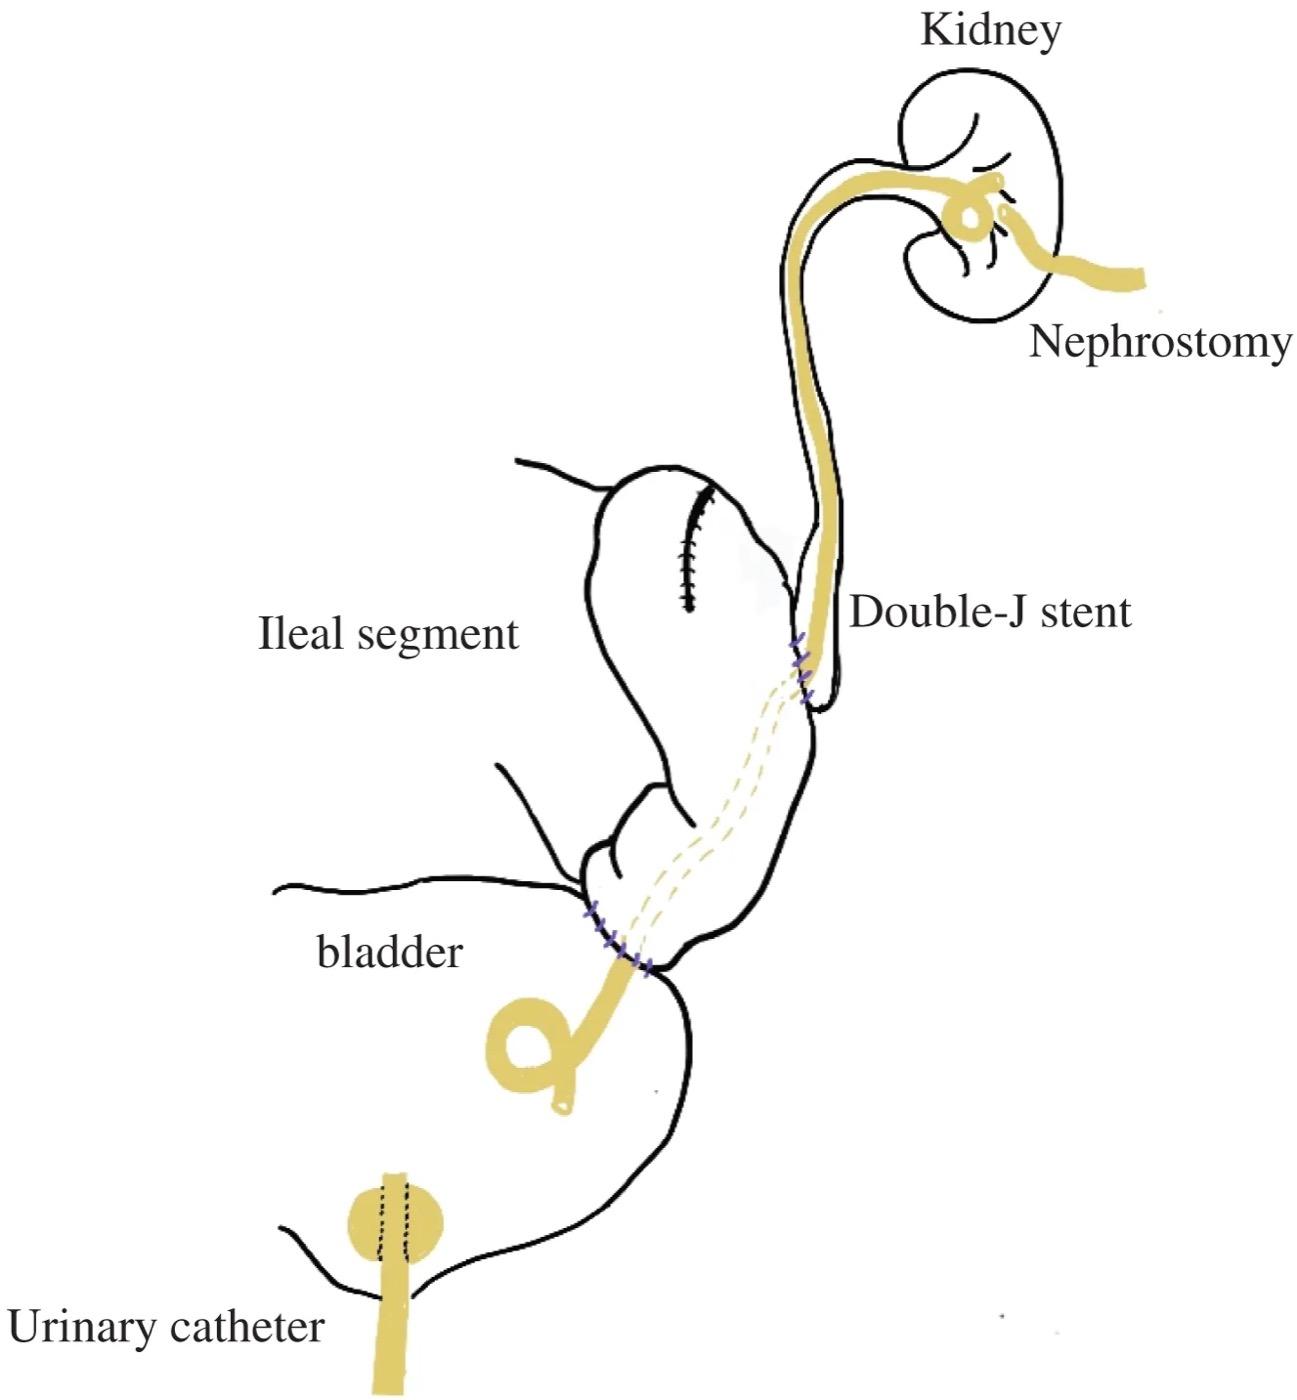
Schematic of a completed ileal ureter interposition after distal ureterectomy for ureter-invading recurrent rectal cancer. The ureter is anastomosed end-to-side to the side wall of an isoperistaltic interposed ileal segment, which is joined end-to-side to the bladder; a double-J stent crosses the ureteroileal anastomosis and runs through the segment into the bladder, with a nephrostomy and urinary catheter in place. The ileovesical anastomosis was hand-sewn under direct vision through the Pfannenstiel extraction incision with a single-layer running 3-0 polyglactin suture. From Yamamoto T, et al. Surg Case Rep. 2026;12(1):cr.26-0394, Fig. 3 (CC BY 4.0).[28]
Positioning and Room Setup
Ileal ureter substitution requires access to the upper tract and bowel, plus the bladder when ileovesical implantation is planned. Repositioning is described in two robotic case reports, whereas a single-position laparoscopic series comprised six women, including three with abdominal-wall ostomies.[9][24][37] One robotic case report of complete ureteral avulsion needed a change from the initial lateral decubitus position to supine and back to lateral decubitus to complete the renal, bowel, and bladder portions of the reconstruction (operative time approximately 300 minutes).[24] A separate robotic case report used preoperative CT measurement to estimate the needed ileal length and completed the operation with one position change, illustrating how planning can limit repositioning.[9] Ileal ureter is a major abdominal reconstruction with a bowel anastomosis and potentially prolonged operative time. The 2024 ESAIC urology guideline does not specify an ileal-ureter regimen; use the VTE Prophylaxis framework to assess procedure and approach, bleeding risk, age, obesity, prior VTE, malignancy, operative duration, and mobility.[35]
Key technical rules
- Use the shortest segment that reaches without tension. Bowel length is metabolic surface area.
- Preserve terminal ileum when possible. This protects B12 and bile-salt absorption.
- Avoid mesenteric twist. A perfect anastomosis fails if the ileal segment is ischemic or kinked.
- Spatulate generously. Anastomotic stricture usually starts with ischemia, tension, or caliber mismatch.
- Control dead space. Urine leak near bowel and retroperitoneum can become abscess or fistula.
Yang-Monti Ileal Ureter
The Yang-Monti modification uses a short ileal segment that is divided, detubularized, and retubularized transversely into a longer narrow tube. It reduces bowel length and mucosal surface area while producing a caliber closer to ureter.[8][10]
Concept
- Isolate 5-7.5 cm of ileum.
- Divide into two or three short segments.
- Incise each segment longitudinally along a paramesenteric line, preserving the mesenteric blood supply.[10]
- Retubularize the opened plates into a longer narrow tube over a catheter.
- Interpose the reconstructed tube as a neo-ureter.
- As an approximate planning guide, one 2-3 cm bowel segment yields roughly 8-10 cm of reconfigured tube, with additional segments joined in series when more length is needed.[25]
Advantages
- far less bowel used than standard ileal ureter,
- less mucus surface area,
- lower expected metabolic burden,
- suitable caliber for submucosal tunneling,
- useful in solitary kidney or mild-moderate CKD when defect length permits.[8][10]
In the long-term Yang-Monti series, renal function parameters improved overall and metabolic complications were not observed, but patients with more advanced CKD (stage 3 in four cases) still deteriorated.[8]
Other Modifications
Tapered ileal ureter
Tapering reduces the diameter of a standard ileal segment to reduce urinary stasis and make antireflux implantation easier. The trade-off is more bowel manipulation, a longer staple or suture line, and potential ischemia.
Ileal onlay flap
When a ureteral plate remains usable, detubularized ileum can be used as an onlay rather than circumferential replacement. This preserves native ureteral blood supply and reduces the amount of bowel mucosa exposed to urine. In a 16-ureter series combining seven reconfigured intestinal interpositions, seven intestinal onlays, and two appendiceal onlays, drainage with preserved function was reported in 14 remaining renal units at mean 44 months; patients reported minor mucus production.[11]
Combined Boari / ileal ureter
For full-length defects, a Boari flap with psoas hitch can bridge the distal gap while a shorter ileal segment bridges the proximal gap. This reduces the total ileal length needed and can preserve bladder-based distal reconstruction.[12]
Downward nephropexy
Downward nephropexy mobilizes the kidney caudally to reduce the remaining gap. It is useful when an ileal or Boari-based reconstruction almost reaches but would otherwise be under tension.[13][14]
Antireflux Strategy
Whether the distal ileovesical anastomosis needs an antireflux mechanism is debated.[5][15][16]
Refluxing anastomosis
Arguments for refluxing implantation:
- technically simpler,
- lower distal obstruction risk,
- acceptable when implanting into a normal low-pressure native bladder,
- long ileal segments may damp visible reflux through bowel peristalsis and capacitance.[5][16]
The largest single-center series concluded that reflux prevention is of minor importance when the native bladder is the recipient, but more important when implanting into an intestinal reservoir.[5]
Antireflux anastomosis
Arguments for antireflux implantation:
- recurrent pyelonephritis concern,
- an intestinal reservoir recipient after confirming safe storage pressures,
- solitary kidney or vulnerable renal unit,
- pediatric or young patient with long expected exposure.
An antireflux mechanism does not make a high-pressure bladder safe, so storage dysfunction is addressed before distal implantation. Distal antireflux designs include submucosal tunneling and a nipple valve; Bonfig et al. described serous-lined extramural tunneling or distal intussusception into an intestinal reservoir.[1][15] Xu et al. described a separate proximal iliopsoas tunnel at the ureter-to-ileum junction, with the distal ileum joined end-to-side to the bladder.[17] Antireflux designs carry a risk of obstruction.
Outcomes
| Study | N | Follow-up | Key Findings |
|---|---|---|---|
| Chung 2006 | 56 | Mean 6 yr | Long-term bowel-replacement series; renal function and reintervention require continued surveillance[3] |
| Armatys 2009 | 91 | Mean 36 mo | 74.7% stable/decreased creatinine; 3.3% anastomotic stricture and 6.6% fistula[18] |
| Kocot 2017 | 157 | Mean 54.1 mo | 25-year single-center experience; creatinine stable or improved in most patients[5] |
| Roth 2017 | 108 | Median 51 mo | 82.4% stable/improved renal function; bilateral repair increased renal-deterioration risk[6] |
| Launer 2021 | 46 | Mean 4.4 yr | 83% success (no further open intervention); 24% major complication rate[2] |
| Ali-El-Dein 2021 | 36 | Median 68 mo | Yang-Monti: improved eGFR overall, no metabolic complications reported[8] |
| Yang 2023 | 15 | Median 14 mo | Totally intracorporeal robotic unilateral/bilateral ileal ureter feasible; functional success 86.7%[19] |
| Ji 2026 | 48 operated; 36 with ≥6 mo follow-up | Median 24 mo in evaluable cohort | Success 33/36 (91.7%); major 30-day complications 9/48 (18.8%)[20] |
| Wang 2026 | 82 | Median 48 mo clinical; SF-36 at 12 mo | Prospective single-arm cohort: among 79 SF-36 respondents at 12 mo, 46.8–74.7% improved by ≥10 SF-36 points from baseline, depending on domain; 1 radiographic reobstruction and 8 grade III–IV complications[29] |
The series measure different endpoints: creatinine was stable or decreased in 68/91 at mean 36 months, 38/46 required no further open surgery at mean 4.4 years, and 33/36 evaluable patients met a symptom, obstruction, and intervention composite at median 24 months.[18][2][20] Major complications occurred in 11/46 (24%) in the Launer series.[2]
Robotic Ileal Ureter Replacement
Robotic intracorporeal ileal ureter replacement has been reported in single-center and multi-institutional series from high-volume reconstructive centers.[19][20][21]
Totally intracorporeal sequence
- Position to access kidney and ureter, bowel, and bladder; port strategy depends on unilateral versus bilateral reconstruction.
- Identify diseased ureter and debride to healthy proximal target.
- Measure the defect after mobilization and adjunctive bladder and kidney maneuvers.
- Harvest ileum intracorporeally.
- Restore bowel continuity with intracorporeal stapled or hand-sewn anastomosis.
- Orient the ileal segment isoperistaltically.
- Complete proximal ileopyelostomy or ileoureterostomy.
- Complete distal ileovesicostomy.
- Place stents, Foley, and drains.
Extracorporeal segment preparation
Some robotic cases use a small extraction incision for ileal harvest and preparation, then return the segment for robotic urinary anastomoses. This can reduce intracorporeal bowel time while preserving minimally invasive urinary reconstruction.[22]
Bilateral configurations
Bilateral reconstructions may use:
- one long U-shaped ileal segment, with one antiperistaltic limb,[36]
- reverse-7 or asymmetric configuration,
- separate ileal segments,
- a "cat-tail" configuration: a single ileal segment (described as approximately 15 cm, and elsewhere in the same source as 15-20 cm) passed through the sigmoid mesentery toward the left renal pelvis and joined end-to-end to the healthy left ureter, with the right ureter joined end-to-side roughly 8-10 cm distal to that anastomosis and the distal ileum joined to the bladder,[26]
- ileal segment plus Boari and psoas adjuncts depending on bladder and defect geometry.[7][19][22]
The cat-tail configuration is an author-described option for simultaneous bilateral long-segment replacement without a reported comparison against the other bilateral layouts above.[26]
In the 2026 multi-institutional robotic series, 48 patients underwent robotic intracorporeal ileal ureter replacement across three institutions; 35.4% were bilateral and 41.7% had prior radiation. Major 30-day complications occurred in 9/48 (18.8%), including urinary anastomotic leaks in 5/48 (10.4%).[20] Study-defined surgical success—no flank pain or ureteral obstruction on functional imaging and/or endoscopy, and no related operative intervention—was 33/36 (91.7%) among patients with at least six months of follow-up.[20] All three observed failures occurred in the radiation subgroup.[20]
Complications
| Complication | Mechanism | Prevention / Management |
|---|---|---|
| Hyperchloremic metabolic acidosis | Ileum absorbs ammonium chloride and secretes bicarbonate | Use shortest bowel length, monitor bicarbonate/chloride, oral alkali |
| Mucus obstruction | Ileal mucosa continues mucus secretion | Hydration, irrigation when needed, endoscopic clearance rarely |
| Anastomotic stricture | Ischemia, tension, caliber mismatch, radiation | Wide spatulation, healthy margins, tension-free routing |
| Urinary leak / fistula | Anastomotic leak, distal obstruction, infected field | Stents, Foley drainage, drains, delayed reconstruction after sepsis |
| UTI / pyelonephritis | Reflux, stasis, mucus, colonization | Treat symptomatic infection; evaluate obstruction or reflux if recurrent |
| Small bowel obstruction | Adhesions or internal hernia | Close mesenteric defects; manage conservatively or surgically |
| Worsening renal function | Baseline CKD, bilateral repair, infection, obstruction, acidosis | Careful selection, lifelong monitoring, early obstruction workup |
| Stones | Mucus, infection, urinary stasis | Surveillance imaging, treat infection/stasis |
| B12 deficiency / bile-salt diarrhea | Terminal ileal loss | Preserve terminal ileum; monitor and supplement |
Hyperchloremic metabolic acidosis is a long-term complication. Kocot et al.'s retrospective series (157 patients; 79 native-bladder, 70 intestinal-reservoir, and 8 ileal-conduit recipients; mean follow-up 54.1 months) reported a 19.5% overall rate; 15/79 (18.9%) native-bladder patients needed permanent sodium bicarbonate.[5] Chronic acidosis can worsen bone health and potassium balance, and patients with reduced renal function have less reserve to compensate.[4]
Alternatives
| Option | Best Fit | Why It May Beat Ileal Ureter |
|---|---|---|
| Psoas hitch | Lower/mid ureteral defect | No bowel in urine; lower metabolic burden |
| Boari flap | Mid/upper defect with good bladder | Uses bladder tissue instead of bowel |
| Buccal mucosa graft ureteroplasty | Long nonobliterative stricture with ureteral plate | Avoids bowel anastomosis and metabolic complications |
| Appendiceal interposition/onlay | Right-sided moderate defect, normal appendix | No bowel anastomosis; small caliber |
| Transureteroureterostomy | Bladder unavailable, contralateral ureter healthy | Avoids bowel but risks contralateral renal unit |
| Renal autotransplantation | Long proximal/panureteral disease when bowel use is unsuitable | Avoids bowel mucosa; adds transplant-level vascular risk[1][23] |
| Diversion or nephrectomy | Poor bladder, poor renal function, unsafe reconstruction | May be safer than heroic salvage |
An eight-center retrospective study compared 15 robotic ileal replacements with 39 robotic renal autotransplants for long ureteric strictures. Thirty-day complications occurred in 73% versus 31%, with Clavien-Dindo grade III or higher events in 13% versus 10%; ileal patients were older, had more comorbidity, and had lower baseline eGFR. Choice depends on bowel suitability, vascular anatomy, renal function, prior radiation, and center expertise.[23]
Surveillance
Ileal ureter patients need long-term functional and metabolic follow-up. When replacement follows ureteral urothelial carcinoma resection, add risk-adapted oncologic surveillance with cystoscopy and upper-tract imaging; the 2026 EAU UTUC follow-up recommendations are weak and vary by tumor risk.[32]
| Surveillance | Typical Interval | Why |
|---|---|---|
| Serum creatinine / eGFR | Every 6-12 mo | Detect obstruction, infection-related injury, CKD progression |
| Electrolytes, bicarbonate, chloride, potassium | Every 6-12 mo | Detect hyperchloremic metabolic acidosis |
| Renal ultrasound or CT/MR urography | At least annually early; individualized long term | Detect hydronephrosis, stones, mucus obstruction |
| MAG3 renography | Symptoms, worsening imaging, solitary kidney, uncertain drainage | Functional obstruction assessment |
| Vitamin B12 | Annually if terminal ileum or longer ileal length used | Detect delayed deficiency |
| Bone health | Consider with chronic acidosis | Acidosis can worsen bone buffering and mineral loss |
| Urine culture | Symptoms or before mucosa-breaching instrumentation | Avoid routine treatment of asymptomatic bacteriuria outside established exceptions |
Operative Pearls
- Use ileal ureter late. Tension-free native, bladder-based, and onlay options come first.
- Radiation strictures. When ileal replacement is chosen, select a well-vascularized ileal segment outside the radiation field.[18][34]
- Keep the segment short. Every extra centimeter is more mucus and metabolic surface area.
- Preserve terminal ileum.
- Orient isoperistaltically. Peristalsis then assists drainage.
- Bilateral renal outcomes. A 108-patient retrospective series associated bilateral repair with worsening renal function (HR 3.7), whereas a later 158-patient series from the same institution found no significant association. Continue renal and metabolic surveillance after bilateral reconstruction.[6][31]
- Radiation. All three failures in the 2026 multi-institutional series occurred after radiation; counsel accordingly.
- Antireflux is context-dependent. In Kocot et al.’s 157-patient series (79 native bladders, 78 intestinal reservoirs), the authors considered reflux prevention of minor importance with native-bladder implantation and recommended antireflux implantation for intestinal reservoirs.[5]
- Metabolic surveillance is part of the operation. Follow-up continues after the stent is removed.
Videos
References
1. Xiong S, Zhu W, Li X, et al. Intestinal interposition for complex ureteral reconstruction: a comprehensive review. Int J Urol. 2020;27(5):377-386. doi:10.1111/iju.14222
2. Launer BM, Redger KD, Koslov DS, et al. Long-term follow up of ileal ureteral replacement for complex ureteral strictures: single institution study. Urology. 2021;157:257-262. doi:10.1016/j.urology.2021.07.012
3. Chung BI, Hamawy KJ, Zinman LN, Libertino JA. The use of bowel for ureteral replacement for complex ureteral reconstruction: long-term results. J Urol. 2006;175(1):179-183. doi:10.1016/S0022-5347(05)00061-3
4. Roth JD, Koch MO. Metabolic and nutritional consequences of urinary diversion using intestinal segments to reconstruct the urinary tract. Urol Clin North Am. 2018;45(1):19-24. doi:10.1016/j.ucl.2017.09.007
5. Kocot A, Kalogirou C, Vergho D, Riedmiller H. Long-term results of ileal ureteric replacement: a 25-year single-centre experience. BJU Int. 2017;120(2):273-279. doi:10.1111/bju.13825
6. Roth JD, Monn MF, Szymanski KM, Bihrle R, Mellon MJ. Ureteral reconstruction with ileum: long-term follow-up of renal function. Urology. 2017;104:225-229. doi:10.1016/j.urology.2017.02.026
7. Kim A, Nam W, Song SH, Jeong IG, Hong B. Use of the ileum for ureteral stricture and obstruction in bilateral, unilateral, and single-kidney cases. Urology. 2018;111:203-207. doi:10.1016/j.urology.2017.08.008
8. Ali-El-Dein B, El-Hefnawy AS, D'Elia G, et al. Long-term outcome of Yang-Monti ileal replacement of the ureter: a technique suitable for mild, moderate loss of kidney function and solitary kidney. Urology. 2021;152:153-159. doi:10.1016/j.urology.2020.09.061
9. Baumgarten AS, Shah BB, Patel TB, Wiegand LR. Robotic ileal interposition for radiation-induced ureteral stricture disease. Urology. 2017;104:9-10. doi:10.1016/j.urology.2017.02.033
10. Ali-el-Dein B, Ghoneim MA. Bridging long ureteral defects using the Yang-Monti principle. J Urol. 2003;169(3):1074-1077. doi:10.1097/01.ju.0000050151.66653.cc
11. Ordorica R, Wiegand LR, Webster JC, Lockhart JL. Ureteral replacement and onlay repair with reconfigured intestinal segments. J Urol. 2014;191(5):1301-1306. doi:10.1016/j.juro.2013.11.027
12. Zhong W, Du Y, Yang K, et al. Ileal ureter replacement combined with Boari flap-psoas hitch to treat full-length ureteral defects: technique and initial experience. Urology. 2017;108:201-206. doi:10.1016/j.urology.2017.07.014
13. Mauck RJ, Hudak SJ, Terlecki RP, Morey AF. Central role of Boari bladder flap and downward nephropexy in upper ureteral reconstruction. J Urol. 2011;186(4):1345-1349. doi:10.1016/j.juro.2011.05.086
14. Hofer MD, Aguilar-Cruz HJ, Singla N, et al. Expanding applications of renal mobilization and downward nephropexy in ureteral reconstruction. Urology. 2016;94:232-236. doi:10.1016/j.urology.2016.04.008
15. Bonfig R, Gerharz EW, Riedmiller H. Ileal ureteric replacement in complex reconstruction of the urinary tract. BJU Int. 2004;93(4):575-580. doi:10.1111/j.1464-410X.2003.04672.x
16. Waldner M, Hertle L, Roth S. Ileal ureteral substitution in reconstructive urological surgery: is an antireflux procedure necessary? J Urol. 1999;162(2):323-326. doi:10.1016/s0022-5347(05)68550-3
17. Xu YM, Feng C, Kato H, Xie H, Zhang XR. Long-term outcome of ileal ureteric replacement with an iliopsoas muscle tunnel antirefluxing technique for the treatment of long-segment ureteric strictures. Urology. 2016;88:201-206. doi:10.1016/j.urology.2015.11.005
18. Armatys SA, Mellon MJ, Beck SD, et al. Use of ileum as ureteral replacement in urological reconstruction. J Urol. 2009;181(1):177-181. doi:10.1016/j.juro.2008.09.019
19. Yang K, Wang X, Xu C, et al. Totally intracorporeal robot-assisted unilateral or bilateral ileal ureter replacement for the treatment of ureteral strictures: technique and outcomes from a single center. Eur Urol. 2023;84(6):561-570. doi:10.1016/j.eururo.2023.04.022
20. Ji EJ, Naser-Tavakolian A, Kanabolo DL, et al. Reconstruction of a devastated ureter: multi-institutional experience with robotic intracorporeal ileal ureter replacement. Eur Urol. 2026. doi:10.1016/j.eururo.2026.01.011
21. Ubrig B, Janusonis J, Paulics L, et al. Functional outcome of completely intracorporeal robotic ileal ureteric replacement. Urology. 2018;114:193-197. doi:10.1016/j.urology.2017.11.019
22. Wang X, Chen S, Li X, et al. Robotic-assisted laparoscopic bilateral ileal ureter replacement with extracorporeal ileal segment preparation for bilateral extensive ureteral strictures: the initial experience. Urology. 2023;176:213-218. doi:10.1016/j.urology.2023.03.026
23. Afferi L, Gallioli A, Territo A, et al. Robotic ileal ureter replacement vs kidney autotransplantation for long ureteric strictures. BJU Int. 2025;135(6):1031-1038. doi:10.1111/bju.16704
24. Farzat M, Al-Taie I, Wagenlehner FM. Robot assisted ileal ureter replacement for complete ureteral avulsion. J Vis Exp. 2026;(234). doi:10.3791/71601
25. Guralnick ML, O'Connor RC. Ileal ureteral replacement. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:303–306.
26. Sabnis R, Patil A, Jain PS. Trauma of the ureter. In: Abdel-Gawad M, Ali-El-Dein B, Barry J, Stenzl A, eds. The Ureter: A Comprehensive Review. Springer; 2023:285–300.
27. National Comprehensive Cancer Network. NCCN Clinical Practice Guidelines in Oncology: Bladder Cancer. Version 3.2026. August 6, 2026. BL-B 4 of 4; UTT-3; Discussion MS-45. Guideline.
28. Yamamoto T, Kitagawa Y, Miki H, Watanabe J, Fukunaga Y. Laparoscopic low anterior resection with ureterectomy and ileal ureter interposition for ureter-invading locally recurrent rectal cancer: a case report. Surg Case Rep. 2026;12(1):cr.26-0394. doi:10.70352/scrj.cr.26-0394
29. Wang X, Li D, Yang K, et al. "Health-related quality of life in patients undergoing ileal ureter replacement for extensive ureteral stricture: a prospective multi-institutional study." Eur Urol Open Sci. 2026;85:16-24. doi:10.1016/j.euros.2026.01.006
30. European Association of Urology. EAU Guidelines on Urological Trauma. 2026. Section 4.2.4.b.2.c, Long segment ureteral injury. Guideline.
31. Soyster ME, Burns RT, Slaven JE, et al. "Long-term renal preservation and complication profile with ileal ureter creation." Urology. 2024;188:138-143. doi:10.1016/j.urology.2024.04.025
32. European Association of Urology. EAU Guidelines on Upper Urinary Tract Urothelial Cell Carcinoma. 2026. Section 8, Follow-up. Guideline.
33. Chen S, Wang X, Li Z, et al. "Minimally invasive versus open ileal ureter with ileocystoplasty: comparative outcomes and 5-year experience." BMC Urol. 2024;24(1):118. doi:10.1186/s12894-024-01509-5
34. Asghar AM, Lee Z, Lee RA, et al. "Robotic ureteral reconstruction in patients with radiation-induced ureteral strictures: experience from the Collaborative of Reconstructive Robotic Ureteral Surgery." J Endourol. 2021;35(2):144-150. doi:10.1089/end.2020.0643
35. Tikkinen KAO, Cartwright R, Jensen AG, Violette PD. "European guidelines on peri-operative venous thromboembolism prophylaxis: first update. Chapter 12: Urology." Eur J Anaesthesiol. 2024;41(8):618-621. doi:10.1097/EJA.0000000000002012
36. Li X, Zhu W, Zeng Z, et al. "Bilateral ileal ureter substitution for patients with ureteral strictures secondary to gynecological tumors radiotherapy: a multi-center retrospective study." Transl Androl Urol. 2021;10(8):3226-3238. doi:10.21037/tau-21-255
37. Wu G, Li H, Luo F, et al. "Total intracorporeal laparoscopic ileal ureter replacement in a single position for ureteral stricture based on membrane anatomy." BMC Surg. 2024;24(1):88. doi:10.1186/s12893-024-02363-w