Pyeloplasty
Pyeloplasty is the definitive reconstructive operation for clinically significant ureteropelvic junction obstruction (UPJO). Across open, laparoscopic, and robot-assisted approaches, durable success usually exceeds 90%, and Anderson-Hynes dismembered pyeloplasty remains the reference operation because it excises the diseased UPJ, permits dependent funnel-shaped reconstruction, and handles crossing vessels cleanly.[1][2][3]
For the disease workup, see UPJ Obstruction. For functional imaging thresholds, see MAG3 renal scintigraphy. For cross-cutting upper-tract reconstruction principles, see Upper Tract Reconstruction Principles.[4][5][6]
Operative Indications
Pyeloplasty is chosen when obstruction is clinically meaningful, anatomically reconstructable, and the renal unit has salvageable function.[1][4][7]
Pediatric patients
Most antenatal hydronephrosis is observed first. When pediatric differential renal function is <20%, the 2026 EAU guideline describes management as controversial: discuss primary pyeloplasty or nephrectomy with the family, and consider observation in selected children, although evidence-based selection criteria are lacking.[70] It states that a staged trial of temporary diversion does not seem advantageous.[70] Even among infants with high-grade hydronephrosis, only a subset ultimately requires surgery, so the pediatric decision is based on trajectory rather than one ultrasound alone.[4][8][9]
The 2026 EAU guideline grades its recommendations to base pediatric surgery on serial hydronephrosis and renal function, and to offer pyeloplasty for clinically confirmed obstruction, as weak.[70] Operative considerations include:
- declining differential renal function on serial renography,
- progressive hydronephrosis or parenchymal thinning,
- recurrent febrile UTI attributable to obstruction,
- pain, stones, hematuria, or failure to thrive from obstruction,
- worsening UTD/SFU grade despite surveillance.[4][8][9]
Adult patients
Adult UPJO is more symptom-driven. Pyeloplasty is indicated for flank pain with documented obstruction, recurrent pyelonephritis, stones from stasis, declining function, or symptomatic equivocal obstruction when the clinical pattern is compelling.[1][7] Intermittent obstruction from a crossing renal vessel can present as Dietl's crisis: severe episodic flank or abdominal pain with nausea, vomiting, and sometimes hematuria, driven by position- or diuresis-dependent kinking of the UPJ across the vessel. In a pediatric surgical series of crossing-vessel UPJO, 10 children had mild prenatal hydronephrosis that decreased before symptoms appeared 5–9 years later, so an earlier mild study could be falsely reassuring; ultrasound during acute symptoms showed significant hydronephrosis, and gross hematuria was the presenting feature in 11% of the 71 children with crossing-vessel obstruction.[57] In one adult RALP series, success remained high even when preoperative MAG3 obstruction severity was equivocal, emphasizing that symptoms, anatomy, and renal function must be interpreted together rather than reduced to T1/2 alone.[7]
Preoperative Planning
Before elective pyeloplasty, obtain a urine culture and treat bacteriuria before surgery. This applies the 2026 EAU Urological Infections guideline's strong recommendation for urological procedures breaching mucosa to an operation that opens the collecting system.[71]
The preoperative plan answers four anatomic and functional questions:
- Is this true obstruction? Diuretic renography evaluates drainage and differential function. A prolonged T1/2, including >20 minutes, cannot diagnose obstruction by itself; interpret images, curves, diuretic response, postvoid drainage, renal function and clinical context together.[5][10]
- Where exactly is the transition point? CT urography, MR urography, retrograde pyelography, and operative inspection define whether the lesion is a short UPJ problem, a longer proximal ureteral stricture, a high insertion, or a salvage anatomy.[10][11]
- Is a crossing vessel present? Lower-pole vessels alter operative planning. Preserve the vessel and select its final relationship to the reconstructed UPJ from intraoperative anatomy; anterior transposition is not routine. A causative crossing vessel generally disfavors endopyelotomy.[12][13][68]
- Is the kidney worth reconstruction? Differential renal function, cortical thickness, symptoms, infection history, stones, and patient goals determine reconstruction versus drainage, observation, or nephrectomy.[1][11] In adults with differential renal function of 30% or less, low-level evidence suggests pyeloplasty may relieve symptoms and stabilize function, but neither baseline function nor cortical thickness consistently predicts functional recovery.[75]
| Study | What It Adds | Practical Use |
|---|---|---|
| Ultrasound | Hydronephrosis grade, AP diameter, parenchymal thickness | Surveillance and pediatric progression tracking |
| MAG3/DTPA renography | Drainage curve and differential renal function | Supports obstruction assessment in clinical context and measures baseline split function[5] |
| CT urography | Stones, crossing vessels, renal pelvis anatomy, secondary causes | Adult operative planning and complex anatomy |
| MR urography | Radiation-free anatomy and functional data | Pediatric, pregnancy, contrast/radiation avoidance |
| Retrograde pyelography | Exact transition point and stricture length | Equivocal or reoperative cases, often at time of surgery |
In a selected cohort, CT parenchymal measurements correlated with renal functional categories; CT alone does not establish nonfunction or justify nephrectomy. Use dedicated functional assessment when it will change renal salvage decisions.[11]
Choosing the Operation
Technique choice follows the anatomy encountered at the UPJ.
| Anatomy | Preferred Operation | Why |
|---|---|---|
| Intrinsic UPJ stenosis, redundant pelvis, crossing vessel, or uncertain mechanism | Anderson-Hynes dismembered pyeloplasty | Excises the diseased segment, reduces pelvis, permits vascular transposition |
| Short intrinsic stenosis, small pelvis, and no dorsal vessel requiring transposition | Fenger plasty | Heineke-Mikulicz widening; selected ventral crossing vessels can be displaced clear of the UPJ[46] |
| High ureteral insertion, small or intrarenal pelvis, no crossing vessel | Foley Y-V plasty or anterior Y-V modification | Advances pelvic flap into ureter without transection |
| Long UPJ/proximal narrowing with generous pelvis | Culp-DeWeerd or Scardino-Prince flap | Pelvic flap bridges a longer defect |
| Pure extrinsic pediatric obstruction by crossing vessel | Vascular hitch | Avoids collecting-system opening only after careful assessment for intrinsic stenosis and adequate drainage after vessel mobilization |
| Short recurrent stricture without crossing vessel or severe hydronephrosis | Endopyelotomy, selectively | Lower morbidity but less durable than pyeloplasty |
| Dense redo UPJ, intrarenal pelvis, inaccessible renal pelvis | Redo pyeloplasty or ureterocalicostomy | Formal salvage reconstruction is more durable than repeat temporizing |
Nondismembered operations are selection-dependent. They have been used for short intrinsic UPJ stenosis or selected ventral crossing-vessel obstruction after vessel displacement; in Rassweiler's algorithm, posterior crossing vessels or a redundant pelvis led to dismembered repair.[13][14][15][46]
Anderson-Hynes Dismembered Pyeloplasty
Anderson-Hynes pyeloplasty remains the default because it solves the largest number of UPJO mechanisms with one design: resect the nonfunctional junction, preserve blood supply, create a dependent wide anastomosis, and transpose the ureter anterior to lower-pole vessels when present.[1][2][6]
Setup and exposure
- Position depends on approach: flank or open, transperitoneal robotic or laparoscopic, or retroperitoneal minimally invasive. For robotic/laparoscopic transperitoneal repair, a technique review of pediatric robot-assisted upper-tract surgery describes a modified lateral decubitus position rotated approximately 30 degrees off the vertical plane, with the table flexed approximately 15 degrees at the kidney rest, a beanbag reaching the neck, and foam padding at pressure points and the face; these are pediatric positioning details but the same lateral-decubitus concept applies to adult transperitoneal and retroperitoneal renal access.[56]
- For the open flank approach, an extraperitoneal incision begins at the tip of the 12th rib and extends no farther anteriorly than the lateral border of the rectus sheath. The external oblique, internal oblique, and transversus abdominis layers are divided in sequence, with the intercostal nerves between the internal oblique and transversus identified and protected; separating the transversalis fascia from the underlying Gerota fascia and peritoneum before placing a self-retaining retractor reduces tearing, and preserving the dorsal perinephric fat aids later coverage of the repair.[58]
- No pyeloplasty-specific VTE recommendation exists. Most repairs are elective, minimally invasive, and comparatively short; apply the general risk framework (age, obesity, prior VTE, malignancy, prolonged operation or immobility) on the VTE Prophylaxis page rather than a fixed regimen, with added weight for open repair, longer operative time, or a redo/salvage case.
- Expose the renal pelvis and proximal ureter with minimal periureteral stripping.
- Identify lower-pole crossing vessels early and preserve them.
- Mobilize only enough ureter and pelvis to create a tension-free repair.
Core steps
- Define the UPJ. Confirm the transition from renal pelvis to normal ureter and identify intrinsic narrowing, high insertion, kinking, fibrosis, stone disease, or vessel compression.
- Transect and excise the diseased segment. Resect to healthy ureter and viable pelvis.
- Spatulate the ureter laterally. A 1-2 cm lateral spatulation creates a broad dependent opening.
- Trim the pelvis selectively. Reduce redundant pelvis only enough to create a dependent funnel; over-resection can create tension. For concomitant stones, an eight-patient robotic series described preoperative mapping of burden and location followed by flexible nephroscopy through the opened renal pelvis, with grasper or basket extraction before completing the UPJ repair.[74]
- Set vessel relationships and place the apical stitch. When transposition is needed, position the ureter or pelvis anterior to the preserved crossing vessel before sewing the anastomosis. The lowest point of ureteral spatulation is joined to the most dependent corner of the renal pelvis. This stitch sets the geometry of the repair.
- Run or interrupt the posterior wall. Use fine absorbable suture, typically 5-0 or 6-0 in adults and children depending on tissue size.
- Place drainage. Most surgeons place a double-J stent before completing the anterior wall; external or stentless strategies are acceptable in selected pediatric or experienced settings. The stent itself can be placed retrograde by cystoscopy before the robotic or laparoscopic portion begins, or antegrade once the UPJ is exposed during the repair. Retrograde pre-placement allows direct or fluoroscopic confirmation of position, can leave a string for office removal without repeat cystoscopy, and decompresses the collecting system to aid pelvis identification and mobilization, at the cost of a stent that can be cumbersome during suturing and can obscure the true location and length of the obstruction; initial cystoscopy and retrograde pyelogram are favored for redo pyeloplasty or complex anatomy.[60] Some surgeons instead begin without a preexisting stent so the dilated pelvis, including crossing vessels, remains easier to identify, aspirating the pelvis if excessive hydronephrosis makes the UPJ hard to dissect, and place the stent later during the repair itself.[60]
- Complete the anterior wall. The anastomosis should be mucosa-to-mucosa, watertight, broad, and not strangulated.
- Inspect the completed repair. Confirm a dependent, tension-free course without kinking or recurrent compression at the preserved vessel.
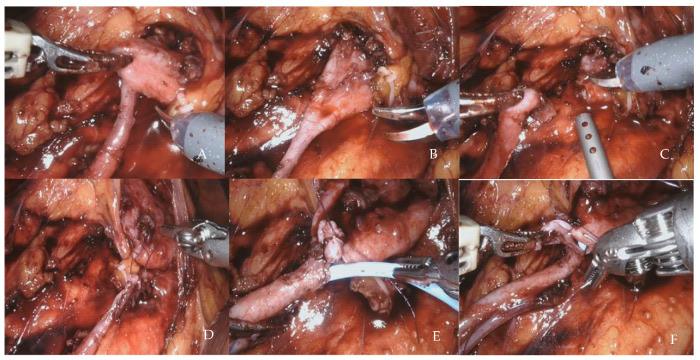
Main steps of robot-assisted laparoscopic pyeloplasty. (A) The ureter is traced proximally to the pelvis. (B) The ureteropelvic junction is delineated and placed on traction. (C) The pelvis is dismembered. (D) First stitch after lateral spatulation of the ureter. (E) Antegrade stenting after the posterior suture line is completed. (F) Anterior suture. From Moretto S, et al. J Clin Med. 2023;12(7):2538, Figure 2 (CC BY).[43]
The ureter-first modification standardizes the operation by opening the ureter just below the UPJ first, then trimming the pelvis only after the true ureteral length and lower pelvic lip are known. This reduces the chance of trimming away the tissue needed for a tension-free dependent funnel.[6]
Anastomotic details that matter. The anastomosis is a dependent funnel. One pediatric comparative study favored 1 mm bites for selected postoperative outcomes; bite depth also depends on age, tissue thickness and redo status. In a meta-analysis of five studies at high risk of bias, continuous suturing shortened operative time by about 33 minutes without a significant difference in complications or failure compared with interrupted suturing.[16][17]
Nondismembered Pyeloplasty
Nondismembered operations widen the UPJ without completely transecting the ureter from the pelvis. Their advantage is simpler suturing and preserved continuity; their limitation is that they cannot reliably excise diseased tissue, transpose a crossing vessel, or reduce a massively redundant pelvis unless modified.[13][14][15]
Fenger plasty
Fenger plasty applies the Heineke-Mikulicz principle: a full-thickness longitudinal incision is carried through the stenotic UPJ from the renal pelvis across the stenosis into the proximal ureter, then closed transversely, identical to Heineke-Mikulicz pyloroplasty. This converts the narrow segment into a wider-caliber channel and can be completed with as few as 1–3 sutures, optionally reinforced with fibrin glue and a Gerota-fascia flap, over an indwelling stent left approximately 6 weeks.[14][18][46]
It is best for short-segment intrinsic stenosis with a small to moderate pelvis. Janetschek's series found ventrally crossing vessels in 79% of cases were not a contraindication (the vessels were displaced cephalad and the Fenger plasty performed beneath them, with Doppler in the last nine patients showing a mean 1.5 cm clearance from the UPJ), but dorsally crossing vessels requiring transposition remain a contraindication.[46]
Advantages:
- fastest and simplest nondismembered option,
- few sutures, shorter operative times than dismembered repair,
- useful in retroperitoneoscopic or laparoscopic settings where complex suturing is undesirable.
Limitations:
- no ability to transpose a dorsally crossing vessel,
- no meaningful pelvic reduction,
- poor fit for high insertion or long strictures; the Heineke-Mikulicz geometry fails when the stenosis is too long.
Outcomes. In the largest series, Janetschek performed 63 Fenger plasties (plus 4 Y-V) across 67 obstructed UPJs laparoscopically or retroperitoneoscopically, with mean operative time 123 minutes and no intraoperative complications.[46] Of the 48 patients available for follow-up (mean 25 months, range 4-60), 47 (98%) were successful; the single failure was a stenosis, aggravated by infection, that was too long for the technique.[46] A retrospective laparoscopic series of 54 patients reported nondismembered success of 90.9% (11 patients: 8 Y-V and 3 Fenger).[14] Pediatric data are mixed and appear selection-dependent: a 34-procedure nondismembered pediatric series reported 91% success (95.5% open, 83.5% laparoscopic),[18] whereas Casale found only 43% success for laparoscopic Heineke-Mikulicz pyeloplasty in 7 children versus 94% for dismembered Anderson-Hynes in 19 (p = 0.002), with 4 of the 7 nondismembered patients presenting with acute flank pain within 3 days of stent removal.[48] Gill's percutaneous endopyeloplasty applies the same longitudinal-incision and transverse-suture principle endoscopically through a nephrostomy tract, with relief of obstruction in all 9 initial patients.[47] A later nonrandomized comparison from the same group, restricted to short-segment (less than 1 cm) primary UPJ obstruction without crossing vessels for the two percutaneous arms, found symptom resolution and unobstructed drainage in 100% of 15 percutaneous endopyeloplasty patients (mean follow-up 11.6 months) versus 93%/88% of 15 percutaneous endopyelotomy patients (mean follow-up 31.4 months) and 93%/100% of 14 laparoscopic dismembered pyeloplasty patients (mean follow-up 20 months); operative time was shortest for endopyelotomy and longest for laparoscopic pyeloplasty.[64]
Foley Y-V plasty
Foley Y-V plasty cuts a Y-shaped incision across the UPJ (the stem running down the proximal ureter through the stenotic segment, the two arms onto the renal pelvis) and advances the resulting V-shaped pelvic flap caudally into the ureteral incision, converting the Y into a V and widening the junction without transecting the ureter. It is classically used for high ureteral insertion, small or intrarenal pelvis, and intrinsic obstruction without a crossing vessel; when an aberrant vessel causes the obstruction the dismembered Anderson-Hynes repair is preferred, since the nondismembered design cannot transpose the ureter anterior to the vessel.[15][19]
The anterior Y-V modification places the flap and both suture lines on the more accessible anterior renal pelvis, simplifying laparoscopic access in a small or intrarenal pelvis; a modified Y-V with elliptic excision of the cranial limbs can extend the technique to selected redundant-pelvis anatomy that the classic flap cannot reduce.[19][20]
Outcomes. Comparative data place Y-V plasty close to Anderson-Hynes. A prospective randomized laparoscopic comparison enrolled 50 patients (25 per arm); the authors reported success of 86% with Y-V versus 95% with Anderson-Hynes at mean follow-up of 26.6 and 26.2 months, respectively, without a statistically significant difference. Success required pain relief, unobstructed renography, and stable or improved differential function; operative time, morbidity, and length of stay were similar, while crossing vessels were more frequent in the Y-V group.[15] A retrospective comparison enrolled 88 patients; after 2 open conversions and 3 losses to follow-up, complete success was 31/34 (91.2%) with Y-V and 45/49 (91.8%) with Anderson-Hynes at mean follow-up of 29 months.[44] The anterior Y-V modification achieved complete success in 34 of 35 patients (97.1%; mean follow-up 24 months),[19] while a retrospective series reported success of 90.9% for 11 nondismembered repairs (8 Y-V and 3 Fenger) versus 88.5% for Anderson-Hynes at mean follow-up of 55.6 months, with shorter operative time for the nondismembered group.[14] A pediatric retroperitoneoscopic series (n = 41; 21 Y-V, 20 Anderson-Hynes) showed 88% overall success at a median 69 months with no difference between techniques.[45] The trade-off is consistent. Y-V is technically simpler with fewer suture lines and often shorter operative times, at the cost of no vessel transposition and no pelvic reduction in its classic form.
Non-transecting Y-V flap with posterior stricturoplasty
A non-transecting Y-V flap pyeloplasty with stricturoplasty has been described as a vascular-preserving variant for primary UPJO with a patent lumen. The rationale borrows from non-transecting urethroplasty: leaving the ureter in continuity preserves its longitudinal blood supply and keeps dismembered pyeloplasty available for revision. A narrow ureteral plate at the UPJ is a potential limitation of flap repairs, and the authors proposed it as a contributor to Heineke-Mikulicz failures, so the posterior ureteral wall is incised (stricturoplasty) to widen the plate before the pelvic flap is advanced.[67]
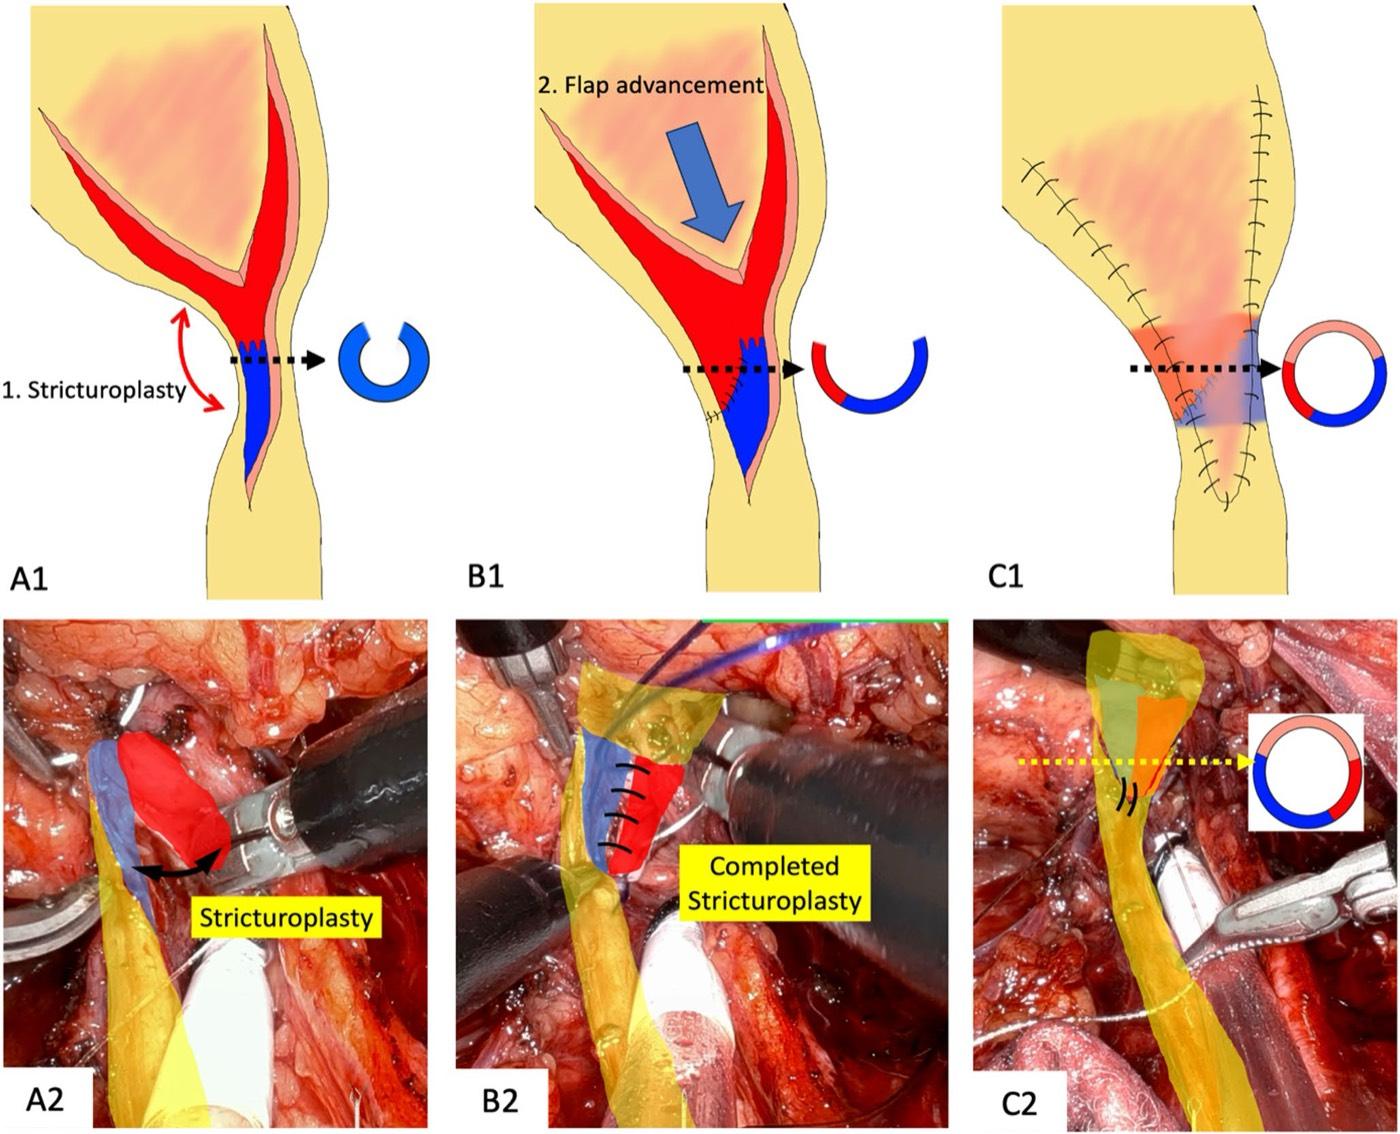
A1–A2, right UPJ before augmentation; B1–B2, after posterior stricturoplasty (performed on the medial or lateral wall, whichever is more mobile); C1–C2, after flap advancement. Red, posterior renal pelvis wall; blue, ureter at the stricture; pink, advanced flap. From Ratanapornsompong W, et al. World J Urol. 2026;44:433, Fig. 1 (CC BY 4.0).
Technique. The described operation used the da Vinci single-port system through a 3 cm supine anterior retroperitoneal incision, two-thirds of the way from the anterior superior iliac spine to the umbilicus, with pneumoretroperitoneum at 8 mmHg. Patients were supine (male) or in lithotomy (female) so that flexible cystoscopy, retrograde wire placement and ureteroscopy could proceed without repositioning. Ureteroscope light combined with near-infrared fluorescence helped locate the obstruction. The Y incision runs on the inferolateral pelvis and lateral ureter, with the inferior limb carried through the UPJ into the proximal ureter. After posterior stricturoplasty and pelvic mobilization, the V flap is advanced and sewn with a running double-armed 4-0 barbed polydioxanone suture over a retrograde stent. Redundant pelvis outside the flap margins can be excised. With a crossing vessel, the UPJ was dissected off the vessel and the flap advancement relocated the neo-UPJ inferiorly, away from it, without a formal Hellström transposition. Drains were not used, and stents were removed in the office at 2–3 weeks.[67]
Outcomes. In a single-surgeon retrospective series of 21 patients (76% female, median age 35; 5 with crossing vessels, 5 with high insertion, 2 after failed endopyelotomy), median operative time was 109 minutes and median blood loss 15 mL, with no conversions or intraoperative complications. Eighteen patients (86%) went home the same day, and none had a Clavien-Dindo grade III or higher complication. At a median 73 weeks, 20 of 21 (95%) were free of secondary intervention with improved symptoms and imaging; the single failure, recurrent obstruction after stent removal, was treated by endopyelotomy. All 8 patients with postoperative renography had a T½ under 20 minutes.[67] Patients with an obliterated UPJ or needing multilevel reconstruction were excluded, there was no comparison group, and postoperative renography was selective. The authors reserve dismembered repair for obliterated or severely fibrotic segments and for malrotated or horseshoe kidneys. Longer obliterated segments go to augmented anastomotic repair or buccal mucosa graft ureteroplasty.[67]
Culp-DeWeerd and Scardino-Prince flaps
Pelvic flap pyeloplasty uses renal pelvic tissue to bridge a longer narrowed UPJ or proximal ureteral segment. Both are nondismembered: a pedicled flap of renal pelvis wall, based at the UPJ, is rotated inferiorly and sutured into the longitudinally opened stricture, maintaining ureteral continuity. The Culp-DeWeerd flap (1951) is cut spirally or obliquely across the pelvis, which yields a longer flap and bridges a longer defect; the Scardino-Prince flap (1953) is a shorter vertical dependent flap. Both require a large, extrarenal, dilated pelvis to supply the tissue; neither is feasible with a small or intrarenal pelvis, and the flap base should be ≥ 1.5–2 cm wide for reliable perfusion.[13][21]
These flaps are uncommon today: being nondismembered they cannot transpose the ureter anterior to a crossing vessel or correct a high insertion, so they have been largely supplanted by Anderson-Hynes, which addresses crossing vessel, high insertion, and redundant pelvis in one operation. A retrospective 133-case laparoscopic comparison found dismembered repair modestly superior to nondismembered repairs (97% versus 89%; p = 0.04).[52] Oesterwitz reported a microsurgical Culp-DeWeerd modification in 11 patients with reduced need for urinary diversion and shorter stay.[21][52]
The spiral-flap concept persists in complex reconstruction. A single-patient report described a laparoscopic dismembered tubularized pelvic flap bridging a 3 cm upper-ureteral defect in recurrent UPJO.[53] In a porcine model (7 animals), chronic percutaneous balloon expansion of the renal pelvis over 4 weeks allowed a tubularized spiral flap to bridge 5–7 cm proximal ureteral defects; two animals died of sepsis.[54] The same geometry has been described as a spiral bladder muscle flap with vascular pedicles for full-length ureteral loss.[55]
Dismembered V-flap
The Diamond-Nguyen dismembered V-flap is a hybrid: the UPJ is transected, but a V-shaped pelvic flap is advanced into the spatulated ureter to create a dependent funnel. It is useful for high insertion or selected redo anatomy where a standard repair would be tight.[22]
Anatomic Variants
Duplex collecting system. UPJ obstruction in a duplex kidney usually involves the lower-pole moiety. In incomplete duplication, options beyond a standard dismembered repair of the lower-pole pelvis include anastomosing the lower-pole pelvis to the upper-pole ureter (end-to-side or side-to-side, with a generous upper-ureteral incision of at least 1.5 cm to support drainage and a tension-free, non-angulated union); complete duplication is generally managed with a standard dismembered pyeloplasty selected by moiety function and stenosis length. Partial nephrectomy rather than repair is favored when the affected moiety is nonfunctioning or minimally functioning, illustrated as roughly 5–10% or less of overall renal function on nuclear imaging; this threshold has not been validated against an outcome comparison.[59][61]
Horseshoe or pelvic kidney. Transperitoneal ports are placed more caudally and medially than the usual renal port positions to accommodate the kidney's lower, medial location. Isthmectomy is generally unnecessary for UPJ obstruction in a horseshoe kidney and is rarely required; fusion of the kidneys by itself is not an indication to divide the isthmus.[63]
Secondary UPJ obstruction with high-grade vesicoureteral reflux. When a markedly dilated, tortuous ureter raises concern for both high-grade reflux and secondary UPJ obstruction, simultaneous ureteral reimplantation and dismembered pyeloplasty is best avoided, because the combined dissection can compromise ureteral blood supply; a staged approach is generally favored, though convincing comparative evidence for staging over a combined repair is lacking. A subadventitial dissection plane at the UPJ has been proposed as a way to protect ureteral perfusion if a combined repair is attempted, but it is not an established substitute for staging.[61]
Open, Laparoscopic, and Robotic Approaches
The reconstructive design is the same regardless of access route. The difference is morbidity, working space, suturing ergonomics, cost, and surgeon experience.[2][23][24]
| Approach | Typical Success | Strengths | Limitations |
|---|---|---|---|
| Open pyeloplasty | 90-99% | Universal access, tactile feedback, reliable for redo/complex anatomy | More pain, larger incision, longer recovery |
| Laparoscopic pyeloplasty | 88-98% | Minimally invasive durability with low cost compared with robotics | Steep learning curve for intracorporeal suturing |
| Robot-assisted pyeloplasty | 92-100% | Suturing ergonomics, shorter learning curve, shorter length of stay in many series | Cost, access, docking/OR-time variability |
Robot-assisted laparoscopic pyeloplasty (RALP) is widely used where robotic access exists. Pediatric meta-analysis shows similar success and complications to open repair with shorter length of stay, while comparative meta-analysis suggests RALP may reduce operative time, complications, and length of stay compared with conventional laparoscopy, though evidence quality is limited.[23][24]
In a retrospective series of 129 adults and children undergoing RALP (mean follow-up 34 months, range 1-147), 125/129 (96.9%) met the study’s success definition of symptom resolution, improved hydronephrosis, or resolved obstruction on imaging; 8-year failure-free survival was 91.5% overall and 96.3% among stented repairs.[3] In NSQIP data for 2,712 adults (2017-2023), 92.2% of pyeloplasties were minimally invasive, with shorter hospitalization and fewer infectious complications than open surgery after adjustment.[25]
A prone posterior dorsal lumbotomy is a described open alternative to the flank approach for Anderson-Hynes repair: an oblique incision between the 12th rib and the spine, extending to just above the iliac crest, with longitudinal division of the latissimus aponeurosis and lumbodorsal fascia and protection of the iliohypogastric nerve, which crosses the fascial incision perpendicularly. It avoids the flank approach's muscle-splitting incisions and its medial/lateral orientation differs from the flank view, but it is less extensible and can limit exposure if the dissection proves difficult. No comparative morbidity data support one open access route over the other.[59]
Transperitoneal versus retroperitoneal
- Transperitoneal access offers a larger working space and is most common.
- Retroperitoneal access provides direct UPJ exposure, avoids bowel mobilization, and is attractive after prior abdominal surgery or for posteriorly accessible kidneys.
A 10-year retroperitoneal RALP experience reported high success, median one-night hospitalization, and low major-complication rates, supporting retroperitoneal access as a mature alternative.[26] With the single-port platform, a supine anterior retroperitoneal approach allows concurrent ureteroscopy without repositioning; one series used it for non-transecting Y-V flap pyeloplasty with 86% same-day discharge.[67]
A transmesenteric transperitoneal route has been described as a selected option in thin patients with little mesenteric fat, often children or thin women, or when the colon lies unusually lateral or posterior to the kidney and conventional mobilization risks a mesenteric rent: the mesenteric peritoneum is opened longitudinally with cold scissors while avoiding mesenteric vessels, and a transabdominal stay suture to elevate the renal pelvis can assist exposure. This is a selected-anatomy technique without comparative outcome data.[62]
Infants
Open pyeloplasty remains common in very small infants, but RALP is increasingly reported as safe and effective in selected infants at experienced centers. The decision is driven by patient size, working distance, anesthesia factors, institutional experience, and the need to avoid compromising the reconstruction for access convenience.[9][27]
Stenting and Drainage
Postoperative drainage is a trade-off between leak risk, tube or stent morbidity, cost, and the need for a second anesthetic in children.[28][29][30]
| Strategy | Advantages | Trade-offs |
|---|---|---|
| Internal double-J stent | Familiar; associated with lower odds of major leak or urinoma than stentless repair in a pediatric network meta-analysis, similar to external stents (mostly low or very low certainty)[72] | Cystoscopic removal in many children, stent symptoms, cost |
| External transanastomotic stent | Avoids cystoscopic removal; favorable cost-effectiveness | External tube care, more leakage than DJ in some analyses |
| Stentless | Shorter operative time and less stent morbidity in selected hands | Higher leak risk; best reserved for favorable repairs and reliable follow-up |
Pediatric network meta-analysis found no significant difference in operative success, hospital stay, renal function improvement, or overall complications among DJ, external, and stentless pyeloplasty, but urine leak patterns and cost differed.[28][31] Adult stentless laparoscopic or robotic pyeloplasty is feasible in selected cases, but most surgeons still stent routine repairs.[29][32] In a single-surgeon randomized trial of primary minimally invasive Anderson-Hynes repair, 24-month scintigraphy showed unobstructed drainage in 29/30 after 2-week versus 30/31 after 6-week double-J stenting (p = 0.962); redo cases were excluded, 21/82 missed 2-year imaging, and follow-up from years 2 to 5 relied mainly on interviews.[73]
Vascular Hitch
The vascular hitch, or Hellstrom-Chapman concept, relocates a lower-pole crossing vessel cranially to relieve extrinsic compression without opening the collecting system.[12][33][34] It is a narrow operation for pure extrinsic obstruction.[12][33][34]
Strict selection criteria:
- pediatric or young patient with imaging suggesting crossing-vessel compression,
- no evidence of intrinsic narrowing,
- preserved UPJ peristalsis and caliber once the vessel is lifted,
- an intraoperative diuretic test that confirms free drainage after vessel displacement.
If drainage remains impaired after lifting the vessel, the patient has intrinsic or mixed UPJO and should receive dismembered pyeloplasty. Failures of vascular hitch are usually failures of selection: the operation treated the vessel but left the stenotic UPJ behind.[12][33]
Endopyelotomy
Endopyelotomy incises the UPJ endoscopically and stents the defect to heal open. It is less invasive than pyeloplasty but less durable, especially with crossing vessels, long strictures, severe hydronephrosis, or poor renal function.[13][35][36]
Best candidates:
- primary short intrinsic UPJ narrowing,
- no crossing vessel,
- preserved renal function,
- mild to moderate hydronephrosis,
- patient preference for lower morbidity despite lower durability.
Avoid endopyelotomy when there is a crossing vessel, stricture length greater than about 2 cm, severe hydronephrosis, markedly impaired differential function, active infection, or secondary ischemic or reoperative narrowing where definitive reconstruction is feasible.[13][35][36]
In a single-institution comparison, estimated 10-year recurrence-free survival was 41% after antegrade endopyelotomy (n = 182) and 75% after pyeloplasty (n = 175; p < 0.001).[35] Endopyelotomy may still have a selective salvage role after failed pyeloplasty when the recurrent segment is short and anatomy is favorable.[35][37]
Failed Pyeloplasty
Failure usually declares itself within the first year, but late failures occur; persistent or recurrent pain, febrile UTI, stones, worsening hydronephrosis, or obstructed drainage warrants reassessment.[3][38]
Redo pyeloplasty
Redo pyeloplasty, including robotic repair, is the usual salvage operation for recurrent UPJO. A 2026 meta-analysis of 12 comparative studies (549 adults and children) associated redo pyeloplasty with higher odds of study-defined success than endopyelotomy or balloon dilation (OR 6.32, 95% CI 3.25-12.32); variable outcome definitions and high-to-serious risk of bias limit certainty.[69] Pediatric reoperative laparoscopic and robotic series (11 and 36 children) report high symptom resolution and radiographic improvement when the recurrent obstruction is reconstructed rather than repeatedly dilated.[39][40]
When scarring or tissue loss prevents a tension-free redo dismembered repair, a buccal mucosa graft (BMG) can augment the reconstruction at the UPJ, applying the same anterior-onlay and augmented-anastomotic principles used for mid-ureteral BMG ureteroplasty, with omental quilting to provide a vascular bed for the free graft. In a multi-institutional series of robotic BMG ureteroplasty for ureteral strictures at various sites, Chao 2025 reported 150/163 (92.0%) freedom from further intervention at median 29 months; 77/163 had prior stricture treatment, which was not an independent predictor of success. Separate reports describe salvage BMG pyeloplasty in two adults after two prior failed repairs and robot-assisted redo pyeloplasty in three children.[49][50][51] See Buccal Mucosa Graft Ureteroplasty for full technique and outcomes.
Salvage ladder
| Salvage Problem | Reconstruction |
|---|---|
| Short recurrent UPJ scar with usable pelvis | Redo dismembered pyeloplasty |
| Intrarenal pelvis or inaccessible scarred renal pelvis | Ureterocalicostomy |
| Long proximal ureteral loss with usable ureteral plate | Buccal mucosa graft ureteroplasty |
| Extensive ureteral disease | Ileal ureter replacement, transureteroureterostomy, or renal autotransplantation |
| Nonfunctional symptomatic renal unit | Nephrectomy after careful functional and patient-goal assessment |
In a prospective multicenter failed-pyeloplasty cohort, predictors of secondary surgical failure included multiple prior pyeloplasties, preoperative indwelling double-J stent, and reduced ipsilateral parenchymal thickness.[41] Of 124 patients followed for a median of 24.4 months, unadjusted failure occurred in 10/45 (22.2%) after balloon dilation, 3/33 (9.1%) after graft or flap ureteroplasty, and 4/46 (8.7%) after redo pyeloplasty; the between-group difference was not statistically significant (p = 0.117).[41] Balloon dilation is reserved for selected low-complexity recurrences.[41]
Outcomes and Follow-up
Successful pyeloplasty is defined by symptom relief, improved or stable hydronephrosis, unobstructed drainage, and preserved or improved differential renal function. Imaging often lags symptoms; persistent postoperative hydronephrosis alone does not equal failure if drainage and clinical course are improving.[1][3][7]
Follow-up commonly includes:
- renal ultrasound after stent removal or within the first several months,
- MAG3/DTPA renography when symptoms persist, ultrasound worsens, or baseline function was threatened,
- longer surveillance in children, solitary kidneys, redo repairs, severe preoperative hydronephrosis, or equivocal postoperative imaging.
In a retrospective collaborative cohort of 759 laparoscopic and robotic pyeloplasties, prior endopyelotomy (HR 4.35) and intraoperative crossing vessels (HR 2.73) were the independent predictors of decreased freedom from secondary procedures. Surgical platform itself was not an independent predictor after adjustment.[42]
Complications can also present late. In a review of 257 children who underwent dismembered pyeloplasty, 55 patients with at least 10 years of post-pubertal follow-up were analyzed: 12.7% were diagnosed with hypertension and 18.2% with proteinuria, at a mean of roughly 16 years postoperatively (differential renal function on MAG3 renography had improved, not declined, by final follow-up). The retrospective cohort's authors recommend evaluating for these signs starting 10 years after surgery and then every 5 years through 20 years.[66]
Complications
In the NSQIP cohort of 2,712 adults, 7.1% had at least one 30-day complication, 4.5% were readmitted and 2.2% required reoperation.[25] The same failure modes recur across approaches:
- urine leak or urinoma,
- UTI or pyelonephritis,
- stent migration, encrustation, symptoms, or retained stent,
- ileus or bowel injury with transperitoneal access,
- bleeding or vascular injury,
- recurrent obstruction,
- persistent pain despite patent drainage.[23][25][43]
Minimally invasive approaches generally reduce blood loss, incision morbidity, length of stay, and convalescence while preserving functional success when performed by teams comfortable with reconstructive suturing.[2][23][43]
One described postoperative workflow for suspected leak checks drain creatinine on postoperative day 1 and removes the Foley catheter if it is normal, then rechecks drain creatinine roughly six hours after a subsequent void trial before removing the drain. A small urinary leak is managed with initial diversion (ureteral stent and Foley catheter); persistent leakage despite these measures, or a large symptomatic intraperitoneal urinoma, prompts percutaneous drainage, which can also be offered up front when faster leak resolution is wanted.[65]
Operative Pearls
- Default to dismembered pyeloplasty when anatomy is uncertain, the pelvis is redundant, a crossing vessel is present, or intrinsic disease is likely.
- Do not perform vascular hitch unless the obstruction disappears intraoperatively after the vessel is lifted.
- Make the anastomosis a dependent funnel. The dependent apical stitch determines the repair.
- Preserve periureteral adventitia. Over-mobilization can turn a short UPJ problem into an ischemic proximal ureter problem.
- Do not overtreat postoperative hydronephrosis. Trend symptoms, drainage, parenchyma, and function together.
- Treat failed pyeloplasty as a reconstruction. Define the recurrent anatomy and escalate to ureterocalicostomy, graft, bowel, or autotransplantation when native redo repair cannot be tension-free.
Videos
References
1. Khan F, Ahmed K, Lee N, et al. Management of ureteropelvic junction obstruction in adults. Nat Rev Urol. 2014;11(11):629-638. doi:10.1038/nrurol.2014.240
2. Autorino R, Eden C, El-Ghoneimi A, et al. Robot-assisted and laparoscopic repair of ureteropelvic junction obstruction: a systematic review and meta-analysis. Eur Urol. 2014;65(2):430-452. doi:10.1016/j.eururo.2013.06.053
3. Hopf HL, Bahler CD, Sundaram CP. Long-term outcomes of robot-assisted laparoscopic pyeloplasty for ureteropelvic junction obstruction. Urology. 2016;90:106-110. doi:10.1016/j.urology.2015.12.050
4. Cai PY, Lee RS. Ureteropelvic junction obstruction/hydronephrosis. Urol Clin North Am. 2023;50(3):361-369. doi:10.1016/j.ucl.2023.04.001
5. Taylor AT, Brandon DC, de Palma D, et al. SNMMI procedure standard/EANM practice guideline for diuretic renal scintigraphy in adults with suspected upper urinary tract obstruction 1.0. Semin Nucl Med. 2018;48(4):377-390. doi:10.1053/j.semnuclmed.2018.02.010
6. Nayyar R, Kumar P, Panaiyadiyan S, Seth A. Ureter-first approach and reduction of pelvis: standardizing handling of ureteropelvic junction during pyeloplasty. Urology. 2022;160:210-216. doi:10.1016/j.urology.2021.10.030
7. Zappia JL, Farrow JM, Song L, et al. Outcomes of robot-assisted laparoscopic pyeloplasty based on degree of obstruction on preoperative Tc-99 MAG-3 renal scintigraphy. J Endourol. 2023;37(2):151-156. doi:10.1089/end.2022.0463
8. Weitz M, Portz S, Laube GF, Meerpohl JJ, Bassler D. Surgery versus non-surgical management for unilateral ureteric-pelvic junction obstruction in newborns and infants less than two years of age. Cochrane Database Syst Rev. 2016;7:CD010716. doi:10.1002/14651858.CD010716.pub2
9. Herndon CDA, Otero HJ, Hains D, Sweeney RM, Lockwood GM. Perinatal urinary tract dilation: recommendations on pre-/postnatal imaging, prophylactic antibiotics, and follow-up: clinical report. Pediatrics. 2025;156(1):e2025071814. doi:10.1542/peds.2025-071814
10. Whitworth P, Courtney KG, Oto A, et al. ACR Appropriateness Criteria Hydronephrosis on prior imaging-unknown cause. J Am Coll Radiol. 2024;21(6S):S144-S167. doi:10.1016/j.jacr.2024.02.020
11. Ark JT, Mitchell CR, Marien TP, Herrell SD. Use of contrasted computerized tomography as a surrogate for nuclear medicine renogram to categorize renal function in the setting of ureteropelvic junction obstruction. Urology. 2016;97:238-244. doi:10.1016/j.urology.2016.04.068
12. Kim JK, Keefe DT, Rickard M, et al. Vascular hitch for paediatric pelvi-ureteric junction obstruction with crossing vessels: institutional analysis and systematic review with meta-analysis. BJU Int. 2022;129(6):679-687. doi:10.1111/bju.15342
13. Rassweiler JJ, Subotic S, Feist-Schwenk M, et al. Minimally invasive treatment of ureteropelvic junction obstruction: long-term experience with an algorithm for laser endopyelotomy and laparoscopic retroperitoneal pyeloplasty. J Urol. 2007;177(3):1000-1005. doi:10.1016/j.juro.2006.10.049
14. Amon Sesmero JH, Delgado MC, de la Cruz Martin B, et al. Laparoscopic pyeloplasty: always dismembered? J Endourol. 2016;30(7):778-782. doi:10.1089/end.2015.0800
15. Szydelko T, Kasprzak J, Lewandowski J, Apoznanski W, Dembowski J. Dismembered laparoscopic Anderson-Hynes pyeloplasty versus nondismembered laparoscopic Y-V pyeloplasty in the treatment of patients with primary ureteropelvic junction obstruction: a prospective study. J Endourol. 2012;26(9):1165-1170. doi:10.1089/end.2011.0642
16. Gu S, Luo H. The optimal suture bite depth in laparoscopic pyeloplasty: a comparative study in children. J Laparoendosc Adv Surg Tech A. 2024;34(9):871-875. doi:10.1089/lap.2023.0434
17. Kim JK, Lee MJ, Gao B, et al. Comparison of continuous and interrupted suture techniques in pyeloplasty: a systematic review and meta-analysis. Pediatr Surg Int. 2022;38(9):1209-1215. doi:10.1007/s00383-022-05173-4
18. Polok M, Chrzan R, Veenboer P, et al. Nondismembered pyeloplasty in a pediatric population: results of 34 open and laparoscopic procedures. Urology. 2011;78(4):891-894. doi:10.1016/j.urology.2011.04.039
19. Szydelko T, Kasprzak J, Apoznanski W, Zdrojowy R. Laparoscopic anterior Y-V pyeloplasty: a valuable treatment option in patients with small or intrarenal pelvis. J Laparoendosc Adv Surg Tech A. 2010;20(7):627-630. doi:10.1089/lap.2010.0223
20. Tsivian A, Tsivian M, Sidi AA. The Y-V pyeloplasty revisited. Urology. 2010;75(1):200-202. doi:10.1016/j.urology.2009.08.062
21. Oesterwitz H, Bick C, Muller P, Hengst E, Seeger W. Management of ureteropelvic junction obstruction using a microsurgical technique. Eur Urol. 1987;13(6):412-414. doi:10.1159/000472836
22. Diamond DA, Nguyen HT. Dismembered V-flap pyeloplasty. J Urol. 2001;166(1):233-235. doi:10.1016/s0022-5347(05)66133-2
23. Sun M, Yu C, Zhao J, et al. The efficacy of robotic-assisted laparoscopic pyeloplasty for pediatric ureteropelvic junction obstruction: a systematic review and meta-analysis. Pediatr Surg Int. 2023;39(1):265. doi:10.1007/s00383-023-05541-8
24. Light A, Karthikeyan S, Maruthan S, et al. Peri-operative outcomes and complications after laparoscopic vs robot-assisted dismembered pyeloplasty: a systematic review and meta-analysis. BJU Int. 2018;122(2):181-194. doi:10.1111/bju.14170
25. Touma Sawaya R, Zein M, Abdessater M. Short-term postoperative outcomes of open and minimally invasive pyeloplasty: evidence from a NSQIP database. World J Urol. 2026;44(1):183. doi:10.1007/s00345-026-06255-x
26. Whiting D, Whitehurst L, Tsang D, et al. Retroperitoneal robotic-assisted laparoscopic pyeloplasty: a 10 year experience in a single institution. J Endourol. 2022;36(5):615-619. doi:10.1089/end.2021.0551
27. Rague JT, Arora HC, Chu DI, et al. Safety and efficacy of robot-assisted laparoscopic pyeloplasty compared to open repair in infants under 1 year of age. J Urol. 2022;207(2):432-440. doi:10.1097/JU.0000000000002232
28. Liu X, Huang C, Guo Y, Yue Y, Hong J. Comparison of DJ stented, external stented and stent-less procedures for pediatric pyeloplasty: a network meta-analysis. Int J Surg. 2019;68:126-133. doi:10.1016/j.ijsu.2019.07.001
29. Bilen CY, Bayazit Y, Gudeloglu A, et al. Laparoscopic pyeloplasty in adults: stented versus stentless. J Endourol. 2011;25(4):645-650. doi:10.1089/end.2010.0401
30. Bayne AP, Lee KA, Nelson ED, et al. The impact of surgical approach and urinary diversion on patient outcomes in pediatric pyeloplasty. J Urol. 2011;186(4 Suppl):1693-1698. doi:10.1016/j.juro.2011.03.103
31. Yiee JH, Baskin LS. Use of internal stent, external transanastomotic stent or no stent during pediatric pyeloplasty: a decision tree cost-effectiveness analysis. J Urol. 2011;185(2):673-680. doi:10.1016/j.juro.2010.09.118
32. Sethi AS, Regan SM, Sundaram CP. Robot-assisted laparoscopic pyeloplasty with and without a ureteral stent. J Endourol. 2011;25(2):239-243. doi:10.1089/end.2010.0192
33. Chiarenza SF, Bleve C, Fasoli L, et al. Ureteropelvic junction obstruction in children by polar vessels. Is laparoscopic vascular hitching procedure a good solution? Single center experience on 35 consecutive patients. J Pediatr Surg. 2016;51(2):310-314. doi:10.1016/j.jpedsurg.2015.10.005
34. Chiarenza SF, Bleve C, Caione P, et al. Minimally invasive treatment of pediatric extrinsic ureteropelvic junction obstruction by crossing polar vessels: is vascular hitching a definitive solution? Report of a multicenter survey. J Laparoendosc Adv Surg Tech A. 2017;27(9):965-971. doi:10.1089/lap.2016.0605
35. Dimarco DS, Gettman MT, McGee SM, et al. Long-term success of antegrade endopyelotomy compared with pyeloplasty at a single institution. J Endourol. 2006;20(10):707-712. doi:10.1089/end.2006.20.707
36. Ost MC, Kaye JD, Guttman MJ, Lee BR, Smith AD. Laparoscopic pyeloplasty versus antegrade endopyelotomy: comparison in 100 patients and a new algorithm for the minimally invasive treatment of ureteropelvic junction obstruction. Urology. 2005;66(5 Suppl):47-51. doi:10.1016/j.urology.2005.06.115
37. Kim EH, Tanagho YS, Traxel EJ, et al. Endopyelotomy for pediatric ureteropelvic junction obstruction: a review of our 25-year experience. J Urol. 2012;188(4 Suppl):1628-1633. doi:10.1016/j.juro.2012.02.016
38. Yanke BV, Lallas CD, Pagnani C, McGinnis DE, Bagley DH. The minimally invasive treatment of ureteropelvic junction obstruction: a review of our experience during the last decade. J Urol. 2008;180(4):1397-1402. doi:10.1016/j.juro.2008.06.020
39. Moscardi PR, Barbosa JA, Andrade HS, et al. Reoperative laparoscopic ureteropelvic junction obstruction repair in children: safety and efficacy of the technique. J Urol. 2017;197(3 Pt 1):798-804. doi:10.1016/j.juro.2016.10.062
40. Jacobson DL, Shannon R, Johnson EK, et al. Robot-assisted laparoscopic reoperative repair for failed pyeloplasty in children: an updated series. J Urol. 2019;201(5):1005-1011. doi:10.1016/j.juro.2018.10.021
41. Xiong S, Fan S, Huang Y, et al. Clinical efficacy and risk factors of minimally invasive surgery for failed pyeloplasty: a prospective multicenter cohort study. Int J Surg. 2025. doi:10.1097/JS9.0000000000004448
42. Lucas SM, Sundaram CP, Wolf JS, et al. Factors that impact the outcome of minimally invasive pyeloplasty: results of the Multi-Institutional Laparoscopic and Robotic Pyeloplasty Collaborative Group. J Urol. 2012;187(2):522-527. doi:10.1016/j.juro.2011.09.158
43. Moretto S, Gandi C, Bientinesi R, et al. Robotic versus open pyeloplasty: perioperative and functional outcomes. J Clin Med. 2023;12(7):2538. doi:10.3390/jcm12072538
44. Szydelko T, Kasprzak J, Apoznanski W, et al. Comparison of dismembered and nondismembered Y-V laparoscopic pyeloplasty in patients with primary hydronephrosis. J Laparoendosc Adv Surg Tech A. 2010;20(1):7-12. doi:10.1089/lap.2009.0210
45. Subotic S, Weiss H, Wyler S, et al. Dismembered and non-dismembered retroperitoneoscopic pyeloplasty for the treatment of ureteropelvic junction obstruction in children. World J Urol. 2013;31(3):689-695. doi:10.1007/s00345-012-0887-0
46. Janetschek G, Peschel R, Bartsch G. Laparoscopic Fenger plasty. J Endourol. 2000;14(10):889-893. doi:10.1089/end.2000.14.889
47. Gill IS, Desai MM, Kaouk JH, Wani K, Desai MR. Percutaneous endopyeloplasty: description of new technique. J Urol. 2002;168(5):2097-2102. doi:10.1016/S0022-5347(05)64304-2
48. Casale P, Grady RW, Joyner BD, et al. Comparison of dismembered and nondismembered laparoscopic pyeloplasty in the pediatric patient. J Endourol. 2004;18(9):875-878. doi:10.1089/end.2004.18.875
49. Chao BW, Raver M, Lin JS, et al. Robotic buccal mucosa graft ureteroplasty: a decade of experience from a multi-institutional cohort. Urology. 2025;197:174-179. doi:10.1016/j.urology.2024.11.059
50. Zampini AM, Nelson R, Zhang JJH, et al. Robotic salvage pyeloplasty with buccal mucosal onlay graft: video demonstration of technique and outcomes. Urology. 2017;110:253-256. doi:10.1016/j.urology.2017.07.023
51. Ahn JJ, Shapiro ME, Ellison JS, Lendvay TS. Pediatric robot-assisted redo pyeloplasty with buccal mucosa graft: a novel technique. Urology. 2017;101:56-59. doi:10.1016/j.urology.2016.12.036
52. Juliano RV, Mendonça RR, Meyer F, et al. Long-term outcome of laparoscopic pyeloplasty: multicentric comparative study of techniques and accesses. J Laparoendosc Adv Surg Tech A. 2011;21(5):399-403. doi:10.1089/lap.2010.0281
53. Kaouk JH, Kuang W, Gill IS. Laparoscopic dismembered tubularized flap pyeloplasty: a novel technique. J Urol. 2002;167(1):229-231. doi:10.1016/s0022-5347(05)65419-5
54. Liatsikos EN, Bernardo NO, Dinlenc CZ, et al. Chronic expansion of the renal pelvis: a new method for reconstruction of upper ureteral defects. Urology. 2000;56(5):867-871. doi:10.1016/s0090-4295(00)00720-2
55. Li Y, Li C, Yang S, et al. Reconstructing full-length ureteral defects using a spiral bladder muscle flap with vascular pedicles. Urology. 2014;83(5):1199-1204. doi:10.1016/j.urology.2014.01.027
56. Chang C, Steinberg Z, Shah A, Gundeti MS. Patient positioning and port placement for robot-assisted surgery. J Endourol. 2014;28(6):631-638. doi:10.1089/end.2013.0733
57. Rigas A, Karamanolakis D, Bogdanos I, Stefanidis A, Androulakakis PA. Pelvi-ureteric junction obstruction by crossing renal vessels: clinical and imaging features. BJU Int. 2003;92(1):101-103. doi:10.1046/j.1464-410x.2003.04265.x
58. Wiener JS. Open pyeloplasty. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:145–154.
59. Estrada CR, Retik AB. Open surgical management of ureteropelvic junction obstruction. In: Montague DK, Gill IS, Angermeier KW, Ross JH, eds. Textbook of Reconstructive Urologic Surgery. Informa Healthcare; 2008:143–150.
60. Davol PE, Fulmer BR, Rukstalis DB. Urologic applications of robotic surgery. In: Montague DK, Gill IS, Angermeier KW, Ross JH, eds. Textbook of Reconstructive Urologic Surgery. Informa Healthcare; 2008:84–96.
61. Rawashdeh YFH, Olsen LH. Surgery of the ureter in children: ureteropelvic junction, megaureter, and vesicoureteral reflux. In: Partin AW, Dmochowski RR, Kavoussi LR, Peters CA, eds. Campbell-Walsh-Wein Urology. 13th ed. Elsevier; 2025:1064–1090.
62. Wagner KR, Jarrett TW. Laparoscopic pyeloplasty. In: Montague DK, Gill IS, Angermeier KW, Ross JH, eds. Textbook of Reconstructive Urologic Surgery. Informa Healthcare; 2008:151–159.
63. Frota R, Stein RJ, Aron M, Gill IS. Laparoscopic surgery in horseshoe and pelvic kidneys. In: Montague DK, Gill IS, Angermeier KW, Ross JH, eds. Textbook of Reconstructive Urologic Surgery. Informa Healthcare; 2008:174–181.
64. Desai MM, Desai MR, Gill IS. Endopyeloplasty versus endopyelotomy versus laparoscopic pyeloplasty for primary ureteropelvic junction obstruction. Urology. 2004;64(1):16-21. doi:10.1016/j.urology.2004.02.031
65. Morgan TN, Soto-Palou F. Laparoscopic and robotic pyeloplasty. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:174–180.
66. Lee HE, Park K, Choi H. An analysis of long-term occurrence of renal complications following pediatric pyeloplasty. J Pediatr Urol. 2014;10(6):1083-1088. doi:10.1016/j.jpurol.2014.03.015
67. Ratanapornsompong W, Sarawong S, Walasek A, Lin JS, Elbakry A, Zhao LC. Single-port robotic non-transecting Y-V flap pyeloplasty with stricturoplasty for ureteropelvic junction obstruction: a case series. World J Urol. 2026;44:433. doi:10.1007/s00345-026-06551-6
68. Boylu U, Oommen M, Lee BR, Thomas R. "Ureteropelvic junction obstruction secondary to crossing vessels-to transpose or not? The robotic experience." J Urol. 2009;181(4):1751-1755. doi:10.1016/j.juro.2008.11.114
69. Chua ME, Wong MM, Gouwtama M, et al. "Challenging recurrent ureteropelvic junction obstructions: endoscopic procedures versus redo-pyeloplasty-a systematic review and meta-analysis." World J Urol. 2026;44(1):256. doi:10.1007/s00345-026-06339-8
70. European Association of Urology. "EAU Guidelines on Paediatric Urology: Dilatation of the Upper Urinary Tract (PUJ Obstruction)." 2026. Guideline chapter
71. European Association of Urology. "EAU Guidelines on Urological Infections." 2026. Guideline chapter
72. Aubert O, M'Tiri S, Kühnapfel A, et al. "The optimal stent-strategy in paediatric pyeloplasty: a systematic review and network meta-analysis." BJU Int. 2026. doi:10.1111/bju.70423
73. Birkhäuser FD, von Rütte T, Moltzahn F, Huber P, Zehnder P. "A short double-J ureteral stent indwelling time is safe and effective following minimally invasive pyeloplasty: long-term results from a prospective randomized controlled trial." Eur Urol Open Sci. 2025;74:28-33. doi:10.1016/j.euros.2025.01.014
74. Atug F, Castle EP, Burgess SV, Thomas R. "Concomitant management of renal calculi and pelvi-ureteric junction obstruction with robotic laparoscopic surgery." BJU Int. 2005;96(9):1365-1368. doi:10.1111/j.1464-410X.2005.05819.x
75. Freitas PFS, Barbosa JABA, Andrade HS, et al. "Pyeloplasty in adults with ureteropelvic junction obstruction in poorly functioning kidneys: a systematic review." Urology. 2021;156:e66-e73. doi:10.1016/j.urology.2021.05.017