Renal Autotransplantation
Renal autotransplantation (RAT) is a complex surgical procedure in which a patient's own kidney is removed (nephrectomy), repaired or reconstructed on a back table (ex vivo bench surgery), and then reimplanted into an iliac fossa selected for suitable vessels and urinary drainage, analogous to a kidney transplant but using the patient's own organ, thereby eliminating the need for immunosuppression.[1][2] It is a rarely performed but widely accepted nephron-sparing technique reserved for highly select patients with complex renovascular, ureteral, oncologic, or pain-syndrome conditions where conventional approaches have failed or are unsuitable.[3]
RAT is a major salvage option considered alongside ileal ureter and other reconstructions.[1][3] Selection depends on defect length, bladder and bowel suitability, renal and iliac vascular anatomy, residual function of the affected kidney, and patient priorities.[1][3] Severe iliac vascular disease, retroperitoneal fibrosis involving the iliac vessels, or little residual function in the affected kidney may make iliac-fossa autotransplantation unsuitable.[31] An eight-centre retrospective comparison of robotic ileal ureter (15 patients) and autotransplantation (39 patients) reported similar renal-function trajectories and major-complication rates, but the groups differed in baseline health and stricture length.[28] A 2026 meta-analysis found no significant difference in pooled success, with only 41 autotransplants among 1,044 patients and low certainty.[29]
Historical Context
First described by Hardy in 1963, RAT was popularized in the 1970s–1980s primarily for complex renovascular disease. In a Cleveland Clinic series (1972–1988), 108 patients underwent RAT for renal artery disease (62%), ureteral replacement (25%), and renal cell carcinoma present bilaterally or in a solitary kidney (13%), with success in 52 of 54 (96%) branch renal artery reconstructions, 25 of 27 (92%) ureteral replacements and 12 of 14 (85%) tumor operations.[2] A nationwide analysis of 817 cases from 2002–2012 confirmed that procedural volume has been increasing, with 97.7% performed at urban teaching hospitals.[4]
Indications
RAT is used for the following conditions.[1][5][6]
1. Complex Renovascular Disease
- The most common historical indication, particularly for complex branch renal artery aneurysms not amenable to in situ repair.[2][7]
- Cold preservation permits longer bench reconstruction than unprotected warm ischemia. Minimize both warm and cold ischemic exposure; longer cold ischemia was associated with complications in a retrospective series.[5][7]
- In a retrospective series of 27 surgically treated patients with renal artery aneurysms, 24 underwent ex vivo surgery and autotransplantation (27 procedures). Immediate kidney patency was 25/27 (92.6%) and was maintained over a mean 47.2-month follow-up; hypertension was cured in 6 and improved in 4 of 17 hypertensive patients.[7]
- Also used for fibromuscular dysplasia, renal artery dissection, and renovascular hypertension refractory to endovascular approaches.[1][2]
2. Ureteral Stricture Disease and Ureteral Trauma
- Ureteral stricture accounted for 41 of 52 patients (79%) in a laparoscopic autotransplant series.[6] The indication mix varies by series: renal artery pathology (22.7%) and ureteral pathology (17%) led in the nationwide inpatient sample, and loin pain or chronic kidney pain (31.5%) led in a two-institution series.[4][5][6]
- Indicated when the entire ureter or a major portion requires replacement and conventional reconstructive options (ureteroureterostomy, Boari flap, psoas hitch, ileal interposition) have failed or are not feasible.[1][2]
- The Cleveland Clinic series reported excellent results in 25 of 27 patients (92%) after replacement of all or a major portion of the ureter, with well-preserved renal function and chronic bacteriuria in one patient.[2]
- Particularly valuable after iatrogenic ureteral injury, radiation-induced strictures, and retroperitoneal fibrosis.[1][8]
- See also Ureteral Stricture for the broader management algorithm.
3. Loin Pain–Hematuria Syndrome (LPHS)
- RAT serves as a form of nephron-sparing renal denervation for patients with debilitating, narcotic-dependent flank pain and hematuria with negative comprehensive urological evaluation.[9][10]
- In distinct LPHS series, pain resolved in 65% of patients treated for chronic kidney pain at a median 13 months, while 19 of 25 successful autotransplant recipients who completed a follow-up questionnaire (76%) were pain-free after a mean 8.4 years; relief lasted beyond 10 years in some cases.[5][10][11]
- In the 2015 two-institution series, pain recurred in 35% of patients treated for chronic kidney pain, and 2 patients required transplant nephrectomy.[5] In the 26-procedure long-term series, 18 (69.2%) gave pain relief, and failures usually occurred within 2 years.[5][10]
- An older nonrandomized study reported recurrence in 12/18 followed neurectomy patients and freedom from pain in 19/25 questionnaire respondents after successful autotransplantation.[11]
- Multidisciplinary pain evaluation precedes surgery. A small 2015 cohort identified no predictors of pain recurrence.[1][5] One center used CT-guided renal-hilar block with >50% immediate pain reduction to help select LPHS candidates; 22 block responders underwent RAT, but only 12 had one-year outcome data, so this remains a center-specific selection tool.[35]
4. Renal Cell Carcinoma (RCC)
- Indicated for complex tumors in a solitary kidney or bilateral synchronous tumors where in situ partial nephrectomy is not feasible, to avoid dialysis dependence.[1][12][13]
- Ex vivo partial nephrectomy and autotransplantation were successful in 12 of 14 patients (85%) in the Cleveland Clinic series.[2]
- Local recurrence has been reported in 1 of 9 patients (11%) in one series[14] and 4 of 16 (25%) after successful autotransplantation in another[15]; CT surveillance of the autotransplant site every 3 to 6 months has been advised in the latter series.[15] Surveillance is tailored to pathological stage, grade, margins, renal function and contemporary oncology guidance.[14][15]
- In the 1990 autotransplantation series, in situ partial nephrectomy was preferred when feasible because the authors considered it less morbid than extracorporeal surgery and autotransplantation.[2] The 2026 EAU guideline strongly recommends partial nephrectomy for T1 RCC and weakly recommends it for T2 RCC with a solitary kidney or CKD if technically feasible; retrospective comparisons of tumors ≥7 cm report higher postoperative complication rates with partial than radical nephrectomy.[32]
5. Upper Tract Urothelial Carcinoma (UTUC)
- Autotransplantation has been described for selected localized UTUC in a solitary kidney or bilateral disease when simpler kidney-sparing treatments are unsuitable.[16][17][18] The 2026 EAU guideline strongly recommends nephroureterectomy for high-risk non-metastatic UTUC and strongly recommends discussing kidney-sparing management for high-risk patients with imperative indications case by case; it does not recommend autotransplantation specifically.[24]
- Pyelovesicostomy after autotransplantation allows simplified endoscopic surveillance and intravesical chemotherapy instillation.[18]
- Long-term follow-up (up to 20 years) shows that recurrence in the autotransplanted kidney is possible, particularly with low-grade tumors that may progress to invasive disease.[19] After kidney-sparing UTUC treatment, the 2026 EAU guideline gives weak risk-stratified surveillance recommendations.[27] For high-risk disease, these include cystoscopy with voided cytology and, after a negative second-look ureteroscopy, imaging urography plus ureteroscopy at 3 and 6 months; ureteroscopy thereafter is optional, and its optimal routine role after endourologic treatment remains uncertain.[27]
- Autotransplantation is an exceptional kidney-preserving reconstruction. A normal opposite kidney does not mandate nephroureterectomy for all UTUC: current EAU guidance favors kidney-sparing management for low-risk disease regardless of contralateral kidney status.[24]
6. Nutcracker Syndrome
- RAT has been used as primary or salvage treatment for selected patients with symptomatic nutcracker syndrome. In a two-center retrospective series of 105 patients, 93.1% of the 101 with 12-month follow-up reported complete flank-pain relief.[30] A separate case documented a functioning graft without recurrent symptoms 7 months after salvage autotransplantation following failed renal-vein transposition.[20]
7. Refractory Nephrolithiasis
- Rare indication; with advances in endourology and minimally invasive stone management, this application has become exceedingly uncommon.[1]
Surgical Technique
The procedure consists of three phases.[1][7][12][13]
Phase 1 — Nephrectomy
- The kidney is mobilized and removed, preserving maximal renal artery and vein length and a viable ureter when benign pathology permits. For UTUC, plan ureteral excision with adequate margins; one autotransplant series removed the ureter with a bladder cuff.[17][24]
- Historically performed via open flank or transabdominal incision; increasingly performed laparoscopically (applying principles of laparoscopic living donor nephrectomy), which reduces donor-site morbidity.[6][13]
Phase 2 — Ex Vivo Bench Surgery
- The kidney is immediately flushed with cold preservation solution (e.g., University of Wisconsin solution or histidine-tryptophan-ketoglutarate) and placed on ice.
- Minimize warm and cold ischemia.[12][21] The eight-patient single-port series reported warm ischemia of 4–10 minutes and cold ischemia of 86–209 minutes.[12][21]
- On the back table, the specific pathology is addressed:
Phase 3 — Autotransplantation
- Select the iliac fossa according to vascular reach and urinary reconstruction; either ipsilateral or contralateral implantation may be appropriate.[25]
- Arterial options include end-to-side anastomosis to the external iliac artery or end-to-end anastomosis to the internal iliac artery, selected for anatomy. Venous outflow commonly uses an end-to-side external iliac vein anastomosis.[25]
- Urinary continuity may be restored by ureteroneocystostomy when a viable ureter remains, pyelovesicostomy when direct pelvis-to-bladder anastomosis is feasible, or a tailored bladder-flap reconstruction; the illustrated complete-avulsion case used a tubularized Boari flap between the renal pelvis and bladder.[16][18][26] In a four-patient solitary-kidney UTUC series, vesicorenal reflux occurred after pyelovesicostomy while kidney function remained stable over 6–14 years.[18]
- A ureteral stent is typically placed.
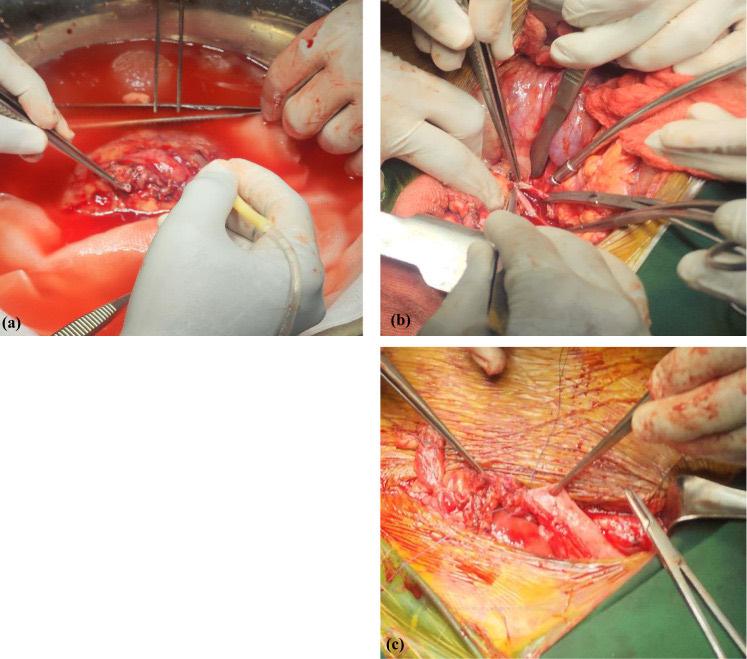
Renal autotransplantation after complete ureteral avulsion. (a) The explanted left kidney after nephrectomy, during perfusion with cold heparinized saline before autotransplantation. (b) Restored blood flow in the transplanted kidney immediately after vascular anastomosis to the external iliac artery and vein in the right iliac fossa. (c) A Boari flap raised from the anterior bladder wall and formed into a tube to bridge the gap between the renal pelvis and the bladder. From Al-Mughalis N, et al. Res Rep Urol. 2025;17:257-261, Figure 1 (CC BY-NC 4.0).[26]
Minimally Invasive and Robotic Approaches
Robot-assisted laparoscopic renal autotransplantation (RAKAT) has emerged as a feasible alternative with potentially improved perioperative outcomes.[1][21][22]
- Single-port robotic autotransplantation using the da Vinci SP platform allows the entire procedure (nephrectomy and reimplantation) through a single 5 cm periumbilical incision without patient repositioning.[21][22] See Single-Port Robotics for the broader incision atlas.
- In a series of 8 single-port cases, operative times ranged from 366–701 minutes, median hospital stay was 3 days (there was no open comparator), and all grafts maintained function with no complications at median 13-month follow-up.[21]
- In the initial single-port experience with three autotransplants, vascular anastomosis took 65–83 minutes and total operative time 510–600 minutes.[22]
- Robotic series establish feasibility in selected patients. Separate robotic and open cohorts report similar graft outcomes and shorter stays; comparative data are insufficient to assess equivalence or morbidity.[1][3] In a separate retrospective cohort of 32 robotic autotransplants (29 for nutcracker syndrome and 3 for LPHS), 9% had Clavien-Dindo grade III complications and 28% had postoperative acute kidney injury; mean follow-up was 10.9 months.[34]
Outcomes
| Outcome Measure | Data | References |
|---|---|---|
| Tran 2015, 52 analyzed of 59 operated | Function retained in 47/52 (90.3%) at median 73.5 months; 5 renal-unit failures | [6] |
| Cowan 2015, 51 patients / 54 autotransplants | Early grade ≥IIIa complications 14.8%; late complications of any grade 12.9%; 2 graft losses | [5] |
| Klein 2025, 11 autotransplants | 3 early grade ≥IIIb complications; 2/11 graft nephrectomies; no deaths or dialysis during follow-up | [3] |
| Oxford 2020, 50 autotransplants (37 for renal tumors) | Grade III-V complications 46%; temporary dialysis 32%; 5/50 eventually required long-term dialysis after graft failure or primary nonfunction | [33] |
| Nationwide inpatient study, 817 cases | In-hospital morbidity 46.2% | [4] |
| Single-port series, 8 patients | No reported complications or graft-function loss at median 13 months; small uncontrolled feasibility cohort | [21] |
These series differ in indications, denominators and follow-up.
Complications
The most common postoperative complications include:[4][5][6][15]
- Administrative diagnoses and inpatient complications. In 817 admissions coded for kidney autotransplantation, a transplanted-kidney failure diagnosis was recorded in 88 (10.7%), hemorrhagic complications in 80 (9.7%), prolonged ileus in 75 (9.2%), and UTI in 73 (8.9%); 11 patients (1.3%) died in hospital.[4]
- Graft vascular thrombosis. Vascular thrombosis can cause early graft loss: a laparoscopic series reported renal-vein thrombosis and autotransplant nephrectomy on postoperative day 1, while a 1992 RCC series listed unspecified postoperative renal vascular thrombosis among causes of four unsuccessful autotransplants.[6][15]
- Pseudoaneurysm. It may present months to years postoperatively.[6][23]
- Delayed graft function. Temporary hemodialysis was required in 2 of 12 patients (16.6%) in one series.[17]
- Ureteral complications. These include stricture and leak.
- Wound infection and blood transfusion. Intraoperative transfusion was required in 6 of 12 patients (50%) in the same series of complex renal tumors.[17]
Predictors of morbidity include obesity (AOR 9.62), fluid and electrolyte disorders (AOR 3.67), preoperative CKD (AOR 1.80), and longer cold ischemia time (p = 0.049).[4][5]
A retrospective 72-patient study detected no outcome difference between earlier and later autotransplantation after diagnosis or intervention; many patients had temporary drainage.[8]
Multidisciplinary Approach
Care involves renal transplant surgeons, vascular surgeons, urologists, nephrologists, dieticians, pain management providers, social workers, and psychiatrists. Collaboration is particularly relevant in LPHS, where psychological comorbidity may affect outcomes.[1] The procedure is performed at experienced, high-volume transplant centers.[3][4]
Key Takeaways
RAT is a nephron-sparing salvage procedure for patients who would otherwise be rendered anephric or face intractable disease. Selected series report durable renal preservation, with vascular complications and graft loss as the main risks. Local recurrence remains a concern in oncologic indications.[1][6][15]
Videos
References
1. Han DS, Johnson JP, Schulster ML, Shah O. "Indications for and Results of Renal Autotransplantation." Curr Opin Nephrol Hypertens. 2023;32(2):183–192. doi:10.1097/MNH.0000000000000860
2. Novick AC, Jackson CL, Straffon RA. "The Role of Renal Autotransplantation in Complex Urological Reconstruction." J Urol. 1990;143(3):452–457. doi:10.1016/s0022-5347(17)39988-3
3. Klein Nulend R, San Jose J, Canagasingham A, et al. "Kidney Autotransplantation: A Dual Centre Experience." ANZ J Surg. 2025. doi:10.1111/ans.70226
4. Moghadamyeghaneh Z, Hanna MH, Fazlalizadeh R, et al. "A Nationwide Analysis of Kidney Autotransplantation." Am Surg. 2017;83(2):162–169. doi:10.1177/000313481708300216
5. Cowan NG, Banerji JS, Johnston RB, et al. "Renal Autotransplantation: 27-Year Experience at 2 Institutions." J Urol. 2015;194(5):1357–1361. doi:10.1016/j.juro.2015.05.088
6. Tran G, Ramaswamy K, Chi T, et al. "Laparoscopic Nephrectomy With Autotransplantation: Safety, Efficacy and Long-Term Durability." J Urol. 2015;194(3):738–743. doi:10.1016/j.juro.2015.03.089
7. Machado M, Machado R, Almeida R. "Renal Autotransplantation for the Treatment of Renal Artery Aneurysm." Ann Vasc Surg. 2022;79:226–232. doi:10.1016/j.avsg.2021.07.048
8. Li KD, Pearce RJ, Sui W, et al. "Renal Autotransplantation: Association Between Preoperative Disease Duration and Surgical Outcomes." Urology. 2024;192:36–42. doi:10.1016/j.urology.2024.06.050
9. Spitz A, Huffman JL, Mendez R. "Autotransplantation as an Effective Therapy for the Loin Pain-Hematuria Syndrome: Case Reports and a Review of the Literature." J Urol. 1997;157(5):1554–1559. doi:10.1016/s0022-5347(01)64792-x
10. Chin JL, Kloth D, Pautler SE, Mulligan M. "Renal Autotransplantation for the Loin Pain-Hematuria Syndrome: Long-Term Followup of 26 Cases." J Urol. 1998;160(4):1232–1235; discussion 1235–1236. doi:10.1097/00005392-199810000-00005
11. Sheil AG, Chui AK, Verran DJ, Boulas J, Ibels LS. "Evaluation of the Loin Pain/Hematuria Syndrome Treated by Renal Autotransplantation or Radical Renal Neurectomy." Am J Kidney Dis. 1998;32(2):215–220. doi:10.1053/ajkd.1998.v32.pm9708604
12. Xu Y, Huang J, Fan X, et al. "Clinical Experience of Bench Surgery Combined With Autotransplantation After Three-Dimensional Laparoscopic Nephrectomy for the Treatment of Highly Complex Renal Tumor." World J Surg Oncol. 2023;21(1):373. doi:10.1186/s12957-023-03246-9
13. Meng MV, Freise CE, Stoller ML. "Laparoscopic Nephrectomy, Ex Vivo Excision and Autotransplantation for Complex Renal Tumors." J Urol. 2004;172(2):461–464. doi:10.1097/01.ju.0000130668.94919.59
14. Zincke H, Sen SE. "Experience With Extracorporeal Surgery and Autotransplantation for Renal Cell and Transitional Cell Cancer of the Kidney." J Urol. 1988;140(1):25–27. doi:10.1016/s0022-5347(17)41475-3
15. Stormont TJ, Bilhartz DL, Zincke H. "Pitfalls of 'Bench Surgery' and Autotransplantation for Renal Cell Carcinoma." Mayo Clin Proc. 1992;67(7):621–628. doi:10.1016/s0025-6196(12)60715-0
16. Pettersson S, Brynger H, Henriksson C, et al. "Treatment of Urothelial Tumors of the Upper Urinary Tract by Nephroureterectomy, Renal Autotransplantation, and Pyelocystostomy." Cancer. 1984;54(3):379–386. doi:10.1002/1097-0142(19840801)54:3<379::AID-CNCR2820540302>3.0.CO;2-U
17. Janssen MWW, Linxweiler J, Philipps I, et al. "Kidney Autotransplantation After Nephrectomy and Work Bench Surgery as an Ultimate Approach to Nephron-Sparing Surgery." World J Surg Oncol. 2018;16(1):35. doi:10.1186/s12957-018-1338-1
18. Steffens J, Humke U, Alloussi S, Ziegler M, Siemer S. "Partial Nephrectomy and Autotransplantation With Pyelovesicostomy for Renal Urothelial Carcinoma in Solitary Kidneys: A Clinical Update." BJU Int. 2007;99(5):1020–1023. doi:10.1111/j.1464-410X.2007.06753.x
19. Holmäng S, Johansson SL. "Tumours of the Ureter and Renal Pelvis Treated With Resection and Renal Autotransplantation: A Study With Up to 20 Years of Follow-Up." BJU Int. 2005;95(9):1201–1205. doi:10.1111/j.1464-410X.2005.05505.x
20. McCabe M, Ellis E, Chacon A, et al. "Use of Cryopreserved Vascular Allograft Reconstruction in Robotic-Assisted Kidney Autotransplantation for Nutcracker Syndrome After Failed Renal Vein Transposition: Description of a Novel Technique." Surg Laparosc Endosc Percutan Tech. 2025. doi:10.1097/SLE.0000000000001400
21. Kaouk J, Chavali JS, Ferguson E, et al. "Single Port Robotic Kidney Autotransplantation: Initial Case Series and Description of Technique." Urology. 2023;176:87–93. doi:10.1016/j.urology.2023.02.030
22. Kaouk J, Eltemamy M, Aminsharifi A, et al. "Initial Experience With Single-Port Robotic-Assisted Kidney Transplantation and Autotransplantation." Eur Urol. 2021;80(3):366–373. doi:10.1016/j.eururo.2021.03.002
23. Eisenberg ML, Lee KL, Zumrutbas AE, et al. "Long-Term Outcomes and Late Complications of Laparoscopic Nephrectomy With Renal Autotransplantation." J Urol. 2008;179(1):240–243. doi:10.1016/j.juro.2007.08.135
24. European Association of Urology. Upper Urinary Tract Urothelial Cell Carcinoma guideline: disease management. 2026. Official guideline.
25. Abraham GP, Siddaiah AT, Ramaswami K, George D, Das K. Ex-vivo nephron-sparing surgery and autotransplantation for renal tumours: revisited. Can Urol Assoc J. 2014;8(9-10):E728-E732. doi:10.5489/cuaj.1775
26. Al-Mughalis N, Al-Ganadi A, Al-Shameri I, et al. Renal autotransplantation for complete ureteral avulsion following dilation and curettage: a rare iatrogenic complication. Res Rep Urol. 2025;17:257-261. doi:10.2147/RRU.S538042
27. European Association of Urology. "Upper Urinary Tract Urothelial Cell Carcinoma: Follow Up." EAU Guidelines. 2026. Official guideline
28. Afferi L, Gallioli A, Territo A, et al. "Robotic ileal ureter replacement vs kidney autotransplantation for long ureteric strictures." BJU Int. 2025;135(6):1031–1038. doi:10.1111/bju.16704
29. Xu M, Yang Y, Zhang Q, Ji G, Song Z, Liang C. "Ileal ureter replacement versus kidney autotransplantation for complex ureteral strictures in the robotic era: a systematic review and meta-analysis." J Robot Surg. 2026;20(1):297. doi:10.1007/s11701-026-03273-0
30. Philip JL, Saben J, Meram E, et al. "Renal autotransplant as a definitive treatment for nutcracker syndrome: A multicenter retrospective study." J Vasc Surg Venous Lymphat Disord. 2025;13(1):101983. doi:10.1016/j.jvsv.2024.101983
31. Lin S, Gai J, Huang S, et al. "Clinical advances in kidney autotransplantation: a review." BMC Surg. 2025;25(1):54. doi:10.1186/s12893-024-02754-z
32. European Association of Urology. "EAU Guidelines on Renal Cell Carcinoma." EAU Guidelines. 2026. Official guideline
33. Vrakas G, Sullivan M. "Current Review of Renal Autotransplantation in the UK." Curr Urol Rep. 2020;21(9):33. doi:10.1007/s11934-020-00986-z
34. Mejia A, Barrera Gutierrez JC, Vivian E, et al. "Robotic assisted kidney auto-transplantation as a safe alternative for treatment of nutcracker syndrome and loin pain haematuria syndrome: A case series report." Int J Med Robot. 2023;19(3):e2508. doi:10.1002/rcs.2508
35. Campsen J, Bassett MR, O'Hara R, et al. "Renal hilar block predicts long-term success of renal auto-transplantation for loin pain hematuria syndrome." Int Urol Nephrol. 2019;51(6):927–930. doi:10.1007/s11255-019-02143-z