Principles of Upper Tract Reconstruction
Upper tract reconstruction follows a small set of rules even when the named operations differ. Define the obstruction precisely, preserve vascularity, and create a wide, tension-free, spatulated repair when native tissue allows. Escalate to grafts, bladder mobilization, bowel, contralateral drainage or renal autotransplantation only when defect length or tissue quality demands it.[1][2][3]
Named operations are listed in the database on the Upper Tract Reconstruction landing page.
1. Characterize the Obstruction Before Choosing the Operation
The stricture's full extent, vascularity, and salvageable renal function guide the choice of reconstruction.[1][2][4][21]
The preoperative workup is built around three questions:
- Where is the lesion? UPJ, proximal ureter, mid ureter, distal ureter, or pan-ureteral.
- How long and how dense is it? A short focal stricture behaves very differently from a long ischemic segment.
- How much function remains? Differential renal function and drainage kinetics influence whether the answer is reconstruction, drainage, or nephrectomy.[1][4]
In practice that usually means:
- CT urography for anatomy and adjacent pathology,
- MAG3 or DTPA renography for differential function and drainage,
- retrograde and, when indicated, antegrade pyelography to estimate stricture length, with final extent confirmed intraoperatively,[26]
- and selective ureteroscopic assessment when endoluminal appearance will change the plan.[1][4][21]
The lesion is staged before the reconstruction is chosen. For elective repair, an existing ureteral stent may be removed or exchanged for nephrostomy to better define the stricture. In a matched retrospective cohort, ureteral rest was associated with surgical success in 96.34% of 82 patients versus 86.59% of 82 without rest.[22] A separate 50-patient distal reimplantation series found no significant difference in 30-day complications, postoperative hydronephrosis, or stricture recurrence at a median 8.6 months of follow-up.[23] A larger retrospective cohort of 284 distal robotic reconstructions, which included several techniques, associated preoperative rest with higher odds of surgical success (adjusted OR 4.2, 95% CI 1.51–11.77).[27]
2. Preserve Blood Supply Relentlessly
The ureteral blood supply is segmental and linked by a delicate longitudinal adventitial network.[2][5]
The practical rules are:
- mobilize only as much ureter as the repair truly needs,
- keep periureteral adventitia intact whenever possible,
- resect back to healthy, bleeding, well-perfused tissue,
- and avoid converting a focal stricture into a long ischemic problem by over-dissection.[2][5]
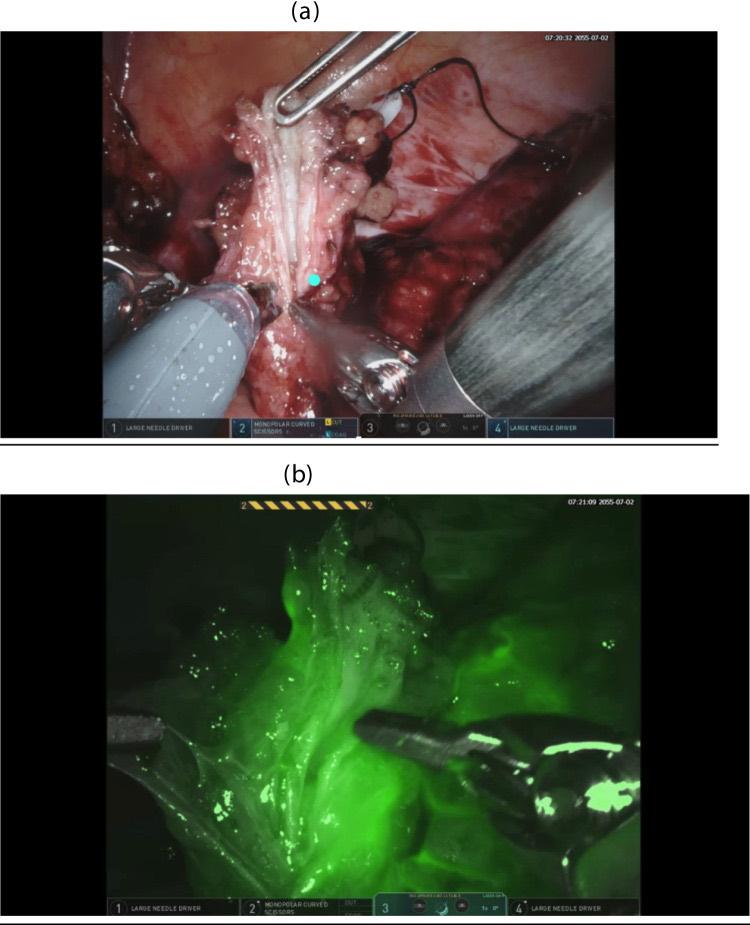
Intravenous indocyanine green (ICG) to assess ureteral perfusion during robotic reconstruction. (a) Under white light, the vascularization of the ureteral tip is doubtful. (b) After intravenous ICG, the tip is shown to be poorly vascularized and is excised before anastomosis. From Bourillon A, et al. World J Urol. 2026;44(1):102, Fig. 3 (CC BY 4.0).[21]
In reoperative, radiated and iatrogenic cases, devascularization is often a larger problem than length alone.[1][3][5]
3. All Successful Repairs Share the Same Anastomotic Rules
Whether the operation is pyeloplasty, ureteroureterostomy, reimplantation, or ileal substitution, the core reconstructive target is the same:
- debride devitalized tissue,
- spatulate generously,
- create a wide mucosa-to-mucosa repair,
- make it watertight but not strangulated,
- ensure it is truly tension-free,
- use temporary internal stenting according to the repair and leak risk; selected adult pyeloplasty can be performed without a stent after weighing urinary leakage against stent morbidity.[1][3][5][24]
Short strictures that appear repairable on imaging often still need escalation. If a proximal native repair would be under tension, downward nephropexy may gain length; proceed only when the final anastomosis is tension-free.[21]
4. Technique Choice Should Follow a Location-Based Ladder
Upper tract reconstruction follows a location-and-length ladder.[1][2][3]
| Defect domain | Usual first-line reconstruction | Common escalation |
|---|---|---|
| UPJ | Dismembered pyeloplasty | Flap pyeloplasty or ureterocalicostomy in select salvage anatomy |
| Short proximal / mid ureter | Ureteroureterostomy | Augmented anastomotic repair or BMG onlay |
| Distal ureter | Ureteral reimplantation | Psoas hitch, then Boari flap if more length is needed |
| Long-segment ureter | BMG in selected partial defects | Ileal ureter, TUU, or renal autotransplantation |
| Entire ureter / devastated field | Ileal ureter when feasible | Renal autotransplantation as salvage |
The guiding rule is to use the simplest reconstruction that solves the defect without compromising vascularity or tension.[1][3]
5. Pyeloplasty Remains the Gold Standard for UPJ Obstruction
For adult UPJ obstruction, Anderson-Hynes dismembered pyeloplasty remains the reference repair across open, laparoscopic and robotic practice. It excises the diseased segment, permits wide spatulation and handles crossing vessels.[2][6]
The design features are:
- remove the scarred UPJ segment,
- preserve enough renal pelvis for a dependent funnel,
- transpose the ureter anterior to crossing vessels when indicated,
- and construct a broad dependent anastomosis.[2][7]
Endopyelotomy has a lower success rate (42%–90% depending on the approach) than pyeloplasty, for which success exceeds 90% with open, laparoscopic and robotic techniques, although endopyelotomy causes less pain and shorter convalescence.[2]
6. Distal Reconstruction Usually Means Moving the Bladder to the Ureter
Distal ureteral reconstruction is conceptually different from proximal repair because the surgeon can recruit the bladder as part of the solution.[3][5][8]
The escalation sequence is usually:
- Direct ureteroneocystostomy when the ureter reaches comfortably.
- Psoas hitch when a modest reach advantage is needed.
- Boari flap when the gap is longer and bladder tissue can be tubularized cranially.[3][8]
The sequence preserves native upper-tract tissue. In distal injury, the distance to the bladder is often the limiting factor; bladder capacity, compliance, mobility and tissue quality determine whether a psoas hitch or Boari flap can bridge the gap safely. A contracted or severely radiated bladder may require a repair without a bladder flap.[3][21]
7. Buccal Mucosa Graft Ureteroplasty Has Become the Middle Tier Option
Buccal mucosa graft ureteroplasty occupies the middle ground between direct native-tissue repair and bowel substitution for longer proximal or mid-ureteral strictures. In the largest multi-institutional retrospective series (163 patients; median stricture length 3.0 cm; 47.2% with prior treatment), 150 (92.0%) remained free of additional interventions at a median follow-up of 29 months.[9][10][11][12]
Its advantages:
- a nontransecting onlay can preserve posterior ureteral attachments and limit circumferential dissection,[10][21]
- it preserves the native ureter,
- it applies familiar oral-mucosa graft biology from urethral reconstruction,
- and it lets the surgeon repair defects that are too long for ureteroureterostomy but too limited for ileal replacement.[10][12]
Two design principles recur in the series:
- choose onlay augmentation when a viable ureteral plate remains; for a fully obliterated segment, favor excision with a primary or augmented anastomosis.[21]
- and wrap the graft with omentum or other well-vascularized tissue whenever possible.[9][10][11]
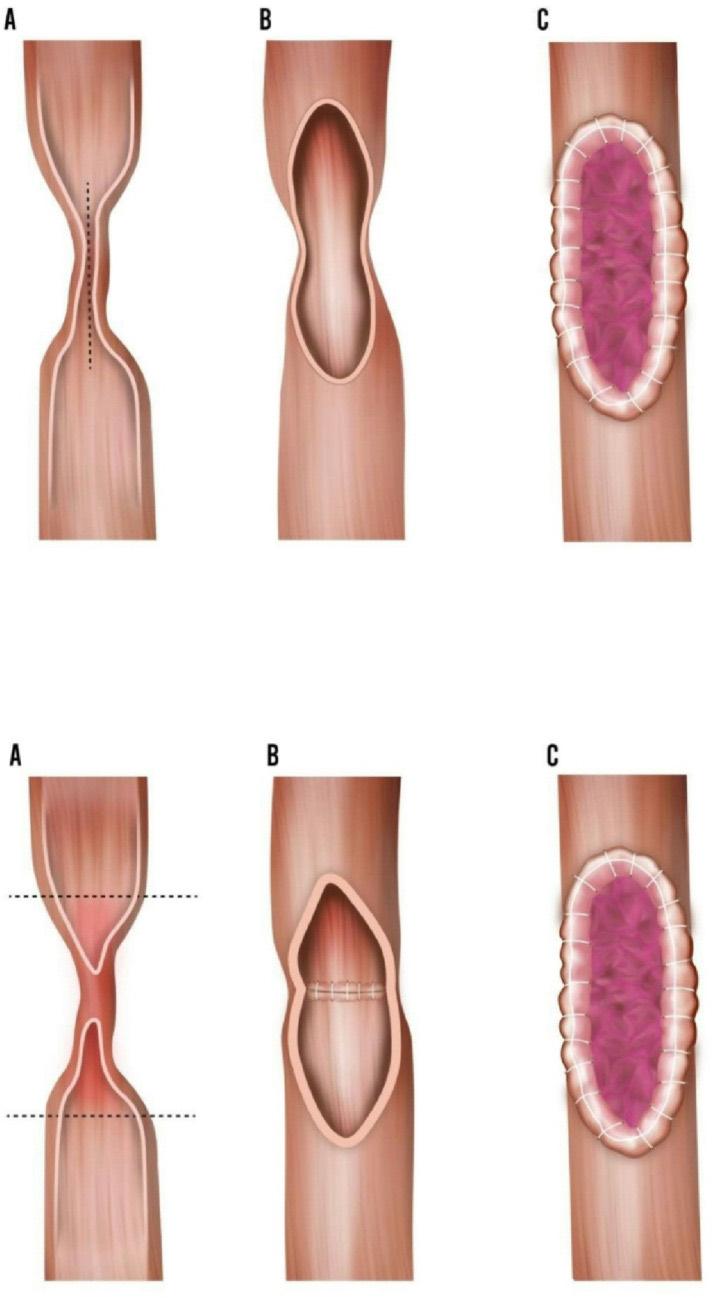
Buccal mucosa graft ureteroplasty. Top row, onlay technique: (A) longitudinal ureterotomy across the stricture, (B) the opened ureteral plate and (C) the graft sutured over the defect. Bottom row, augmented anastomotic technique: (A) the narrowed segment marked for excision, (B) posterior-wall anastomosis forming a ureteral plate and (C) the graft sutured over the remaining anterior defect. From Bourillon A, et al. World J Urol. 2026;44(1):102, Fig. 7 (CC BY 4.0).[21]
8. Ileal Ureter Is the Standard Native-Tissue Exit Ramp
When defect length exceeds what native ureter, bladder mobilization, or oral-mucosa augmentation can realistically solve, ileal ureter substitution is the usual salvage option. In a single-institution retrospective series of 46 patients receiving ileal ureter interposition (mean stricture length 9.1 cm; 43 open operations), 83% required no further open intervention at a mean follow-up of 4.4 years.[13] Eight patients (17%) later required major surgery, including three nephrectomies, and 11 (24%) had a major complication.[13][14][15][16]
Bowel is used when three conditions are met:
- the defect is too long for a durable native repair,
- the kidney has enough function to justify salvage,
- and the patient can tolerate the metabolic and revisional burden of bowel in the urinary tract, with suitable bowel health, renal and hepatic function, and bladder storage and emptying; monitor serum chemistry for hyperchloremic metabolic acidosis.[13][14][21][25]
Its technical logic is different from graft repair:
- isolate a well-vascularized ileal segment with dependable mesenteric reach,
- avoid kinking or mesenteric tension,
- protect the upper tract at the proximal end,
- and minimize the length of bowel used when adjuncts such as a Boari flap can help bridge part of the distance.[14][15][16]
9. TUU and Autotransplantation Are Salvage Tools, Not Early Moves
Transureteroureterostomy and renal autotransplantation come late in the ladder. TUU joins the donor ureter to the contralateral ureter, potentially jeopardizing that healthy drainage axis; autotransplantation relocates the kidney to the pelvis.[3][17][18][19]
TUU
TUU works when the contralateral ureter is healthy and safely reachable, and when ipsilateral repair would take place in a hostile or radiated field. The operative rule is to mobilize the recipient ureter sparingly and avoid tension or angulation of the donor ureter. In a retrospective series of 63 patients (67% benign indications), the TUU was patent in 54 of 56 patients (96.4%) with follow-up imaging at a mean of 5.8 years, and postoperative complications occurred in 23.8%.[17]
Renal autotransplantation
Autotransplantation is the major salvage option for complex proximal or multi-segment disease when bowel is undesirable or prior surgery has exhausted more direct pathways. The operation is a renal transplant performed for benign salvage. In a retrospective series of 52 patients (41 with ureteral stricture disease), 47 (90.3%) had long-term function of the autotransplanted unit at a median follow-up of 73.5 months.[18][19]
10. Select Endoscopic Treatment for Favorable Benign Strictures
Endoscopic management has a role in highly selected short benign strictures. In an 8-year single-center retrospective series of 142 patients with benign ureteral strictures (85.2% stone-related), symptomatic improvement with radiographic alleviation of blockage was reported after endourological treatment in 51.6% of 95 patients and after reconstruction in 95.7% of 47 patients (p < 0.01). Endourological treatment had shorter operative time, blood loss and hospital stay, and its success was higher for strictures ≤2 cm.[4]
Repeated endoscopic treatment may delay definitive repair.[21] In practice:
- endoscopic treatment for selected short, nonobliterative benign strictures; use a ureteral stent or nephrostomy for temporary drainage when needed,[3][21]
- reconstruction for durable restoration of drainage when the stricture biology is already declaring itself.[4]
11. Tissue Interposition and Damage Control Still Matter
Two practical principles cut across the entire field.
Use vascularized coverage when the field is hostile
Omentum, peritoneum and other vascularized tissue layers:
- support graft or anastomotic healing,
- separate urine from raw tissue planes,
- and provide a buffer against fibrosis in radiated or reoperative cases.[9][10][11]
In the unstable patient, drainage comes before elegance
For an iatrogenic ureteral injury recognized during emergency digestive surgery, intraoperative repair is preferred when the patient's condition and urologic expertise permit .[3][5] In an unstable patient, temporary urinary diversion followed by delayed reconstruction is appropriate; severe inflammation or poor tissue quality may also favor staged repair.[3][20][21] AUA permits temporary drainage followed by delayed definitive repair in unstable patients .[20]
The aim is to preserve the renal unit and set up a later reconstruction.
Core Principles at a Glance
- Stage the obstruction fully before choosing the reconstruction.
- Preserve ureteral adventitia and blood supply at every step.
- Build wide, spatulated, tension-free repairs and choose drainage for the procedure and leak risk.
- Choose the simplest location-appropriate operation that can succeed durably.
- Use pyeloplasty as the default UPJ repair.
- Use bladder mobilization maneuvers to solve distal reach problems before escalating to substitution.
- Use oral-mucosa grafting as the middle-tier option for longer proximal and mid-ureteral disease.
- Reserve ileal ureter for true long-segment defects with salvageable renal function.
- Reserve TUU and renal autotransplantation for carefully selected salvage settings.
- Prefer definitive reconstruction over serial endoscopic temporizing for most durable benign strictures.
- Use vascularized tissue coverage in hostile fields and damage-control drainage in unstable ones.
Bottom Line for the Reconstructive Surgeon
Upper tract reconstruction restores drainage by location and defect length under vascular constraints. The named procedures differ, but the logic is shared: define the defect, respect the blood supply, do the simplest repair that can be tension-free, and escalate only as anatomy or tissue quality requires.[1][2][3][18]
Videos
References
1. Drain A, Jun MS, Zhao LC. Robotic ureteral reconstruction. Urol Clin North Am. 2021;48(1):91-101. doi:10.1016/j.ucl.2020.09.001
2. Khan F, Ahmed K, Lee N, et al. Management of ureteropelvic junction obstruction in adults. Nat Rev Urol. 2014;11(11):629-638. doi:10.1038/nrurol.2014.240
3. de'Angelis N, Schena CA, Marchegiani F, et al. 2023 WSES guidelines for the prevention, detection, and management of iatrogenic urinary tract injuries during emergency digestive surgery. World J Emerg Surg. 2023;18(1):45. doi:10.1186/s13017-023-00513-8
4. Ou Y, Zhang G, Zhu X, et al. Evaluation of risk factors, treatment options, and prognostic-related factors in patients with benign ureteral strictures: an 8-year single-center experience. Int J Urol. 2023;30(10):847-852. doi:10.1111/iju.15211
5. White C, Stifelman M. Ureteral reimplantation, psoas hitch, and Boari flap. J Endourol. 2020;34(S1):S25-S30. doi:10.1089/end.2018.0750
6. Autorino R, Eden C, El-Ghoneimi A, et al. Robot-assisted and laparoscopic repair of ureteropelvic junction obstruction: a systematic review and meta-analysis. Eur Urol. 2014;65(2):430-452. doi:10.1016/j.eururo.2013.06.053
7. Nayyar R, Kumar P, Panaiyadiyan S, Seth A. Ureter-first approach and reduction of pelvis: standardizing handling of ureteropelvic junction during pyeloplasty. Urology. 2022;160:210-216. doi:10.1016/j.urology.2021.10.030
8. Dell'Oglio P, Palagonia E, Wisz P, et al. Robot-assisted Boari flap and psoas hitch ureteric reimplantation: technique insight and outcomes of a case series with ≥1 year of follow-up. BJU Int. 2021;128(5):625-633. doi:10.1111/bju.15421
9. Lee Z, Waldorf BT, Cho EY, et al. Robotic ureteroplasty with buccal mucosa graft for the management of complex ureteral strictures. J Urol. 2017;198(6):1430-1435. doi:10.1016/j.juro.2017.06.097
10. Zhao LC, Weinberg AC, Lee Z, et al. Robotic ureteral reconstruction using buccal mucosa grafts: a multi-institutional experience. Eur Urol. 2018;73(3):419-426. doi:10.1016/j.eururo.2017.11.015
11. Chao BW, Raver M, Lin JS, et al. Robotic buccal mucosa graft ureteroplasty: a decade of experience from a multi-institutional cohort. Urology. 2025;197:174-179. doi:10.1016/j.urology.2024.11.059
12. Bello D, Van Shufflin M, Hofer MD. Expanding the armamentarium: perspectives on buccal mucosal grafts and appendiceal flaps in ureteral reconstructive surgery. J Clin Med. 2025;14(21):7681. doi:10.3390/jcm14217681
13. Launer BM, Redger KD, Koslov DS, et al. Long-term follow up of ileal ureteral replacement for complex ureteral strictures: single institution study. Urology. 2021;157:257-262. doi:10.1016/j.urology.2021.07.012
14. Xiong S, Zhu W, Li X, et al. Intestinal interposition for complex ureteral reconstruction: a comprehensive review. Int J Urol. 2020;27(5):377-386. doi:10.1111/iju.14222
15. Xu YM, Feng C, Kato H, Xie H, Zhang XR. Long-term outcome of ileal ureteric replacement with an iliopsoas muscle tunnel antirefluxing technique for the treatment of long-segment ureteric strictures. Urology. 2016;88:201-206. doi:10.1016/j.urology.2015.11.005
16. Zhong W, Du Y, Yang K, et al. Ileal ureter replacement combined with Boari flap-psoas hitch to treat full-length ureteral defects: technique and initial experience. Urology. 2017;108:201-206. doi:10.1016/j.urology.2017.07.014
17. Iwaszko MR, Krambeck AE, Chow GK, Gettman MT. Transureteroureterostomy revisited: long-term surgical outcomes. J Urol. 2010;183(3):1055-1059. doi:10.1016/j.juro.2009.11.031
18. Han DS, Johnson JP, Schulster ML, Shah O. Indications for and results of renal autotransplantation. Curr Opin Nephrol Hypertens. 2023;32(2):183-192. doi:10.1097/MNH.0000000000000860
19. Tran G, Ramaswamy K, Chi T, et al. Laparoscopic nephrectomy with autotransplantation: safety, efficacy and long-term durability. J Urol. 2015;194(3):738-743. doi:10.1016/j.juro.2015.03.089
20. Morey AF, Broghammer JA, Hollowell CMP, et al. Urotrauma Guideline 2020: AUA Guideline. J Urol. 2021;205(1):30–35. doi:10.1097/JU.0000000000001408. Full guideline, published 2014; amended April 2017 and August 2020.
21. Bourillon A, Peyronnet B, McGuire BB, Pinar U, Lee Z, Nair R, et al. Ureteral stricture: current treatment algorithm and key surgical principles in the robotic upper urinary tract reconstruction era. World J Urol. 2026;44(1):102. doi:10.1007/s00345-025-06181-4
22. Zhou Y, Chai S, Xu K, et al. "Effect of ureteral rest on surgical outcomes in adults with ureteral stricture undergoing reconstruction: a propensity score matching study." World J Urol. 2025;43(1):186. doi:10.1007/s00345-025-05577-6
23. Campbell K, Singh SM, Vetter J, et al. "Ureteral Rest is Unnecessary Prior to Ureteral Reimplantation." J Endourol. 2026;40(2):229-232. doi:10.1177/08927790251404448
24. Mittal A, Subramanyam AD, Panwar VK, Singh DK, Agrawal O. "Stented versus stentless pyeloplasty in adults: a systematic review of surgical outcomes and complications." Indian J Urol. 2026;42(1):6-15. doi:10.4103/iju.iju_318_25
25. Waterloos M, Campos-Juanatey F, Hallscheidt P, et al. "EAU Guidelines on Urological Trauma." EAU Guidelines Office, Arnhem, Netherlands; 2026. Guideline.
26. Xu K, Dong M, Liang C, et al. "Advancing urological practice: the value of combined antegrade and retrograde ureterography for the management of complex ureteral strictures." Transl Androl Urol. 2026;15(5):169. doi:10.21037/tau-2026-1-0129
27. Lee M, Zhao K, Chao B, et al. "Preoperative factors for success of robotic ureteral reconstruction for distal ureteral strictures." J Endourol. 2024;38(12):1359-1363. doi:10.1089/end.2024.0595