Ureteral Reimplantation
Ureteral reimplantation (ureteroneocystostomy) restores continuity between the ureter and bladder. For transecting ureteroneocystostomy, the reconstructive target is a tension-free, well-vascularized, spatulated, watertight ureterovesical anastomosis, often supported with a stent; when reflux prevention matters, an adequate detrusor or submucosal tunnel creates a flap-valve mechanism.[1][2][3]
The operation is used in two overlapping settings:
- Pediatric antireflux or megaureter surgery. Vesicoureteral reflux (VUR), primary obstructive megaureter (POM), duplex systems, ureterocele-associated reflux or obstruction, and failed endoscopic injection.[1][3][4]
- Adult distal ureteral reconstruction. Iatrogenic injury, distal ureteral stricture, endometriosis, radiation injury, retroperitoneal fibrosis, distal ureterectomy for urothelial carcinoma[56], and congenital distal anomalies presenting in adulthood.[2][5][6]
For cross-cutting upper-tract reconstruction principles, see Upper Tract Reconstruction Principles. For adult stricture workup and the reconstruction ladder, see Ureteral Stricture. For longer defects, see Boari Flap & Psoas Hitch.
Indications
Pediatric
Common pediatric indications include:
- VUR with breakthrough febrile UTI on prophylaxis, high-grade reflux, progressive renal scarring, declining function, persistent reflux after observation or endoscopic therapy, or family preference for definitive correction.[1][3][4]
- Primary obstructive megaureter when surveillance fails because of recurrent UTI, worsening hydronephrosis, declining split function, pain, stones, or progressive ureteral dilation.[7][8]
- Duplex systems, ectopic ureters, ureteroceles, and refluxing or obstructing ureteral limbs when reconstruction preserves the renal unit.
- Failed endoscopic injection therapy, especially with persistent high-grade reflux or recurrent febrile UTI.[3][9]
The EAU 2026 paediatric guideline (limited update, March 2026) states that the traditional sequence of initial medical treatment followed by surgery should be challenged and that treatment should follow risk group. Its recommendations are:[38]
- Offer reimplantation to patients with persistent high-grade reflux and endoscopic correction for lower grades (strong).
- Offer reimplantation or endoscopic correction for frequent breakthrough infections (weak) and surgical repair to children older than one year with high-grade reflux and abnormal renal parenchyma (weak).
- Offer surgical correction if parents prefer definitive therapy to conservative management (strong).[38]
- Treat lower urinary tract dysfunction first when it is found (strong), and manage children aged one to five years conservatively at first (strong).
The AUA guideline (published 2010, amended 2017) treats surgery as an option, not a requirement: open or endoscopic correction may be used, and randomized trials showed fewer febrile UTIs after open repair than with continuous antibiotic prophylaxis. It recommends treating bladder and bowel dysfunction first, preferably before any reflux surgery, and it recommends continuous prophylaxis for children with reflux and bladder and bowel dysfunction while that dysfunction is being treated.[39]
The EAU guideline states that robust prospective trials are lacking, that the evidence is generally low-level, and that reimplantation outperforms endoscopic correction for higher grades. It reports success of 92–98% for open techniques and describes Cohen cross-trigonal reimplantation as the most popular open procedure.[38]
The randomized RIVUR trial evaluated trimethoprim-sulfamethoxazole prophylaxis in 607 children with reflux diagnosed after a first or second febrile or symptomatic urinary tract infection. Recurrent urinary tract infection occurred in 12.9% of children on prophylaxis versus 23.6% on placebo (relative risk 0.55, 95% CI 0.38–0.78), with the largest effect in children with baseline bladder and bowel dysfunction. Renal scarring did not differ significantly (11.9% versus 10.2%). Among children with a first recurrence caused by E. coli, trimethoprim-sulfamethoxazole resistance was more common in isolates from the prophylaxis group (63% versus 19%).[43]
Adult
Adult reimplantation is usually reconstructive rather than antireflux-driven. Indications include:
- Iatrogenic distal ureteral injury during gynecologic, colorectal, urologic, vascular, or pelvic oncologic surgery.[5][10]
- Distal ureteral stricture from prior surgery, stones, radiation, endometriosis, retroperitoneal fibrosis, ischemia, or chronic inflammation.[2][6]
- Distal ureterectomy with reimplantation is included in NCCN's kidney-preserving options for selected distal ureteral urothelial carcinoma.[56] AUA/SUO 2023 prefers this approach for surgically eligible patients with high-risk or unfavorable low-risk UTUC endoscopically confined to the lower ureter in a functional renal unit .[57]
- Partial cystectomy for a select bladder tumor (solitary, without carcinoma in situ, most often at the dome or in a diverticulum) can occasionally require reimplantation when the tumor or resection margin is close enough to a ureteral orifice that the orifice itself must be excised. NCCN does not treat the need for ureteral reimplantation as an absolute contraindication to partial cystectomy.[56]
- Transplant ureteral complications and selected congenital distal ureteral anomalies persisting into adulthood.[2]
Core Principles
These principles guide standard transecting reimplantation; the non-transecting side-to-side variant uses a healthy proximal ureterotomy instead of distal transection and spatulation.[2][5][10][49]
- Reach without tension. If the ureter cannot reach the bladder comfortably, mobilize the bladder, add a psoas hitch, or escalate to a Boari flap.
- Preserve ureteral blood supply. Keep periureteral adventitia and longitudinal vessels intact; avoid skeletonizing the distal ureter.
- Debride to healthy ureter. Ischemic, radiated, scarred, or devitalized distal ureter should not be sewn into the bladder.
- Spatulate the ureter. A wide mucosa-to-mucosa anastomosis reduces the risk of secondary ureterovesical junction obstruction.
- Stent the repair. Most adult reconstructions and many pediatric reimplants are supported with a double-J or externalized stent during early healing.
- Use absorbable suture. Fine 4-0 to 6-0 absorbable suture is typical, scaled to patient size and tissue quality. 7.[44] Create a tunnel when reflux matters. A tunnel-to-ureter diameter ratio of roughly 4-5:1 is the classic antireflux target; a modeling study has questioned whether the traditional 5:1 rule overestimates the tunnel length actually needed.[44]
- Drain and protect the field. Leave a catheter and, for adult open or robotic injury reconstructions, a closed suction drain near the repair. A multicenter comparison of adult robotic versus open reimplantation found a shorter bladder catheter dwell time with the robotic approach on multivariate analysis, without reporting the absolute duration for either group.[6]
The pediatric operation is usually judged by reflux resolution and preservation of bladder function. The adult operation is judged by ureteral patency, renal preservation, leak avoidance, and durability in hostile tissue.
Positioning and Room Setup
Open pediatric intravesical and extravesical reimplantation is performed supine through a low transverse or Pfannenstiel-type incision. For robot-assisted pelvic reimplantation, a technique review of pediatric robotic upper- and lower-tract surgery describes a semilithotomy position with the knees kept low to avoid collision with the robotic arms, the table in Trendelenburg approximately 25 degrees from horizontal, arms tucked at the sides with palms up to protect the ulnar nerve, and a wide egg-crate pad across the chest left loose enough for chest wall movement.[40] Traditional robotic docking places the robot between the legs, which limits access to the perineum and urethra for cystoscopy or stent manipulation during the case; a side-docking position (robot at the patient's side, facing the head) has been described for adult robotic distal ureteral reconstruction specifically to preserve that access.[41]
No reimplantation-specific VTE recommendation exists. Apply the general risk framework (age, obesity, prior VTE, malignancy, prolonged operation or immobility) on the VTE Prophylaxis page; steep Trendelenburg and a longer robotic case (psoas hitch or Boari flap) push toward the higher end of that assessment.
Technique Selection
| Situation | Preferred Technique | Main Trade-off |
|---|---|---|
| Pediatric unilateral VUR | Lich-Gregoir, Cohen, or Politano-Leadbetter | Extravesical is less painful; intravesical is familiar and versatile |
| Pediatric bilateral VUR | Cohen or selected bilateral Lich-Gregoir | Cohen avoids urinary retention concern; Lich-Gregoir reduces cystotomy morbidity in selected hands |
| Primary obstructive megaureter | Reimplantation with or without tapering | Tailoring adds ischemic risk but may be needed for very dilated ureters |
| Adult short distal ureteral loss | Direct ureteroneocystostomy | Refluxing adult reimplant is often acceptable if bladder is low pressure |
| Adult distal/mid defect under tension | Ureteroneocystostomy with psoas hitch | Mobilizes bladder to ureter; avoid genitofemoral nerve injury |
| Longer mid/proximal defect | Boari flap +/- psoas hitch | Uses bladder flap length; requires adequate capacity and tissue quality |
| Marginal ischemic distal ureter | Non-transecting or adventitia-preserving reimplant | Preserves vascular reserve when complete transection is risky |
| Bladder unavailable or frozen pelvis | Transureteroureterostomy, ileal ureter, autotransplantation | Salvage options with higher complexity |
Intravesical Reimplantation
Intravesical operations open the bladder, mobilize the ureteral orifice from within, and create a submucosal tunnel. They are especially familiar in pediatric VUR and duplex-system surgery.[1][11] A 1997 AUA Pediatric Vesicoureteral Reflux Guidelines Panel report pooling outcomes across the literature reported surgical success after open ureteral reimplantation (any technique) in 7,731/8,061 ureters (95.9%, approximately 96%) and 959/1,008 patients (95.1%). In the smaller grade-stratified dataset, success by ureter was grade I 108/109 (99%), II 874/882 (99.1%), III 993/1,010 (98.3%), IV 386/392 (98.5%), and V 155/192 (80.7%).[42]
When bladder capacity limits the tunnel length available after ureteral tailoring or tapering, a spatulated-nipple technique has been described: roughly 2 cm of ureter is brought through the bladder and secured at the hiatus, the distal ureter is spatulated and everted, its margin is sutured to urothelium around the original orifice, and the spatulation is reapproximated more proximally.[45]
Cohen cross-trigonal
The Cohen technique creates a cross-trigonal submucosal tunnel from the native ureteral orifice toward the contralateral bladder wall. The ureter is advanced through the tunnel and matured at the new hiatus.[11][12]
Strengths. Cohen reimplantation has a high reflux-resolution rate, is established worldwide, works well for bilateral VUR and avoids creating a new extravesical hiatus. In a retrospective series of 120 children, success (no postoperative reflux or ureteral obstruction) was 97.8% with the cross-trigonal technique and 96.7% with Politano-Leadbetter.[11]
Limitations. Future retrograde ureteral access can be difficult because the ureteral orifice is relocated across the trigone. Cystotomy is associated with more bladder spasm, hematuria, catheter time and postoperative discomfort than extravesical approaches. The technique is not ideal when preserving orthotopic ureteral access matters.[12][13][14] Case reports describe regaining access after Cohen reimplantation with curved angiographic catheters, angled guidewires, or retrograde ureteroscopy for later stone removal, stent retrieval, or pyelography in selected patients, but no pooled success rate has been reported.[46]
Politano-Leadbetter
Politano-Leadbetter reimplantation creates a new superolateral bladder hiatus and tunnels the ureter submucosally toward a trigonal orifice position. It preserves a more natural ureteral trajectory and facilitates future retrograde access compared with Cohen.[11][15]
Its main penalty is obstruction risk at the new hiatus or tunnel, particularly if the ureter kinks, the tunnel is tight, or the ureter is over-mobilized.[11][15]
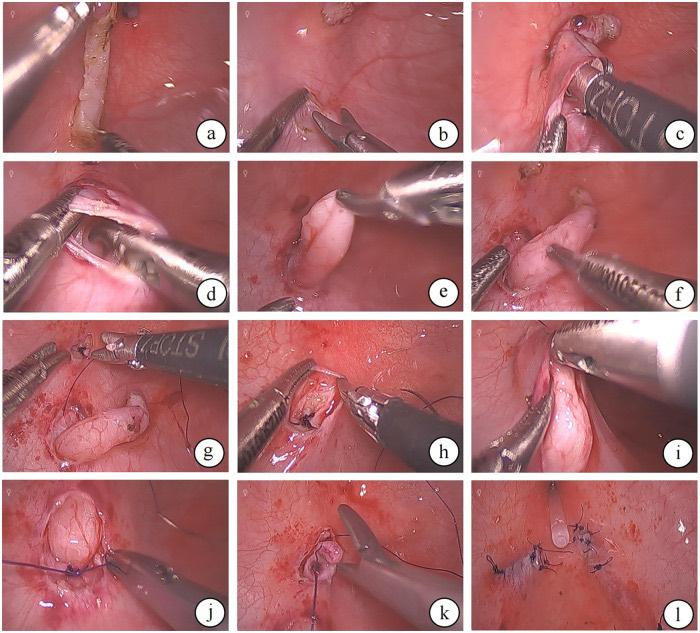
Pneumovesicoscopic Politano-Leadbetter reimplantation. (a) Ureteral mobilization. (b) Mucosal incision about 3 cm superior to the original orifice along the projected ureteral course. (c) Submucosal tunnel from the new hiatus toward the original orifice. (d) Detrusor dissection inferior to the new hiatus to reach the extravesical space. (e) Ureter drawn into the bladder through the new hiatus. (f) Check for kinking or torsion. (g) Closure of the detrusor at the original orifice and assessment of tunnel length. (h) Further mucosal dissection toward the bladder neck to lengthen the tunnel when needed. (i) Ureter passed through the submucosal tunnel. (j) Closure of the detrusor defect at the new hiatus with proximal ureteral fixation. (k) Interrupted ureteral-to-bladder mucosal anastomosis. (l) Final appearance after bilateral fixation. From Huang M, et al. Front Pediatr. 2026;14:1855283, Figure 1 (CC BY 4.0).[58]
Glenn-Anderson
Glenn-Anderson advances the ureter distally along the trigone, maintaining a more orthotopic ureteral course. It is less common than Cohen or Politano-Leadbetter but remains relevant in POM and pneumovesicoscopic variants, where preserving a natural course and limiting kinking are valuable.[16]
Extravesical Reimplantation
Lich-Gregoir
Lich-Gregoir describes extravesical antireflux reconstruction. In classic pediatric reflux repair, detrusorrhaphy lengthens the tunnel while preserving the native ureteral insertion. The EAU 2026 paediatric guideline specifies preoperative cystoscopy before planned Lich-Gregoir repair to assess bladder mucosa and ureteral-orifice position and configuration.[38] Adult distal reconstruction or transplant variants create a new ureterovesical anastomosis within a detrusor trough.[13][17]
Step sequence for the adult reimplantation variant
- Mobilize the distal ureter with periureteral adventitia intact.
- Spatulate the ureter.
- Mobilize the bladder enough to eliminate tension; add psoas hitch if needed.
- Incise detrusor for a 4-5:1 tunnel length while preserving mucosa.
- Open bladder mucosa at the distal end of the trough.
- Perform mucosa-to-mucosa ureterovesical anastomosis. 7.[44] Place a stent.
- Close the detrusor over the ureter without compression.
Advantages. Lich-Gregoir avoids cystotomy. Series report shorter operative time and catheterization, and less hematuria, bladder spasm and postoperative pain than with intravesical repair. It suits robotic adult distal reconstruction and pediatric unilateral VUR.[12][13][14]
Limitations. Bilateral extravesical dissection can transiently impair bladder emptying by disrupting periureteral pelvic plexus fibers. Transient retention followed bilateral robotic extravesical reimplantation in 4/103 patients (3.9%) in one multicenter series.[18] Tunnel length may be limited in small bladders, and the detrusor must not be closed too tightly over a large or tapered ureter.[12][18]
A 2026 meta-analysis of eight retrospective studies (1,314 children) comparing Cohen and Lich-Gregoir in pediatric VUR found shorter operative time, shorter hospitalization, and fewer bladder spasms and less hematuria with Lich-Gregoir. Persistent VUR and UTI did not differ significantly.[12] A randomized trial of 44 children with unilateral VUR found no persistent reflux after either Lich-Gregoir or Politano-Leadbetter. Lich-Gregoir had a shorter operative time (66.7 vs 79.3 min), no gross hematuria and less postoperative pain.[13] In a propensity-matched series of bilateral VUR (14 children per group), Lich-Gregoir had shorter operative time and fewer bladder spasms, with one transient retention and no difference in persistent VUR.[14]
Adult Distal Reconstruction
Adult reimplantation is often performed for injury or stricture rather than reflux.[2][5][10] For traumatic injury distal to the iliac vessels, AUA Statement 12b recommends ureteral reimplantation or primary ureteral repair performed over a stent when feasible (Recommendation; Grade C). Reimplantation is favored when distal-ureter viability is doubtful; a psoas hitch or bladder flap can relieve anastomotic tension.[55] For the adult with persistent or newly recognized primary reflux, reflux nephropathy, or reflux after transplantation or prior reimplantation, see Adult Vesicoureteral Reflux.
For UTUC distal ureterectomy, AUA/SUO 2023 recommends excising the complete distal ureter, including the intramural tunnel and ureteral orifice, and closing the urinary tract watertight . Its ureterectomy discussion calls for assessment of endoscopic tumor extent, bladder capacity and function when Boari flap or bowel reconstruction may be needed, proximal and distal frozen-section margins, avoidance of urinary spillage and a tension-free repair. AUA/SUO recommends a single perioperative intravesical chemotherapy instillation for eligible patients undergoing segmental ureterectomy, including distal ureterectomy, to reduce bladder recurrence .[57] NCCN lists distal ureterectomy and reimplantation with or without perioperative intravesical chemotherapy.[56]
Direct ureteroneocystostomy
Direct reimplant is appropriate when the distal ureteral defect is short and the bladder dome can reach the ureter after mobilization. In low-pressure adult bladders, a refluxing reimplant can be acceptable. A higher-pressure bladder requires treatment of its storage dysfunction; a tunnel alone does not protect the upper tract from an unsafe reservoir.[2][10] Some authors test the completed anastomosis intraoperatively by instilling 200–300 mL of saline into the bladder to check for a leak, though no validated target volume has been established.[48]
Psoas hitch
When direct reimplant is under tension, the bladder is mobilized and fixed to the ipsilateral psoas tendon, bringing the bladder to the ureter rather than pulling the ureter to the bladder.[2][19]
Technical points:
- identify the genitofemoral and femoral nerves when visible; their positions vary, so use superficial psoas muscle bites if no nerves are seen. Femoral palsy requiring suture removal was reported in two children after psoas hitch.[62][63]
- confirm bladder capacity is adequate for the planned reconstruction; for Boari flap, published suggested minimum capacities vary from 150 to 400 mL.[47]
- reimplant into the mobilized bladder dome without tension,
- avoid in severely contracted bladder, hostile frozen pelvis, or neurogenic high-pressure bladder unless the bladder problem is addressed.[2][19]
Boari flap
If psoas hitch is insufficient, a wide-based full-thickness bladder flap is raised, rotated cranially, and tubularized to bridge a longer ureteral gap. It is often combined with a psoas hitch and can reach the mid or even upper ureter in selected patients with adequate bladder capacity.[20][21][22]
Radiation injury, prior pelvic surgery, and reduced bladder capacity are the main constraints. In one retrospective cohort of 29 women after Boari reconstruction, 8 (27.6%) developed new lower urinary tract symptoms during a mean 22.3-month follow-up; oral anticholinergics managed these symptoms effectively.[21]
Transureteroureterostomy
Transureteroureterostomy is a second-line option when the ipsilateral bladder cannot be used and the contralateral ureter is healthy. It is used selectively because it places the contralateral renal unit at risk.[10]
Minimally Invasive and Robotic Reimplantation
Robot-assisted ureteral reimplantation (RALUR) most commonly uses an extravesical Lich-Gregoir-style repair in children and adults. Its value is suturing precision, shorter recovery, and easier bladder mobilization for psoas hitch or Boari flap compared with conventional laparoscopy.[6][18][23]
Pediatric RALUR
A 2026 systematic review and meta-analysis of eight retrospective pediatric studies (n = 546) found similar success and complication rates for robotic and open ureteral reimplantation.[23] RALUR had shorter hospital stay and lower analgesic use but longer operative time.[23] A nine-center series of robotic extravesical reimplantation in 260 children (363 ureters) reported radiographic resolution in 246/280 ureters with postoperative imaging (87.9%); the authors described this as approaching but short of open-surgery results.[18] A retrospective 13-center series of 1,343 children (68% with reflux) reported 96% surgical success at a mean follow-up of 14 months.[24] Median operative time was 202 minutes for robotic and 240 minutes for laparoscopic approaches (p = 0.45), and grade 3 complications occurred in 0.5% and 1.2%.[24]
The EAU 2026 paediatric guideline is more cautious: it reports that pooled robotic results vary widely and on average are poorer than open surgery, with longer operative time, higher cost and more postoperative complications leading to secondary intervention, but less pain and shorter stay. It does not recommend laparoscopic or robotic repair as routine, and offers it as an alternative in centers with established experience.[38] It notes that older children with complex anatomy or a failed injection or open reimplant may benefit from the robotic approach, and advises caution with bilateral repair because of transient retention.[38]
Learning curve remains real. Contemporary pediatric series using CUSUM methods suggest competence and efficiency improve after early case accumulation, with operative times falling as teams standardize port placement, detrusorotomy length, top-down closure, and stent strategy.[25]
Adult robotic reimplantation
Adult robotic reimplantation has become a major option for benign distal strictures and iatrogenic injuries. Retrospective comparative series report shorter hospital stay and catheterization, lower blood loss and comparable or fewer complications than open repair. One multicenter series compared 51 robotic with 79 open repairs, and one single-center series compared 21 with 28.[6][26] A 2025 meta-analysis pooled four retrospective cohorts (141 robotic, 117 open): three cohorts (128/258 patients) involved post-cystectomy ureteroenteric revisions, and the fourth also included ureteroureterostomy.[61] In this mixed population, robotic repair was associated with fewer recorded complications (RR 0.40, 95% CI 0.17–0.91) and a shorter hospital stay (mean difference 4.97 days); reintervention did not differ significantly.[61] Median follow-up across studies ranged from 12 to 23.5 months.[61] Robotic psoas hitch and Boari flap have been described for longer distal defects when bladder capacity and tissue quality permit; one retrospective single-center series included 37 patients (81% psoas hitch, 19% Boari flap) with median follow-up of 24 months.[20]
For a marginally vascularized distal ureter, a robotic nontransecting side-to-side technique has been described in a small case series: a ureterotomy proximal to the diseased segment is anastomosed side-to-side to a cystotomy with two running monofilament sutures, avoiding extensive posterior ureterovesical-junction dissection; it can be combined with a psoas hitch or Boari flap. A 2024 retrospective CORRUS cohort reported unadjusted success in 56/61 side-to-side, 143/155 refluxing transecting and 20/21 non-refluxing reimplants; the side-to-side group had more prior radiation and a median follow-up of 7.1 months, so comparative effectiveness remains uncertain.[49][60] A direct transvesical robotic technique has also been described, particularly for ureterovaginal fistula: the bladder is filled with 200 mL saline and mobilized by dividing the medial umbilical ligaments, a cystotomy is made, and after ureteral spatulation the ureter is anchored to detrusor and anastomosed mucosa-to-mucosa over a stent before the cystotomy is closed.[50]
Pneumovesicoscopic reimplantation
Pneumovesicoscopic reimplantation places ports directly into the bladder and performs a Cohen, Politano-Leadbetter, or modified Glenn-Anderson repair under CO2 cystoscopy. It reduces incision morbidity but is technically demanding, takes longer early in experience, and is limited by small bladder working space.[16][27]
Endoscopic Injection for VUR
Dextranomer/hyaluronic acid copolymer (Deflux) is injected beneath or within the ureteral tunnel to coapt the ureteral orifice.[28][29]
| Technique | Concept | Best Use |
|---|---|---|
| STING | Subureteric injection below the orifice | Lower-grade reflux, straightforward anatomy |
| HIT | Intraureteral injection under hydrodistention | Higher-grade reflux, coaptation of the distal tunnel |
The AUA guideline meta-analysis reports reflux resolution in 98.1 per 100 children after open surgery (95% CI 95.1–99.1) and 83.0 per 100 after a single injection of bulking agent (95% CI 69.1–91.4), with limited data on durability.[39] Injection avoids hospitalization and can be repeated.[39] One single-center series of 1,551 children with mostly grade III–IV reflux reported resolution after the first injection in 87.1% of ureters.[29] Success is grade-dependent and reduced by bladder-bowel dysfunction. In the AUA meta-analysis, initial endoscopic resolution was 50% with and 89% without bladder-bowel dysfunction, while open surgery resolved 97% in both groups.[28][29][39]
A Cochrane review of 34 randomized trials (4,001 children) found little or no difference in febrile UTI at one to two years in the three-trial, 254-child comparison of endoscopic injection with or without antibiotics versus antibiotics alone (RR 0.74, 95% CI 0.31–1.78; low-certainty evidence).[30] It concluded that the added benefit of surgical or endoscopic correction over antibiotics alone remains unclear. Surgery plus antibiotics may reduce repeat febrile UTI (RR 0.43, moderate-certainty evidence), without a difference in new kidney defects. Injection is a minimally invasive reflux-correction option; trials have not shown that it prevents renal scarring.[30]
Primary Obstructive Megaureter
Primary obstructive megaureter is often observed, but surgery is indicated when obstruction declares itself clinically or functionally.[7][8] The British Association of Paediatric Urologists' 2014 consensus identified febrile urinary tract infection or pain, an initial differential renal function below 40% (especially with massive hydroureteronephrosis), worsening dilation during conservative management, or a decline of 5% in differential renal function on serial renograms as indicators for considering surgery.[51] A prospective observational series of conservatively managed primary non-refluxing megaureters found complete resolution in 76% of 26 ureteric units with an initial diameter under 10 mm (median time to resolution 60 months), versus 17% of 24 units with a diameter of 10 mm or more (median time to resolution 102 months); stones and declining renal function were more common in the larger-diameter group.[52]
Operative choices:
- Endoscopic balloon dilatation or ureterovesical-junction incision can be considered for selected children with persistent or progressive POM, particularly when reimplantation into a small infant bladder is difficult. An EAU panel systematic review found no randomized trials and variable success definitions; some children subsequently required salvage reimplantation.[64]
- Reimplant without tapering when the ureteral diameter is modest and a nonobstructing tunnel can be created.
- Excisional tapering when the ureter is too large to tunnel safely without obstruction. A free-hand technique limits tapering to the intramural ureter: a 10- or 12-Fr catheter and marking sutures define the segment, adventitial flaps are raised to that level, the intervening ureteral strip is excised, and the ureter is re-anastomosed full-thickness with the adventitia re-approximated, avoiding the bulkier intravesical mass that can follow folding tapering.[53]
- Plication tapering when preserving blood supply is prioritized. Folding around an 8- or 10-Fr catheter (sized to the patient) with interrupted absorbable sutures suits a moderately dilated ureter under about 1.75 cm in diameter; a larger ureter may remain bulky and difficult to reimplant even after folding.[54]
- Refluxing ureterovesicostomy has been used in selected infants or small bladders where definitive reimplantation may be disproportionate.[31][32][33] In one retrospective series, 7/47 children (15%) underwent reimplantation or takedown by a median 43-month follow-up.[31][32][33]
Tailoring adds dissection, ischemic risk and obstruction risk. In a retrospective series of 383 children, tailoring-tapering-folding, obstructing megaureter (>9 mm), duplex anatomy and refractory voiding dysfunction were independent predictors of complications.[34] In a comparative series of 53 patients with 65 excisionally tapered megaureters (31 obstructive and 34 refluxing renal units), success (improved hydronephrosis without reflux) was reached in 86% of intravesical and 76% of extravesical reimplants. Patients with preoperative reflux or voiding dysfunction appeared to benefit from an intravesical approach, and younger age was associated with poorer outcomes regardless of technique.[31]
Complications
Most complications are minor, but the operation has a few predictable failure modes.[15][34][35][36]
| Complication | Pattern |
|---|---|
| Postoperative hydronephrosis | Common early; usually transient, especially after high-grade reflux or megaureter repair |
| Febrile UTI | Most common in the first postoperative year; risk increases with bladder-bowel dysfunction and residual obstruction |
| Secondary ureterovesical junction obstruction | More concerning after tight tunnels, Politano-Leadbetter hiatus, tapering or ischemic ureter |
| Persistent or recurrent VUR, including symptomatic adult reflux | Usually low-frequency after open pediatric repair; higher in early robotic or endoscopic series. After adult refluxing reimplantation, reflux may cause voiding-related flank pain or recurrent UTI and occasionally prompt non-refluxing revision.[59] |
| Urinary retention | Classic concern after bilateral extravesical dissection |
| Bladder spasms and hematuria | More common after intravesical/cystotomy approaches |
| Contralateral de novo VUR | Usually low-grade and often transient |
| Leak or urinoma | Suggests anastomotic tension, devascularization, distal obstruction, or stent malfunction |
Early ultrasound is often abnormal. In a single-surgeon series, new or worse hydronephrosis occurred in 27.6% of ureters after robotic and 30.8% after open reimplantation, and resolved in 91.4% and 75%, with no intervention required. Postoperative hydronephrosis is interpreted with symptoms, febrile UTI, renal function and interval trend.[35]
Follow-up
Routine follow-up usually includes renal and bladder ultrasound after catheter or stent removal. The AUA guideline sets renal ultrasound after open or endoscopic reflux surgery as a standard, to look for obstruction (postoperative obstruction 0.4 per 100 children in the meta-analysis). It recommends voiding cystography after endoscopic injection and lists it as an option after open reimplantation. After open repair, VCUG or nuclear imaging is often reserved for recurrent febrile UTI, worsening hydronephrosis, concerning renal function, or institutional pediatric protocols.[15][39]
In a retrospective series of 34 children (53 renal units) followed for at least 10 years, children with an uncomplicated first year and no obstruction had a low risk of late complications. Postoperative ureterovesical junction obstruction occurred in 4/53 units (7.5%) among 34 children meeting a minimum 10-year follow-up criterion; all four obstructions followed Politano-Leadbetter repair and were diagnosed seven to nine months postoperatively.[15] The authors suggest extended follow-up for Politano-Leadbetter repair, girls and preoperative reflux nephropathy.[15] In a two-center series of 69 children followed for a mean of 17.5 years, none had recurrent reflux, obstruction or de novo VUR.[36] For symptomatic toilet-trained children with grade IV–V reflux, abnormal kidneys and no lower urinary tract dysfunction, the EAU 2026 risk table lists postoperative VCUG only on indication and kidney-status follow-up until after puberty.[38] Extended surveillance is also used after POM, recurrent UTI, voiding dysfunction, solitary kidney and complex adult reconstruction.[37]
Operative Pearls
- Reach beats force. If the ureter barely reaches, add a psoas hitch or Boari flap.
- Do not skeletonize the ureter. Adventitial blood supply is the repair's margin of safety.
- Tunnel size matters. Too short refluxes; too tight obstructs.
- Bilateral extravesical repair can impair bladder emptying. Preserve periureteral nerves and counsel about transient retention.
- Adult refluxing reimplant is sometimes acceptable. Patency and tension-free healing may matter more than a perfect tunnel in a low-pressure adult bladder.
- Megaureter tapering should be deliberate. Tailor only when the ureter is too large for a safe nonobstructing tunnel.
- A hostile bladder changes the ladder. Radiation, small capacity, neurogenic high pressure, or frozen pelvis may push the surgeon toward augmentation, bowel substitution, TUU, or autotransplantation.
Videos
References
1. Tullus K. Vesicoureteric reflux in children. Lancet. 2015;385(9965):371-379. doi:10.1016/S0140-6736(14)60383-4
2. White C, Stifelman M. Ureteral reimplantation, psoas hitch, and Boari flap. J Endourol. 2020;34(S1):S25-S30. doi:10.1089/end.2018.0750
3. Peters CA, Skoog SJ, Arant BS Jr, et al. Summary of the AUA guideline on management of primary vesicoureteral reflux in children. J Urol. 2010;184(3):1134-1144. doi:10.1016/j.juro.2010.05.065
4. Montini G, Tullus K, Hewitt I. Febrile urinary tract infections in children. N Engl J Med. 2011;365(3):239-250. doi:10.1056/NEJMra1007755
5. de'Angelis N, Schena CA, Marchegiani F, et al. 2023 WSES guidelines for the prevention, detection, and management of iatrogenic urinary tract injuries during emergency digestive surgery. World J Emerg Surg. 2023;18(1):45. doi:10.1186/s13017-023-00513-8
6. Ziewers S, Dotzauer R, Thomas A, et al. Robotic-assisted vs. open ureteral reimplantation: a multicentre comparison. World J Urol. 2024;42(1):194. doi:10.1007/s00345-024-04875-9
7. Lopez M, Perez-Etchepare E, Bustangi N, et al. Laparoscopic extravesical reimplantation in children with primary obstructive megaureter. J Laparoendosc Adv Surg Tech A. 2023;33(7):713-718. doi:10.1089/lap.2019.0396
8. Rivetti G, Marzuillo P, Guarino S, et al. Primary non-refluxing megaureter: natural history, follow-up and treatment. Eur J Pediatr. 2024;183(5):2029-2036. doi:10.1007/s00431-024-05494-7
9. Kirsch AJ, Cooper CS, Lackgren G. Non-animal stabilized hyaluronic acid/dextranomer gel (NASHA/Dx, Deflux) for endoscopic treatment of vesicoureteral reflux: what have we learned over the last 20 years? Urology. 2021;157:15-28. doi:10.1016/j.urology.2021.07.032
10. Drain A, Jun MS, Zhao LC. Robotic ureteral reconstruction. Urol Clin North Am. 2021;48(1):91-101. doi:10.1016/j.ucl.2020.09.001
11. Burbige KA. Ureteral reimplantation: a comparison of results with the cross-trigonal and Politano-Leadbetter techniques in 120 patients. J Urol. 1991;146(5):1352-1353. doi:10.1016/S0022-5347(17)38090-4
12. Wang M, Xi Y, Huang N, Zhang L, Liu J. Comparative efficacy and safety of Cohen versus Lich-Gregoir ureteral reimplantation in pediatric vesicoureteral reflux: a systematic review and meta-analysis. PeerJ. 2026;14:e20636. doi:10.7717/peerj.20636
13. Schwentner C, Oswald J, Lunacek A, et al. Lich-Gregoir reimplantation causes less discomfort than Politano-Leadbetter technique: results of a prospective, randomized, pain scale-oriented study in a pediatric population. Eur Urol. 2006;49(2):388-395. doi:10.1016/j.eururo.2005.11.015
14. Fujii T, Satoh H, Sato A, et al. Lich-Gregoir vs. Cohen ureteral re-implantation surgery for bilateral vesicoureteral reflux: a propensity score analysis. Pediatr Int. 2025;67(1):e70010. doi:10.1111/ped.70010
15. Gerwinn T, Zellner M, Prouza A, et al. Long-term follow-up after ureteral reimplantation in children: a 12-year analysis. Pediatr Surg Int. 2025;41(1):95. doi:10.1007/s00383-025-05992-1
16. Pan H, Wang R, Jiang M, et al. Long-term efficacy and learning curves of Cohen and modified Glenn-Anderson pneumovesicoscopic ureteral reimplantation for primary obstructive megaureter: a retrospective cohort study with meta-analysis. Pediatr Surg Int. 2026;42(1):164. doi:10.1007/s00383-026-06404-8
17. Hudry D, El Hajj H, Narducci F, Leblanc E. Laparoscopic ureteral reimplantation applying the modified psoas hitch and Lich-Gregoir onlay technique: a 10-step surgical video. Int Urogynecol J. 2022;33(9):2577-2579. doi:10.1007/s00192-021-04990-w
18. Boysen WR, Ellison JS, Kim C, et al. Multi-institutional review of outcomes and complications of robot-assisted laparoscopic extravesical ureteral reimplantation for treatment of primary vesicoureteral reflux in children. J Urol. 2017;197(6):1555-1561. doi:10.1016/j.juro.2017.01.062
19. Riedmiller H, Becht E, Hertle L, Jacobi G, Hohenfellner R. Psoas-hitch ureteroneocystostomy: experience with 181 cases. Eur Urol. 1984;10(3):145-150. doi:10.1159/000463777
20. Dell'Oglio P, Palagonia E, Wisz P, et al. Robot-assisted Boari flap and psoas hitch ureteric reimplantation: technique insight and outcomes of a case series with at least 1 year of follow-up. BJU Int. 2021;128(5):625-633. doi:10.1111/bju.15421
21. Hardesty JK, Burns RT, Soyster ME, Jansen NE, Mellon M. Female bladder dysfunction following Boari bladder flap ureteral reconstruction. Urology. 2024;186:31-35. doi:10.1016/j.urology.2024.01.020
22. Andrade C, Narducci F, Bresson L, Leblanc E. Boari flap ureteroneocystostomy in an oncological patient. Gynecol Oncol. 2016;143(1):193. doi:10.1016/j.ygyno.2016.07.115
23. Gazzaneo M, Bosisio M, Mandarano G, Boroni G, Alberti D. Comparative outcomes of open and robotic ureteral reimplantation in children with vesicoureteral reflux: a systematic review and meta-analysis. J Pediatr Surg. 2026;61(3):162883. doi:10.1016/j.jpedsurg.2025.162883
24. Chertin L, Kocherov S, Bakaleyshchik P, et al. Laparoscopic and robot-assisted laparoscopic reimplantation for lower ureter pathology: a multi-institutional comparative study in 1343 patients. Urology. 2024;186:166-171. doi:10.1016/j.urology.2024.02.021
25. Shengkun S, Xin L, Xiaoming Y, et al. Mastering the learning curve with quality assurance: outcomes of robot-assisted ureteral reimplantation in a pediatric cohort. J Pediatr Surg. 2026;61(5):162941. doi:10.1016/j.jpedsurg.2026.162941
26. Carbonara U, Branche B, Cisu T, et al. Robot-assisted ureteral reimplantation: a single-center comparative study. J Endourol. 2021;35(10):1504-1511. doi:10.1089/end.2021.0083
27. Canon SJ, Jayanthi VR, Patel AS. Vesicoscopic cross-trigonal ureteral reimplantation: a minimally invasive option for repair of vesicoureteral reflux. J Urol. 2007;178(1):269-273. doi:10.1016/j.juro.2007.03.059
28. Escolino M, Kalfa N, Castagnetti M, et al. Endoscopic injection of bulking agents in pediatric vesicoureteral reflux: a narrative review of the literature. Pediatr Surg Int. 2023;39(1):133. doi:10.1007/s00383-023-05426-w
29. Puri P, Kutasy B, Colhoun E, Hunziker M. Single center experience with endoscopic subureteral dextranomer/hyaluronic acid injection as first line treatment in 1,551 children with intermediate and high grade vesicoureteral reflux. J Urol. 2012;188(4 Suppl):1485-1489. doi:10.1016/j.juro.2012.02.023
30. Williams G, Hodson EM, Craig JC. Interventions for primary vesicoureteric reflux. Cochrane Database Syst Rev. 2019;2:CD001532. doi:10.1002/14651858.CD001532.pub5
31. DeFoor W, Minevich E, Reddy P, et al. Results of tapered ureteral reimplantation for primary megaureter: extravesical versus intravesical approach. J Urol. 2004;172(4 Pt 2):1640-1643. doi:10.1097/01.ju.0000138529.43179.dd
32. Khondker A, Rickard M, Kim JK, et al. Should a refluxing internal diversion be considered a temporizing procedure? Extended follow-up and outcomes after side-to-side ureterovesicostomy for primary obstructive megaureter in young children. J Urol. 2024;212(1):196-204. doi:10.1097/JU.0000000000003966
33. Mittal S, Srinivasan A, Bowen D, et al. Utilization of robot-assisted surgery for the treatment of primary obstructed megaureters in children. Urology. 2021;149:216-221. doi:10.1016/j.urology.2020.10.015
34. Suer E, Ozcan C, Mermerkaya M, et al. Can factors affecting complication rates for ureteric re-implantation be predicted? Use of the modified Clavien classification system in a paediatric population. BJU Int. 2014;114(4):595-600. doi:10.1111/bju.12746
35. Babajide R, Andolfi C, Kanabolo D, Wackerbarth J, Gundeti MS. Postoperative hydronephrosis following ureteral reimplantation: clinical significance and importance of surgical technique and experience. J Pediatr Surg. 2023;58(3):574-579. doi:10.1016/j.jpedsurg.2022.07.002
36. Neeman BB, Kocherov S, Jaber J, et al. Long term results of non-refluxing ureteral reimplantation in the pediatric population. Pediatr Surg Int. 2023;39(1):173. doi:10.1007/s00383-023-05466-2
37. Diamond DA, Chan IHY, Holland AJA, et al. Advances in paediatric urology. Lancet. 2017;390(10099):1061-1071. doi:10.1016/S0140-6736(17)32282-1
38. European Association of Urology. EAU Guidelines on Paediatric Urology: Vesicoureteric Reflux (section 17). 2026 limited update, March 2026. Guideline.
39. Peters CA, Skoog SJ, Arant BS Jr, et al. Management and Screening of Primary Vesicoureteral Reflux in Children. American Urological Association; published 2010, amended 2017.
40. Chang C, Steinberg Z, Shah A, Gundeti MS. Patient positioning and port placement for robot-assisted surgery. J Endourol. 2014;28(6):631-638. doi:10.1089/end.2013.0733
41. Slater RC, Farber NJ, Riley JM, Shilo Y, Ost MC. Contemporary series of robotic-assisted distal ureteral reconstruction utilizing side docking position. Int Braz J Urol. 2015;41(6):1154-1159. doi:10.1590/S1677-5538.IBJU.2014.0601
42. Elder JS, Peters CA, Arant BS Jr, et al. Pediatric Vesicoureteral Reflux Guidelines Panel summary report on the management of primary vesicoureteral reflux in children. J Urol. 1997;157(5):1846-51. doi:10.1016/s0022-5347(01)64882-1
43. RIVUR Trial Investigators, Hoberman A, Greenfield SP, Mattoo TK, et al. Antimicrobial prophylaxis for children with vesicoureteral reflux. N Engl J Med. 2014;370(25):2367-2376. doi:10.1056/NEJMoa1401811
44. Kalayeh K, Fowlkes JB, Schultz WW, Sack BS. The 5:1 rule overestimates the needed tunnel length during ureteral reimplantation. Neurourol Urodyn. 2021;40(1):85-94. doi:10.1002/nau.24526
45. Peard LM, Pope JC IV. Ureteroneocystostomy. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:276-291.
46. De Castro R, Hubert KC, Palmer JS. Retrograde ureteral access after cross-trigonal ureteral reimplantation: a straightforward technique. J Pediatr Urol. 2011;7(1):57-60. doi:10.1016/j.jpurol.2010.02.004
47. Knight RB, Hudak SJ, Morey AF. Strategies for open reconstruction of upper ureteral strictures. Urol Clin North Am. 2013;40(3):351-361. doi:10.1016/j.ucl.2013.04.005
48. Attalla K, Sfakianos JP. Injury Repair of Pelvic Ureter. In: Hoffman M, Hull TL, Bochner BH, eds. Major Complications of Female Pelvic Surgery: A Multidisciplinary Approach. Springer; 2025:167-173.
49. Slawin J, Patel NH, Lee Z, et al. Ureteral reimplantation via robotic nontransecting side-to-side anastomosis for distal ureteral stricture. J Endourol. 2020;34(8):836-839. doi:10.1089/end.2019.0877
50. Sayegh AS, Rangel E, Sotelo R. Ureterovaginal Fistula. In: Sotelo R, Polotti CF, Arriaga J, eds. Urinary Fistula. Springer; 2022:151-158.
51. Farrugia MK, Hitchcock R, Radford A, et al. British Association of Paediatric Urologists consensus statement on the management of the primary obstructive megaureter. J Pediatr Urol. 2014;10(1):26-33. doi:10.1016/j.jpurol.2013.09.018
52. Ranawaka R, Hennayake S. Resolution of primary non-refluxing megaureter: an observational study. J Pediatr Surg. 2013;48(2):380-383. doi:10.1016/j.jpedsurg.2012.11.017
53. DeFoor WR Jr, Sheldon CA. Surgical management of primary vesicoureteral reflux and megaureters. In: Montague DK, Gill IS, Angermeier KW, Ross JH, eds. Textbook of Reconstructive Urologic Surgery. Informa Healthcare; 2008:226-234.
54. Fretz PC, Austin JC, Cooper CS, Hawtrey CE. Long-term outcome analysis of Starr plication for primary obstructive megaureters. J Urol. 2004;172(2):703-705. doi:10.1097/01.ju.0000129301.54906.ca
55. Morey AF, Broghammer JA, Hollowell CMP, et al. Urotrauma Guideline 2020: AUA Guideline. J Urol. 2021;205(1):30–35. doi:10.1097/JU.0000000000001408. Full guideline, published 2014; amended April 2017 and August 2020.
56. National Comprehensive Cancer Network. NCCN Clinical Practice Guidelines in Oncology: Bladder Cancer. Version 3.2026. August 6, 2026. BL-B 2 and 4 of 4; UTT-3; Discussion MS-19, MS-45. Guideline.
57. Coleman JA, Clark PE, Bixler BR, et al. Diagnosis and Management of Non-Metastatic Upper Tract Urothelial Carcinoma: AUA/SUO Guideline. J Urol. 2023;209(6):1071-1081. doi:10.1097/JU.0000000000003480
58. Huang M, Zhang T, Wang C, Dai S, Xia H, Cao X, et al. Pneumovesicoscopic ureteral reimplantation for pediatric vesicoureteral reflux: Politano-Leadbetter vs. Cohen technique. Front Pediatr. 2026;14:1855283. doi:10.3389/fped.2026.1855283
59. Rosenfeld J, Boehm D, Raikar A, et al. "A review of complications after ureteral reconstruction." Asian J Urol. 2024;11(3):348-356. doi:10.1016/j.ajur.2024.02.007
60. Zhao K, Lee M, Raver M, et al. "Techniques for ureteral reimplantation for distal disease." Urol Video J. 2024;24:100288. doi:10.1016/j.urolvj.2024.100288
61. Hassan AA, Mady AM, Abozied H, et al. "Robotic assisted vs. open ureteral reimplantation in adults: a systematic review and meta-analysis." J Robot Surg. 2025;19(1):373. doi:10.1007/s11701-025-02511-1
62. Crook TJ, Steinbrecher HA, Tekgul S, Malone PSJ. "Femoral nerve neuropathy following the psoas hitch procedure." J Pediatr Urol. 2007;3(2):145-147. doi:10.1016/j.jpurol.2006.06.009
63. Maldonado PA, Slocum PD, Chin K, Corton MM. "Anatomic relationships of psoas muscle: clinical applications to psoas hitch ureteral reimplantation." Am J Obstet Gynecol. 2014;211(5):563.e1-563.e6. doi:10.1016/j.ajog.2014.07.008
64. Skott M, Gnech M, 't Hoen LA, et al. "Endoscopic dilatation/incision of primary obstructive megaureter. A systematic review. On behalf of the EAU paediatric urology guidelines panel." J Pediatr Urol. 2024;20(1):47-56. doi:10.1016/j.jpurol.2023.09.005