Ureterocalicostomy
Ureterocalicostomy is a proximal upper-tract reconstruction in which the ureter is anastomosed directly to a lower pole renal calix, bypassing the renal pelvis and ureteropelvic junction (UPJ). It is usually a salvage operation for recurrent or complex UPJ obstruction when a redo pyeloplasty would be unsafe, under tension, or anatomically impossible.[1][2][3]
For the default UPJ operation, see Pyeloplasty. For the disease workup, see UPJ Obstruction. For reconstruction selection principles, see Upper Tract Reconstruction Principles.
Core Principle
The operation works by abandoning the scarred or inaccessible renal pelvis and creating a new dependent drainage route from the lower pole calix to the ureter. The lower pole parenchyma is amputated or deeply incised until caliceal mucosa is visible, the ureter is spatulated, and a wide mucosa-to-mucosa ureterocaliceal anastomosis is created over a ureteral stent.[1][2][4]
The technical concept is true caliceal exposure. Anastomosing ureter to raw renal parenchyma invites tissue ingrowth, restenosis, bleeding, leak, and failure; durable ureterocalicostomy requires visible caliceal mucosa, mucosal approximation, dependent geometry, and no tension.[1][4]
Indications
Ureterocalicostomy is considered when the proximal collecting system cannot be reconstructed reliably with a standard ureteropelvic anastomosis.[1][3][5]
| Scenario | Why Ureterocalicostomy Helps |
|---|---|
| Failed pyeloplasty or failed endopyelotomy | Bypasses peripelvic fibrosis; this was the most common adult indication in the contemporary 72-patient cohort (48.6%)[3] |
| Completely intrarenal or minimal renal pelvis | Avoids trying to create a new UPJ from an inaccessible pelvis[6][7] |
| Short proximal ureter | The lower pole calix provides a lower, more dependent target than the renal pelvis[2] |
| Secondary UPJ obstruction after pyelolithotomy or PCNL | Bypasses post-stone-surgery scarring; 33.3% of the adult contemporary cohort had this indication[3] |
| Iatrogenic UPJ or proximal ureteral injury | Salvage option when direct ureteropelvic repair is not feasible[5] |
| Proximal ureteral stricture refractory to endoscopic management | Useful when the stricture is close to the hilum and the pelvis is scarred or diminutive[4][10] |
| Fusion, rotation, or ascent anomaly with UPJ obstruction | Can bypass difficult pelvic geometry in horseshoe or malrotated kidneys[1] |
| Reversed caliceopelvic ratio | Severe calicectasis with little usable pyelectasis favors a caliceal target[5] |
Where it fits in the salvage ladder. Most recurrent UPJ obstructions still deserve redo pyeloplasty if there is a usable renal pelvis and healthy ureter. Ureterocalicostomy becomes attractive when the renal pelvis is intrarenal, obliterated, or densely scarred; the lower pole calix is more accessible than the old UPJ; and renal function remains worth preserving.
Contraindications and Caution Zones
Ureterocalicostomy cannot restore useful drainage to a kidney with too little functioning parenchyma.[3]
Avoid or reconsider the operation when:
- split renal function or single-kidney GFR is too poor to justify reconstruction,
- cortical thickness is severely attenuated (<5 mm predicted failure in the largest adult cohort),
- active infection is uncontrolled,
- the lower pole calix is not reachable without excessive parenchymal bleeding or ischemia,
- distal ureteral length or vascularity is inadequate,
- the patient would be better served by nephrectomy, chronic drainage, ileal ureter, or renal autotransplantation.
In the largest adult cohort, GFR <20 mL/min/1.73 m² and cortical thickness <5 mm were independent predictors of failure; serum creatinine >1.7 mg/dL was associated with failure on univariate analysis only.[3]
Preoperative Planning
Preoperative planning should answer four questions:
- Is the renal unit salvageable? Use MAG3/DTPA renography, cortical thickness, symptoms, infection history, and patient goals. No single function threshold determines salvageability; interpret the renogram with cortical thickness, drainage, symptoms and the consequences of losing the renal unit.[3]
- Is the renal pelvis usable? CT urography, MR urography, retrograde pyelography, and operative history determine whether redo pyeloplasty is realistic or whether the pelvis is intrarenal, scarred, or inaccessible.[6][7]
- Where is the best caliceal target? The lower pole is preferred because it is dependent, often dilated, and anatomically reachable after lower pole parenchymal amputation. Confirm that the intended calix communicates with the remaining collecting system; an unrecognized stenotic or blind-ending lower-pole infundibulum caused failure in one patient in a retrospective series.[15]
- Is the ureter healthy enough? The ureter must be well vascularized, mobile enough for a tension-free anastomosis, and free of distal disease that would make a caliceal repair pointless.
Drainage with a ureteral stent or nephrostomy is reasonable before definitive repair when infection, renal functional uncertainty, severe obstruction, or reoperative anatomy needs stabilization.
Congenital infundibulopelvic stenosis is a rare cause of dilated calices with diminutive infundibula and renal pelvis, distinct from typical UPJ obstruction; the authors intervened in three cases with progressive hydronephrosis or worsening renal insufficiency. In a small case series, later cases were managed with preoperative three-dimensional MR-urography mapping of the dilated calyceal system to plan selective calicocalicostomies draining to a lower-pole ureterocalicostomy, rather than the multiple infundibuloplasties used in an earlier case.[14]
Surgical Technique
Ureterocalicostomy can be performed open, laparoscopically, or robotically.[2][4][7] Preserve ureteral blood supply, expose caliceal mucosa, spatulate the ureter widely, stent the repair, and create a watertight dependent anastomosis.[2][4][7]
Exposure
- Position and access depend on side, prior surgery, body habitus, and surgeon experience.
- Mobilize the kidney enough to expose the lower pole and renal pelvis region.
- Mobilize the proximal ureter with minimal adventitial stripping.
- Identify the old UPJ, crossing vessels, stones, clips, scar, or prior repair if safely visible.
Ureteral preparation
- For the dismembered sequence described below, divide the UPJ or proximal ureter at healthy tissue; a retrospective laparoscopic series also described 7 of 24 termino-lateral repairs without ureteral transection.[15]
- Close or ligate the renal pelvic side when a pelvis remnant remains.
- Spatulate the distal ureter generously, usually laterally or posterior-laterally depending on its orientation to the lower pole calix.
- Confirm that the ureter reaches the lower pole calix without tension or twist.
Lower pole caliceal exposure
The lower pole parenchyma is amputated, guillotined, or deeply incised until the caliceal lumen and mucosa are clearly exposed.[1][4] In a chronically obstructed kidney, the cortex may be thin and bleeding limited; with a thicker cortex, hemostasis and precise calix identification can be more difficult. In four pediatric robotic cases, Adamic et al. described flexible nephroscopy through the renal pelvis with needle puncture toward the scope light to locate a dependent calix, and noted that hilar control may be needed for substantial cortical bleeding.[11]
Technical goals:
- remove enough parenchyma to prevent tissue overgrowth across the anastomosis,
- preserve as much functioning lower pole tissue as possible,
- control bleeding before sewing; Adamic et al. caution that harmonic-scalpel heat near the collecting system can cause tissue necrosis, urine leak, and anastomotic breakdown.[11]
- avoid closing the caliceal opening with hemostatic sutures,
- keep the caliceal mucosa visible throughout the anastomosis.
Some earlier operative descriptions call for complete lower-pole amputation.[12] A deep incision exposing caliceal mucosa while preserving functioning parenchyma has also been described in four pediatric robotic cases when it exposes the calix adequately.[11] A retrospective 37-patient cohort associated partial lower-pole resection with poorer outcomes, but partial resection was selected for parenchyma <10 mm and complete resection for parenchyma >10 mm.[16]
Anastomosis
- Place the most dependent corner stitch between the ureteral spatulation apex and the exposed caliceal mucosa.
- Sew the posterior wall with interrupted or running fine absorbable suture, commonly 4-0 or 5-0 depending on tissue size.
- Place a double-J ureteral stent across the repair.
- Complete the anterior wall as a mucosa-to-mucosa anastomosis.
- Confirm that the ureter is not kinked, twisted, narrowed by parenchyma, or under tension.
- Drain the operative field when leak risk or reoperative scarring warrants it.
Gill et al. removed stents at 5 and 8 weeks in two laparoscopic cases; timing is individualized by tissue quality, leak risk, and surgeon preference.[2]
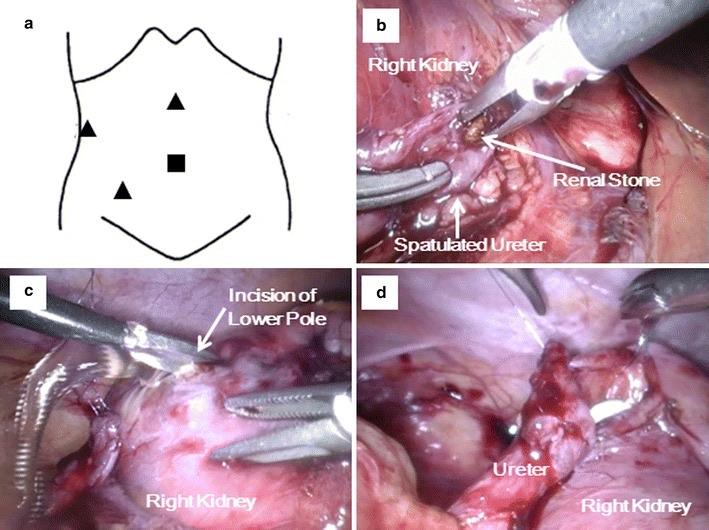
Laparoscopic right ureterocalicostomy. (a) A 12 mm umbilical camera port (square) and three 5 mm working ports (triangles). (b) Pyelolithotomy without lithotripsy through the ureteral incision, with the spatulated ureter labeled. (c) Incision of the lower pole without renal pedicle clamping. (d) Ureterocaliceal anastomosis over a double-J ureteral stent. From Nishimura Y, et al. BMC Res Notes. 2017;10(1):247, Fig. 2 (CC BY).[6]
Close the renal capsule over the cut parenchymal surface when feasible, but avoid closing it close to the ureterocaliceal anastomosis itself, because the capsule can externally compress and narrow the new lumen; protecting the anastomosis with perinephric fat or a peritoneal or omental flap has been described instead.[13]
Failure mode. The common technical failure is an anastomosis to a small caliceal window surrounded by residual renal parenchyma. If parenchyma remains proud around the repair, healing can narrow the ureterocaliceal opening. The target should be generous, dependent, mucosa-lined, and connected to the remaining collecting system; even a patent anastomosis may not drain a markedly capacious pelvis.[11][15]
Surgical Approaches
| Approach | Role | Technical Notes | Evidence Signal |
|---|---|---|---|
| Open | Traditional reference operation, especially for hostile reoperative fields | Best tactile exposure and vascular control; longer incision and recovery | Pediatric series report approximately 90% good or excellent outcomes (Radford et al. included one laparoscopically assisted case)[1][9] |
| Laparoscopic | Minimally invasive duplication of open principles | Requires advanced intracorporeal suturing and caliceal exposure; initial reports demonstrated feasibility | Gill et al. reported the first laparoscopic experience in 2004 (2 patients)[2] |
| Robot-assisted | An option where robotic reconstruction expertise is available; comparative superiority is unproven | Wristed suturing helps with the mucosa-to-mucosa anastomosis and reoperative dissection | Pediatric series report high short-term success and short hospitalization[7][8]; a review of eight small studies that included robotic procedures (one pooled laparoscopic and robotic outcomes) reported study-level success of 66.7%–100% and reoperation of 0%–50%.[17] |
The operation still depends on correct calix selection, lower pole exposure, ureteral vascular preservation, and adequate residual renal function.
Outcomes
Reported success varies across heterogeneous ureterocalicostomy cohorts. A 72-patient adult series reported 50/72 (69.5%) success at mean 60.3 months[3]; a predominantly adult 24-patient laparoscopic series reported 22/24 (91.6%) with symptom improvement or resolution and a nonobstructive or equivocal diuretic renogram at median 60 months[15]. Populations and outcome definitions differ.[3][15]
| Series | Population | Key Outcomes |
|---|---|---|
| Mesrobian and Kelalis 1989 | 21 pediatric patients | 90% excellent results with decreased or eliminated hydronephrosis[1] |
| Matlaga et al. 2005 | 11 contemporary open adult patients | Mean differential function on the operated side rose from 54.6% to 60.1% at mean 10.1-month follow-up (range 5–32 months)[10] |
| Casale et al. 2008 | 9 pediatric robotic patients | No obstruction on diuretic renography at 6 and 12 months; mean hospital stay 21 hours[7] |
| Radford et al. 2011 | 13 pediatric patients, mean follow-up 2.6 years | 12/13 (92%) had reduced dilation and improved drainage on ultrasonography and/or isotope imaging, the authors' definition of good functional outcome; one child required successful revision for symptomatic anastomotic obstruction at five months.[9] |
| Srivastava et al. 2017 | 72 adult open/laparoscopic patients followed for at least 2 years (mean 60.3 months) | 50/72 (69.5%) were classified as successes; 22/72 (30.5%) met a composite failure definition involving another procedure for persistent symptoms and/or repeated scans showing obstruction with declining function on two occasions 3 months apart. Six underwent nephrectomy; UTI was the most common complication (22/72, 30.6%).[3] |
| Mittal et al. 2022 | 24 multi-institutional pediatric robotic patients | 92% improved symptoms and hydronephrosis without further intervention at median 16 months; 8% required nephrectomy[8] |
The adult study reported 50/72 (69.5%) successes at mean 60.3 months[3]; the pediatric robotic study reported 9/9 (100%) unobstructed renograms at 6 and 12 months[7]. Age, anatomy, baseline function, outcome definitions and follow-up differ.[3][7][8]
Predictors of Failure
The best adult failure-predictor data come from Srivastava et al.'s contemporary 72-patient cohort.[3]
| Cohort predictor (first three rows) or operative concern (last two rows) | Interpretation |
|---|---|
| Cortical thickness <5 mm | Independent predictor of failure |
| GFR <20 mL/min/1.73 m² | Independent predictor of failure; associated with poorer outcome in this cohort; assess salvage individually |
| Serum creatinine >1.7 mg/dL | Associated with failure on univariate analysis, but not independent on multivariate analysis |
| Multiple prior interventions | Raises scar burden and lowers reconstructive margin for error |
| Inadequate lower pole parenchymal excision | Technical failure risk from tissue ingrowth or restenosis |
A solitary kidney, symptoms, recurrent infection, patient preference, and alternative morbidity can shift the decision, but low GFR plus very thin cortex is a warning that the operation may become a complex bridge to chronic stenting or nephrectomy.
Complications
Complications reflect both upper-tract reconstruction and lower pole renal parenchymal incision:
- urinary tract infection or pyelonephritis,
- urinary leak or urinoma,
- perinephric abscess,
- bleeding from lower pole parenchymal amputation,
- stent symptoms, migration, encrustation, or retained stent,
- recurrent obstruction at the ureterocaliceal anastomosis,
- need for balloon dilation, chronic stent exchange, redo ureterocalicostomy, nephrostomy, or nephrectomy.[1][3][8][9]
In the adult 72-patient series, UTI was the most common complication at 30.6%; failed cases were managed with nephrectomy, frequent double-J stent changes or balloon dilation, or repeat ureterocalicostomy.[3] The multi-institutional pediatric robotic cohort reported no Clavien-Dindo grade III-V complications within 30 days.[8] In a separate retrospective multicenter cohort of 15 children undergoing laparoscopic or robot-assisted ureterocalicostomy, 3/15 (20%) had Clavien-Dindo grade II urinary leaks, none requiring reintervention.[18]
Follow-up
Follow-up should document symptom response, hydronephrosis trajectory, drainage, and renal function.
Typical surveillance:
- ultrasound after stent removal and again during early follow-up,
- MAG3/DTPA renography when symptoms persist, hydronephrosis worsens, or baseline function was threatened; a 24-patient retrospective laparoscopic cohort also obtained renal scintigraphy six weeks after stent removal and annual DTPA diuretic renography thereafter.[15]
- urine culture and renal function testing when infection, solitary kidney, or borderline function is present,
- longer surveillance for pediatric patients, reoperative anatomy, borderline cortical thickness, or persistent hydronephrosis.
Persistent hydronephrosis can lag behind clinical improvement, so failure should be defined by the whole pattern: symptoms, infections, imaging progression, drainage curve, differential function, and need for secondary intervention.
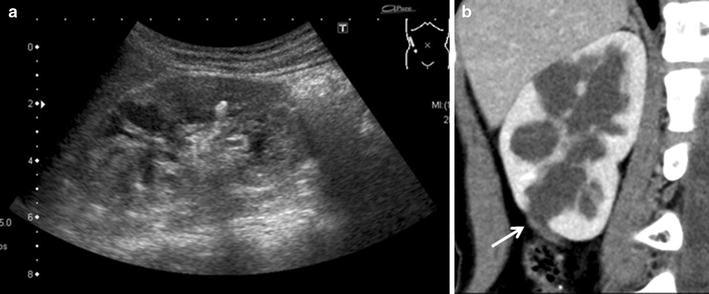
Imaging after laparoscopic ureterocalicostomy. (a) Ultrasound 6 months after surgery shows improvement in the hydronephrosis. (b) CT at 15 months shows a patent anastomosis (white arrow). From Nishimura Y, et al. BMC Res Notes. 2017;10(1):247, Fig. 3 (CC BY).[6]
Operative Pearls
- Choose it because the pelvis is unusable or inaccessible.
- The lower pole calix must be opened widely enough to see mucosa.
- Preserve ureteral adventitia. A well-exposed calix still fails if the ureter is devascularized.
- Use the lower pole because it gives dependent drainage and often reduces tension.
- In good-functioning kidneys, expect more bleeding during lower pole amputation than in paper-thin end-stage kidneys.
- Stent the repair.
- Counsel adults considered for ureterocalicostomy that success is not assured (reported 69.5%; 50 of 72 at mean 60.3 months across mixed indications in the largest adult cohort).[3] Cortical thickness and baseline renal function predicted failure in that cohort.
Videos
References
1. Mesrobian HG, Kelalis PP. Ureterocalicostomy: indications and results in 21 patients. J Urol. 1989;142(5):1285-1287. doi:10.1016/s0022-5347(17)39058-4.
2. Gill IS, Cherullo EE, Steinberg A, et al. Laparoscopic ureterocalicostomy: initial experience. J Urol. 2004;171(3):1227-1230. doi:10.1097/01.ju.0000114233.66534.b0.
3. Srivastava D, Sureka SK, Yadav P, et al. Ureterocalicostomy for reconstruction of complicated ureteropelvic junction obstruction in adults: long-term outcome and factors predicting failure in a contemporary cohort. J Urol. 2017;198(6):1374-1378. doi:10.1016/j.juro.2017.06.079.
4. Korets R, Hyams ES, Shah OD, Stifelman MD. Robotic-assisted laparoscopic ureterocalicostomy. Urology. 2007;70(2):366-369. doi:10.1016/j.urology.2007.04.024.
5. Osman T, Eltahawy I, Fawaz K, et al. Ureterocalicostomy for treatment of complex cases of ureteropelvic junction obstruction in adults. Urology. 2011;78(1):202-207. doi:10.1016/j.urology.2011.01.044.
6. Nishimura Y, Moriya K, Nakamura M, et al. Laparoscopic ureterocalicostomy for ureteropelvic junction obstruction in a 10-year-old female patient: a case report. BMC Res Notes. 2017;10(1):247. doi:10.1186/s13104-017-2569-x.
7. Casale P, Mucksavage P, Resnick M, Kim SS. Robotic ureterocalicostomy in the pediatric population. J Urol. 2008;180(6):2643-2648. doi:10.1016/j.juro.2008.08.052.
8. Mittal S, Aghababian A, Eftekharzadeh S, et al. Robot-assisted laparoscopic ureterocalicostomy in the setting of ureteropelvic junction obstruction: a multi-institutional cohort. J Urol. 2022;208(1):180-185. doi:10.1097/JU.0000000000002484.
9. Radford AR, Thomas DF, Subramaniam R. Ureterocalicostomy in children: 12 years experience in a single centre. BJU Int. 2011;108(3):434-438. doi:10.1111/j.1464-410X.2010.09925.x.
10. Matlaga BR, Shah OD, Singh D, Streem SB, Assimos DG. Ureterocalicostomy: a contemporary experience. Urology. 2005;65(1):42-44. doi:10.1016/j.urology.2004.08.024.
11. Adamic BL, Lombardo A, Andolfi C, Hatcher D, Gundeti MS. Pediatric robotic-assisted laparoscopic ureterocalycostomy: salient tips and technical modifications for optimal repair. BJUI Compass. 2021;2(1):53-57. doi:10.1002/bco2.53.
12. Estrada CR, Retik AB. Open surgical management of ureteropelvic junction obstruction. In: Montague DK, Gill IS, Angermeier KW, Ross JH, eds. Textbook of Reconstructive Urologic Surgery. Informa Healthcare; 2008:143–150.
13. Nakada SY, Knoedler MA, Best SL. Management of upper urinary tract obstruction. In: Partin AW, Dmochowski RR, Kavoussi LR, Peters CA, eds. Campbell-Walsh-Wein Urology. 13th ed. Elsevier; 2025:1903–1941.
14. Bayne CE, Peters CA. Congenital infundibulopelvic stenosis: indications for intervention, surgical technique, and review of literature. J Pediatr Urol. 2016;12(6):389.e1-389.e5. doi:10.1016/j.jpurol.2016.04.042
15. Morgan HL, de Arruda Pessoa F, Riccetto E, et al. "Primary versus rescue laparoscopic ureterocalicostomy for complex upper urinary tract obstruction: a single-center series with long-term follow-up." Int Urol Nephrol. 2026. doi:10.1007/s11255-026-05276-0
16. Demchenko V, Shchukin D, Antonyan I, Lisova G, Harahatyi A, Shus A. "Ureterocalicostomy for reconstruction of the upper urinary tract." Georgian Med News. 2020;(303):33–39. PMID:32841177.
17. Spinos T, Kallidonis P, Tatanis V, et al. "Robotic-assisted laparoscopic ureterocalicostomy (RALUC): a systematic review of its applications." World J Urol. 2026;44:47. doi:10.1007/s00345-025-06046-w
18. Esposito C, Blanc T, Patkowski D, et al. "Laparoscopic and robot-assisted ureterocalicostomy for treatment of primary and recurrent pelvi-ureteric junction obstruction in children: a multicenter comparative study with laparoscopic and robot-assisted Anderson-Hynes pyeloplasty." Int Urol Nephrol. 2022;54(10):2503-2509. doi:10.1007/s11255-022-03305-2