Principles of Genital Reconstruction
Genital reconstruction repairs penile, scrotal, vulvar and perineal defects after disease, injury or tissue loss. The plan follows the tissue actually missing and the patient's priorities for urinary function, sexual activity, sensation, appearance and protection of exposed structures.[1][2]
The dedicated Gender-Affirming Surgery section covers those pathways. Peyronie's surgery addresses tunical deformity.
Define the defect before choosing a technique
| Domain | Questions that change the operation |
|---|---|
| Skin and soft tissue | What viable skin remains? Is the problem limited to surface coverage, or is there fibrosis, lymphedema or substantial dead space? |
| Urethra and voiding | Is there a meatal/urethral lesion, fistula or obstruction requiring separate evaluation or reconstruction? |
| Glans, corpora and neurovascular structures | Which structures are intact, exposed or injured? What can be preserved safely? |
| Scrotum and testes | Are the testes and their coverings viable? Can residual scrotal tissue provide tension-free coverage? |
| Vulva, vagina and perineum | Will closure narrow or displace the introitus, urethral opening or anus? Is deeper vaginal or pelvic reconstruction required? |
| Recipient and donor tissues | Consider previous surgery, radiation, scars, vascular supply, tissue quality and donor morbidity |
Deep pelvic defects need a plan for filling dead space and protecting organs as well as replacing skin. Extensive resections are planned jointly with the urologic, gynecologic, colorectal and plastic-surgery teams.[1][3][2]
Choose the reconstruction that meets the need
The reconstructive ladder organizes the available options. A suitable flap can be chosen without first failing every simpler operation.
| Option | Typical role | Main limitation |
|---|---|---|
| Primary closure or local advancement | Adequate viable tissue that closes without tension or distortion | Excessive tension can compromise healing or narrow adjacent openings |
| STSG or FTSG | Surface coverage on a vascularized bed | Requires revascularization; cannot fill substantial dead space; contracture and sensory changes remain possible |
| Local or regional flap | Provides vascularized coverage, sometimes with useful bulk | Pedicle reach, prior treatment and donor morbidity constrain choice |
| Free tissue transfer | Selected extensive, composite or otherwise unsuitable defects | Requires recipient vessels, microsurgical expertise and a postoperative monitoring plan |
A large superficial genital wound may accept a graft, while a smaller but deep defect may need vascularized tissue. Exposed testes alone do not automatically require a flap if a suitable vascularized covering remains.[4][1][3]
Examples by tier: local or regional fasciocutaneous flaps depend on the internal pudendal territory, the upper medial thigh plexus or the descending branch of the inferior gluteal artery, and pudendal-thigh and lotus petal flaps are examples. When the defect is pelviperineal, myocutaneous flaps supply resurfacing and the bulk to fill the pelvic cavity. Rectus and gluteus flaps have largely superseded gracilis in most situations because of the gracilis flap's intrinsic limitations. Perforator-based muscle-sparing flaps are increasingly reported, and free tissue transfer is limited to defects that standard techniques cannot cover.[8] In a two-center series of 46 patients, the authors used local flaps for smaller perineal defects and described rectus abdominis as their standard for larger defects needing dead-space closure.[9] Across 31 post-abdominoperineal-resection studies (764 patients), VRAM flap necrosis was 20/437 (4.6%) and reoperation was 24/265 (9.1%), while perineal hernia was 7/47 (14.9%) in gluteal fasciocutaneous cases; most studies evaluated only one flap type, limiting direct comparisons.[24] In BIOPEX-2, a randomized trial after abdominoperineal resection for rectal cancer, a gluteal turnover flap did not show superiority over primary closure for uncomplicated 30-day perineal wound healing (42/76 [55%] vs 49/82 [60%]); presacral abscess, a secondary outcome, was less frequent with the flap (7/78 [9%] vs 19/86 [22%]).[25] Total pelvic exenteration was excluded.[25]
Establish readiness and preserve viable tissue
Control infection and remove nonviable tissue before definitive reconstruction. AUA advises limited debridement of nonviable genital tissue while preserving potentially viable skin (Statement 31; Standard, Grade B).[22] After destructive infection, reconstruction proceeds when the wound is stable and further debridement is not needed. No fixed waiting interval suits every patient. Tailor excision to the disease while preserving unaffected skin, dartos and important neurovascular structures when appropriate.[4]
For grafts, establish hemostasis and close contact with a viable recipient bed, then protect against shear, fluid collection and constriction. Dermal matrices and NPWT are selective adjuncts. The cited FDA summary lists two contraindications for Integra Dermal Regeneration Template: clinically diagnosed infected wounds and known sensitivity to bovine collagen or chondroitin. Follow the instructions for the exact product.[4][5]
Radiated, scarred or repeatedly operated tissues may require recruitment of healthier vascularized tissue. Donor and pedicle choices account for abdominal incisions, previous flap harvest and stoma requirements. Immediate versus staged reconstruction depends on source control, margin assessment, the exposed structures and the consequences of leaving the wound open.[3]
Match the plan to the anatomy
Penile skin: preserve adequate mobility for erection and avoid a constricting closure. Assess shaft skin, glans, urethra and corpora separately. Graft thickness and donor selection involve tradeoffs.[26] In one retrospective series of adult acquired buried penis, postoperative complications and recurrence did not differ significantly between nine FTSG and 13 STSG recipients.[26] See Penile Skin Grafting.[4]
Scrotum: preserve viable residual tissue when possible. Grafts and regional flaps are both established options. A 2026 review of 107 reports encompassing 619 patients and 625 flaps after Fournier gangrene reported flap loss in 1.6%. Heterogeneous populations, limited comparative data and inconsistent functional reporting prevent a universal graft-versus-flap rule.[6] See Scrotal Reconstruction.
Vulva and perineum: preserve or restore the position and caliber of urinary, vaginal and anal openings; minimize painful scar tension and consider the patient's sexual goals. Choose among local, thigh-based, abdominal or other flaps according to the three-dimensional defect and donor tissues. No single standardized flap sequence fits every vulvovaginal resection.[2][1] See Vulvar Reconstruction.
Reconstruction after penile tumor excision
The oncologic plan comes first: establish histology, achieve negative margins and choose organ preservation when suitable. The EAU guideline strongly recommends organ-sparing surgery and reconstructive techniques for lesions confined to the glans and prepuce (PeIN, Ta, T1–T2) in patients willing to comply with strict follow-up.[7] It also strongly recommends counseling that organ-sparing procedures are associated with a higher local-recurrence risk than amputative surgery.[7] NCCN Version 2.2026 allows resurfacing only in highly selected patients (category 2A), lists complete glansectomy for selected PeIN or Ta tumors (category 2B), and restricts pT1a glansectomy to cases requiring it for complete clearance with negative margins (category 2A). NCCN lists partial or total penectomy for T2 or greater disease, unlike the EAU organ-sparing options for selected glans-confined cT1–T2 disease.[23][7] The reconstructive options run from tissue-sparing to radical.[18]
| Option | Reconstruction | EAU-reported recurrence-free rate |
|---|---|---|
| Mohs micrographic surgery | Margin-controlled excision of superficial disease | Mean 5-year rate 88.2% in 51 men, mostly T1. Data are very limited and the panel does not routinely recommend it[7] |
| Glans resurfacing | Excision of glans epithelium with split-thickness skin graft | Reported RFR 75–96.6% across five studies of 68 invasive cases[7] |
| Partial or total glansectomy | Neoglans commonly covered with split-thickness skin graft over the corpora; EAU reports graft loss of 1.5–23.5% and meatal stenosis of 2.8–14.3%. Poor vascular function, diabetes, immunosuppression or prior groin radiation make grafting less suitable because of higher failure risk; discuss grafting versus primary closure.[7] | 5-year rate 78.0–95.8% (6 studies)[7] |
| Partial penectomy | Preserves a stump for standing micturition | — |
| Total penectomy | Perineal urethrostomy, or phalloplasty with a later erectile device in selected patients | — |
NCCN recommends partial penectomy for high-grade tumors when a functional stump and negative margins can be retained, and total penectomy when this is not feasible (category 2A); it gives no numeric stump-length cutoff.[23] For partial penectomy, preserve enough stump length for standing voiding with the urinary stream passing over the scrotum.[19] Because postoperative retraction can bury a short stump, estimate the anticipated stump length in both the standing and supine positions, particularly in obese patients or those with a prominent prepubic fat pad; a buried stump raises the risk of infection, annular skin strictures, hygiene difficulty and patient dissatisfaction. When oncologically feasible, the proximal crura can be preserved during total penectomy, since they may later support the rear tips of a penile prosthesis if phalloplasty is planned; this is not possible when the crura are tumor-involved.[19]
For selected patients after subtotal penectomy who may pursue later phalloplasty, one described staged approach preserves the corporal ends and adequate urethral length and uses an infrapubic rather than a perineal urethrostomy, to keep the perineum available for the later procedure.[20] For men with a retained partial-penectomy stump and adequate shaft skin who are considered for phalloplasty, one described lengthening sequence removes shaft skin over the corporal heads, covers them with split-thickness graft, develops the infrapubic space, divides the suspensory ligaments, and uses a dorsal V-Y plasty with scrotal skin flaps for coverage; the author estimated about 2–3 cm of added length.[21]
Reconstruction is planned within the oncologic team so that surveillance and further treatment options are preserved.
Scrotal reconstruction after Fournier gangrene
Reconstruction follows debridement and source control. The choice scales with the defect.[6][12][17]
| Defect | Reconstruction |
|---|---|
| Small | Primary tension-free closure or local pedicled flaps from residual scrotal skin. Split-thickness grafts and distant flaps are reserved for extensive loss[17] |
| Scrotal skin loss with exposed testes | After debridement and stabilization, tension-free closure or a local flap may suit defects with enough viable tissue; split-thickness skin grafting can cover more extensive superficial loss on a vascularized bed. Orchidopexy before grafting is a described 10-patient technique with acceptable cosmetic results and no chronic pain, discomfort or further intervention at a median follow-up of 8 months.[12][17] |
| Large | Regional flaps. Medial thigh, pudendal thigh, ALT and gracilis flaps were most common in a 2026 review of 619 patients (625 flaps); flap loss was reported in 1.6% of cases overall[6] |
Testicular thigh pouches are another described option.[12] The pedicled SCIP flap has been described in small reports (three patients with all flaps surviving, and one further case) as a thin, pliable flap with consistent anatomy for perineoscrotal defects.[13][14]
Vulvovaginal and perineal reconstruction after cancer resection
Treatment of vulvar and vaginal neoplasia aims at local control and often does not restore form and function. Höckel and Dornhöfer argue that reconstruction integrated into primary treatment improves aesthetic and functional results and quality of life.[2] They note that functional restoration in irradiated tissue is limited.[2]
Options are matched to defect size and site.[10]
| Defect | Options |
|---|---|
| Small | Local advancement (for example V-Y or rhomboid flaps) |
| Moderate | Fasciocutaneous flaps from the internal pudendal or medial thigh territories, such as pudendal-thigh (Singapore) and lotus petal flaps, or gracilis flaps[8] |
| Large or pelviperineal, including post-exenteration | Myocutaneous flaps such as the VRAM, which combine pelvic dead-space obliteration with perineal resurfacing[8][9] |
| Pelviperineal defects involving vaginal reconstruction | Myocutaneous flaps (rectus, gluteus or gracilis) are of proven advantage for resurfacing and filling the pelvic cavity after extensive resection[8] |
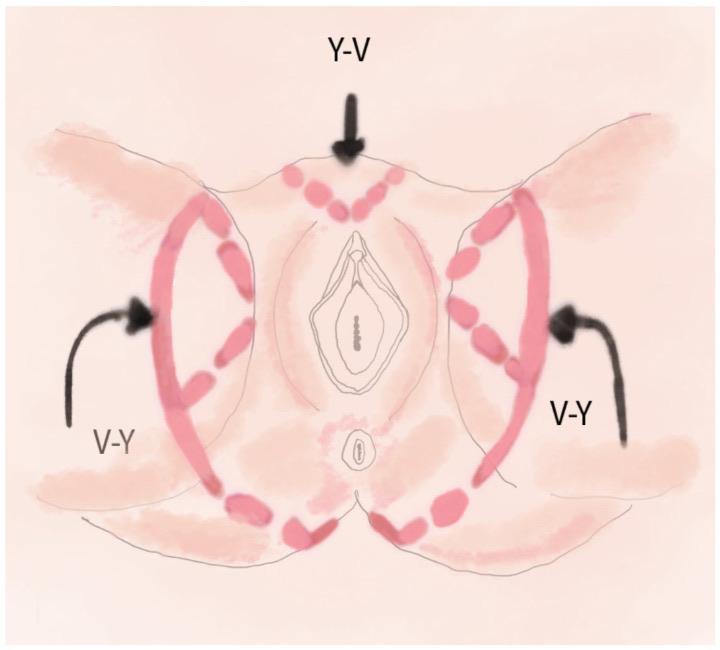
Local advancement for a vulvar and perineal defect: two V-Y advancement flaps from the intragluteal fold region, drawn as triangular wings on either side, and a third Y-V flap from the mons pubis above the defect. Arrows indicate the direction of advancement toward the center. From Jędrasiak A, et al. J Clin Med. 2025;14(13):4456, Figure 2 (CC BY).[10]
In a 34-patient series after bowel, gynecologic or sacral tumor resection, dehiscence followed two bilateral-gracilis reconstructions, one internal pudendal artery perforator flap and one lotus petal flap; surgical-site infection occurred once after a gracilis reconstruction and once after an oblique rectus flap.[11] The flaps treated different defects.[11] The authors reported no documented recurrence in 15 of 34 patients, but at least one such patient had only two years of follow-up. They describe most operations as salvage procedures.[11]
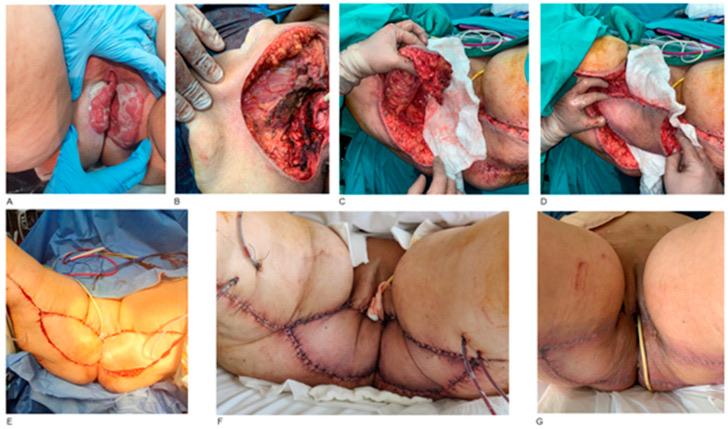
Vulvovaginal reconstruction with bilateral gracilis flaps. (A) Extended vulvar and vaginal squamous cell carcinoma. (B) Defect after wide resection, including bilateral excision of the labia majora, labia minora and vagina. (C, D) Harvest of bilateral V-Y pedicled gracilis myocutaneous flaps. (E) Completed vulvovaginal and perineal reconstruction. (F) Both flaps viable seven days after surgery. (G) Two weeks after surgery, healing without infection or dehiscence; the patient also had an end colostomy. From Bini A, Stavrianos S. J Clin Med. 2025;14(9):3172, Figure 2 (CC BY).[11]
Gender-affirming genital surgery
Phalloplasty, metoidioplasty and vaginoplasty are covered in Masculinizing Surgery and Feminizing Surgery, including eligibility, staging and complications. The neourethra is the main source of morbidity after phalloplasty. A meta-analysis tabulated 21 studies (1,566 patients) and reported separate pooled rates of 23.9% for urethral fistula and 25.0% for stricture or stenosis.[15] Standing voiding was 91.5% across 13 studies (745 patients); patient-reported satisfaction was 90.5% among studies reporting that outcome.[15] Prelaminated-flap urethras had a higher stricture rate than tube-in-tube urethras.[15] In a self-selected survey of 129 transmasculine respondents after genital reconstruction, 79 had phalloplasty only, 32 metoidioplasty only and 18 both.[16] Across this mixed group, 51 (40%) reported urethrocutaneous fistula, 41 (32%) stricture and 25 (19%) worsened mental health.[16]
Counseling and follow-up
Baseline function and the outcomes the patient values are documented. Counseling covers donor wounds, staged surgery, loss of sensation, painful erection or intercourse, contracture, wound problems, recurrent disease and possible revision.[4][2]
Follow-up assesses wound and donor-site healing, urinary function, sensation, sexual comfort, contracture and recurrence, with disease-specific surveillance when indicated. Patient-reported outcomes are recorded, and results distinguish people, operations, graft area and time to recurrence.
See Also
- Penile Reconstruction
- Scrotal Reconstruction
- Vulvar Reconstruction
- Plastic Surgery Principles
- Flaps in GU Reconstruction
- Grafts in GU Reconstruction
- Radiation Tissue Effects
- Wound Healing Adjuncts
References
1. Shahzad F, Ray E. "Pelvic and perineal reconstruction." Plast Reconstr Surg. 2024;154(4):803e–816e. doi:10.1097/PRS.0000000000011137
2. Höckel M, Dornhöfer N. "Vulvovaginal reconstruction for neoplastic disease." Lancet Oncol. 2008;9(6):559–568. doi:10.1016/S1470-2045(08)70147-5
3. Brodbeck R, Horch RE, Arkudas A, Beier JP. "Plastic and reconstructive surgery in the treatment of oncological perineal and genital defects." Front Oncol. 2015;5:212. doi:10.3389/fonc.2015.00212
4. Alwaal A, McAninch JW, Harris CR, Breyer BN. Utilities of Split-Thickness Skin Grafting for Male Genital Reconstruction. Urology. 2015;86(4):835–839. doi:10.1016/j.urology.2015.07.005.
5. US Food and Drug Administration. Integra Dermal Regeneration Template / Omnigraft: Summary of Safety and Effectiveness Data, P900033/S042. 2016. Contraindications. FDA SSED.
6. Alammar A, Laing K, Somasundaram J, Wallace DL, Rogers AD. "Flap reconstruction following Fournier's gangrene: a systematic review of techniques and outcomes." Burns. 2026;52(3):107888. doi:10.1016/j.burns.2026.107888
7. European Association of Urology. EAU Guidelines on Penile Cancer. 2026. Disease management, section6.1. Guideline.
8. Wong DS. Reconstruction of the perineum. Ann Plast Surg. 2014;73(Suppl 1):S74–S81. doi:10.1097/SAP.0000000000000237
9. John HE, Jessop ZM, Di Candia M, et al. An algorithmic approach to perineal reconstruction after cancer resection: experience from two international centers. Ann Plast Surg. 2013;71(1):96–102. doi:10.1097/SAP.0b013e3182414485
10. Jędrasiak A, Juniewicz H, Raczek W, et al. Reconstruction of the vulva and perineum: comparison of surgical methods. J Clin Med. 2025;14(13):4456. doi:10.3390/jcm14134456
11. Bini A, Stavrianos S. Pelvic and perineal reconstruction after bowel, gynecological or sacral tumor resection: a case series. J Clin Med. 2025;14(9):3172. doi:10.3390/jcm14093172
12. Hayon S, Demzik A, Ehlers M, McGowan M, Mohan C, Figler BD. Orchidopexy and split-thickness skin graft for scrotal defects after necrotizing fasciitis. Urology. 2021;152:196. doi:10.1016/j.urology.2021.02.007
13. B S, Khanna A, Taylor D. Pedicled superficial circumflex iliac artery perforator (SCIP) flap for perineo-scrotal reconstruction following Fournier's gangrene. ANZ J Surg. 2023;93(1–2):276–280. doi:10.1111/ans.18066
14. Han HH, Lee JH, Kim SM, Jun YJ, Kim YJ. Scrotal reconstruction using a superficial circumflex iliac artery perforator flap following Fournier's gangrene. Int Wound J. 2016;13(5):996–999. doi:10.1111/iwj.12353
15. Hu CH, Chang CJ, Wang SW, Chang KV. A systematic review and meta-analysis of urethral complications and outcomes in transgender men. J Plast Reconstr Aesthet Surg. 2022;75(1):10–24. doi:10.1016/j.bjps.2021.08.006
16. Robinson IS, Blasdel G, Cohen O, Zhao LC, Bluebond-Langner R. Surgical outcomes following gender-affirming penile reconstruction: patient-reported outcomes from a multi-center, international survey of 129 transmasculine patients. J Sex Med. 2021;18(4):800–811. doi:10.1016/j.jsxm.2021.01.183
17. Schifano N, Castiglione F, Cakir OO, Montorsi F, Garaffa G. Reconstructive surgery of the scrotum: a systematic review. Int J Impot Res. 2022;34(4):359–368. doi:10.1038/s41443-021-00468-x
18. Bickell M, Beilan J, Wallen J, Wiegand L, Carrion R. Advances in surgical reconstructive techniques in the management of penile, urethral, and scrotal cancer. Urol Clin North Am. 2016;43(4):545–559. doi:10.1016/j.ucl.2016.06.015
19. Horenblas S, Malone PR, Muneer A. Surgical Treatment of Penile Cancer. In: Muneer A, Arya M, Jordan GH, eds. Atlas of Male Genitourethral Surgery: The Illustrated Guide. Wiley-Blackwell; 2014:134-150. doi:10.1002/9781118651292.ch11
20. Brandes SB, Eswara JR. Penile and Inguinal Reconstruction and Tissue Preservation for Penile Cancer. In: Brandes SB, Morey AF, eds. Advanced Male Urethral and Genital Reconstructive Surgery. 2nd ed. Humana Press; 2014:655-673. doi:10.1007/978-1-4614-7708-2_46
21. Watkin NA. Reconstructive surgery in penile cancer. In: Montague DK, Gill IS, Angermeier KW, Ross JH, eds. Textbook of Reconstructive Urologic Surgery. Informa Healthcare; 2008:668-674.
22. Morey AF, Broghammer JA, Hollowell CMP, et al. Urotrauma Guideline 2020: AUA Guideline. J Urol. 2021;205(1):30–35. doi:10.1097/JU.0000000000001408. Full guideline, published 2014; amended April 2017 and August 2020.
23. National Comprehensive Cancer Network. NCCN Clinical Practice Guidelines in Oncology: Penile Cancer. Version 2.2026. June 5, 2026.
24. Calpin GG, Davey MG, Maguire B, et al. "Optimal approaches to flap reconstruction following abdominoperineal resection: A systematic review." Surgeon. 2025;23(3):155–161. doi:10.1016/j.surge.2025.01.010
25. Kreisel SI, et al. "Perineal Wound Closure Using Gluteal Turnover Flap After Abdominoperineal Resection for Rectal Cancer: The BIOPEX-2 Randomized Clinical Trial." JAMA Surg. 2025;160(4):378–385. doi:10.1001/jamasurg.2024.6818
26. Gül M, Plamadeala N, Falcone M, et al. "No difference between split-thickness and full-thickness skin grafts for surgical repair in adult acquired buried penis regarding surgical and functional outcomes: a comparative retrospective analysis." Int J Impot Res. 2026;38(3):259–265. doi:10.1038/s41443-024-00832-7