Paraffinoma Excision and Penile Resurfacing
Paraffinoma, also called sclerosing lipogranuloma or oleogranuloma, is a chronic foreign-body granulomatous response after subcutaneous penile injection of liquid paraffin, mineral oil, or Vaseline (petroleum jelly) for augmentation. Liquid silicone injection can produce a similar reaction called siliconoma. Symptomatic infiltrative disease, ulceration, necrosis, infection, deformity, or functional impairment commonly leads to excision or debridement and reconstruction; management is individualized to symptoms, anatomic extent, skin viability, injected material, and patient goals. No formal guideline or comparative trial establishes one universal operation.[1][2][3][8]
For the causal substances, pathophysiology, imaging, and complication phenotype, see Non-Autologous Penile Injectables. For the male cosmetic decision framework, see Male Cosmetic Genital Surgery. For the broader penile-skin-reconstruction umbrella (Fournier's, lichen sclerosus, oncologic resection, avulsion), see Penile Skin / Shaft Reconstruction.
Indications
In Pang's review of heterogeneous male genital injections, 78.8% of reported patients underwent surgery; in its 35-patient single-center cohort, 32 (91.4%) did so.[2] When resection is chosen, remove clinically involved foreign-body tissue while preserving critical structures and viable coverage where feasible; reconstruction follows the resulting defect.[1][4][12] Reported operative triggers include:[2][5][6]
- Firm, irregular or indurated mass with deformity; cosmetic dissatisfaction was reported by 20/35 (57.1%) in Pang's single-center cohort.[2]
- Pain or swelling (45.7% in Pang's cohort)[2]
- Erectile dysfunction
- Voiding difficulty / phimosis or failed urethral catheterization
- Skin necrosis or ulceration. In Pang's mixed-injectate cohort, three patients with necrosis underwent acute debridement followed by deferred further excision and scrotal-flap reconstruction.[2] Necrosis occurred in 13/18 patients in one advanced oleogranuloma referral series.[3]
- Scrotal or suprapubic involvement that changes resection margins or flap donor skin availability.[12][11]
Preoperative Considerations
- Extent of infiltration. Diagnosis is primarily clinical. In selected extensive, uncertain, or deep disease, penile or scrotal MRI can help map subcutaneous and scrotal involvement, assess the relationship to Buck's fascia and neurovascular structures, and support planning or differential diagnosis.[16] MRI descriptions of breast paraffinomas (hypointense on T2-weighted images, with no contrast enhancement) come from non-penile tissue.[7]
- Malignancy assessment. When an ulcer or mass raises concern for carcinoma, obtain tissue diagnosis before definitive resurfacing; the EAU-ASCO 2026 penile cancer guideline gives pretreatment biopsy a Strong recommendation when malignancy is not clinically obvious.[18] Histopathology of excised tissue can confirm foreign-body granuloma and identify unexpected malignancy; Pang's review found one SCC specimen, without establishing an incidence.[2]
- Native shaft skin and scrotal donor tissue. Preservable native shaft skin guides closure choice.[4] Before selecting a scrotal flap, assess remaining scrotal skin and its blood supply: Murányi excluded extensive anterior or whole-scrotal infiltration from flap reconstruction and used another coverage method when scrotal perfusion might be compromised.[12]
- Multidisciplinary input. Urology and reconstructive surgery may both be needed when disease is extensive or coverage is complex. In Marín-Martínez's 8-patient two-center series, a combined urology and plastic surgery approach was used and postoperative erectile function (IIEF-5) was preserved in all. No study compares team configurations.[4]
- Goals and psychological support. Explore expectations, the motivation for injection, body-image distress, sexual concerns, and realistic postoperative appearance; involve appropriate support when concerns are clinically significant.[2][5]
- Disclosure and counseling. Patients may be reluctant to disclose the injection history, as in the case reports of Cohen and Akkus. A non-judgmental approach helps establish the timeline and the injected substance.[1][6]
Reconstructive Options
Napolitano's systematic review of 152 reported cases identified six techniques: bilateral scrotal flap, simple excision with primary closure, two-stage scrotal flap, medial prepuce-suprapubic advancement flap, STSG and FTSG.[8] Selection is guided by the amount and location of involved skin, scrotal-tissue availability, prior surgery, contamination or necrosis, patient preference, and reconstructive expertise.[8][4]
| Technique | Indication | Notes |
|---|---|---|
| Local excision + primary closure | Localized disease with sufficient viable native shaft skin | Preserves native skin when the defect closes without undue tension; patient selection drives the apparent results.[3][9] |
| Bilateral scrotal flap — single stage | Extensive/circumferential shaft-skin loss with suitable scrotal tissue | Widely described in specialist series. In Jeong's original report, all 34 flaps in 17 patients survived, with immediate tactile sensibility; the authors note that a hirsute scrotum may be a contraindication.[10] In Murányi's 49-patient single-surgeon cohort, 30 completed the long-term questionnaire and 27/30 met the authors' patient-reported success definition.[10][12] |
| Bilateral scrotal flap — two stage | Extensive disease when a staged course is acceptable or preferred | Stage 1 buries the denuded shaft in scrotal tissue; stage 2 releases and fashions coverage. In Lumbiganon's retrospective comparison, 10/12 two-stage patients versus 10/23 single-stage patients had no Clavien-Dindo complication, but selection was nonrandomized and total hospital stay was longer.[8][13] |
| Split-thickness skin graft (STSG) | Scrotal skin unavailable/insufficient or graft coverage otherwise selected after confirming a viable recipient bed; Jeong reported that residual corporal-surface granuloma precluded grafting in his series.[10] | Kang's 2026 retrospective series used Matriderm, STSG and NPWT in 11 patients with Vaseline, hyaluronic acid or unknown fillers; no patient was identified as having paraffin injection. Near-complete graft take at the first dressing change on postoperative day 5 occurred in 10/11.[14] |
| Full-thickness skin graft (FTSG) | Selected defects and donor sites | Reported donor sites and techniques vary; comparative superiority over STSG or flaps is unestablished.[5][8] |
| Bipedicled scrotal-flap variants | Extensive disease with suitable scrotal tissue | Shin compared T-style and inverted-V ventral anastomoses in 34 patients. All 14 inverted-V flaps survived, but 3/14 had delayed healing and 1/14 had wound infection. Murányi later described a distinct tunnel pull-through design with a ventral inverted-V incision closed longitudinally. These are nonrandomized technique series.[15][12] |
| Medial prepuce-suprapubic advancement flap | Named in the systematic review | Described in individual reports; no comparative data[8] |
Pang single-center distribution
In Pang's 35-patient single-center cohort, 32 patients underwent surgery. Primary procedures included:[2]
- Local excision and primary closure: 19/32 (59.4%)[2]
- Circumcision: 5/32 (15.6%)[2]
- Excision with split-skin graft or scrotal flap reconstruction: 5/32 (15.6%)[2]
- Eighteen of 35 patients (51%) underwent more than one procedure.[2] The count includes planned staged and unplanned procedures.
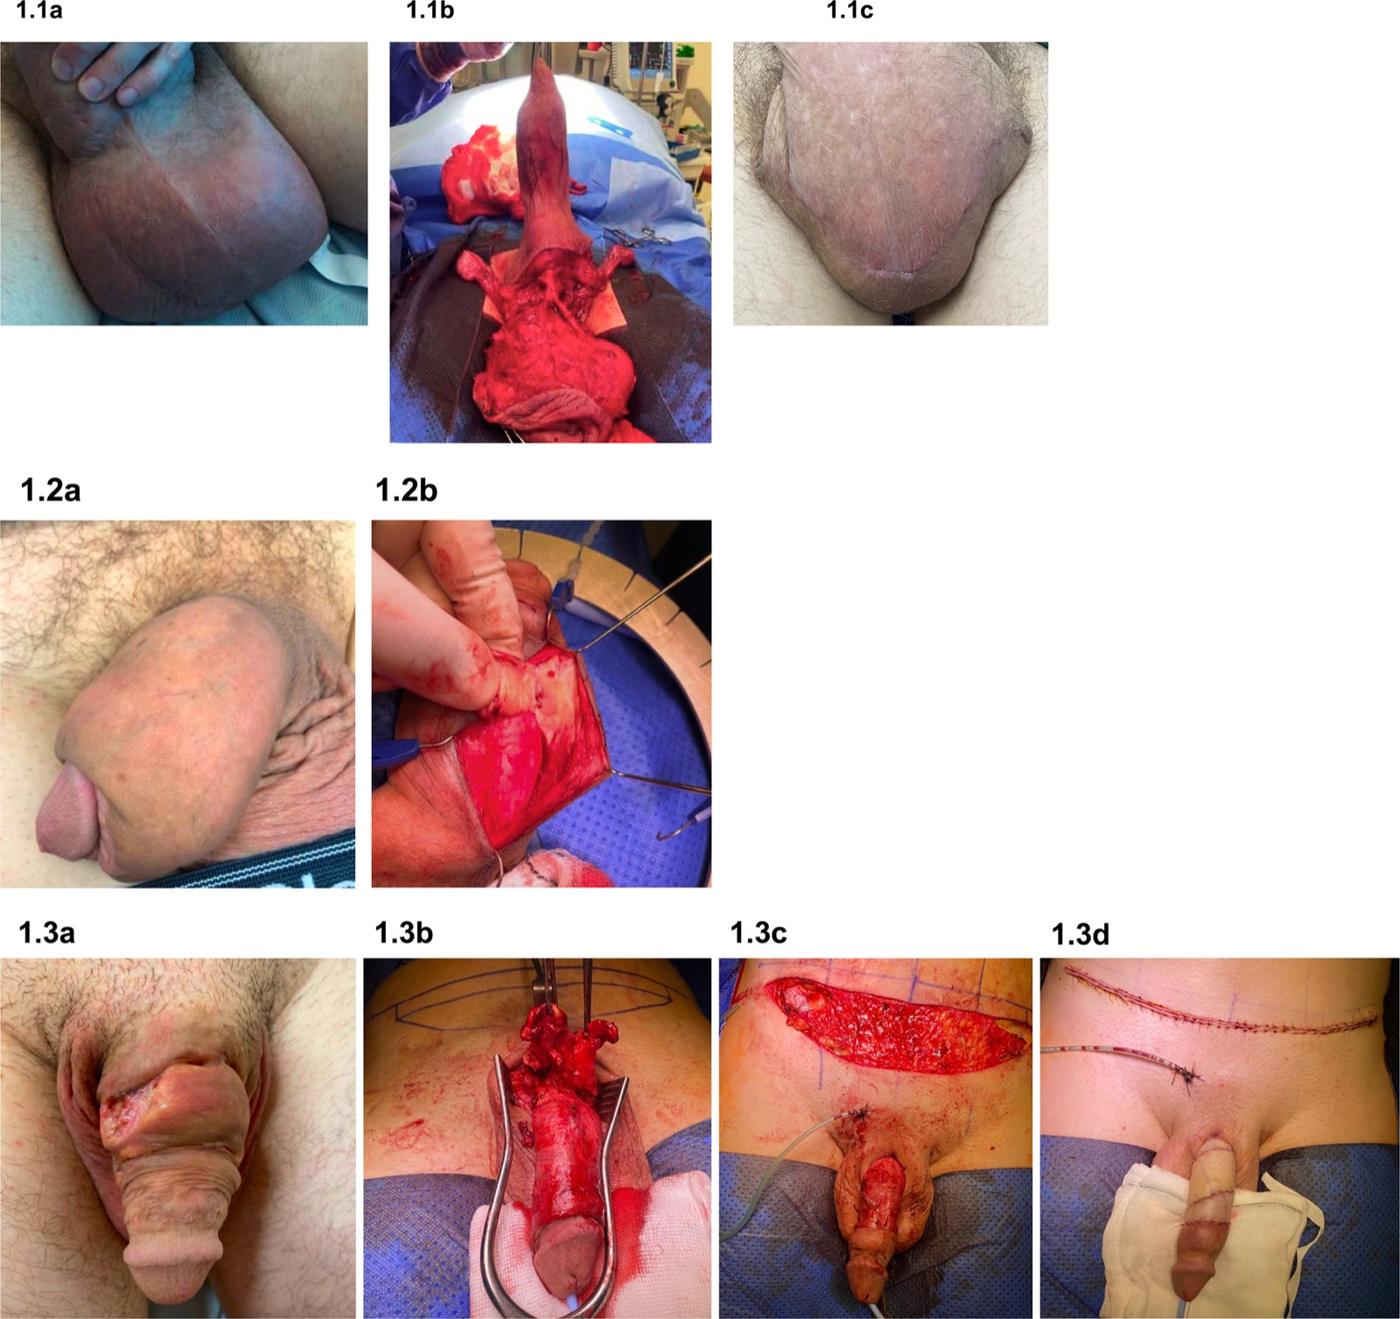
Selected cases from the Pang single-center series. 1.1a, penoscrotal edema after silicone injection; 1.1b, excision of scrotal silicone; 1.1c, appearance 6 weeks after surgery. 1.2a, penile edema after paraffin injection; 1.2b, dissection of the foreign material. 1.3a, penile ulceration and deformity after paraffin injection; 1.3b, excision of the abnormal penile tissue; 1.3c, preparation of a full-thickness skin graft; 1.3d, completed excision and skin-graft reconstruction. From Pang KH, et al. Int J Impot Res. 2024;36(5):498-508, Fig. 1 (CC BY).[2]
Surgical Technique — Bilateral Scrotal Flap (Single Stage)
The following is the modified single-stage bipedicle scrotal-flap sequence reported by Murányi and related technique papers for extensive shaft involvement.[12][15]
- Subcoronal incision. Circumferential incision just proximal to the corona, sparing the glans.
- Degloving. Deglove from the subcoronal incision in the plane between Buck's fascia and involved dartos; a dorsal longitudinal skin incision may be needed for firm, thickened skin.[12]
- Proximal margin and excision. After degloving, make Murányi's proximal circumferential incision at the penile base proximal to affected skin, then remove involved tissue in the plane between infiltrated dartos and Buck's fascia.[12] Preserve the dorsal neurovascular bundle, urethra, and corpora cavernosa / spongiosum.[12][15]
- Measure and mark the scrotal flap. After excision, measure the denuded shaft circumference and length and the proximal penile incision circumference. Use these dimensions to mark the horizontal scrotal incision while preserving the bipedicled flap's vascular supply.[12]
- Subcutaneous tunnel. Create a tunnel between the scrotal incision and the proximal penile incision.[12]
- Pull-through. Deliver the denuded penis through the scrotal tunnel.
- Flap inset. Suture the horizontal scrotal incision to the subcoronal skin edge and close the proximal circumferential incision longitudinally along the dorsal midline. Make the ventral inverted-V incision, dissect the testes from the flap down to the tunica vaginalis, and close the V longitudinally.[12][15]
- Layered scrotal closure.
Two-stage variant
- Stage 1. Excision of involved tissue; the denuded penis is buried within a scrotal tunnel. Reported intervals to release vary by technique and patient.
- Stage 2. Release of the penis from the scrotum; scrotal skin is fashioned into definitive coverage. Lumbiganon 2023 reported no Clavien-Dindo complication in 10/12 two-stage versus 10/23 single-stage patients; wound infection, dehiscence and reoperation differences individually were imprecise and not statistically established, while postoperative fever was higher and total stay shorter in the single-stage group. The retrospective comparison is vulnerable to selection and small-sample confounding.[13]
NPWT-assisted STSG (single-stage alternative)
- Kang 2026 protocol: complete excision, application of dermal substitute (Matriderm), STSG, then negative-pressure wound therapy at −125 mmHg.
- 10/11 near-complete graft take at the postoperative day-5 dressing change; one partial graft loss with hematoma required evacuation, and one patient had chronic discharge from remnant filler. Median satisfaction was 37/45; median follow-up was 18 months.[14]
- This provides a reported single-stage option when graft coverage is selected; comparative durability against flap reconstruction is unknown.
Outcomes
| Series | n | Technique | Success | Complications |
|---|---|---|---|---|
| Murányi 2022[12] | 49 treated; 30/49 questionnaire respondents at mean 26.9 months | Modified bipedicle scrotal flap | 27/30 respondents were satisfied or very satisfied; this was the authors' success definition | 13/49 (26.5%) had a recorded complication, with no postdischarge visit for 8/49; erectile dysfunction was reported by 2/30 questionnaire respondents |
| Lumbiganon 2023[13] | 42 total; 23 single-stage and 12 two-stage compared | Single- vs two-stage scrotal flap | No validated global success endpoint | No Clavien-Dindo complication: 10/23 vs 10/12; fever: 13/23 vs 1/12 |
| Suleiman 2024[3] | 18 | Primary closure (9) or two-stage scrotal flap (9) | All 18 underwent surgery; success rate not reported | Necrosis was a presentation finding in 13/18, not a postoperative complication |
| Marín-Martínez 2023[4] | 8 | Single- and two-stage resection with coverage; extensive liquid-paraffin disease needed two stages or a graft | Postoperative erectile function (IIEF-5) preserved in all | — |
| Kang 2026[14] | 11 | NPWT + dermal substitute + STSG | Near-complete graft take at the postoperative day-5 dressing change in 10/11 | One partial graft loss with hematoma requiring evacuation; one remnant-filler discharge |
Many reports preserve erectile or intercourse ability, but outcome instruments and denominators are inconsistent and selection is strong. Murányi's technique dissects between involved dartos and Buck's fascia; its 30 questionnaire respondents all reported intercourse ability, while two reported erectile dysfunction.[4][12]
Complications
| Complication | Rate / note |
|---|---|
| Wound infection | Lumbiganon: 2/23 (8.69%) single-stage vs 0/12 two-stage; the confidence interval was very wide[13] |
| Wound dehiscence | Lumbiganon: 5/23 (21.74%) single-stage vs 1/12 (8.33%) two-stage; no statistically established difference[13] |
| Postoperative fever | Lumbiganon: 13/23 (56.52%) single-stage vs 1/12 (8.33%) two-stage[13] |
| Marginal flap necrosis / partial graft loss | Murányi reported marginal flap necrosis in 8/49 (16.3%), seven subcoronal and one midscrotal; debridement and local care led to secondary healing. Kang reported partial graft loss with hematoma in 1/11 STSG patients.[12][14] |
| Penile lymphedema | Murányi: 1/30 questionnaire respondents[12] |
| Chronic discharge from remnant filler | Reported after residual foreign material and may prompt further assessment or surgery[14] |
| Erectile/sexual symptoms | Reported inconsistently; preoperative disease and reconstruction both complicate attribution[4][12] |
| Glans necrosis after removal | A 2025 systematic review of postoperative glans necrosis identified four cases after paraffinoma removal; it did not provide a procedure-specific incidence.[17] |
| Additional procedures | Pang reported more than one procedure in 18/35 patients, a count that includes planned/staged care[2] |
Non-Surgical Options
Evidence for nonoperative treatment is limited and heterogeneous. Pang's systematic review found 21.2% managed conservatively; necrosis, infection, progressive ulceration, obstruction, suspected malignancy, or major functional impairment require prompt specialist assessment.[2]
- Intralesional triamcinolone and hot-water baths were used in one reported patient who declined surgery.[6]
- These reports do not show reliable reversal of established granulomatous infiltration and should not delay necessary debridement or diagnostic evaluation.
Key Principles
- Resect involved foreign-body tissue while preserving critical anatomy and viable coverage. Residual material can perpetuate symptoms, and complete excision is described as the treatment of choice to prevent recurrence.[1] Murányi's technique dissects between the involved dartos and Buck's fascia.[12]
- Choose coverage to fit the defect and donor tissue. Primary closure, scrotal flaps and skin grafts all have reported roles; no comparative trial establishes one preferred pathway.[2][8]
- Single- versus two-stage tradeoffs are not settled. One small retrospective comparison found fewer aggregate complications but longer total stay with staging; individual wound-event comparisons were imprecise.[13]
- NPWT with dermal substitute and STSG has single-arm 11-patient data.[14]
- Counsel about uncertain functional and cosmetic outcomes. Intercourse ability was retained in selected series, but erectile symptoms, lymphedema, wound problems and additional procedures occurred.[4][12]
- Modified Y-V/inverted-V geometry is intended to reduce high-tension junctions.[12][15]
- Address expectations and body-image concerns alongside physical reconstruction.[2][5]
References
1. Cohen JL, Keoleian CM, Krull EA. Penile paraffinoma: self-injection with mineral oil. J Am Acad Dermatol. 2001;45(6 Suppl):S222-4. doi:10.1067/mjd.2001.103995.
2. Pang KH, Randhawa K, Tang S, et al. Complications and outcomes following injection of foreign material into the male external genitalia for augmentation: a single-centre experience and systematic review. Int J Impot Res. 2024;36(5):498-508. doi:10.1038/s41443-023-00675-8.
3. Suleiman M, Mustafa A, Ainayev Y, et al. The surgical management of penile oleogranuloma: case series. Int J Impot Res. 2024;36(5):509-514. doi:10.1038/s41443-023-00779-1.
4. Marín-Martínez FM, Guzmán Martínez-Valls PL, Dekalo S, Weiss J, Haran O. Aesthetic and functional results after single- and two-stage resection and reconstruction of penile paraffinomas — experience from two tertiary centers and a surgical management algorithm. Urology. 2023;171:227-235. doi:10.1016/j.urology.2022.09.022.
5. Lauria J, Zappalà G, Sidoti FC, et al. Paraffinoma of the penis following subcutaneous paraffin injections: a case report and surgical management. Int J Impot Res. 2026;38(3):266-267. doi:10.1038/s41443-025-01169-5.
6. Akkus E, Iscimen A, Tasli L, Hattat H. Paraffinoma and ulcer of the external genitalia after self-injection of Vaseline. J Sex Med. 2006;3(1):170-2. doi:10.1111/j.1743-6109.2005.00096.x. PMID 16409233.
7. Wang J, Shih TT, Li YW, Chang KJ, Huang HY. Magnetic resonance imaging characteristics of paraffinomas and siliconomas after mammoplasty. J Formos Med Assoc. 2002;101(2):117-23. PMID 12099202
8. Napolitano L, Marino C, Di Giovanni A, et al. Two-stage penile reconstruction after paraffin injection: a case report and a systematic review of the literature. J Clin Med. 2023;12(7):2604. doi:10.3390/jcm12072604.
9. Santucci RA, Zehring RD, McClure D. Petroleum jelly lipogranuloma of the penis treated with excision and native skin coverage. Urology. 2000;56(2):331. doi:10.1016/s0090-4295(00)00625-7.
10. Jeong JH, Shin HJ, Woo SH, Seul JH. A new repair technique for penile paraffinoma: bilateral scrotal flaps. Ann Plast Surg. 1996;37(4):386-93. doi:10.1097/00000637-199610000-00007.
11. Wong KT, Lee PS, Chan YL, Chow LT. Paraffinoma in anterior abdominal wall mimicking liposarcoma. Br J Radiol. 2003;76(904):264-7. doi:10.1259/bjr/31110098.
12. Murányi M, Varga D, Kiss Z, Flaskó T. A new modified bipedicle scrotal skin flap technique for the reconstruction of penile skin in patients with paraffin-induced sclerosing lipogranuloma of the penis. J Urol. 2022;208(1):171-178. doi:10.1097/JU.0000000000002480.
13. Lumbiganon S, Pachirat K, Sirithanaphol W, et al. Surgical treatment of penile foreign body granuloma: penile shaft reconstruction with single- versus two-stage scrotal flap techniques. Int J Urol. 2023;30(8):681-687. doi:10.1111/iju.15209.
14. Kang D, Hong SE, Kim YH. Single-stage penile resurfacing for foreign body granuloma: a simplified negative pressure wound therapy-assisted protocol with dermal substitute. Urology. 2026. doi:10.1016/j.urology.2026.04.013.
15. Shin YS, Zhao C, Park JK. New reconstructive surgery for penile paraffinoma to prevent necrosis of ventral penile skin. Urology. 2013;81(2):437-41. doi:10.1016/j.urology.2012.10.017.
16. Cormio L, Di Fino G, Scavone C, et al. Magnetic resonance imaging of penile paraffinoma: case report. BMC Med Imaging. 2014;14:39. doi:10.1186/1471-2342-14-39.
17. Hazir B, Merseburger AS, Roesch MC, Osmonov D. "Glans necrosis following penile procedures: a systematic review of etiology, frequency, and management." Int J Impot Res. Published online August 18, 2025. doi:10.1038/s41443-025-01151-1. PMID 40826180.
18. EAU-ASCO Penile Cancer Guidelines. EAU Guidelines. Edn. presented at the EAU Annual Congress London 2026. ISBN 978-94-92671-32-5. Diagnostic Evaluation and Staging.