Penile Reconstruction
This atlas organizes reconstruction of penile skin, glans and more extensive defects after trauma, infection, inflammatory disease, congenital differences or tumor resection. Start with the General Principles, then use the technique links according to the tissue missing and the patient's functional goals. Peyronie's surgery and Gender-Affirming Surgery have separate pathways.
Assess the problem
Determine what viable skin and dartos remain, whether the urethra, glans or corpora are involved, and whether the wound is ready for reconstruction. Preserve useful native tissue and avoid a closure that restricts erection. Review sensation, voiding, sexual activity, appearance, donor morbidity and the likelihood of staged treatment.[1][2]
| Presentation | Assessment that changes the plan |
|---|---|
| Adult-acquired buried penis | Separate shaft-skin deficiency from contributory suprapubic tissue, abdominal pannus and scrotal disease; evaluate associated urinary symptoms |
| Infection or Fournier's gangrene | Control infection and complete debridement before definitive coverage; determine bed viability and any need to fill dead space |
| LS or another inflammatory skin disorder | Assess skin, meatus and urethra separately; coordinate disease treatment and reconstruction |
| Foreign-body granuloma | Establish the extent of material and diseased tissue, healthy donor options and whether immediate coverage is appropriate |
| Lymphedema or hidradenitis | Assess combined penile, scrotal and perineal involvement; tailor tissue removal and coverage |
| Tumor excision | Establish histology, oncologic extent and appropriate margins before selecting reconstruction |
| Circumcision injury with shaft skin loss | Measure residual skin. In a 12-patient retrospective series with 65% to 95% skin loss, 9 injuries involved a Mogen clamp; 10 patients received FTSG and 2 received tissue expansion. Six of the 10 FTSG recipients had complications, including lymphedema in 3; the authors prefer expansion when enough residual skin can be expanded.[13] |
| Trauma or congenital/redo defect | Assess all involved structures and previous repairs; use specialist reconstruction where necessary. Tissue expansion is used after failed hypospadias or exstrophy-epispadias repair when residual skin is scarce |
Choose coverage by tissue requirements
| Findings | Options to consider | Important tradeoff |
|---|---|---|
| Enough viable skin for closure without distortion | Primary closure, local advancement or selected Z-plasty | Avoid tension and a constricting ring |
| Superficial loss with a vascularized bed | STSG or FTSG | Donor quality, graft take, contracture, sensation and hair characteristics |
| Need for vascularized coverage or additional tissue | Suitable local, regional or free flap | Pedicle availability, donor morbidity, bulk, hair and possible staging |
| Matrix-assisted grafting being considered | Product-specific dermal matrix plus STSG | Uncertain comparative benefit, cost and product-dependent timing |
| Residual skin suitable for planned expansion | Selected staged tissue expansion | Device complications, repeated visits and reoperation burden |
No validated circumference threshold universally separates primary closure, grafting and flap reconstruction. A graft bed and the covering over exposed corpora or testes must be assessed directly. Scrotal donor skin may be hair-bearing; neither a flap nor a graft guarantees normal sensation or elasticity.[1][2][3]
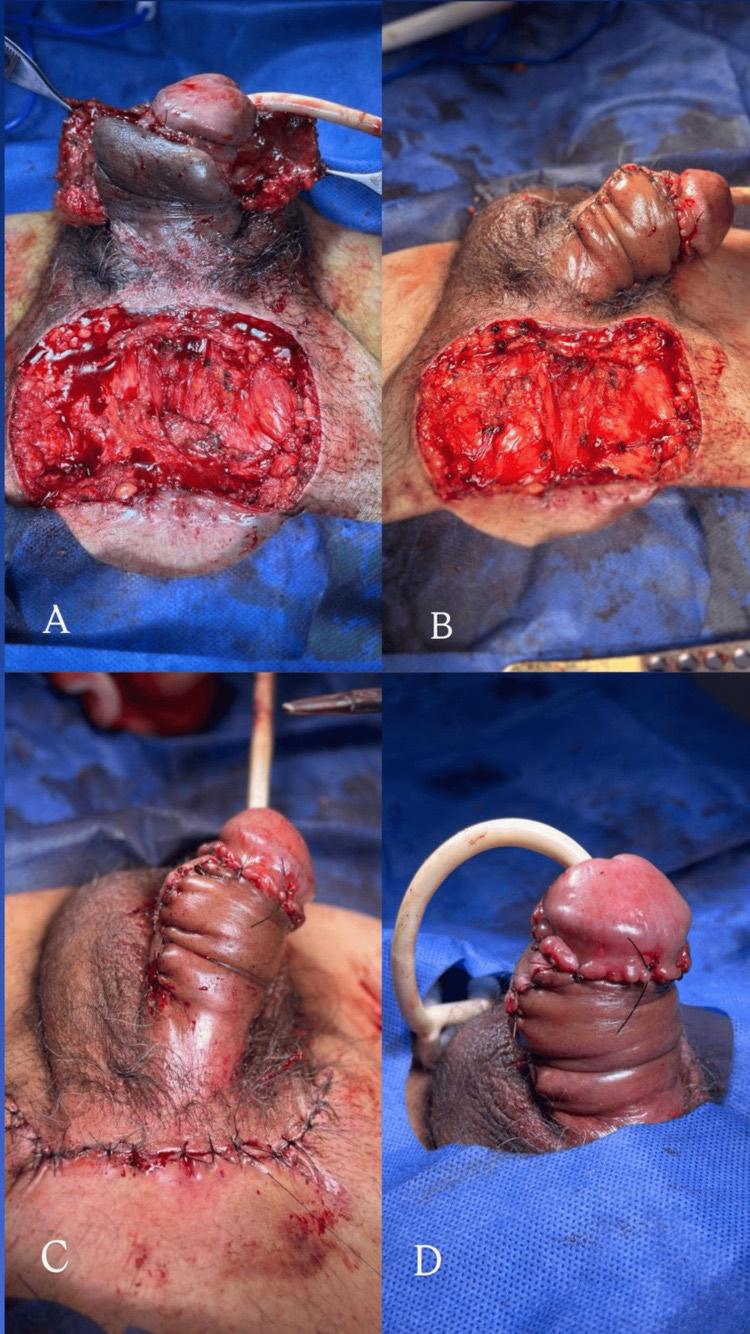
Staged regional-flap coverage of the penile shaft after skin necrosis. (A) Before division, the pedicled suprapubic flap is integrated with the shaft. (B) Pedicle division and release from the suprapubic donor site. (C) Advancement and contouring of the flap for definitive shaft coverage with a tension-free proximal inset. (D) Immediate postoperative appearance after completion of the inset. From Osio-Muñoz JA, et al. Cureus. 2026;18(3):e105606, Figure 5 (CC BY).[18]
Do not place Integra on a clinically infected wound or use it in a patient with known sensitivity to bovine collagen or chondroitin materials.[4] NPWT or a silicone cover does not remove this contraindication. MatriDerm and Integra are not interchangeable staged protocols: selected MatriDerm formulations have been used with simultaneous STSG, while bilayer Integra is often followed by delayed grafting.[4][5][6] Details are in Penile Skin Grafting and Penile Tissue Substitutes.
Retrospective series report outcomes for different genital reconstructions. In a 54-adult cohort including penile and scrotal grafts, STSG achieved more than 90% graft take in 52; the authors reported maintained or improved erection and normal voiding, with follow-up ranging from six months to ten years.[2] In 22 patients repaired with bilateral pedicled scrotal flaps, early complications were suture dehiscence (31.8%), infection (13.6%) and hematoma (4.6%), with 9.1% early revisions.[3] Late complications were skin retraction (27.3%), testicular ascension (22.7%) and penile shortening (13.6%), with 27.3% late revisions.[3]
Buried-penis classification
PAS describes the penile skin and escutcheon complex (P), abdominal pannus (A) and scrotal skin (S). In its 101-patient multicenter validation cohort from 10 institutions, agreement between two reviewers was high (κ = 0.95) and categories correlated with the operations performed. The most common subtypes were P2c (contributory escutcheon with insufficient penile skin; 27%), A0 (no pannus; 41%) and S0 (normal scrotal skin; 71%). Repairs included escutcheonectomy (59 patients), scrotoplasty (51), STSG (50), penile skin excision (47) and panniculectomy (7).[7] This supports structured description.[7]
Mirastschijski proposed a three-type system. Type 1 (pseudo-buried penis) has the penis under lax skin without retraction and is treated by apronectomy and prepubic lift with tissue fixation. Type 2 (intermediate) has partial invagination and is treated by prepubic apronectomy with anchoring sutures. Type 3 (classical) has complete retraction into prepubic fat, often with stenotic scar after circumcision, and is treated by scar excision, fat reduction with extraction of the shaft, anchoring sutures and reconstruction of the penile envelope. Use classifications to communicate anatomy while matching the operation to actual findings and patient goals.[8] See Buried Penis Repair.
Congenital penile torsion and penoscrotal web
Torsion and curvature are reassessed after degloving with an artificial erection. Degloving and release of dartos at the penoscrotal junction may itself reduce torsion; for persistent torsion, rotation of a dorsal dartos flap has been described.[14][15] For severe torsion, one described technique divides the dysgenetic dartos bands at the penile base and, through a ventral proximal midline incision when needed, fixes the base of the right corporal body to the pubic symphysis to add clockwise rotation, placing the suture lateral to the 10-o'clock dorsal-nerve branch; radical urethral mobilization has not been needed for isolated torsion in this author's experience. During skin closure in severe torsion, the median raphe is not used as the midline reference, because this can recreate counterclockwise rotation. One chapter recommends deferring newborn circumcision when counterclockwise torsion exceeds 60 degrees so repair and circumcision can occur under one anesthetic, and reports that dorsal dartos rotation, often combined with ventral dartos resection, has corrected torsion of 90 degrees or more, without a denominator or cohort.[15]
For penoscrotal webbing, one described approach uses inverted-V incisions on either side of the web and establishes the penoscrotal junction by securing ventral shaft skin to the corpora on either side of the urethra, avoiding skin dimpling.[14] These are chapter-attributed operative descriptions without denominators or comparative outcomes; the existing curvature guidance on the Peyronie's Disease pages remains the reference for acquired curvature.
Glans and cancer-related reconstruction
The 2026 EAU guideline strongly recommends offering organ-sparing surgery and reconstruction for PeIN, Ta or T1–T2 lesions confined to the glans or prepuce when the patient will comply with strict follow-up; obtain histologically negative margins for invasive carcinoma.[9] For PeIN alone at the margin, immediate re-resection has uncertain oncologic benefit, and EAU describes surveillance with or without topical therapy as reasonable.[9] The EAU guideline states that an excision margin of 5 to 10 mm gives acceptably low recurrence rates and that recurrence rose considerably only when the margin was under 1 mm. It allows minimal macroscopic margins for smaller, less aggressive lesions and suggests a wider margin or partial penectomy for higher-risk lesions. Margin width therefore depends on size, grade and invasion, and a universal 5–10 mm prescription is inappropriate for bulky or higher-risk tumors. Glans resurfacing preserves the underlying glans; glansectomy with neoglans reconstruction addresses a different defect. For a neoglans graft after glansectomy, discuss higher graft-failure risk in patients with poor vascular function, diabetes, immunosuppression or prior groin radiation.[9] EAU strongly recommends informing patients that organ-sparing surgery is associated with a higher risk of local recurrence than amputative surgery.[9] Local recurrence requires restaging and individualized salvage; EAU weakly recommends offering organ-sparing surgery for small recurrences without corpus cavernosum invasion and amputative surgery for large recurrences or corpus cavernosum involvement.[9]
Elst's 550-patient retrospective study involved a lower-risk glans-sparing cohort (79% pT1) and excluded lymphatic or systemic disease preceding or accompanying local recurrence.[10] At a median follow-up of 41 months it observed 29% local recurrence and 99% five-year cancer-specific survival.[10] Penile intraepithelial neoplasia in the surgical margin independently predicted local recurrence (HR 2.28).[10] Current EAU guidance specifically distinguishes higher-risk cohorts in which local recurrence is associated with poorer survival.[10][9]
A review of 14 studies encompassing 327 glansectomies found generally favorable functional outcomes but heterogeneous definitions and reporting; only five studies reported glansectomy separately.[11] At a mean follow-up of 40.7 months, the pooled recurrence proportion was 9.1%.[11] Reported proportions across studies were 91.1% with preserved erectile function, 62.5% sexually active, 75.6% voiding standing, 83.7% with maintained glans sensation and 86.3% satisfied with appearance; partial graft loss (6.1%) and meatal stenosis (8.1%) were the main complications.[11] See Glans Reconstruction.
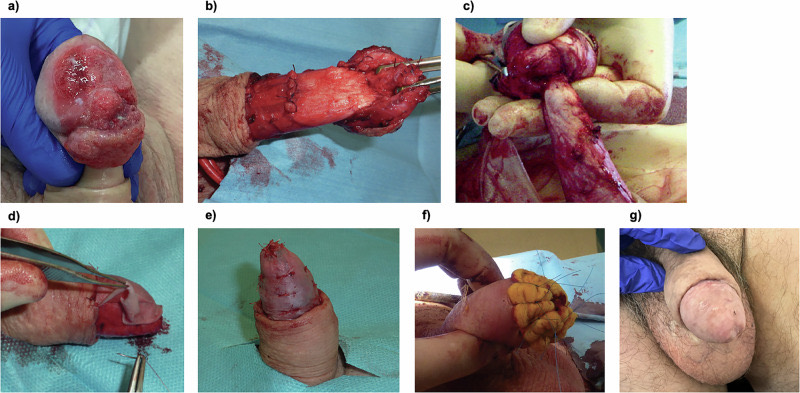
Glansectomy with split-thickness skin graft neoglans reconstruction. (a) Tumour confined to the glans. (b) Dissection above Buck's fascia. (c) Urethral transection, leaving about 1 cm beyond the corporal tips. (d, e) A split-thickness skin graft laid over the exposed distal corporal bodies. (f) Tie-over dressing for graft application. (g) Postoperative appearance. From Pang KH, et al. Int J Impot Res. 2026;38(3):206–213, Fig. 2 (CC BY 4.0).[11]
NCCN Version 2.2026 considers partial penectomy the standard surgical approach for high-grade primary tumors when a functional stump and negative margins can be retained; total penectomy is recommended when this is not feasible (category 2A). Cavernosal invasion requires partial or total penectomy, with intraoperative frozen sections to assess margins. Reconstruction is planned around the tissue remaining after an adequate resection.[17] NCCN restricts pT1a glansectomy to cases requiring it for complete clearance and lists penectomy for T2 or greater disease; EAU supports suitable organ-sparing surgery for glans-confined cT1–T2 disease.[17][9] These selection criteria differ from the EAU organ-sparing approach.[17][9]
For partial penectomy specifically, one described meatal-maturation sequence mobilizes the urethra distally from the corpus spongiosum (about 1–1.5 cm) before transection, spatulates it dorsally, and approximates it to the penile skin to form an oblique meatus whose open side faces 12 o'clock; adequate spatulation, mucosal eversion at skin approximation and a long elliptical suture line are proposed to reduce meatal stenosis.[16]
Interpret the technique database
The database includes established procedures and less common described techniques.[12]
Plan the sequence from the wound bed and defect extent: wound bed and infection status first, then circumference and structures exposed, then graft, flap, matrix or expansion, and finally concurrent procedures such as escutcheonectomy, scrotoplasty, panniculectomy or urethroplasty. Plan wound and donor-site care, dressing and catheter needs, and follow-up according to the actual reconstruction. Assess healing, sensation, erection-related tethering, urinary function, recurrent disease and patient-reported outcomes over time. Graft take, flap survival and success of the complete reconstruction are different endpoints.[2][3]
Treatment Database
| Procedure | Domain | Reconstructive role |
|---|---|---|
| Buried Penis Repair (overview) | Adult-Acquired Buried Penis | Integrated assessment of shaft skin, suprapubic tissue, scrotum and associated urinary problems. |
| Panniculectomy | Adult-Acquired Buried Penis | Abdominal pannus contributing to concealment or limiting access and care. |
| Escutcheonectomy | Adult-Acquired Buried Penis | Contributory suprapubic tissue; coordinate with the actual shaft-skin requirements. |
| Penile Skin Grafting (STSG / FTSG) | Shaft Skin — Graft | Surface coverage on a suitable vascularized bed after disease or tissue loss. |
| Primary Closure ± Z-Plasty (penis on stretch) | Shaft Skin — Graft | Defects with enough viable skin for tension-free closure; selected scar release. |
| Bipedicled Anterior Scrotal Flap (Fakin) | Shaft Skin — Flap | Selected shaft defects with suitable scrotal donor tissue and vascular supply. |
| Modified Bipedicle Scrotal Tunnel Flap (Murányi) | Shaft Skin — Flap | A described scrotal tunnel technique for selected foreign-body-related shaft defects. |
| Modified Bilateral Butterfly Scrotal Flap (Yao) | Shaft Skin — Flap | A described bilateral scrotal-flap option for shaft coverage. |
| Staged Bipedicled Scrotal Flap (Pribaz / McLaughlin) | Shaft Skin — Flap | Staged coverage of selected shaft-skin deficiencies after appropriate wound preparation. |
| Ventral Slit Scrotal Flap (VSSF) | Shaft Skin — Flap | Selected buried-penis repairs with usable dorsal skin; assess the complete defect. |
| Total Anterior Scrotal Flap (Zhao) | Shaft Skin — Flap | A specialized anterior scrotal-flap option for selected shaft defects. |
| Reverse Bilateral Anterior Scrotal Artery Flap (Gao) | Shaft Skin — Flap | A specialized scrotal-flap design requiring careful vascular and donor assessment. |
| Sensate External Pudendal Artery Perforator (EPAP) Hemi-Scrotal Flap (Tsukuura) | Shaft Skin — Flap | A sensate perforator-based option described in a case report; comparative outcomes are uncertain. |
| Penile Tissue Substitutes and Adjuncts | Tissue Substitute | Optional matrix-supported grafting; tissue expansion and NPWT have separate roles. |
| ALT Free Flap — Massive Genital / Perineal Defect | Free Tissue Transfer | Selected large or composite defects requiring vascularized tissue; assess pedicled and free options. |
| SCIP Lymphatic Flap (SCIP-LFT) — Genital Elephantiasis | Free Tissue Transfer | Selected lymphedema reconstruction combining coverage with a lymphatic-tissue approach; evidence remains limited. |
| Radial Forearm Free Flap (RFFF) — Total Penile Reconstruction | Free Tissue Transfer | One option for total penile reconstruction, with donor-site, sensory and staging tradeoffs. |
| Glans Resurfacing (TGR / PGR / CSGR) | Glans / Cancer Reconstruction | Selected superficial glans disease after histologic assessment; distinct from glansectomy. |
| Glansectomy With STSG | Glans / Cancer Reconstruction | Selected invasive glans-confined cancer after oncologic assessment and counseling. |
| Glanuloplasty With Flaps (IUF / Gulino / scrotal / rectus) | Glans / Cancer Reconstruction | Specialized neoglans reconstruction options after tissue loss or resection. |
| Inverted Urethral Flap (IUF) Glanuloplasty (Belinky / Chavarriaga) | Glans / Cancer Reconstruction | Urethral-flap neoglans reconstruction when suitable, adequately perfused urethral tissue is available. |
| Gulino Everted Urethral Flap Glanuloplasty | Glans / Cancer Reconstruction | An everted urethral-flap technique; select according to the resection and available tissue. |
| Scrotal Flap Glanuloplasty (Mazza / Cheliz) | Glans / Cancer Reconstruction | A scrotal-tissue option for selected neoglans defects. |
| Rectus Abdominis Myofascial Neoglans (Shaeer) | Glans / Cancer Reconstruction | A specialized myofascial neoglans technique described in limited reconstructive experience. |
| Microsurgical Penile / Glans Replantation | Trauma / Replantation | Urgent specialist assessment after penile or glans amputation. |
| Cecil-Culp Procedure (Scrotal Dropback) | Staged / Salvage | Selected staged salvage of complex urethrocutaneous fistula and penile-skin defects. |
| Penile / Total Penis-Scrotum-Lower-Abdominal-Wall VCA (GUVCA) | Staged / Salvage | Highly selected transplantation requiring specialized evaluation and long-term immunosuppression. |
References
1. Kristinsson S, Johnson M, Ralph D. Review of penile reconstructive techniques. Int J Impot Res. 2021;33(3):243–250. doi:10.1038/s41443-020-0246-4
2. Alwaal A, McAninch JW, Harris CR, Breyer BN. Utilities of split-thickness skin grafting for male genital reconstruction. Urology. 2015;86(4):835–839. doi:10.1016/j.urology.2015.07.005
3. Mendel L, Neuville P, Allepot K, et al. Bilateral pedicled scrotal flaps as an alternative to skin graft in penile shaft defects repair. Urology. 2023;176:206–212. doi:10.1016/j.urology.2023.03.025
4. US Food and Drug Administration. Integra Dermal Regeneration Template / Omnigraft: Summary of Safety and Effectiveness Data, P900033/S042. 2016. Contraindications. FDA SSED.
5. Liguori G, Papa G, Boltri M, et al. Reconstruction of penile skin loss using a combined therapy of negative-pressure wound therapy, dermal regeneration template, and split-thickness skin graft application. Int J Impot Res. 2020;33(8):854–859. doi:10.1038/s41443-020-00343-1
6. Crane J, Lloyd A, Kaul A, Sethia K, Clibbon J. Matriderm® as a biological scaffold in penile resurfacing: a single-centre case series. J Plast Reconstr Aesthet Surg. 2026;115:325–330. doi:10.1016/j.bjps.2026.02.045
7. Schlaepfer CH, Flynn KJ, Alsikafi NF, et al. Clinical validation of an adult-acquired buried penis classification system based on standardized evaluation of the penis, abdomen, and scrotum. Urology. 2023;180:249–256. doi:10.1016/j.urology.2023.04.048
8. Mirastschijski U. Classification and treatment of the adult buried penis. Ann Plast Surg. 2018;80(6):653–659. doi:10.1097/SAP.0000000000001410
9. European Association of Urology. EAU Guidelines on Penile Cancer. 2026. Disease management, primary tumour, section 6.1. Guideline.
10. Elst L, Roussel E, Miletic M, et al. Local recurrence after glans-sparing surgery: no impact on penile cancer-specific survival. BJU Int. 2026;137(1):146–153. doi:10.1111/bju.70055
11. Pang KH, Alnajjar HM, Muneer A. Functional outcomes of glansectomy to treat localised penile cancer: a systematic review. Int J Impot Res. 2026;38(3):206–213. doi:10.1038/s41443-025-01062-1
12. Tsukuura R, Engmann T, Miyazaki T, Yamamoto T. The sensate external pudendal artery perforator (EPAP) hemi-scrotal flap for the circumferential skin defect of the penile shaft: a case report and literature review. Microsurgery. 2025;45(7):e70123. doi:10.1002/micr.70123
13. Harris TGW, Khandge P, Wu WJ, et al. Surgical approach to penile reconstruction for shaft skin excision from circumcision. Pediatr Surg Int. 2023;39(1):138. doi:10.1007/s00383-023-05409-x
14. Bush NC, Snodgrass WT. Congenital Penile Abnormalities. In: Muneer A, Arya M, Jordan GH, eds. Atlas of Male Genitourethral Surgery: The Illustrated Guide. Wiley-Blackwell; 2014:25-42.
15. Fisher PC, Park JM. Penile torsion repair using dorsal dartos flap rotation. J Urol. 2004;171(5):1903-1904. doi:10.1097/01.ju.0000120148.79867.5c
16. Gonzalgo ML, Ritch CR, Parekh DJ. Partial Penectomy. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:1012-1015.
17. National Comprehensive Cancer Network. NCCN Clinical Practice Guidelines in Oncology: Penile Cancer. Version 2.2026. June 5, 2026.
18. Osio-Muñoz JA, Álvarez-Dávalos C, Hernández-Mancillas EM, Hernadez-Macillas M, Vázquez-Lara SE. Penile reconstruction with a pedicled suprapubic flap after cutaneous necrosis secondary to modeling substance disease: a case report. Cureus. 2026;18(3):e105606. doi:10.7759/cureus.105606