Vulvar Reconstruction
Non-gender-affirming vulvar reconstruction addresses defects and sequelae of vulvar cancer, extramammary Paget disease (EMPD), VIN, lichen sclerosus and lichen planus, FGM/C, trauma, vulvar hidradenitis suppurativa and GSM-related symptoms treated with fat grafting. Feminizing gender-affirming vulvoplasty and vaginoplasty are covered under 04k Gender-Affirming Surgery.
Decision Framework
Vulvar reconstruction restores form and function of a composite three-dimensional structure: labia majora and minora, clitoral hood and clitoris, vestibule, posterior fourchette and perineal body. It also protects pudendal blood supply and sensation.[2][3] Indications include defects after vulvar cancer, extramammary Paget disease or VIN excision; selected refractory sequelae of lichen sclerosus or lichen planus; FGM/C; trauma; infection; and hidradenitis suppurativa. WHO estimates that more than 230 million girls and women alive today have undergone FGM/C.[22] Höckel and Dornhöfer describe neoplastic defect classes; Ricotta proposes a location-based Toulouse algorithm; Han and Caretto describe other selected reconstructive pathways.[2][5][7][18] Kwong's prospective 69-woman/136-flap mixed-condition cohort reports postoperative wound and patient-reported outcomes without a primary-closure comparator.[4] FGM/C operations and other indications require their own counseling and evidence appraisal.[13][14][19]
Assess Clinical Context
| Variable | Sub-Categories |
|---|---|
| Etiology | Vulvar cancer / EMPD / VIN (occult invasion in 4/13 of one selected skinning-vulvectomy series[8]) / lichen sclerosus or lichen planus sequelae / FGM/C / trauma / Fournier's gangrene / vulvar HS. Fat grafting for GSM-related symptoms is investigational, not an established reconstructive first-line indication. |
| Defect characteristics | Location (anterior commissure / lateral hemivulva / posterior / total); depth (superficial vs deep); size; adjacent-structure involvement (vagina / urethra / anus / groin / mons pubis) |
| Primary vs secondary reconstruction | Prior surgery / flaps used; prior radiation; recurrent disease |
| Patient factors | Age, BMI, smoking, diabetes, radiation history, comorbidities, fertility goals (preservation if oncologic) |
| Functional goals | Sexual function, continence, ambulation and body image; in Kwong's selected questionnaire subset, 40/45 respondents said reconstruction helped acceptance of their cancer diagnosis and surgery[4] |
Determine If Reconstruction Is Needed
Consider reconstruction when primary approximation would impose excessive tension, distort the urethra or introitus, leave dead space or compromise function. For vulvar squamous-cell carcinoma, ESGO 2023 recommends reconstructive expertise within the multidisciplinary team for early and advanced disease and selection by patient and tumor characteristics and team experience .[34] The guideline identifies no preferred reconstructive technique.[34] Coordinate cancer extent and treatment with the disease-specific pathway.[6] Kwong's prospective cohort reported none-to-mild complications for 126/136 flaps at day 7 and 113/136 at days 8–30.[4]
Technique Selection by Defect Type
The options below summarize published techniques by defect pattern. Match available vascular territory, depth, radiation, oncologic margins and patient goals in a reconstructive team.
| Defect Type | Reported options to consider | Other options | Key constraint |
|---|---|---|---|
| Small, anterior or posterior commissure | Limberg (rhomboid) flap or primary closure when laxity allows | Anterior- or posterior-based labial flap | Closure under tension at the posterior fourchette (introital stenosis) |
| Moderate, lateral (hemivulvectomy) | Consider V-Y medial-thigh, lotus petal (LPF) or another nearby flap according to reach and vascularity | Internal pudendal-artery perforator (IPAP) flap in selected defects; Han's approach is a cohort-specific algorithm | A flap whose pedicle or donor area is compromised by resection or prior treatment |
| Moderate, posterior | Gluteal V-Y flap or lotus petal (lower-petal variant) with scar in gluteal fold | Genito-crural island perforator flap in selected defects (Commenge 2026: 27 patients / 46 flaps)[16] | Posterior closure under tension |
| Total vulvectomy | Bilateral V-Y + bilateral LPF combinations; pubolabial V-Y flap can reconstruct the entire vulva with a single flap | Combined flap algorithms per Höckel-Dornhöfer 11-procedure taxonomy | Pubolabial V-Y when groin dissection has extended medially |
| Extended with inguinal involvement | Pedicled ALT flap in selected extended defects, as described by Gentileschi, especially when inguinal or previously treated tissue is involved[17] | Tensor fasciae latae (TFL) flap when donor territory and reach fit | Mons pubis flap when groin dissection has compromised the superficial external pudendal artery |
| Extended, posterior (perianal / gluteal) | Gluteal-thigh flap (inferior gluteal artery; ideal for posterior orientation) | Gracilis myocutaneous flap | VRAM when posterior orientation is dominant |
| Extended, anterior (suprapubic) | VRAM (large pelvic dead-space filling) or pedicled DIEP (rectus-sparing alternative) | ALT flap | VRAM in patient at high abdominal-hernia risk; consider DIEP |
| Vulvar + vaginal (Negosanti Type II) | Pedicled DIEP flap (Negosanti 2015 algorithm; Type II requires tissue volume)[15] | VRAM; tubularized gracilis or ALT for neovagina | Skin grafts alone for combined vulvovaginal defects |
| Superficial (VIN / Paget — skinning vulvectomy) | STSG (scalp / thigh / buttock donor) permits histologic examination; occult invasion was 4/13 in Lavoué's selected cohort[8] | FTSG from groin crease in small selected defects; historical skinning-vulvectomy experience provides context[9] | STSG when deep defect requires bulk |
| Secondary reconstruction (recurrence) | Choice depends on unused flaps and the radiation field. Caretto's 2023 algorithm uses ALT, DIEP, V-Y or a free flap as needed[18] | Free flap when all pedicled options exhausted | Re-using already-radiated flap territory |
| FGM/C reconstruction | Offer individualized multidisciplinary assessment of FGM/C type, anatomy and symptoms. WHO 2025 conditionally recommends deinfibulation for women and girls with Type III FGM/C (low-certainty evidence) and conditionally suggests clitoral reconstruction for selected women living with FGM/C (very-low-certainty evidence), with informed counseling before surgery.[23] | Foldès-style reconstruction, selected aOAP/hood variants or Mañero vaginal-mucosal graft, each with different source populations[13][21] | Automatic surgery or promised sensory/sexual outcomes |
| Lichen sclerosus with introital stenosis | Optimize disease control; consider perineoplasty / de-adhesion for persistent functional stenosis despite adequate topical treatment[10] | Selected local flap or aOAP for complex refractory sequelae; fat grafting remains investigational | Operating on uncontrolled active disease; applying one cohort's relapse percentage to all procedures |
| GSM / vulvar atrophy | Evidence-based nonsurgical management and individualized assessment | Fat grafting or PRP remain investigational for GSM; evidence for symptom benefit is limited[32] | Presenting regenerative surgery as established first-line care |
For a posterior perineal/perianal defect, one described design uses bilateral broad-based local flaps: each flap is freed from the underlying fat, rotated posteriorly and medially to cover the defect, and its distal edge sutured to the anal mucosa, with an illustrated flap length of about half the base width (for example 3 cm length to a 6 cm base).[28]
Delayed secondary reconstruction after direct closure remains an option when a late functional problem emerges.[29] One case report describes a patient with chronic burning vulvar pain from urethral-orifice eversion presenting three years after radical vulvectomy with direct closure, treated with bilateral 14 × 5 cm gluteal-fold flaps at that time;the authors advocate immediate reconstruction to avoid this sequela.[29]
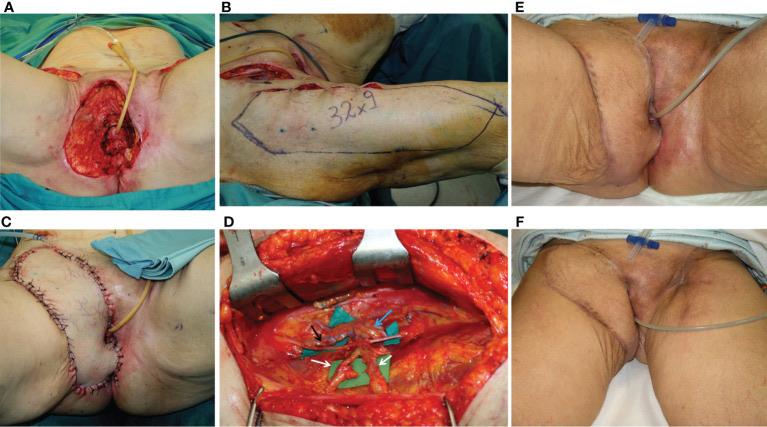
Secondary reconstruction with a pedicled anterolateral thigh (ALT) flap. (A) Defect of the entire right perineum, mons pubis and right groin after excision of recurrent vulvar cancer. (B) ALT flap marked on the right thigh with a 32 × 9 cm skin paddle. (C) Flap inset for vulvo-perineal and right groin reconstruction. (D) Pedicle with two perforators (white arrows) from the descending branch of the lateral circumflex femoral artery (blue arrow), with the motor nerve to vastus lateralis spared (black arrow). (E, F) Late postoperative results with uneventful wound healing. From Caretto AA, et al. Front Oncol. 2023;13:1195580, Figure 5 (CC BY).[18]
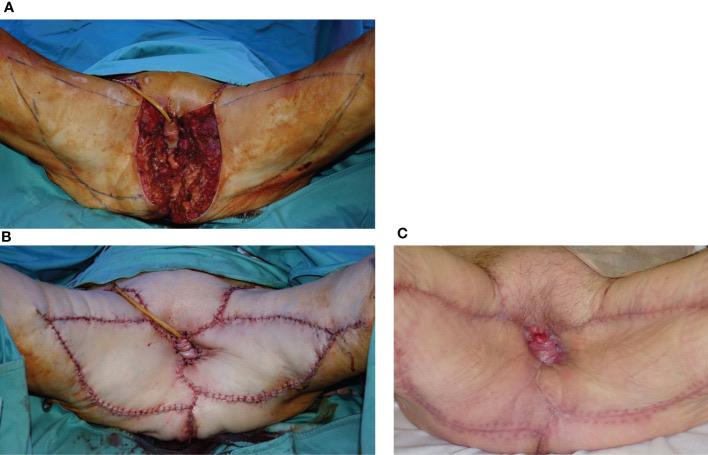
(A) Posterior pelvectomy for recurrent vulvar cancer after previous surgery and radiation therapy, with flap outlines marked. (B) Defect repaired with bilateral V-Y advancement flaps. (C) Late postoperative result with uneventful wound healing. From Caretto AA, et al. Front Oncol. 2023;13:1195580, Figure 7 (CC BY).[18]
Perforator vs Musculocutaneous Flap Sub-Comparison
| Feature | Fasciocutaneous (local LPF / V-Y and perforator IPAP / ALT / genito-crural) | Musculocutaneous (VRAM / gracilis) |
|---|---|---|
| Donor-site morbidity | Varies by flap and harvest | Eseme's proportional meta-analysis reported 57.6% for VRAM versus 16.0% for gracilis across different oncologic series[20] |
| Tissue bulk for pelvic dead space | Volume varies by flap; Negosanti used pedicled DIEP for Type II vulvovaginal defects requiring pelvic dead-space fill[15] | Substantial bulk with VRAM and with gracilis muscle |
| Irradiated recipient bed | Depends on the pedicle, radiation field and remaining tissue | Vascularized bulk may help selected deep defects; no universal superiority is established |
| Sensation preservation | Depends on flap design and nerve preservation | Depends on design and nerve preservation |
| Aesthetic outcome | Often thinner and locally matched, with case-specific tradeoffs | May provide necessary volume but require contour adjustment |
| Surgical complexity | Depends on perforator dissection and defect | Depends on harvest, transfer and donor closure |
| Evidence context | Small, heterogeneous location-specific series and author algorithms[5][7][15] A 2024 meta-analysis of 49 studies (1,840 women) reported no statistically significant difference in short-term complication rates between patients receiving perforator (n = 276) and non-perforator (n = 1,564) reconstructions.[31] The non-perforator group included local lotus-petal and V-Y flaps as well as muscle flaps; quality-of-life data were sparse.[31] | Proportional meta-analysis and selected observational cohorts with different defects and treatment histories[1][20] |
Special Decision Branch — Clitoral / Vulvovestibular Reconstruction Post-FGM/C
The extent of clitoral injury varies by FGM/C type and individual anatomy. A residual clitoral body may be accessible beneath scar, but its presence, neurovascular integrity and potential function must be assessed rather than assumed.[19][23]
| Step | Operation | Anchor |
|---|---|---|
| 1 | Assess scar and remnant anatomy; a Foldès-style approach releases scar and exposes the clitoral remnant while protecting dorsal neurovascular structures | Foldès original technique; 38/40 studies in Almadori's scoping review used Foldès-style clitoral reconstruction, which is not the same as 95% of patients[14][24] |
| 2 | Selected suspensory-ligament release and downward mobilization, avoiding neurovascular injury | Foldès and variant-specific technique descriptions[13][24] |
| 3 | Fixation and any projection target depend on the chosen variant; bulbocavernosus anchoring and ≥ 5-mm projection are O'Dey-specific teaching, not Foldès requirements | O'Dey 2024 PRS[13] |
| 4 | Optional Omega-Domed (OD) preputial flap for clitoral hood reconstruction (85% of O'Dey series) | O'Dey 2024 PRS[13] |
| 5 | Optional aOAP flap in selected complex cases (used in 36% of O'Dey's 119-person mixed-procedure FGM/C cohort) | O'Dey 2024 PRS[13] |
| 6 | Offer sexual-health counseling before or alongside surgery and multidisciplinary support, with individual follow-up needs | WHO 2025 conditional recommendation[23] |
| Alternative | Vaginal mucosal graft for clitoral / labial reconstruction; Mañero's 32-person series reported mean FSFI 16 to 29 without a control group | Mañero 2018 Obstet Gynecol[21] — see database |
Special Decision Branch — Surgical Management of Lichen Sclerosus
LS surgery addresses selected functional sequelae despite adequate medical treatment; it does not cure the inflammatory disease.[10][25] Continue individualized dermatologic follow-up and topical therapy according to activity and current guidance.[10][25]
| Indication | Reported surgical approach | Other considerations | Caveat |
|---|---|---|---|
| Introital stenosis with dyspareunia / apareunia after adequate topical therapy | Perineoplasty / de-adhesion (Lauber 2021: 41 respondents from 70 invited; median follow-up 2.3 years (range 1–5)) | Local skin flap in selected defects | Continue individualized disease control; residual dyspareunia was reported by 10/27 Lauber respondents who answered that item[10] |
| Severe refractory LS with sexual dysfunction | Skinning vulvectomy followed by bilateral aOAP reconstruction was used in 53/61 selected patients in O'Dey’s retrospective mixed-procedure series[11] | Additional scar surgery or clitoral re-exposure was performed when indicated[11] | Relapse risk requires ongoing dermatologic surveillance |
| LS sequelae after multiple failed interventions | Selected local skin flaps; Rangatchew's series of 38 women reported a surgical benefit in 75% of survey respondents with baseline dyspareunia, with an 8.4-year mean clinical follow-up in those followed[27] | Topical disease management and counseling remain necessary | Its 38% severe relapse is from a small followed subgroup[27] |
Lichen Planus-Related Vulvovaginal Agglutination
For selected patients with vulvovaginal agglutination due to lichen planus, a 34-patient retrospective series described adhesion lysis and intraoperative dilator placement, removal of the dilator after 48 hours, and high-potency intravaginal corticosteroid with regular dilator use thereafter.[33] Severe re-agglutination occurred in 2/34 patients and reoperation in 1/34.[33]
Concurrent Procedures
| Procedure | When |
|---|---|
| Inguinofemoral lymphadenectomy | Through separate incisions from vulvectomy; may limit availability of groin-based flaps. See Groin Defect Reconstruction After Inguinal Lymphadenectomy for groin-wound coverage options. |
| Sentinel lymph-node biopsy | Oncologic eligibility depends on full staging, groin assessment and current specialist guidelines; coordinate with the vulvar-cancer pathway |
| Vaginal reconstruction | If vaginal resection is included, evaluate bowel, including sigmoid, or tubularized vascularized tissue according to the defect; sigmoid is not established as preferred |
| Urethral reconstruction | If urethral meatus is involved — careful repositioning to prevent stenosis or spraying |
| Psychosexual counseling | Offer according to patient goals and indication, particularly before or alongside FGM/C reconstruction[23] |
| Adjuvant radiotherapy | Coordinate timely treatment with oncology. In Commenge's uncontrolled cohort, adjuvant vulvar radiotherapy started without delay after genito-crural flaps[16] |
For vulvar cancer surgery, the 2026 ESGO consensus recommends IV antimicrobial prophylaxis within 60 minutes before incision, with intraoperative redosing for prolonged procedures .[30]
Postoperative Management & Surveillance
- Wound dehiscence is common; pooled rates across flap designs and indications have limited value for individual prognosis.
- Sexual rehabilitation. In Kwong's respondent subsets, sexual activity was reported by 5/54 preoperatively and 11/45 at 12 months (p = 0.041).[4]
- Urinary continence. In the same cohort, 26/54 reported no incontinence before surgery versus 37/46 at 12 months (p = 0.0038); follow-up denominators differed.[4]
- Oncologic surveillance. In a retrospective series of 36 women reconstructed after resection of advanced or recurrent vulvar malignancy, 21 (58.3%) recurred at a median of 5 months after reconstruction.[26]
- LS-specific. Monitor ongoing inflammation and functional recurrence; tailor topical maintenance to activity and guideline-based follow-up.[12][25]
- FGM/C-specific. Offer multidisciplinary follow-up responsive to sexual-health, psychological and urogenital needs; no single patient-reported scale is mandatory for every person.[23]
Treatment Database
| Procedure | Domain | Best for / indication |
|---|---|---|
| Primary Closure (small defects with adequate laxity) | Primary Closure / Graft | Small anterior-vulvar defects with adequate laxity; avoid tension at posterior fourchette. |
| Skin Graft — STSG (scalp donor) / FTSG (groin donor) | Primary Closure / Graft | Superficial defects after skinning vulvectomy for VIN / Paget. |
| Limberg (Rhomboid) Flap | Local Random / Fasciocutaneous | Small anterior or posterior commissure defects when laxity allows a rhomboid transposition. |
| V-Y Advancement — Medial Thigh | Local Random / Fasciocutaneous | Moderate lateral (hemivulvectomy) defects; local advancement flap from the medial thigh. |
| V-Y Advancement — Gluteal | Local Random / Fasciocutaneous | Moderate posterior defects; advancement flap with the scar in the gluteal fold. |
| V-Y Advancement — Pubolabial (Single-Flap Total Vulva) | Local Random / Fasciocutaneous | Total vulvectomy defects; reported as a single-flap reconstruction of the entire vulva. |
| Lotus Petal Flap (LPF) | Local Random / Fasciocutaneous | Moderate lateral or posterior defects; local fasciocutaneous transposition flap. |
| Pudendal-Thigh (Singapore) Flap | Local Random / Fasciocutaneous | Local fasciocutaneous pudendal-thigh flap for vulvar and vaginal defects. |
| Gluteal-Fold (Sulcus / Infragluteal) Flap | Local Random / Fasciocutaneous | Posterior vulvar and perineal defects; flap from the gluteal fold. |
| Genito-Crural Island Perforator Flap (GCIPF) | Local Random / Fasciocutaneous | Lateral / anterior vulvar defects; perforator island flap from the labiocrural fold. |
| Internal Pudendal Artery Perforator (IPAP) Flap | Local Random / Fasciocutaneous | Reported option for selected medial vulvar defects; confirm perforator anatomy, reach and donor suitability. |
| External Pudendal Artery Perforator (EPAP) Flap | Local Random / Fasciocutaneous | Anterior / mons-pubis / hemivulvectomy defects; hair-bearing skin matched to labia majora. |
| Medial Circumflex Femoral Artery Perforator (MCFAP) Flap | Local Random / Fasciocutaneous | Medial-thigh perforator flap for vulvar and perineal defects. |
| Profunda Artery Perforator (PAP / DFAP) Flap | Local Random / Fasciocutaneous | Perforator flap from the posterior-medial thigh on profunda artery branches. |
| Inferior Gluteal Artery Perforator (IGAP) Flap | Local Random / Fasciocutaneous | Posterior and perineal vulvar defects; perforator flap from the inferior gluteal region. |
| Vertical Posteromedial Thigh (vPMT / PMTP) Propeller Flap | Local Random / Fasciocutaneous | Extensive perianal-genital defects; propeller perforator from posteromedial thigh on profunda perforators. |
| Anterior- or Posterior-Based Labial Flap | Local Random / Fasciocutaneous | Anterior or posterior commissure defects and partial vaginal-wall deficit. |
| Mons-Pubis Flap (Mayer SEPA Pedicle Flap) | Local Random / Fasciocutaneous | Hemivulvectomy defects needing hair-bearing skin matching the labia majora. |
| Pedicled Anterolateral Thigh (ALT) Flap | Regional Pedicled | Reported option for extended vulvar or inguinal defects when its pedicle and arc of rotation are suitable. |
| Gracilis Myocutaneous Flap (Standard or Short-Gracilis Variant) | Regional Pedicled | Pelvic dead-space obliteration; selected lateral or vaginal reconstruction. |
| Transverse Upper Gracilis (TUG) Flap | Regional Pedicled | Lateral vulvar defects beyond the vulvo-crural fold; transverse-design gracilis variant. |
| Vertical Rectus Abdominis Myocutaneous (VRAM) Flap | Regional Pedicled | Anteriorly extended defects and combined vulvovaginal reconstruction after exenteration. |
| Transverse Rectus Abdominis Myocutaneous (TRAM) Flap | Regional Pedicled | Historically reported for vulvar and vaginal reconstruction; the linked page has comparative context. |
| Pedicled DIEP Flap (Deep Inferior Epigastric Perforator) | Regional Pedicled | Reported muscle-sparing option for selected combined vulvar-vaginal defects; not an automatic Negosanti Type II assignment. |
| Tensor Fasciae Latae (TFL) Flap | Regional Pedicled | Regional option when the defect involves the groin and donor/pedicle territory remains viable. |
| Gluteal-Thigh (Posterior-Thigh / Friedman-Reece) Flap | Regional Pedicled | Posteriorly extended defects with perianal / gluteal extension; irradiated bed. |
| Free ALT Flap (Single Split Flap for Total Vulvectomy) | Free Tissue Transfer | Total vulvectomy when pedicled ALT cannot reach or prior flaps used. |
| Free DIEP Flap (Secondary Reconstruction) | Free Tissue Transfer | Secondary reconstruction when abdominal pedicled flaps are unavailable or irradiated. |
| Foldès Clitoral Reconstruction (± OD Preputial Flap) | FGM/C Reconstruction | Selected FGM/C clitoral reconstruction after informed counseling; outcomes vary and the dorsal neurovascular structures are protected. |
| Vaginal Mucosal Graft for Clitoral / Labial Reconstruction (Mañero) | FGM/C Reconstruction | FGM/C neoclitoral coverage and labial reconstruction using free vaginal-mucosal graft. |
| Anterior Obturator Artery Perforator (aOAP) Flap — Vulvovestibular | FGM/C Reconstruction | Vulvovestibular reconstruction in FGM/C and refractory LS after skinning vulvectomy. |
| Fat Grafting for FGM/C Vulvar Scars | FGM/C Reconstruction | Experimental fat-grafting approach for selected FGM/C scars; long-term benefit and comparative efficacy remain unknown. |
| Defibulation (Type III FGM/C) | FGM/C Reconstruction | Type III FGM/C after individualized assessment and counseling; pregnancy timing may be antepartum or intrapartum according to preference and clinical context. |
| Fat Grafting (± PRP / SVF) for Vulvar LS | Regenerative / Fat Grafting | Investigational adjunct for selected LS symptoms; not a replacement for individualized topical disease control. |
| Microfat / Nanofat Grafting for GSM (Vulvar Atrophy) | Regenerative / Fat Grafting | Investigational adjunct for selected GSM symptoms after standard options and patient goals are reviewed. |
| Perineoplasty / De-Adhesion (LS Introital Stenosis) | Lichen Sclerosus — Surgical | LS introital stenosis causing dyspareunia despite adequate clobetasol. |
| Skinning Vulvectomy + aOAP Flap (Severe Refractory LS) | Lichen Sclerosus — Surgical | Severe refractory LS with sexual dysfunction unresponsive to conservative care. |
| Local Skin Flaps for LS Sequelae (Long-Term Outcomes) | Lichen Sclerosus — Surgical | Selected LS sequelae after disease control; one small long-term series reported severe relapse in 38% of those followed, not a universal risk. |
| Acquired Vaginal Stenosis Repair | Other Acquired Vaginal / Vestibular — Surgical | Vaginal narrowing or shortening after radiation, prolapse surgery, vaginectomy or fistula repair; release, flap or graft by extent of scar. |
| Vestibulectomy | Other Acquired Vaginal / Vestibular — Surgical | Refractory localized provoked vestibulodynia after conservative and medical management has failed. |
References
1. Singh M, Kinsley S, Huang A, et al. Gracilis-flap reconstruction of the perineum: an outcomes analysis. J Am Coll Surg. 2016;223(4):602–610. doi:10.1016/j.jamcollsurg.2016.06.383
2. Höckel M, Dornhöfer N. Vulvovaginal reconstruction for neoplastic disease. Lancet Oncol. 2008;9(6):559–568. doi:10.1016/S1470-2045(08)70147-5
3. Pavlov A, Bhatt N, Damitz L, Ogunleye AA. A review of reconstruction for vulvar cancer surgery. Obstet Gynecol Surv. 2021;76(2):108–113. doi:10.1097/OGX.0000000000000866
4. Kwong FL, Pounds R, Farah Y, Yap JKW. Vulval flap reconstruction in women with benign, preneoplastic and malignant vulval conditions: a prospective study. BJOG. 2025;132(8):1156–1165. doi:10.1111/1471-0528.18156
5. Ricotta G, Russo SA, Ferron G, Meresse T, Martinez A. The Toulouse algorithm: vulvar cancer location-based reconstruction. Int J Gynecol Cancer. 2025;35(4):100065. doi:10.1016/j.ijgc.2024.100065
6. National Comprehensive Cancer Network. Vulvar Cancer (NCCN Clinical Practice Guidelines). Updated 2026-01-06.
7. Han WY, Kim Y, Han HH. A simplified algorithmic approach to vulvar reconstruction according to various types of vulvar defects. Ann Plast Surg. 2023;91(2):270–276. doi:10.1097/SAP.0000000000003597
8. Lavoué V, Lemarrec A, Bertheuil N, et al. Quality of life and female sexual function after skinning vulvectomy with split-thickness skin graft in women with vulvar intraepithelial neoplasia or vulvar Paget disease. Eur J Surg Oncol. 2013;39(12):1444–1450. doi:10.1016/j.ejso.2013.09.014
9. Rettenmaier MA, Berman ML, DiSaia PJ. Skinning vulvectomy for the treatment of multifocal vulvar intraepithelial neoplasia. Obstet Gynecol. 1987;69(2):247–250.
10. Lauber F, Vaz I, Krebs J, Günthert AR. Outcome of perineoplasty and de-adhesion in patients with vulvar lichen sclerosus and sexual disorders. Eur J Obstet Gynecol Reprod Biol. 2021;258:38–42. doi:10.1016/j.ejogrb.2020.12.030
11. O'Dey DM, Rosendahl M, Mordehay D, Kameh Khosh M. Anterior obturator artery perforator (aOAP) flap: a last-resort treatment option for sexual dysfunction in lichen sclerosus et atrophicus. J Plast Reconstr Aesthet Surg. 2024;95:331–339. doi:10.1016/j.bjps.2024.05.046
12. American College of Obstetricians and Gynecologists. Diagnosis and management of vulvar skin disorders: ACOG Practice Bulletin Summary, Number 224. Obstet Gynecol. 2020;136(1):222–225. doi:10.1097/AOG.0000000000003945
13. O'Dey DM, Kameh Khosh M, Boersch N. Anatomical reconstruction following female genital mutilation/cutting. Plast Reconstr Surg. 2024;154(2):426–438. doi:10.1097/PRS.0000000000011026
14. Almadori A, Palmieri S, Coho C, et al. Reconstructive surgery for women with female genital mutilation: a scoping review. BJOG. 2024;131(12):1604–1619. doi:10.1111/1471-0528.17886
15. Negosanti L, Sgarzani R, Fabbri E, et al. Vulvar reconstruction by perforator flaps: algorithm for flap choice based on the topography of the defect. Int J Gynecol Cancer. 2015;25(7):1322–1327. doi:10.1097/IGC.0000000000000481
16. Commenge V, Martinez A, Ricotta G, et al. Use of the genito-crural island perforator flap in vulvar reconstruction: a single-center experience. Int J Gynecol Cancer. 2026;36(2):102847. doi:10.1016/j.ijgc.2025.102847
17. Gentileschi S, Servillo M, Garganese G, et al. Versatility of pedicled anterolateral thigh flap in gynecologic reconstruction after vulvar cancer extirpative surgery. Microsurgery. 2017;37(6):516–524. doi:10.1002/micr.30077
18. Caretto AA, Servillo M, Tagliaferri L, et al. Secondary post-oncologic vulvar reconstruction — a simplified algorithm. Front Oncol. 2023;13:1195580. doi:10.3389/fonc.2023.1195580
19. Meremikwu C, Oringanje C, Moses C, et al. Clitoral reconstructive surgery in women and girls living with female genital mutilation: a systematic review. Int J Gynaecol Obstet. 2026;172 Suppl 1:81–94. doi:10.1002/ijgo.70760
20. Eseme EA, Scampa M, Viscardi JA, et al. Surgical outcomes of VRAM vs gracilis flaps in vulvo-perineal reconstruction following oncologic resection: a proportional meta-analysis. Cancers. 2022;14(17):4300. doi:10.3390/cancers14174300
21. Mañero I, Labanca T. Clitoral reconstruction using a vaginal graft after female genital mutilation. Obstet Gynecol. 2018;131(4):701–706. doi:10.1097/AOG.0000000000002511
22. World Health Organization. Female genital mutilation — fact sheet. Updated January 2025.
23. World Health Organization. WHO guideline on the prevention of female genital mutilation and clinical management of complications: recommendations and best-practice statements. 2025.
24. Foldès P, Cuzin B, Andro A. Reconstructive surgery after female genital mutilation: a prospective cohort study. Lancet. 2012;380(9837):134–141. doi:10.1016/S0140-6736(12)60400-0
25. Kirtschig G, Woelber L, Günthert A, et al. Evidence- and consensus-based guideline on lichen sclerosus. J Dtsch Dermatol Ges. 2026;24(4):566–584. doi:10.1111/ddg.70000
26. Zhang W, Zeng A, Yang J, et al. Outcome of vulvar reconstruction in patients with advanced and recurrent vulvar malignancies. BMC Cancer. 2015;15:851. doi:10.1186/s12885-015-1792-x
27. Rangatchew F, Knudsen J, Thomsen MV, Drzewiecki KT. Surgical treatment of disabling conditions caused by anogenital lichen sclerosus in women: an account of surgical procedures and results, including patient satisfaction, benefits, and improvements in health-related quality of life. J Plast Reconstr Aesthet Surg. 2017;70(4):501–508. doi:10.1016/j.bjps.2016.12.008
28. Baggish MS. Wide Excision With or Without Skin Graft. In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:915-922.
29. Roh S, Miyamoto S, Kitamura Y, Mito D, Okazaki M. Secondary vulvar reconstruction using bilateral gluteal fold flaps after radical vulvectomy with direct closure. Plast Reconstr Surg Glob Open. 2021;9(4):e3550. doi:10.1097/GOX.0000000000003550
30. Haidopoulos D, Zapardiel I, Planchamp F, et al. "European Society of Gynecological Oncology Consensus Statement on the prevention of surgical complications in gynecologic oncology." Int J Gynecol Cancer. 2026;36(9):104862. doi:10.1016/j.ijgc.2026.104862
31. Wendelspiess S, Kouba L, Stoffel J, et al. "Perforator versus non-perforator flap-based vulvoperineal reconstruction—a systematic review and meta-analysis." Cancers (Basel). 2024;16(12):2213. doi:10.3390/cancers16122213
32. Moccia F, Pentangelo P, Ceccaroni A, Raffone A, Losco L, Alfano C. "Injection Treatments for Vulvovaginal Atrophy of Menopause: A Systematic Review." Aesthetic Plast Surg. 2023;47(6):2788–2799. doi:10.1007/s00266-023-03550-5
33. Russell CB, Welch KC, Saunders NA, Haefner HK, Schmidt PC. "Outcomes After Lysis of Adhesions and Dilator Placement for Treatment of Vulvovaginal Agglutination Due to Lichen Planus." J Low Genit Tract Dis. 2023;27(2):152–155. doi:10.1097/LGT.0000000000000724
34. Oonk MHM, Planchamp F, Baldwin P, et al. "European Society of Gynaecological Oncology Guidelines for the Management of Patients with Vulvar Cancer - Update 2023." Int J Gynecol Cancer. 2023;33(7):1023–1043. doi:10.1136/ijgc-2023-004486