ATOMS — Adjustable Transobturator Male System
The ATOMS (Adjustable Transobturator Male System) (A.M.I., Feldkirch, Austria; first introduced 2008) is an adjustable, non-circumferential compression device for post-prostatectomy stress urinary incontinence. The AdVance depends on urethral repositioning and residual sphincter function. ATOMS provides adjustable ventral compression of the urethra against the urogenital diaphragm; A.M.I.'s current product indication also specifies residual external sphincter function.[31] It has been studied across severity strata and as salvage after failed AdVance.[1][2][3][4][22]
For positioning versus other male slings and the AUS, see Male Urethral Slings — chooser.
Device design and mechanism
- A polypropylene mesh with a central silicone cushion is placed beneath the bulbar urethra by a transobturator approach.
- Mesh arms pass outside-in through the obturator foramina around the inferior pubic rami; the returning arms are secured to central attachment sutures in the manufacturer's illustrated technique. The exact fixation and model-specific steps require the supplied IFU.[5][6][28]
- The cushion is connected by a conduit to a subcutaneous port for percutaneous saline adjustment in the office.
- The mechanism is adjustable ventral compression, which differs from AdVance repositioning.[7][31]
Device generations — port design matters
The ATOMS has evolved through three port designs that differ in operative time and port complications:[8][9]
| Generation | Years | Port | Key issue |
|---|---|---|---|
| IP — Inguinal Port | 2009–2013 | Titanium, inguinal | Most port complications (29 grade IIIb in the generation comparison); across all generations, local titanium intolerance caused 41% of removals[8][9] |
| SP — Scrotal Port | 2013–2015 | Manually-connectable titanium, scrotal | Shorter OR vs IP; titanium intolerance persists[8][9] |
| SSP — Silicone-covered Scrotal Port | 2014–present | Pre-connected, fully silicone-covered, scrotal | Current generation; significantly fewer port complications (IP vs SSP p = 0.019; SP vs SSP p = 0.045) and a better ICIQ-SF than SP; the meta-analysis found a device-generation effect on dryness rate |
The SSP is the contemporary generation represented in newer cohorts.
Surgical technique
- Through a perineal incision, expose the bulbospongiosus and seat the cushion against it beneath the bulbar urethra. In their proximal revision technique, Queissert et al. moved the posterior scrotal neurovascular bundle laterally during obturator passage to avoid nerve compression.[10][31]
- In four revision cases, Queissert et al. (2023) described seating the cushion immediately below the proximal bulbar urethra after transverse division of the perineal central tendon on the bulbospongiosus, a mediodorsal obturator puncture about 1.5 cm below the previous insertion, and paraurethral tunneller exit below the membranous urethra; tight mesh fixation was added in the later cases to seat the cushion partly retrobulbar. Primary implantation with this variation remains to be studied.[10]
- Transobturator arms pass outside-in around the inferior pubic rami and return for fixation to the central device, as depicted in the historical manufacturer brochure. A.M.I. specifies the ATOMS or A.M.I. TOA tunneller for arm passage; follow the applicable model IFU.[28][31]
- A subcutaneous silicone-covered scrotal port (SSP) allows percutaneous saline adjustment with a non-coring port needle; volume can be added for persistent leakage or removed for urinary retention.[31]
- Mean operative time was approximately 47 min (range 29–112) in the European multicenter series.[5]
- Mean postoperative saline adjustments ranged from 2.4 to 4.0 across series.[5][6][11] In Queissert et al.'s four-case revision report, outpatient fills followed assessment for symptomatic voiding dysfunction. At their center, no significant improvement with a total cushion volume above 15 mL prompted retrograde urethrography to assess position; malposition prompted repeat ATOMS, while continued leakage despite further adjustment of an acceptably positioned cushion prompted a recommendation for AUS.[10]
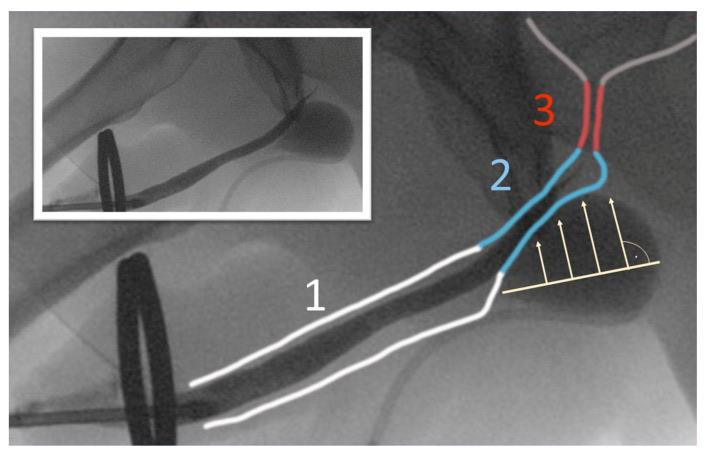
Retrograde urethrogram after a second ATOMS SSP placed with the proximal implantation technique, labeling the penile urethra (1), urethral bulb (2) and rhabdosphincter or sphincteric coaptation zone (3). The cushion now compresses the urethral bulb directly and possibly the rhabdosphincter; the authors suggest a lengthened coaptation zone. This patient became completely dry. From Queissert F, et al. J Clin Med. 2023;12(13):4409, Figure 9 (CC BY).[10]
Outcomes
| Study | N | Follow-up | Study-reported outcome 1 | Study-reported outcome 2 | Note |
|---|---|---|---|---|---|
| Seweryn 2012[6] | 38 | 16.9 mo (mean) | 84.2% overall success | 60.5% dry (0–1 pad and <15 mL/24 h) | First prospective study |
| Hoda 2013[5] | 99 | 17.8 mo (mean) | 92% overall success | 63% dry | European multicenter; 34.3% had prior failed surgery |
| Friedl 2017 (long-term EMC)[9] | 287 | 31 mo (median) | 90% overall success | 64% dry (<10 mL/day and 0–1 pad/day) | Pad use 4 → 1; pad test 400 → 18 mL (both p < 0.001) |
| Angulo 2018 (Iberian, retrospective)[12] | 215 | 24.3 mo (mean) | — | 173/215 (80.5%) dry after adjustment; 157/215 (73%) dry at follow-up | After adjustment: 96.2% mild / 75.3% moderate-to-severe; 85.1% satisfied |
| Doiron 2019[11] | 160 | 9 mo (median) | 80.0% study-defined continence | — | Canadian multicenter; radiation → 62.5% vs 87.9% |
| Esquinas 2019 SR/meta[13] | 1,393 (20 studies) | 20.9 mo (standardized mean) | — | 67% dry (no pad or one safety pad/day); 90% improved | Pad count −4.14/d; 24-h pad test −443 mL |
| Redmond 2021[14] | 289 | 19.6 mo (mean) | 73.3% continence (≤1 pad if baseline ≥2; 0 pads if baseline 1) | — | Multicenter; radiation HR 2.3 and diabetes HR 2.2 were associated with failure to achieve continence |
| Angulo 2020 (Iberian long-term)[15] | Same 215 men as Angulo 2018 | 60.6 mo (mean) | — | 72.1% dry at last FU (46% no pads / 26% security pad) | Among 173 dry after adjustment: the authors' Kaplan–Meier freedom-from-recurrent-SUI estimates were 96/93.6/91.1/89.2% at 1/2/3/5 yr; they also reported 86.7% at 8 yr, although their stated maximum observed follow-up was 91 mo. 25/215 (11.6%) explanted |
| Giammò 2023 (Italian long-term)[16] | 99 | 62.9 mo (median) | 74.7% continent by study definition (29 dry; 45 socially continent) | 29.3% pad-free | Kaplan–Meier freedom from complete device removal estimated at 97/93/91/90/87.9% at 12/24/36/48/60 mo; 20/99 underwent surgery (7 port revisions, 2 port removals retaining the cushion, and 11 complete device removals) |
| Bajaj 2024[1] | 140 | 11 mo (median) | 82.9% reported fewer pads | 76.4% (no pad or one safety pad/day; self-reported) | 90-day complications 14.3% |
| Téllez 2024[17] | 40 | 32.5 mo (median) | 80% dry (pad test ≤20 mL) | 45% total continence (zero leakage) | Retrospective series after TURP or HoLEP rather than radical prostatectomy |
In Angulo 2018, dry meant no pad or one safety pad/day, or a negative 24-hour pad test with occasional loss <10 mL/day.[12]
Comparative evidence
vs ProACT — Angulo 2019 PLoS meta
In an indirect comparison of separate observational cohorts, pooled estimates favored ATOMS for several outcomes. Unequal follow-up and heterogeneity limit interpretation; overall complications did not differ significantly (17% versus 26%, p = 0.07). Reported estimates included: dry 68% versus 55% (p = 0.01); satisfaction 87% versus 56% (p = 0.002); explant 5% versus 24% (p < 0.001); working device at 1 / 2 / 3 yr 92 / 85 / 81% versus 76 / 61 / 58%.[18]
vs REMEEX — Angulo 2021 SR/meta (n = 1,919)
This indirect synthesis of 29 observational studies, without a direct comparison, favored ATOMS for dryness, improvement and explantation. The complication difference was not statistically significant:[19]
| Outcome | ATOMS | REMEEX | p |
|---|---|---|---|
| Dryness | 69.3% | 53.4% | 0.008 |
| Improvement | 90.8% | 80.2% | 0.007 |
| Complication | 18.9% | 35.8% | 0.096 (NS) |
| Explantation | 5.5% | 13.9% | 0.027 |
Differences persist when restricted to current-generation devices (ATOMS SSP versus Remeex System II).
vs AUS
- Geretto 2023 propensity-matched (n = 49 each, mean follow-up 43 months). Dryness was 44.9% with the AUS versus 22.5% with ATOMS (p = 0.03). Self-reported improvement was similar (81% with ATOMS versus 71% with the AUS, p = 0.78). The AUS was associated with more high-grade complications, reinterventions and explantations; freedom from explantation at 60 months was 82% with ATOMS versus 67% with the AUS (p = 0.03), while reintervention-free survival was 67% versus 53% (p = 0.11).[20]
- Esquinas 2021 (102 ATOMS / 27 AUS; mean follow-up 34.9 months). Total dryness (76.5% versus 66.7%, p = 0.33) and social continence were similar, although AUS patients had more severe baseline disease. Surgical revision was more frequent with the AUS (22.2% versus 6.9%, p = 0.029), and time to explant was shorter with the AUS.[21]
Salvage roles
ATOMS after failed AdVance / AdVance XP
Queissert 2022 multicenter (n = 88, 42.5-mo mean): 76.1% social continence / 56.8% pad-free; mean leakage 422 to 38 g/d (p < 0.001).[22] This observational cohort describes ATOMS as a salvage option without a randomized comparison against AUS.[22] For persistent or recurrent SUI after a sling, the AUA/GURS/SUFU 2024 guideline recommends AUS .[30]
After failed initial ATOMS
Angulo 2021 international multicenter (n = 902): 8.65% revision rate at mean 4.1 yr; among 58 reimplants (31 repeat ATOMS / 27 AUS), pad-test, pad-count, satisfaction and PGI-I measures favored repeat ATOMS in this nonrandomized subgroup, and postoperative complications did not differ. The article title reports equivalent outcomes for the two devices.[23]
Predictors of failure
- Prior radiation. Radiation is the most consistent negative predictor. Doiron 2019 found continence in 62.5% of irradiated versus 87.9% of non-irradiated men (p = 0.002) and satisfaction in 69.8% versus 93.2% (p = 0.001).[11] Radiation was associated with explantation in Redmond 2021 (HR 2.7, p = 0.02).[14] A dedicated multicenter series of 223 irradiated men (Angulo 2023; mean follow-up 36 ± 21 months) reported 95/223 (42.6%) dry after adjustment, 26/223 (11.7%) explanted, and 105/125 satisfaction respondents (84%) satisfied.[24] In a later SSP-only matched analysis (171 radiated and 171 nonradiated men; mean follow-up 27.5 months), study-defined dryness was 42.7% versus 67.3%, with more revision and explantation after radiation.[32] In Kidess et al.'s retrospective single-center series of 131 men, the irradiated group had lower immediate postoperative complete continence (21% versus 51%, p = 0.02) and higher explantation (21% versus 6%, p = 0.018). The authors reported comparable longer-term continence and no statistically significant differences by radiotherapy timing (at or before 24 months versus later than 24 months before implantation).[11][14][24][25]
- Diabetes. Diabetes was independently associated with failure to achieve continence (HR 2.2, p = 0.007).[14]
- Higher baseline severity. Higher preoperative pad use was independently associated with failure (HR 1.1 per pad in Redmond 2021), and baseline severity predicted earlier explantation in the long-term Iberian cohort.[14][15]
- Prior urethral or bladder-neck stricture. In Ullate 2022, 21/149 men (14%) had been treated for urethral or bladder-neck stricture at least six months before ATOMS implantation and had stable 16 Ch urethral caliber; after device adjustment, 38% met pad-test continence (≤20 mL/day) versus 83% without prior stricture (p < 0.0001).[26] After propensity matching the difference in dryness was no longer significant (p = 0.236), although previous stricture remained in the multivariable failure model. Redmond 2021 found no association with prior urethral stenosis.[14][26]
- Prior devices, positive preoperative urine culture and baseline severity. In Friedl’s multicenter cohort of 62 men after prostate surgery (median follow-up 17.7 months), multivariable analysis associated prior devices with implant removal, positive urine culture with no improvement or ≥3 pads/24 hours, and SUI severity with no improvement or ≥150 mL/24 hours on pad testing. A poor Charlson comorbidity index was significant in univariable analysis; radiotherapy and urethral stricture were not associated with these outcomes in this cohort.[27]
- Age and obesity were not significant predictors in most studies.[14][27]
Complications
- Major complications (Clavien III+): approximately 3.0% pooled / 4.4% Canadian.[11][13]
- Acute urinary retention: 4/99 men in Giammò's long-term series; all resolved after cushion deflation.[16]
- Explantation: Published cohorts differ in follow-up and case mix: previously cited series report 3.25–20% (11.6% in the long-term Iberian cohort; 20% across port generations in Friedl 2017), while a 2025 retrospective single-center cohort reported 22/80 (27.5%) removals across its full observation period (median follow-up three years) and a Kaplan–Meier five-year implant-survival estimate of 71% (95% CI 56–81).[9][12][15][34]
- Reasons for explantation in long-term Iberian: inefficacy 44%, port erosion 40%, pain and inefficacy 12%, infection 4%.[15]
- Perineal or scrotal pain was common early (68.7% in the European multicenter series, resolving in 3–4 weeks with non-opioid analgesics).[5] Persistent pain can occur.[5][9]
- Erosion is uncommon but documented: port erosion contributed to explants in the long-term Iberian cohort, and a published case describes late bulbar urethral erosion after adjustment in a patient with prior radiation and stricture.[15][29]
- Postoperative urgency/OAB. In a prospective 56-man ATOMS cohort, lower volume at the first involuntary detrusor contraction and higher urethral resistance were independently associated with postoperative OAB.[33]
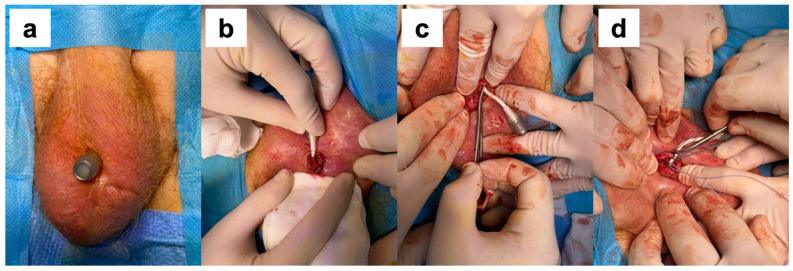
Management of an extruded scrotal port. (a) Port extrusion through the scrotal skin. (b) Exposure of the connection tubing to the port. (c) Clamping of the connection tubing. (d) Placement of nonabsorbable sutures before the tubing is divided and the port removed. From Giammò A, Ammirati E. J Clin Med. 2023;12(6):2296, Figure 1 (CC BY).[16]
Current positioning
The AUA/GURS/SUFU 2024 guideline describes ATOMS as approved in Europe and Canada and under FDA review. It is used in Europe, Canada, Australia and New Zealand.[30]
ATOMS is an adjustable, minimally invasive device that has been used for mild-to-severe post-prostatectomy SUI in primary and salvage settings. The AUA/GURS/SUFU 2024 guideline states that new evidence shows ATOMS is safe and effective in men with mild to severe SUI, and that men with prior radiotherapy or prior urethral stricture surgery had significantly worse continence, complication and satisfaction outcomes. The AUA/GURS/SUFU guideline advises against routinely implanting male slings in severe SUI and recommends an AUS over a sling or adjustable balloon after radiotherapy .[30] The EAU 2026 guideline rates evidence for adjustable slings as limited (level 3) and makes no recommendation for their use because evidence for added benefit from adjustability is absent.[35] Reported advantages:
- Postoperative adjustability. Adjustment is done in clinic through the SSP without reoperation.[6][11]
- Benefit across severity strata. In the retrospective Iberian cohort, dryness after adjustment (no pad or one safety pad/day) was 96.2% for mild and 75.3% for moderate-to-severe baseline SUI.[12] Success is lower in some higher-risk groups.[14]
- Comparative durability estimates versus ProACT and AUS come from separate cohorts or nonrandomized comparisons. Port and urethral erosion remain possible.[18][20][29]
- An observational salvage option after failed fixed sling, alongside AUS and other individualized choices.[22]
Limitations are the absence of randomized trials, reduced efficacy in irradiated patients and in those with prior stricture in several series, the need for multiple office adjustments, and limited US availability.
See Also
- Male Urethral Slings — chooser
- AdVance / AdVance XP
- ProACT Periurethral Balloons
- Argus Sling
- Artificial Urinary Sphincter (AUS)
Videos
References
1. Bajaj M, Frampton C, Losco G, Westenberg A. Adjustable transobturator male system (ATOMS) for stress urinary incontinence: the evidence is mounting. BJU Int. 2024;133(Suppl 3):33–38. doi:10.1111/bju.16118
2. Welk BK, Herschorn S. The male sling for post-prostatectomy urinary incontinence: a review of contemporary sling designs and outcomes. BJU Int. 2012;109(3):328–344. doi:10.1111/j.1464-410X.2010.10502.x
3. Averbeck MA, Woodhouse C, Comiter C, et al. Surgical treatment of post-prostatectomy stress urinary incontinence in adult men: report from the 6th International Consultation on Incontinence. Neurourol Urodyn. 2019;38(1):398–406. doi:10.1002/nau.23845
4. Sahai A, Abrams P, Dmochowski R, Anding R. The role of male slings in post-prostatectomy incontinence: ICI-RS 2015. Neurourol Urodyn. 2017;36(4):927–934. doi:10.1002/nau.23264
5. Hoda MR, Primus G, Fischereder K, et al. Early results of a European multicentre experience with a new self-anchoring adjustable transobturator system for treatment of stress urinary incontinence in men. BJU Int. 2013;111(2):296–303. doi:10.1111/j.1464-410X.2012.11482.x
6. Seweryn J, Bauer W, Ponholzer A, Schramek P. Initial experience and results with a new adjustable transobturator male system for the treatment of stress urinary incontinence. J Urol. 2012;187(3):956–961. doi:10.1016/j.juro.2011.10.138
7. Comiter C. Surgery for postprostatectomy incontinence: which procedure for which patient? Nat Rev Urol. 2015;12(2):91–99. doi:10.1038/nrurol.2014.346
8. Mühlstädt S, Friedl A, Zachoval R, et al. An overview of the ATOMS generations: port types, functionality and risk factors. World J Urol. 2019;37(8):1679–1686. doi:10.1007/s00345-018-2548-4
9. Friedl A, Mühlstädt S, Zachoval R, et al. Long-term outcome of the adjustable transobturator male system (ATOMS): results of a European multicentre study. BJU Int. 2017;119(5):785–792. doi:10.1111/bju.13684
10. Queissert F, Bruecher B, Schrader AJ. A new proximal adjustable sling ATOMS SSP implantation technique with focus on the urethral bulb: lessons learned from revision surgery. J Clin Med. 2023;12(13):4409. doi:10.3390/jcm12134409
11. Doiron RC, Saavedra A, Haines T, et al. Canadian experience with the adjustable transobturator male system for post-prostatectomy incontinence: a multicenter study. J Urol. 2019;202(5):1022–1028. doi:10.1097/JU.0000000000000420
12. Angulo JC, Cruz F, Esquinas C, et al. Treatment of male stress urinary incontinence with the adjustable transobturator male system: outcomes of a multi-center Iberian study. Neurourol Urodyn. 2018;37(4):1458–1466. doi:10.1002/nau.23474
13. Esquinas C, Angulo JC. Effectiveness of adjustable transobturator male system (ATOMS) to treat male stress incontinence: a systematic review and meta-analysis. Adv Ther. 2019;36(2):426–441. doi:10.1007/s12325-018-0852-4
14. Redmond EJ, Nadeau G, Tu LM, et al. Multicentered assessment of clinical outcomes and factors associated with failure of the adjustable transobturator male system (ATOMS). Urology. 2021;148:280–286. doi:10.1016/j.urology.2020.09.045
15. Angulo JC, Virseda-Chamorro M, Arance I, et al. Long-term outcome of adjustable transobturator male system for stress urinary incontinence in the Iberian multicentre study. Neurourol Urodyn. 2020;39(6):1737–1745. doi:10.1002/nau.24410
16. Giammò A, Ammirati E. Long-term survival rate of ATOMS implant for male stress urinary incontinence and management of late complications. J Clin Med. 2023;12(6):2296. doi:10.3390/jcm12062296
17. Téllez C, Diego R, Szczesniewski J, et al. Results of adjustable transobturator male system for stress urinary incontinence after transurethral resection or holmium laser enucleation of the prostate: international multicenter study. J Clin Med. 2024;13(16):4628. doi:10.3390/jcm13164628
18. Angulo JC, Schönburg S, Giammò A, et al. Systematic review and meta-analysis comparing adjustable transobturator male system (ATOMS) and adjustable continence therapy (ProACT) for male stress incontinence. PLoS One. 2019;14(12):e0225762. doi:10.1371/journal.pone.0225762
19. Angulo JC, Ruiz S, Lozano M, et al. Systematic review and meta-analysis comparing adjustable transobturator male system (ATOMS) and male readjustment mechanical external (REMEEX) system for post-prostatectomy incontinence. World J Urol. 2021;39(4):1083–1092. doi:10.1007/s00345-020-03300-1
20. Geretto P, Ammirati E, Falcone M, et al. Comparison study between artificial urinary sphincter and adjustable male sling: a propensity-score-matched analysis. J Clin Med. 2023;12(17):5489. doi:10.3390/jcm12175489
21. Esquinas C, Ruiz S, de Sancha E, et al. Outcomes of a series of patients with post-prostatectomy incontinence treated with an adjustable transobturator male system or artificial urinary sphincter. Adv Ther. 2021;38(1):678–690. doi:10.1007/s12325-020-01563-z
22. Queissert F, Rourke K, Schönburg S, et al. ATOMS (adjustable transobturator male system) is an effective and safe second-line treatment option for recurrent urinary incontinence after implantation of an AdVance/AdVance XP fixed male sling? A multicenter cohort analysis. J Clin Med. 2022;11(1):81 (online 2021). doi:10.3390/jcm11010081
23. Angulo JC, Schönburg S, Giammò A, et al. Artificial urinary sphincter or a second adjustable transobturator male system offer equivalent outcomes in patients whom required revision on the initial ATOMS device: an international multi-institutional experience. Neurourol Urodyn. 2021;40(3):897–909. doi:10.1002/nau.24646
24. Angulo JC, Téllez C, Giammò A, et al. Results of adjustable trans-obturator male system in patients with prostate cancer treated with prostatectomy and radiotherapy: a multicenter study. J Clin Med. 2023;12(14):4721. doi:10.3390/jcm12144721
25. Kidess M, Lederer E, Pyrgidis N, et al. Adjustable transobturator male system (ATOMS) after radiotherapy: is timing everything? A single-center experience. Neurourol Urodyn. 2025. doi:10.1002/nau.70158
26. Ullate A, Arance I, Virseda-Chamorro M, et al. ATOMS (adjustable trans-obturator male system) in patients with post-prostatectomy incontinence and previously treated urethral stricture or bladder neck contracture. J Clin Med. 2022;11(16):4882. doi:10.3390/jcm11164882
27. Friedl A, Mühlstädt S, Rom M, et al. Risk factors for treatment failure with the adjustable transobturator male system incontinence device: who will succeed, who will fail? Results of a multicenter study. Urology. 2016;90:189–194. doi:10.1016/j.urology.2015.12.044
28. A.M.I. ATOMS System Product Brochure. 2016. Historical manufacturer device and fixation diagrams. Consult the current model IFU for operative instructions.
29. Paynter JA, Qin KR, Chee J, et al. Late erosion of an Adjustable Transobturator Male System (ATOMS) device. IJU Case Rep. 2025;8(1):44–46. doi:10.1002/iju5.12804
30. Breyer BN, Kim SK, Kirkby E, et al. Updates to Incontinence After Prostate Treatment: AUA/GURS/SUFU Guideline (2024). J Urol. 2024;212(4):531–538. doi:10.1097/JU.0000000000004088
31. A.M.I. "ATOMS: Adjustable TransObturator Male System." Manufacturer product page. Product indication and specifications (accessed October 2026).
32. Angulo JC, Giammò A, Queissert F, et al. "The effectiveness of adjustable trans-obturator male system (ATOMS) in radiated patients is reduced: A propensity score-matched analysis." BJUI Compass. 2024;5(4):506–514. doi:10.1002/bco2.329
33. Virseda-Chamorro M, Téllez C, Salinas-Casado J, et al. "Factors Influencing Postoperative Overactive Bladder after Adjustable Trans-Obturator Male System Implantation for Male Stress Incontinence following Prostatectomy." J Clin Med. 2023;12(24):7505. doi:10.3390/jcm12247505
34. Jasarevic S, Jankovic D, Hutterer GC, et al. "Intermediate- and Long-term Results After Adjustable Transobturator Male System Implantation." Urology. 2025;196:130–136. doi:10.1016/j.urology.2024.11.054
35. Cornu JN, Elterman D, Hashim H, et al. "EAU Guidelines on the Management of Non-neurogenic Male Lower Urinary Tract Symptoms (LUTS)." EAU Guidelines. EAU Guidelines Office, Arnhem, the Netherlands; 2026:73–74. ISBN 978-94-92671-32-5. Section 5.6.5.b.2