Burch Colposuspension
Burch colposuspension is a suture-based, mesh-free operation for female stress urinary incontinence (SUI). Sutures suspend the supportive vaginal tissues beside the bladder neck and proximal urethra toward Cooper's (iliopectineal) ligament. The aim is urethral support without excessive elevation or obstruction. It differs from the historical Marshall–Marchetti–Krantz (MMK) operation, which uses pubic periosteal fixation.[4]
Burch remains a surgical option in current AUA/SUFU and NICE guidance. It can suit a woman who wants to avoid both a mesh sling and fascial harvest, particularly when an abdominal pelvic operation is already planned.[14][15]
For procedure selection, see the Female Stress Incontinence Database, Female Slings & Suspensions, and Urethral Bulking Agents. Transvaginal needle suspensions, the earlier vaginal alternative to Burch, are described on Needle Suspensions and In Situ Slings (Historical). For the origin of the operation, see the History of Prolapse Surgery & Urogynecology.
Selection and Preoperative Assessment
- Confirm bothersome SUI or stress-predominant mixed incontinence, document stress leakage, and discuss pelvic-floor muscle training, continence devices and the available operations. Burch treats the stress component; urgency can persist or develop after surgery.[14][15]
- Review prior continence and prolapse operations, voiding symptoms, postvoid residual, urinalysis, prolapse and tissue mobility. A fixed or scarred urethra or vagina may make colposuspension less suitable. The 2024 CUA guideline lists inadequate vaginal length or mobility and inability to safely access the retropubic space as contraindications, and advises against Burch for intrinsic sphincter deficiency.[30] For a woman considering bariatric surgery, it recommends delaying SUI surgery .[30]
- Urodynamics is not mandatory for every primary operation. AUA/SUFU permits omission in an otherwise uncomplicated index patient with clearly demonstrated SUI.[14] Additional assessment is appropriate when the diagnosis is uncertain, emptying is impaired, urgency predominates, neurogenic disease is suspected, or prior surgery or prolapse complicates the presentation. NICE specifies preoperative cystometry for urge-predominant or unclear incontinence, voiding symptoms, anterior or apical prolapse or prior SUI surgery.[14][15]
- For a fixed, immobile urethra, AUA/SUFU lists pubovaginal sling, retropubic midurethral sling, bulking or an adjustable retropubic sling as options; its discussion favors an autologous pubovaginal sling for a nonmobile urethra.[14]
- Discuss abdominal access and recovery, recurrent SUI, postoperative emptying problems, urgency and subsequent prolapse. A mesh-free operation still uses sutures and can cause suture-related complications.[4][10][14]
- Obesity is not a contraindication but modestly raises operative burden. In a prospective nested cohort of 250 women undergoing retropubic continence surgery, the 79 women with BMI ≥30 had greater estimated blood loss than nonobese women (344 versus 284 mL, p = 0.03) and a mean operation about 15 minutes longer (p = 0.02), with no detected difference in length of stay or major complications.[21]
Anatomy and Operative Principles
The retropubic space lies behind the pubic symphysis and in front of the bladder. Burch may support a small cystocele, but significant anterior prolapse needs a dedicated repair plan rather than reliance on colposuspension alone.[31] Important structures include the bladder neck and proximal urethra, supportive anterior vaginal tissues, Cooper's ligament, the obturator neurovascular bundle, external iliac vessels and variable corona mortis vessels.[4]
Open Burch
- Obtain retropubic exposure through a suitable lower abdominal incision and identify the bladder neck and proximal urethra. A catheter and vaginal assistance can help define the anatomy.
- Mobilize the bladder sufficiently to expose strong vaginal supporting tissue lateral to the bladder neck and proximal urethra. Avoid blind lateral dissection near the obturator and external iliac vessels and corona mortis.
- Place suspension sutures through the supportive vaginal tissue while avoiding the vaginal epithelium, bladder and urethra. A commonly described technique uses two sutures on each side; published techniques vary in number, material and exact position.
- Secure the sutures to the ipsilateral Cooper's ligament while supporting the vagina. Adjust the suspension without forcing the vaginal wall against the ligament or over-elevating or kinking the outlet. No fixed clamp, distance or tension rule replaces anatomic assessment.
- Perform cystoscopic inspection for bladder injury or intravesical sutures and check ureteral efflux. Address an abnormal finding before completing the procedure.[4]
Laparoscopic or Robotic Approach
Transperitoneal or extraperitoneal access can reproduce the suture suspension; port number and configuration depend on the approach and accompanying operations.[7] Laparoscopy generally permits faster recovery than an open incision, but the comparative evidence is strongest for short-term subjective continence.[4][6] The 2019 Cochrane objective-cure estimate within 18 months pooled laparoscopic suture and mesh-and-staple methods (RR 0.94, 95% CI 0.86–1.02; 1,117 women) and is not specific to mesh-free Burch. The EAU 2026 evidence summary reports higher objective cure after open colposuspension (level 1a), while noting low-quality ESTER network evidence.[6][29]
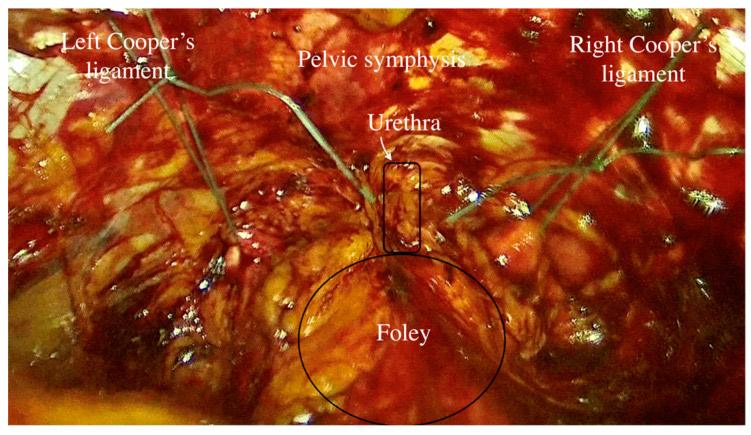
Anatomical landmarks of the space of Retzius during laparoscopic Burch colposuspension: left and right Cooper's ligaments, the pubic symphysis, the urethra and the position of the Foley catheter, with sutures running to each Cooper's ligament. From Brasoveanu S, et al. Life (Basel). 2024;14(3):380, Figure 2 (CC BY 4.0).[26]
The 2019 laparoscopic Cochrane review separates suture colposuspension from older mesh-and-staple colposuspension.[6] The published “TOT-like Burch” report is an educational technique video.[5]
Suture number affects outcome in at least one randomized comparison: in a trial of 161 women undergoing laparoscopic Burch, two single-bite sutures on each side of the urethra gave a significantly higher one-year objective cure among women with one-year pad-test data (148 of 161 randomized) than one double-bite suture on each side (83% versus 58%, p = 0.001), though the single-suture technique was faster (median 60 versus 77 minutes, p < 0.001). This is one trial of one laparoscopic configuration.[20]
What the Comparative Evidence Shows
| Evidence | Result | Interpretation |
|---|---|---|
| SISTEr, multicenter randomized trial: 329 Burch and 326 autologous rectus-fascial sling assignments | At 24 months, Kaplan–Meier overall success estimates were 38% Burch vs 47% sling; stress-specific success was 49% vs 66% | The sling improved continence more, with more morbidity. 520 women had a known 24-month outcome.[3] |
| E-SISTEr, observational extension of the randomized cohort | Five-year Kaplan–Meier continence estimates were 24.1% Burch vs 30.8% sling under the extension's stringent composite definition | 482 women enrolled and 357 completed five-year follow-up; incontinent women were more likely to enroll. Satisfaction remained higher than strict dryness: 126/172 Burch and 148/179 sling respondents were satisfied at five years.[16] |
| 2019 Cochrane: laparoscopic suture vs open colposuspension | Subjective cure within 18 months: RR 1.04, 95% CI 0.99–1.08; 6 trials, 755 women | High-certainty evidence for this short-term endpoint; longer-term comparative evidence and many harm estimates remain uncertain.[6] |
| Karmakar 2021, matched observational cohort | No ongoing SUI reported by 279/336 (83.0%) after open Burch and 857/1,008 (85.0%) after retropubic MUS | Mean follow-up differed: 13.1 vs 10.1 years. This was not a randomized equivalence trial, excluded intrinsic sphincter deficiency, and used different endpoints from SISTEr. Later prolapse surgery was more frequent after Burch.[10] |
| UK/Ireland TVT trial, 5-year follow-up, randomized (344 women: 175 TVT, 169 colposuspension) | A negative one-hour pad test at 5 years was reported by 44/49 (90%) after colposuspension versus 58/72 (81%) after TVT (p = 0.21) | Only 121 of 344 randomized women had 5-year pad-test data. The trial did not detect a significant difference; it also reported more enterocele and rectocele after colposuspension and some late tape complications after TVT.[25] |
| Zilberlicht 2023, secondary analysis of the same matched cohort as Karmakar 2021 | A composite "surgical failure" endpoint (patient-reported outcome plus need for repeat surgery) was 22% after Burch and 20% after MUS (p = 0.35) | Different endpoint from Karmakar's "no ongoing SUI" comparison above; not a separate cohort. Predictors of Burch failure included BMI >25, preoperative anticholinergic use, age >60 and prior incontinence surgery (HR 3.2, 2.8, 2.6 and 2.5); predictors of MUS failure included BMI >30, preoperative anticholinergic use, smoking, diabetes and prior incontinence surgery (HR 3.6, 2.6, 2.5, 1.8 and 2.3).[22] |
SISTEr's overall success required a negative pad test, no leakage in a three-day diary, a negative stress test, no self-reported stress-incontinence symptoms and no retreatment. Stress-specific success omitted the pad-test and diary requirements.[3][16] E-SISTEr used no diary leakage, no self-reported stress symptoms and no surgical retreatment.[3][16]
In Ye's 14-year cohort, 39/57 respondents reported no SUI, but only 57/84 original participants completed follow-up.[11] Conrad's 90.5% result combined cure or substantial improvement, rather than dryness alone.[11][12]
A small 2026 open-label trial reported more 12-month failures after laparoscopic Burch than transobturator tape (34.6% versus 7.7%; 26 women per arm).[13] The 2017 open-colposuspension review and 2019 laparoscopic review also have older search dates; their conclusions must be read alongside current guidelines and later trials.[1][6][13][14][15]
Concomitant Prolapse Surgery
First distinguish symptomatic SUI, occult SUI and no demonstrable SUI. In a stress-continent woman with prolapse, perform a prolapse-reduction test to detect occult SUI .[29] For women with symptomatic or occult SUI undergoing prolapse surgery, discuss combined surgery versus reassessment and staged continence treatment, including the higher adverse-event risk with combined surgery.[14][15][29] In one small trial of women with preoperative SUI, the five-year data could not determine whether adding Burch to abdominal sacrocolpopexy changed postoperative SUI (RR 1.17, 95% CI 0.60–2.26; 45 women; low certainty).[2] For women with neither symptomatic nor occult SUI undergoing abdominal prolapse surgery, the 2026 EAU guideline recommends against concomitant anti-incontinence surgery .[29]
CARE randomized 322 women without preoperative stress-incontinence symptoms who were undergoing abdominal sacrocolpopexy. The journal's 2016 correction changed the three-month composite SUI endpoint to 33.6% with Burch versus 57.4% without Burch after correction of stress-test coding.[17] The endpoint included symptoms, stress testing or treatment. The 23.8%/44.1% rates were superseded by the correction.[8][17][18]
The 2026 Cochrane prolapse/continence review judged the evidence for prophylactic Burch in stress-continent women uncertain: two abdominal-sacrocolpopexy trials gave a two-year SUI RR of 0.72 (95% CI 0.53–0.99), with substantial inconsistency (I² = 75%) and low certainty.[2] Its favorable findings for concomitant midurethral slings in symptomatic or occult SUI concern different populations and procedures.[2] In a separate randomized trial of women with symptomatic or occult SUI undergoing abdominal sacrocolpopexy, two-year stress-specific continence was 40/57 (70%) after retropubic midurethral sling versus 25/56 (45%) after Burch (P = 0.006).[28] These intention-to-treat denominators include women without a two-year assessment; 48/57 sling and 45/56 Burch participants completed that assessment.[28]
A 2025 nonrandomized interim cohort had only 20 women, mixed preoperative continence states and patient-selected treatment. In the 2025 MICRO randomized trial of 50 stress-continent women undergoing minimally invasive sacrocolpopexy, the three-month composite of SUI symptoms, positive stress test or SUI treatment occurred in 13/26 (50.0%) with Burch and 10/24 (41.7%) without Burch (P = 0.555).[27] Use individualized counseling about postoperative SUI risk, additional operative morbidity and staged treatment.[9][14][15]
Complications and Follow-up
- During and soon after surgery: bleeding, bladder injury, intravesical suture, infection, wound problems and impaired emptying. The 2019 Cochrane direct comparisons for bladder perforation and voiding dysfunction were imprecise. The EAU 2026 broader synthesis reports bladder or urethral perforation in 3.7% after laparoscopic versus 0.7% after open colposuspension and rates postoperative voiding dysfunction as more common after laparoscopy (level 1a).[4][6][29]
- Emptying. Arrange a postoperative voiding assessment and a catheterization plan when needed. Persistent obstruction warrants reassessment. In SISTEr, protocol-defined voiding dysfunction was less frequent with Burch than with autologous sling (2% versus 14%).[3][14]
- Urgency and UUI. Pre-existing urgency may persist and new symptoms can occur. SISTEr's excess treated postoperative UUI with sling was mainly persistent disease; new treated UUI occurred in 11 women in each arm (about 3%). Urgency symptoms and urodynamic detrusor overactivity are different outcomes.[3]
- Later prolapse. In Karmakar's cohort, subsequent prolapse surgery occurred in 11/336 (3.3%) after Burch and 11/1,008 (1.1%) after retropubic MUS; 9 of the 11 Burch repairs involved the posterior compartment.[10] An older cohort of 441 women reported anatomical (not necessarily surgically treated) pelvic-support defects after 8.6 years of follow-up (range 3–16 years): 18.9% after Burch without cul-de-sac obliteration versus 11.4% with a concomitant Moschcowitz procedure and about 2% with concomitant uterosacral-ligament approximation.[24] The 18.9% versus 11.4% difference was not statistically significant.[24]
- Later recurrent SUI, pain, dyspareunia or urinary symptoms. Investigate the cause, including emptying dysfunction, recurrent prolapse and suture exposure or bladder erosion when indicated.[4][10][11][14]
- Reoperation at 10 years. A national English cohort of first-time SUI surgery (2006–2013) found the cumulative incidence of any reoperation (further SUI surgery, mesh removal, or prolapse or incisional hernia repair) at 10 years was 21.3% after retropubic colposuspension, versus 10.9% after mesh sling insertion and 12.0% after autologous fascial sling.[19] Concurrent prolapse repair occurred in 17.1% of colposuspension patients, 16.9% of mesh-sling patients and 8.6% of autologous-sling patients.[19] A sensitivity analysis excluding concurrent prolapse repair or hysterectomy found 10-year any-first-reoperation incidences of 19.9%, 9.8% and 11.1%, respectively.[19] A separate US claims-based cohort of 155,458 women, defining reoperation more narrowly as repeat SUI surgery, found the opposite ranking: the 9-year cumulative incidence of repeat SUI surgery was lower after Burch (10.8%) than after sling (13.0%, adjusted HR 1.28 for sling versus Burch, 95% CI 1.19–1.37).[23] The English and US cohorts use different reoperation definitions and health systems, so their estimates should remain separate.[23]
Review continence, urgency, emptying, residual urine, pain, healing and sexual function after surgery. AUA/SUFU recommends early contact for significant problems and an examination within six months; longer-term access to reassessment remains important because recurrence and complications may appear later.[14]
Videos
References
1. Lapitan MCM, Cody JD, Mashayekhi A. Open retropubic colposuspension for urinary incontinence in women. Cochrane Database Syst Rev. 2017;7:CD002912. doi:10.1002/14651858.CD002912.pub7.
2. Baessler K, Christmann-Schmid C, Haya N, et al. Surgery for women with pelvic organ prolapse with or without stress urinary incontinence. Cochrane Database Syst Rev. 2026;2:CD013108. doi:10.1002/14651858.CD013108.pub2.
3. Albo ME, Richter HE, Brubaker L, et al. Burch colposuspension versus fascial sling to reduce urinary stress incontinence. N Engl J Med. 2007;356(21):2143-2155. doi:10.1056/NEJMoa070416.
4. Veit-Rubin N, Dubuisson J, Ford A, et al. Burch colposuspension. Neurourol Urodyn. 2019;38(2):553-562. doi:10.1002/nau.23905.
5. Aleksandrov A, Meshulam M, Rabischong B, Botchorishvili R. Laparoscopic TOT-like Burch colposuspension: back to the future? J Minim Invasive Gynecol. 2021;28(1):24-25. doi:10.1016/j.jmig.2020.04.018.
6. Freites J, Stewart F, Omar MI, Mashayekhi A, Agur WI. Laparoscopic colposuspension for urinary incontinence in women. Cochrane Database Syst Rev. 2019;12:CD002239. doi:10.1002/14651858.CD002239.pub4.
7. Hill AJ, Jallad K, Walters MD. Laparoscopic Burch colposuspension using a 3-trocar system: tips and tricks. J Minim Invasive Gynecol. 2017;24(3):344. doi:10.1016/j.jmig.2016.08.816.
8. Brubaker L, Cundiff GW, Fine P, et al. Abdominal sacrocolpopexy with Burch colposuspension to reduce urinary stress incontinence. N Engl J Med. 2006;354(15):1557-1566. doi:10.1056/NEJMoa054208.
9. Oyama K, Ikeda S, Yuda M. Does concurrent Burch colposuspension reduce postoperative stress urinary incontinence in laparoscopic sacrocolpopexy? An interim analysis. J Minim Invasive Gynecol. 2025;32(9):807-814. doi:10.1016/j.jmig.2025.05.009.
10. Karmakar D, Dwyer PL, Murray C, et al. Long-term effectiveness and safety of open Burch colposuspension vs retropubic midurethral sling for stress urinary incontinence — results from a large comparative study. Am J Obstet Gynecol. 2021;224(6):593.e1-593.e8. doi:10.1016/j.ajog.2020.11.043.
11. Ye Y, Wang Y, Tian W, et al. Burch colposuspension for stress urinary incontinence: a 14-year prospective follow-up. Sci China Life Sci. 2022;65(8):1667-1672. doi:10.1007/s11427-021-2042-9.
12. Conrad DH, Pacquee S, Saar TD, et al. Long-term patient-reported outcomes after laparoscopic Burch colposuspension. Aust N Z J Obstet Gynaecol. 2019;59(6):850-855. doi:10.1111/ajo.13048.
13. Abughanima MF, Elazab AS, Shalaby M, et al. "Laparoscopic Burch Colposuspension Versus Transobturator Tape for the Treatment of Stress Urinary Incontinence in Egyptian Women: A 12-Month Randomized Controlled Trial." Neurourol Urodyn. Published online August 11, 2026. doi:10.1002/nau.70403
14. American Urological Association/Society of Urodynamics, Female Pelvic Medicine & Urogenital Reconstruction. Surgical Treatment of Female Stress Urinary Incontinence. 2017; amended 2023. Official guideline.
15. NICE. Urinary incontinence and pelvic organ prolapse in women: management. NG123. Recommendations, especially 1.3.15–1.3.16, 1.5.1–1.5.3 and 1.9.1–1.9.2.
16. Brubaker L, Richter HE, Norton PA, et al. Five-year continence rates, satisfaction and adverse events of Burch urethropexy and fascial sling surgery for urinary incontinence. J Urol. 2012;187(4):1324-1330. doi:10.1016/j.juro.2011.11.087. Full text.
17. Correction: Abdominal sacrocolpopexy with Burch colposuspension to reduce urinary stress incontinence. N Engl J Med. 2016;374:2297-2298. doi:10.1056/NEJMx160015.
18. Brubaker L, Brown MB, Weber AM. Corrections to report of a trial of Burch colposuspension. N Engl J Med. 2016;374:2295. doi:10.1056/NEJMc1605817. University-hosted journal correspondence.
19. Muller P, Gurol-Urganci I, van der Meulen J, et al. Risk of reoperation 10 years after surgical treatment for stress urinary incontinence: a national population-based cohort study. Am J Obstet Gynecol. 2021;225(6):645.e1-645.e14. doi:10.1016/j.ajog.2021.08.059.
20. Persson J, Wølner-Hanssen P. Laparoscopic Burch colposuspension for stress urinary incontinence: a randomized comparison of one or two sutures on each side of the urethra. Obstet Gynecol. 2000;95(1):151-155. doi:10.1016/s0029-7844(99)00529-3.
21. Rogers RG, Lebküchner U, Kammerer-Doak DN, Thompson PK, Walters MD, Nygaard IE. Obesity and retropubic surgery for stress incontinence: is there really an increased risk of intraoperative complications? Am J Obstet Gynecol. 2006;195(6):1794-1798. doi:10.1016/j.ajog.2006.07.012.
22. Zilberlicht A, Karmakar D, Dwyer PL, Murray C, Kugelman N. Predictors of surgical failure of open Burch colposuspension versus retropubic midurethral sling for stress urinary incontinence. Urology. 2023;177:69-73. doi:10.1016/j.urology.2023.04.019.
23. Jonsson Funk M, Siddiqui NY, Kawasaki A, Wu JM. Long-term outcomes after stress urinary incontinence surgery. Obstet Gynecol. 2012;120(1):83-90. doi:10.1097/AOG.0b013e318258fbde.
24. Langer R, Lipshitz Y, Halperin R, Pansky M, Bukovsky I, Sherman D. Prevention of genital prolapse following Burch colposuspension: comparison between two surgical procedures. Int Urogynecol J Pelvic Floor Dysfunct. 2003;14(1):13-16. doi:10.1007/s00192-002-0999-y.
25. Ward KL, Hilton P; UK and Ireland TVT Trial Group. Tension-free vaginal tape versus colposuspension for primary urodynamic stress incontinence: 5-year follow up. BJOG. 2008;115(2):226-233. doi:10.1111/j.1471-0528.2007.01548.x.
26. Brasoveanu S, Balulescu L, Grigoraș D, Erdelean D, Olaru F, Bardan R, et al. Evaluating patient preferences and clinical outcomes for modified laparoscopic Burch colposuspension and transobturator tape procedures in stress urinary incontinence treatment. Life (Basel). 2024;14(3):380. doi:10.3390/life14030380.
27. Mou T, Gillingham A, Geynisman-Tan J, et al. "Minimally Invasive Burch Colposuspension to Reduce De Novo Stress Incontinence: The MICRO Randomized Trial." South Med J. 2025;118(9):622-627. doi:10.14423/SMJ.0000000000001872
28. Trabuco EC, Linder BJ, Klingele CJ, et al. "Two-Year Results of Burch Compared With Midurethral Sling With Sacrocolpopexy: A Randomized Controlled Trial." Obstet Gynecol. 2018;131(1):31-38. doi:10.1097/AOG.0000000000002415
29. European Association of Urology. EAU Guidelines on Non-neurogenic Female LUTS. EAU Guidelines Office, Arnhem, The Netherlands; 2026. ISBN 978-94-92671-32-5. Disease management chapter, section 4.7.5.
30. Carlson KV, et al. "2024 Canadian Urological Association guideline: Female stress urinary incontinence." Can Urol Assoc J. 2024;18(4):83-102. doi:10.5489/cuaj.8751.
31. Sohlberg EM, Elliott CS. "Burch Colposuspension." Urol Clin North Am. 2019;46(1):53-59. doi:10.1016/j.ucl.2018.08.002.