ProACT — Adjustable Continence Therapy (Periurethral Balloons)
The ProACT (Adjustable Continence Therapy) system uses paired periurethral balloons for male SUI. FDA approval covers adult men with intrinsic-sphincter-deficiency SUI lasting at least 12 months after radical prostatectomy or TURP despite conservative therapy.[13] See the device page for labeling, contraindications and handling. The indication follows the FDA label. The 2014 Cochrane review found a single randomized comparison of AUS with Macroplastique after prostate surgery.[1] A later narrative review describes broader observational ProACT/ACT use beyond the FDA-labeled population.[3]
For positioning versus other minimally invasive male SUI options, see Male Urethral Slings — chooser.
ProACT is a periurethral balloon system, not a sling. It acts by focal compression at the bladder neck. It does not reposition the urethra or compress the bulbar urethra from below.
Device design and mechanism
For post-radical-prostatectomy placement, the IFU targets the bladder neck; after TURP or enucleation, it describes a space at the membranous urethra lateral to the external sphincter and dorsolateral to the prostatic-remnant apex. The balloons provide titrated, noncircumferential focal compression.[13] Each balloon connects via a conduit to a titanium port placed in the scrotum, allowing percutaneous volume adjustment at follow-up visits; Gregori et al. performed adjustments without anesthesia.[2]
Surgical technique
Positioning and Room Setup
The FDA-posted physician IFU specifies oral antibiotics started before anesthesia, then lithotomy positioning with acute hip abduction for perineal access; the perineum and groin are prepped with Betadine, and the fluoroscopy C-arm is positioned and draped into the field before incision.[13]
- The FDA-posted physician IFU specifies general or spinal anesthesia, cystourethroscopy and fluoroscopic placement. For post-prostatectomy implantation, the IFU directs the U-channel sheath with sharp trocar toward the bladder neck, parallel and superolateral to the membranous urethra, using controlled twisting and frequent fluoroscopy. Because fluoroscopy gives a two-dimensional view, it cannot show whether the trocar tip lies anterior or posterior to the bladder neck. Remove the sharp trocar once its tip appears to reach the bladder neck; the blunt trocar can advance the final 0.5–1 cm to reduce bladder or urethral perforation risk. For each balloon, after confirming its position fluoroscopically, withdraw the U-channel sheath approximately 2 cm and check that the balloon has not moved before inflation; recheck its position and inflation under fluoroscopy.[13] The IFU then calls for cystoscopic confirmation of urethral integrity.[13] TRUS-guided placement, which may use local anesthesia, has been reported in observational cohorts. It is a published variant and differs from the FDA-posted implantation sequence. Model-specific training and the supplied IFU apply.[2][3][13]
- After cystourethroscopy, drain the bladder and instill 100–200 mL of Solution D with a bladder syringe for visualization. Retain the cystoscope sheath/obturator during dissection to visualize and palpate the urethra; the IFU does not call for routine postoperative Foley drainage. After closure, the IFU calls for confirming spontaneous voiding; if the patient cannot void, a Foley catheter is placed until the anesthetic effect resolves and voiding is reattempted, and if voiding still fails, balloon volume is reduced in 0.5 mL increments from both balloons until the patient voids. If urethral perforation occurs intraoperatively, the IFU directs withdrawing the sheath, omitting or removing the balloon on that side, and placing a urethral Foley catheter for three days.[13]
- The IFU describes up to 1.5 mL initial fill per balloon with isotonic saline or contrast diluted to isotonicity according to Appendix A; use saline for known contrast allergy and the same inflation medium at later adjustments.[13] Early dryness may reflect procedure-related edema, which, combined with excess balloon pressure, can cause tissue necrosis.[13] Do not adjust therapeutically before six weeks; thereafter, consider adjustments about every four weeks, up to 1 mL per balloon per visit and never more than 8.0 mL in either balloon.[13] Only the specified 23-gauge needle is used for adjustments. If leakage shows no or very little improvement when each balloon reaches 4.5 mL, the IFU calls for an X-ray to confirm position and says revision may be indicated if a balloon is misplaced. For retention, the IFU describes deflating each balloon in 0.5 mL increments until voiding resumes.[13]
- Perforation and retention rates vary by cohort and definition. The FDA IFU warns that misdirected tissue dilation can perforate the rectum.[13] Fernandez et al. describe one MAUDE report of rectal perforation requiring diverting colostomy; MAUDE provides no incidence denominator.[10] The FDA-posted safety table records bladder or urethral perforation in 19/123 (15.4%) and urinary retention in 19/123 (15.4%) of implanted participants through 24 months.[13] A TRUS-guided series reported lower rates: bladder perforation 2/79 (2.5%) and transient retention 1/79 (1.2%).[2][13]
Efficacy
The systematic reviews below synthesize mainly observational cohorts. No randomized comparison is available.
| Study | Design / n | Follow-up | Key outcome |
|---|---|---|---|
| Larson 2019 meta[5] | SR/meta of 19 studies, n = 1,264 overall | Mean 3.6 yr | Pads/day 4.0 → 1.1 (17 studies, n = 1,005); study-defined dryness 60.2% (no pads or <1 pad/day; 13 studies, n = 667); dry or improved 81.9% (improvement = >50% fewer pads/day; 13 studies, n = 781); I-QOL +30.8 (8 studies, n = 448) |
| Tricard 2023 meta[6] | Updated SR/meta, 18 studies, n = 1,570 | Mean ~ 3 yr | Social continence 53% using 0–1 pads/day; this permits a safety pad |
| FDA pivotal / Nash 2019[7][13][17] | Prospective; 124 implantation attempts, 123 implanted; 68 completed four-year follow-up | 18 mo primary; 4 yr completers | Intent-to-treat: 57/124 (46.0%) had at least 50% lower 24-hour pad weight at 18 months; the prespecified study-level performance goal was not met. Among four-year completers, mean pad weight fell 293 → 73 g; one procedure-related serious adverse event |
| Finazzi Agrò 2019 multicenter[8] | National Italian, n = 240 | 24 mo (152 pts to 5 yr) | 29.6% dry (<8 g on a 24-hour pad test) / 37.5% improved (>50% lower pad weight with residual loss >8 g) at 24 mo; 67.1% combined. Similar efficacy in the 152-patient five-year subset. |
| Nestler 2019 long-term[9] | Single-center, n = 134 | Study median 118 mo | 112 implantations reported successful; 63 patients underwent revision, with success in 49/63 (77.8%) |
| Paillusson 2025[18] | Retrospective updated cohort; 196 of 212 implanted men analyzed, 18% previously irradiated | Median 63 mo | Composite success 81/196 (41%) (0–1 pad/day plus patient-improvement score at least 80/100); 125/196 retained balloons and 71/196 had definitive explantation |
Efficacy by severity
In the Gregori TRUS-guided series (62 patients completing adjustment), dry rates were 85% for mild, 63.6% for moderate and 33.3% for severe SUI.[2] The 4-year pivotal study reported pad-weight reductions across all severity levels.[7] AUA 2024 allows offering balloons across mild through severe SUI in non-radiated patients.[14]
Complications and durability
The nine-centre retrospective cohort reported complications in 22.5% of 240 men with at least 24 months of follow-up.[8] The 2023 meta-analysis reported a mean complication rate of 31.2% across 18 heterogeneous studies (n = 1,570; mean follow-up 34.7 months).[6] A 2025 systematic review of 1,607 patients catalogued 752 adverse events. The percentages below use the 752 events as the denominator:[10]
- Mechanical or balloon failure: 30%
- Device migration or malposition: 21%
- Device erosion: 16%
| Metric | Value |
|---|---|
| Explantation rate | 24–26.5%[6][11] |
| Reoperation rate | 22.7–34%[4][6] |
| Working ProACT device at 1 / 2 / 3 yr (2 durability studies) | 76% / 61% / 58%[11] |
Reintervention is a counseling issue. In Angulo 2019, working-device estimates for ATOMS were 92%, 85% and 81% at 1, 2 and 3 years. That was an indirect comparison of separate observational cohorts with differing follow-up.[11]
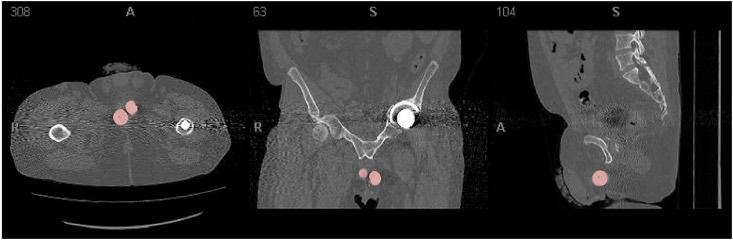
Pelvic CT (axial, coronal and sagittal) after an initial ProACT implantation, with the balloons (red) in a suboptimal position. From Kong L, et al. Urol Case Rep. 2023;49:102424, Fig. 3a (CC BY 4.0).[15]
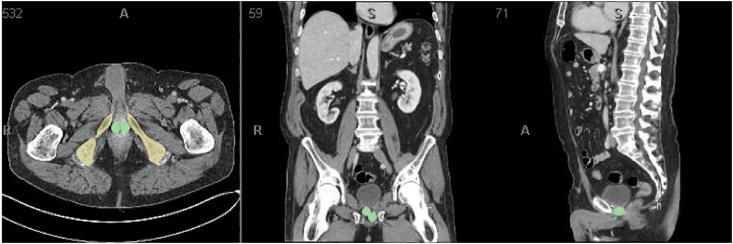
Pelvic CT (axial, coronal and sagittal) in a different patient showing an optimal balloon position (green) adjacent to the pubic bone (yellow). From Kong L, et al. Urol Case Rep. 2023;49:102424, Fig. 3b (CC BY 4.0).[15]
Negative predictive factors
- Prior pelvic radiotherapy was associated with worse outcomes in observational ProACT cohorts: Gregori 2010 reported study-defined continence in 5/14 (35.7%) irradiated versus 36/48 (75%) non-irradiated men completing adjustment at a mean 25 months; Rouprêt 2011 reported 46% success (0–1 pad/day) among 30 irradiated men at mean 56.3 months, with more urethral erosion after radiotherapy (p = 0.005).[2][12] Multiple reviews advise against use in irradiated patients.[2][3][6][12]
- Baseline severity. Severe SUI was associated with a lower success rate in Ricard 2022 (p = 0.033).[2][4][14] Severity-specific results vary between series.[2][4][14]
Salvage role after failed sling
Munier 2020: In this retrospective two-center series after sling failure, 26 men received ProACT and one attempted implant was abandoned after urethral injury. Before ProACT, this cohort averaged 2.3 pads/day, and five men had received adjuvant radiotherapy. At a mean 36 months, 18/27 attempted cases (66.7%) achieved zero pads per day and 26/27 (96.3%) had at least 50% pad-count improvement.[19]
Comparative evidence — ATOMS-vs-ProACT meta
The Angulo 2019 meta-analysis pooled 41 observational studies (3,059 patients), with no direct comparative trial. Pooled estimates favored ATOMS for several outcomes. Unequal follow-up, heterogeneity and selection differences limit causal interpretation. Overall complications did not differ significantly (17% versus 26%, p = 0.07):[11]
| Endpoint | ATOMS | ProACT | p |
|---|---|---|---|
| Dryness | 68% | 55% | 0.01 |
| Improvement | 91% | 80% | 0.007 |
| Satisfaction | 87% | 56% | 0.002 |
| Explantation | 5% | 24% | < 0.001 |
| Working device 3 yr | 81% | 58% | — |
Current positioning
AUA/GURS/SUFU 2024 permits offering adjustable balloons to non-radiated men with mild through severe SUI after prostate treatment .[14] The 2026 EAU guideline advises offering AUS or ProACT only in expert centres and warning about complications, mechanical failure and explantation .[16] Counseling covers AUS and other alternatives, manual dexterity, adjustment visits and revision risk. After primary, adjuvant or salvage radiotherapy, AUA/GURS/SUFU 2024 recommends offering AUS over slings or adjustable balloons .[14] EAU 2026 recommends against ProACT after pelvic radiotherapy .[16] In one series, 29.4% of ProACT patients ultimately required an AUS.[4]
See Also
- Male Urethral Slings — chooser
- ATOMS Sling, indirect observational comparisons and their limitations
- Artificial Urinary Sphincter (AUS), most predictable option across mild to severe SUI per AUA/GURS/SUFU 2024
Videos
References
1. Silva LA, Andriolo RB, Atallah ÁN, da Silva EM. Surgery for stress urinary incontinence due to presumed sphincter deficiency after prostate surgery. Cochrane Database Syst Rev. 2014;(9):CD008306. doi:10.1002/14651858.CD008306.pub3
2. Gregori A, Romanò AL, Scieri F, et al. Transrectal ultrasound-guided implantation of adjustable continence therapy (ProACT): surgical technique and clinical results after a mean follow-up of 2 years. Eur Urol. 2010;57(3):430–436. doi:10.1016/j.eururo.2009.11.031
3. den Hoedt S, Blok BFM. Adjustable continence therapy (ProACT/ACT) with periurethral balloons for treatment of stress urinary incontinence: a narrative review. Transl Androl Urol. 2024;13(8):1744–1761. doi:10.21037/tau-22-807
4. Ricard H, Léon G, Branchereau J, et al. Adjustable continence balloons in postprostatectomy incontinence: outcomes and complications. Neurourol Urodyn. 2022;41(6):1414–1422. doi:10.1002/nau.24967
5. Larson T, Jhaveri H, Yeung LL. Adjustable continence therapy (ProACT) for the treatment of male stress urinary incontinence: a systematic review and meta-analysis. Neurourol Urodyn. 2019;38(8):2051–2059. doi:10.1002/nau.24135
6. Tricard T, Song QX, Munier P, et al. Adjustable continence therapy (proACT) for the treatment of male stress urinary incontinence post-prostatectomy: a systematic review and meta-analysis (2023 update). World J Urol. 2023;41(7):1793–1802. doi:10.1007/s00345-023-04452-6
7. Nash S, Aboseif S, Gilling P, et al. Four-year follow-up on 68 patients with a new post-operatively adjustable long-term implant for post-prostatectomy stress incontinence: ProACT. Neurourol Urodyn. 2019;38(1):248–253. doi:10.1002/nau.23838
8. Finazzi Agrò E, Gregori A, Bianchi D, et al. Efficacy and safety of adjustable balloons (ProACT) to treat male stress urinary incontinence after prostate surgery: medium and long-term follow-up data of a national multicentric retrospective study. Neurourol Urodyn. 2019;38(7):1979–1984. doi:10.1002/nau.24103
9. Nestler S, Thomas C, Neisius A, et al. Long-term results of ProACT primary and repeat implantation for treatment of stress urinary incontinence in men. World J Urol. 2019;37(6):1173–1179. doi:10.1007/s00345-018-2483-4
10. Fernandez AM, Patel HV, Li KD, et al. Adjustable continence therapy for men (ProACT): systematic review and compendium of adverse events. Transl Androl Urol. 2025;14(5):1476–1483. doi:10.21037/tau-24-587
11. Angulo JC, Schönburg S, Giammò A, et al. Systematic review and meta-analysis comparing adjustable transobturator male system (ATOMS) and adjustable continence therapy (ProACT) for male stress incontinence. PLoS One. 2019;14(12):e0225762. doi:10.1371/journal.pone.0225762
12. Rouprêt M, Misraï V, Gosseine PN, et al. Management of stress urinary incontinence following prostate surgery with minimally invasive adjustable continence balloon implants: functional results from a single center prospective study. J Urol. 2011;186(1):198–203. doi:10.1016/j.juro.2011.03.016
13. US Food and Drug Administration. ProACT PMA P130018, approved November 24, 2015. Approval record; physician IFU, Rev A.
14. AUA/GURS/SUFU. Incontinence After Prostate Treatment Guideline, amended 2024, statements 22 and 24. Guideline.
15. Kong L, Coddington ND, Flynn BJ. Secondary placement of adjustable continence therapy (ProACT™) using open perineal technique: case report of ProACT placement in a man with a devastated urethra following pelvic trauma and multiple AUS erosions. Urol Case Rep. 2023;49:102424. doi:10.1016/j.eucr.2023.102424
16. European Association of Urology. EAU Guidelines on the Management of Non-neurogenic Male LUTS. 2026 ed., §5.6.5.c.2. Guideline
17. U.S. Food and Drug Administration. ProACT Adjustable Continence Therapy for Men (P130018): Summary of Safety and Effectiveness Data. 2015. FDA SSED.
18. Paillusson D, De Guerry ML, De Vergie S, Perrouin-Verbe MA. "Flexible cystoscopy-guided implantation of ProACT: Surgical technique and long-term outcomes." BJUI Compass. 2025;6(3):e70005. doi:10.1002/bco2.70005
19. Munier P, Nicolas M, Tricard T, et al. What if artificial urinary sphincter is not possible? Feasibility and effectiveness of ProACT for patients with persistent stress urinary incontinence after radical prostatectomy treated by sling. Neurourol Urodyn. 2020;39(5):1417–1422. doi:10.1002/nau.24355