Transobturator Mid-Urethral Sling
The transobturator mid-urethral sling (TMUS, TOT, TVT-O) treats female stress urinary incontinence by placing a polypropylene tape beneath the midurethra through the obturator foramen rather than the retropubic space.[1][2] Its main appeal is a lower risk of bladder and retropubic vascular injury. Its main tradeoff is groin or thigh pain.[2][3]
For shared MUS counseling and FDA context, see Female Slings & Suspensions.
Indications
TMUS may be considered for patients with uncomplicated SUI and urethral hypermobility who choose a full-length synthetic sling, particularly when retropubic passage should be avoided.[2][4][7]
Guidelines differ. AUA/SUFU 2023 states that clinicians may offer a retropubic, transobturator or single-incision sling to index patients who choose a midurethral sling .[4] NICE NG123 (recommendation 1.5.10) advises against a transobturator approach unless specific circumstances, such as previous pelvic procedures, make the retropubic approach undesirable.[4][7]
| Scenario | Why TMUS fits |
|---|---|
| Hypermobility-predominant SUI | Provides midurethral support with cure rates overlapping RMUS in many trials |
| High concern for bladder perforation | Bladder perforation is substantially lower than with RMUS[2][3] |
| High concern for postoperative retention | Voiding dysfunction is lower than RMUS in comparative data[2][3] |
| Hostile retropubic space | Avoids prior retropubic dissection planes |
In expert practice, relative reasons to avoid TMUS include chronic groin pain, obturator neuralgia, major adductor pain syndromes, severe intrinsic sphincter deficiency and patient preference for the longest retropubic evidence base. AUA/SUFU advises against synthetic MUS during concomitant urethral diverticulectomy, urethrovaginal fistula repair or urethral mesh excision , and advises clinicians to strongly consider avoiding mesh in patients at risk for poor wound healing after radiation therapy or with significant scarring or poor tissue quality .[4]
Routes
| Route | Direction | Practical note |
|---|---|---|
| Outside-in TOT | Groin incision to vaginal incision | Delorme-style route |
| Inside-out TVT-O | Vaginal incision to groin incision | de Leval-style route; efficacy is similar. Cochrane and meta-analysis data show fewer vaginal perforations with inside-out, and Cochrane shows more voiding dysfunction. In the TOMUS route subgroup, which was not designed for this comparison, vaginal perforations were more frequent with inside-out (10 of 13 in the transobturator arm)[2][3][5] |
Both routes place the tape in a flatter, more transverse vector than RMUS. This lowers retropubic risk but places the sling arms near the obturator internus, the adductors and the obturator neurovascular compartment.
Technique
Inside-out TVT-O
- Place the patient in dorsal lithotomy and insert a Foley catheter.
- Make a midurethral vaginal incision.
- Develop lateral paraurethral tunnels toward the inferior pubic ramus and obturator membrane. One described approach to preserving vaginal-wall thickness during passage injects 10 cc of saline at the midurethra (optionally laterally toward the sulcus for a transobturator sling) while tenting the vaginal wall with toothed forceps and identifying the plane with an 18-gauge needle; early blanching suggests injection too superficial, and absence of a visible bleb suggests injection too deep. Direct visualization and palpation of the trocar trajectory and vaginal wall during passage are advised. If a lateral vaginal mucosal perforation is recognized, a deeper access path is created, the trocar is repassed through it, and the mucosa is closed with absorbable suture.[11] If the urethra is injured, do not place a synthetic sling during that procedure .[4] In TOMUS (597 women), a subsequent 2-year adverse-event analysis reported no clinically relevant sequelae detected after intraoperative bladder or vaginal perforations.[3][11][17]
- Make bilateral groin crease exit incisions at the planned trocar exit sites.
- Pass the helical trocar from the vaginal incision through the obturator membrane and obturator foramen to the groin incision.
- Repeat contralaterally.
- Adjust the tape tension-free under the midurethra.
- Perform cystoscopy after sling placement to inspect the bladder and urethra for injury, including after an uncomplicated pass.[4][8]
- Trim the tape at the skin and close vaginal and groin incisions.
Outside-in TOT
The vaginally placed tape can also be delivered from a groin-to-vagina direction (Delorme-style). Two chapter-described sequences illustrate this route.
- One description locates the groin-crease skin incision at the notch along the internal edge of the inferior pubic ramus and the adductor longus tendon, using thumb position while pinching the tendon as a surface guide. The helical trocar enters perpendicular to the skin through the obturator membrane, is rotated medially toward the contralateral index finger placed beneath the ischiopubic ramus, and is advanced until it contacts that finger and exits through the vaginal incision. The vagina is then inspected for inadvertent lateral-fornix penetration (a buttonhole) before cystoscopy.[12]
- A second description maintains trocar contact with the ischiopubic ramus, then turns around the bone into a short, horizontal transobturator course aimed toward the urethral meatus, with a vaginally placed finger behind the pubic bone guiding the tip into the incision and protecting the urethra. This author keeps the vaginal dissection deep, preserves the perineal membrane, and restarts the pass if the unguided segment after the needle leaves the bone exceeds 15 mm. Tape adjustment is described as elasticity-dependent: about 5 mm of space is left between a low-elasticity tape and the urethra, while a high-elasticity tape is allowed to rest against the urethra without compression. These are one author's described technical parameters, not validated universal thresholds.[13]
Technical rules
- Aim lateral and not cephalad. The dissection is not retropubic.
- Keep the tape flat and symmetric before removing sheaths.
- Avoid overcorrection. TMUS remains a tension-free sling.
- Counsel about transient groin or thigh pain before surgery.
- Contact the patient in the early postoperative period about significant voiding difficulty, pain or unexpected events; examine patients who report these findings .[4]
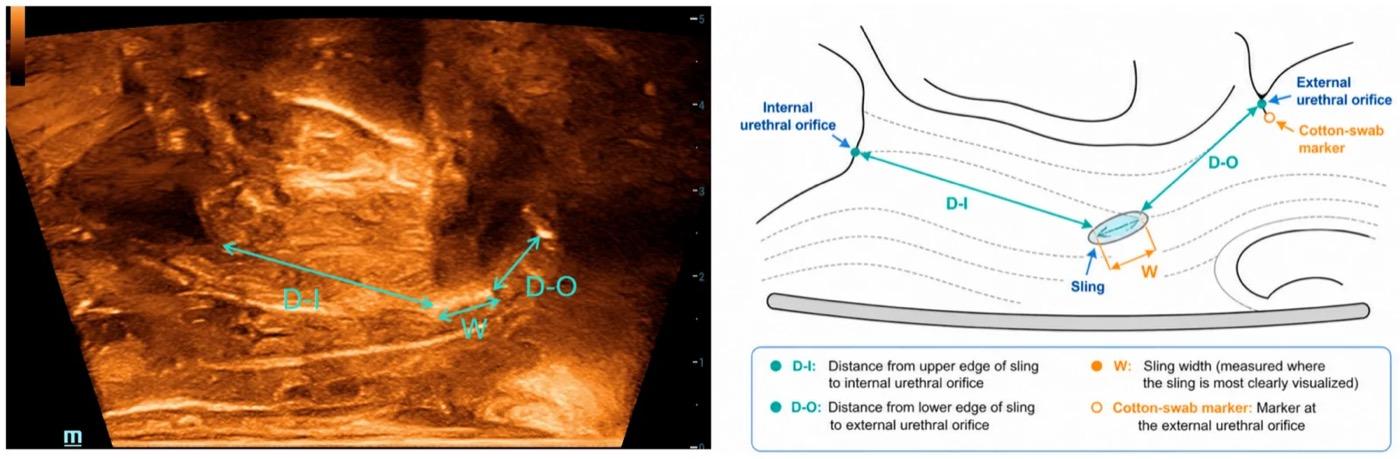
Postoperative transrectal biplane ultrasound after transobturator mid-urethral sling surgery. Left, sagittal B-mode image at rest; right, the corresponding schematic showing the sling, the internal urethral orifice and the external urethral orifice marked with a cotton swab. W is the maximum visible sling width, D-I the distance from the upper edge of the sling to the internal urethral orifice, and D-O the distance from the lower edge of the sling to the marked external orifice. From Li X, et al. Diagnostics. 2026;16(17):2864, Figure 1 (CC BY 4.0).[15]
Outcomes
TMUS has short-term cure rates broadly overlapping RMUS. In TOMUS, the 12-month objective composite met the trial's equivalence criterion (77.7% TMUS versus 80.8% RMUS), while the subjective composite did not meet that prespecified criterion despite no statistically significant difference.[3] Broader comparative syntheses place both full-length MUS routes among effective SUI operations. A network meta-analysis ranked RMUS above TMUS for cure near 12 months (odds ratio for TMUS 0.74, 95% credible interval 0.59 to 0.92).[6] Longer-term comparisons are less certain in the Cochrane review, which reported more repeat incontinence surgery after the transobturator route (RR 8.79, 4 trials, low-quality evidence).[2] EAU guidance strongly recommends informing women that long-term outcomes are superior with the retropubic route.[2][3][5][6][8] In the French VIGI-MESH register (852 transobturator and 1,830 retropubic slings), serious complications at 2 years were 2.9% versus 5.8%, and adjusted reoperation for recurrence was higher after transobturator slings (HR 1.9); that difference disappeared after excluding women with previous SUI surgery.[9] In a separate French national emulated trial of first sling implantation, weighted 5-year sling removal or section was 3.25% after TOT (n = 170,781) versus 4.13% after retropubic TVT (n = 44,360), while second sling implantation for recurrent SUI was more frequent after TOT.[18] A single-center retrospective cohort reported reoperation for recurrent SUI in 8.8% of transobturator and 4.4% of retropubic slings; median follow-up was 9.6 years for transobturator recipients and 11.4 years for retropubic recipients.[10] Among women undergoing concomitant prolapse repair, the covariate-matched association for reoperation after transobturator versus retropubic placement was HR 3.96 (95% CI 1.35–11.58).[10] In a separate multicenter TVT-O cohort, 168 women underwent surgery and 157 were evaluated at 13 years. Sling exposure was reported in four women, all after the 10-year follow-up point.[14] One of the 157 women assessed at 13 years (0.6%) reported persistent mild groin pain (visual analog score 2 of 10) that did not require analgesics.[14] In another prospective TVT-O cohort of 70 women with pure SUI and complete 17-year follow-up, tape exposure occurred in 7/70 (10%).[16] All seven underwent partial sling removal and vaginal re-suturing; one later required urethral bulking for recurrent SUI. These are cohort-specific outcomes.[16]
| Outcome | TMUS counseling point |
|---|---|
| Efficacy | Similar short-term objective outcomes to RMUS in TOMUS; severe ISD/fixed-urethra selection requires separate counseling |
| Bladder perforation | About 0.6% in the Cochrane pooled comparison (versus about 4.5% retropubic); none among the 299 TOMUS transobturator assignments (15 of 298 retropubic)[2][3] |
| Voiding dysfunction | Lower than RMUS in comparative data[2][3] |
| Groin / thigh pain | Higher than RMUS (Cochrane 6.4% versus 1.3%); usually of short duration[2] |
| Mesh exposure | No consistent difference from RMUS[2] |
Operative Pearls
- TMUS suits a problematic retropubic space and suits an obturator compartment problem poorly.
- A patient with fixed urethra or severe ISD may need RMUS, autologous fascial pubovaginal sling, or another outlet strategy instead.
- Persistent focal groin pain after TMUS should trigger evaluation for mesh arm pain, obturator neuralgia, or pelvic floor myalgia.
- Perform intraoperative cystoscopy even though bladder perforation is uncommon with TMUS. EAU strongly recommends cystoscopy during synthetic midurethral sling insertion, and the AUA/SUFU guideline text advises intraoperative cystoscopy with midurethral slings to confirm lower-tract integrity.[4][8]
References
1. Wu JM. "Stress Incontinence in Women." N Engl J Med. 2021;384(25):2428-2436. doi:10.1056/NEJMcp1914037
2. Ford AA, Rogerson L, Cody JD, Aluko P, Ogah JA. "Mid-Urethral Sling Operations for Stress Urinary Incontinence in Women." Cochrane Database Syst Rev. 2017;7:CD006375. doi:10.1002/14651858.CD006375.pub4
3. Richter HE, Albo ME, Zyczynski HM, et al. "Retropubic versus Transobturator Midurethral Slings for Stress Incontinence." N Engl J Med. 2010;362(22):2066-2076. doi:10.1056/NEJMoa0912658
4. Kobashi KC, Vasavada S, Bloschichak A, et al. "Updates to Surgical Treatment of Female Stress Urinary Incontinence (SUI): AUA/SUFU Guideline (2023)." J Urol. 2023;209(6):1091-1098. doi:10.1097/JU.0000000000003435
5. Fusco F, Abdel-Fattah M, Chapple CR, et al. "Updated Systematic Review and Meta-Analysis of the Comparative Data on Colposuspensions, Pubovaginal Slings, and Midurethral Tapes in the Surgical Treatment of Female Stress Urinary Incontinence." Eur Urol. 2017;72(4):567-591. doi:10.1016/j.eururo.2017.04.026
6. Imamura M, Hudson J, Wallace SA, et al. "Surgical Interventions for Women With Stress Urinary Incontinence: Systematic Review and Network Meta-Analysis of Randomised Controlled Trials." BMJ. 2019;365:l1842. doi:10.1136/bmj.l1842
7. NICE. Urinary incontinence and pelvic organ prolapse in women: management. NG123. Published 2019, last updated 24 June 2019. Surgical recommendations.
8. European Association of Urology. Non-neurogenic Female LUTS: Disease Management. Current online guideline, accessed 20 September 2026. Midurethral sling recommendations.
9. Armengaud C, Fauconnier A, Drioueche H, et al. "Serious Complications and Recurrences After Retropubic vs Transobturator Midurethral Sling Procedures for 2682 Patients in the VIGI-MESH Register." Am J Obstet Gynecol. 2024;230(4):428.e1-428.e13. doi:10.1016/j.ajog.2023.11.1241
10. Trad ATA, El Nashar SA, Linder BJ, et al. "Long-Term Outcomes After Retropubic and Transobturator Sling Procedures: Reoperation for Recurrent Stress Urinary Incontinence." BJOG. Published online July 2, 2026. doi:10.1111/1471-0528.70295
11. Gaines N, Gupta P, Sirls LT. Synthetic midurethral slings: exposure and perforation. In: Goldman HB, ed. Complications of Female Incontinence and Pelvic Reconstructive Surgery. 2nd ed. Springer (Humana Press); 2017:177-192. doi:10.1007/978-3-319-49855-3_17
12. Gomelsky A. Transobturator midurethral slings. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:776-783.
13. Delorme E. Transobturator tape for surgical treatment of stress urinary incontinence: outside-in technique. In: Cardozo L, Staskin D, eds. Textbook of Female Urology and Urogynecology. Vol 2: Surgical Perspectives. 5th ed. CRC Press; 2023:807-816. doi:10.1201/9781003144243-81
14. Serati M, Braga A, Caccia G, et al. TVT-O for treatment of pure urodynamic stress urinary incontinence: efficacy and adverse effects at 13-years follow-up. Neurourol Urodyn. 2020;39(5):1423-1429. doi:10.1002/nau.24358
15. Li X, Wei N, Sun R, Liu X, Zou Y, Wei X, et al. Transrectal biplane ultrasound combined with cotton swab marking of the external urethral orifice for evaluating the postoperative position of transobturator mid-urethral sling: a study on standardized ultrasound measurement and inter-observer reliability. Diagnostics. 2026;16(17):2864. doi:10.3390/diagnostics16172864
16. Braga A, Papadia A, Gamarra E, et al. "Long-Term Outcomes of Tension-Free Vaginal Tape Obturator: Efficacy and Safety at Long-Term Follow-Up." J Clin Med. 2024;13(19):5699. doi:10.3390/jcm13195699
17. Brubaker L, Norton PA, Albo ME, et al. "Adverse Events over Two Years after Retropubic or Transobturator Midurethral Sling Surgery: Findings from the Trial of Midurethral Slings (TOMUS) Study." Am J Obstet Gynecol. 2011;205(5):498.e1-498.e6. doi:10.1016/j.ajog.2011.07.011
18. Guillot-Tantay C, Guillo S, Thuy Diep Tran MH, et al. "Long-term safety of mid-urethral sling for stress urinary incontinence in women: an emulated trial using French national health data system." EClinicalMedicine. 2025;87:103411. doi:10.1016/j.eclinm.2025.103411