Colpocleisis (Le Fort and Total)
Colpocleisis treats symptomatic advanced pelvic organ prolapse by reducing the prolapse and closing most of the vaginal canal. It is an option for a patient who accepts permanent loss of penetrative vaginal intercourse, particularly when frailty or other medical conditions increase the burden of reconstructive surgery. Many patients obtain substantial symptom relief, but recurrence, urinary symptoms and complications remain possible.[1][2][3]
For treatment selection, see Prolapse Repair. Concurrent stress-incontinence procedures are covered in the Female Stress Incontinence Database. For the 1877 Le Fort operation, see the History of Prolapse Surgery & Urogynecology.
Choosing an Obliterative Repair
Discuss observation, pessary treatment and reconstructive surgery alongside colpocleisis. NICE recommends considering colpocleisis for uterine or vault prolapse when the patient does not intend penetrative vaginal sex and has a physical condition that increases operative or postoperative risk.[1]
| Decision | Practical discussion |
|---|---|
| Symptoms and goals | Establish which bulge, pressure, emptying or activity limitations the patient wants improved. Anatomic prolapse without bothersome symptoms does not itself require surgery. |
| Vaginal intercourse | Obtain the patient's informed agreement to permanent vaginal closure. Discuss possible future changes in relationships or sexual goals. Nonpenetrative sexual activity and clitoral stimulation remain possible. Partner involvement is optional and depends on the patient's wishes. |
| Medical and functional reserve | Assess frailty, comorbidities, mobility, cognition, anesthetic risk and recovery support. The operation still carries medical and surgical risks. |
| Uterine preservation | Clarify whether the uterus and cervix are present, whether there is concerning bleeding or pathology, and the implications of limiting future vaginal access. |
| Urinary and bowel symptoms | Separate prolapse symptoms from stress leakage, urgency, retention and defecatory complaints. Prolapse repair may improve some symptoms without curing every pelvic-floor problem. |
These discussions should precede technique selection.[1][2][3]
Positioning and Room Setup
Dorsal lithotomy with boot or candy-cane stirrups is standard. Because colpocleisis is chosen disproportionately for older or frail patients, padding, pressure-point protection and minimizing operative time carry added weight even though no colpocleisis-specific positioning study exists; a survey of gynecologic departments found lower-extremity compartment syndrome after lithotomy occurred mostly in operations longer than 4 hours, with no consensus prevention protocol.[14] Some surgeons rehearse high lithotomy positioning at the preoperative visit to confirm an older or mobility-limited patient can achieve it, and document any unilateral limitation in hip mobility as part of planning.[22] No colpocleisis-specific VTE recommendation exists; apply the general risk framework (age, obesity, prior VTE, malignancy, prolonged operation or immobility) on the VTE Prophylaxis page, weighted toward the older, less mobile population colpocleisis typically serves.
Variants and Anatomy
| Variant | Key distinction |
|---|---|
| Le Fort / partial colpocleisis | Anterior and posterior denuded surfaces are approximated to form a central septum, retaining lateral epithelial channels. When the uterus remains, the channels permit drainage from the cervix. Partial techniques can also be used after hysterectomy. |
| Total colpocleisis / colpectomy | More extensive epithelial removal and obliteration are performed for vault prolapse, usually after a previous hysterectomy. Published techniques use layered approximation or serial purse-string reduction. |
| Colpocleisis with concomitant hysterectomy | Hysterectomy and obliterative closure are combined when the individualized plan includes uterine removal. Hysterectomy is an additional decision, not a prerequisite for colpocleisis. |
Terminology and accompanying repairs vary among studies. Preserve enough distal anterior vaginal tissue to avoid compromising the urethra and bladder outlet. Perineorrhaphy or levator plication may accompany the repair, but neither a mandatory levator repair nor a fixed final vaginal depth and width is established for all patients.[2][3][7] Karram routinely adds perineorrhaphy and distal levatorplasty to narrow the genital hiatus during Le Fort colpocleisis and considers this important for limiting recurrence.[18]
Preoperative Assessment
- Examine and document prolapse. Record the compartments, POP-Q findings, genital hiatus, tissue quality, ulceration, prior operations and any concerning vaginal or cervical lesion. Confirm whether a uterus or cervical stump is present.[1][2]
- Consider upper-tract imaging with severe prolapse. In a retrospective cohort of 121 women with fourth-degree uterovaginal or vault prolapse, hydronephrosis was present in 20.6% overall (7.1% with severe vault prolapse, 22.4% with severe uterovaginal prolapse) and renal impairment in 3.3%; of 25 women with hydronephrosis, 64% resolved completely and 20% had a smaller residual degree after treatment.[19] This single older cohort is not colpocleisis-specific, but supports considering preoperative renal ultrasound and postoperative surveillance with severe prolapse.[19][20]
- For a uterus- or cervix-preserving (Le Fort) repair, weigh upper-genital-tract evaluation before closure. Because access for future cervical or endometrial surveillance is reduced afterward, some authors recommend transvaginal ultrasound or endometrial biopsy, together with cervical cytology, before a partial colpocleisis; a woman who needs ongoing upper-genital-tract surveillance may be better served by a different repair.[20]
- Assess bladder function. Document stress and urgency symptoms, voiding difficulty and postvoid residual when indicated.[1][2][3] A prolapse-reduction cough stress test can reveal otherwise masked stress leakage and inform counseling.[1][2][3]
- Use urodynamics for a specific decision. NICE recommends multichannel filling and voiding cystometry before stress-incontinence surgery when anterior or apical prolapse, voiding dysfunction, unclear incontinence type or urge-predominant mixed incontinence, or previous SUI surgery complicates assessment.[1]
- Evaluate bleeding and retained organs. Investigate postmenopausal bleeding, abnormal examination findings and relevant cervical or endometrial risk before closure. Confirm that cervical screening is appropriate for the patient's age and history. Select ultrasound or sampling according to the clinical indication.[2]
- Explain future access. Uterine and cervical evaluation becomes more difficult after closure. Drainage channels do not provide normal examination access or eliminate future cancer risk.[2][6] Persistent or new bleeding and discharge still require evaluation.[2][6] A history of cervical pathology warrants individualized assessment because colpocleisis limits later cervical screening or biopsy; reconstructive repair may better preserve access. In a 2026 global expert Delphi consensus, 93% agreed against uterus- or cervix-preserving obliterative repair for isolated high-risk HPV without another cervical abnormality, and 89% agreed that hysterectomy should be considered for unexplained postmenopausal bleeding despite normal investigations and no other cause.[27] If hysterectomy is added to address cervical or uterine risk, weigh the higher observed in-hospital complication odds in one cohort, longer operating time and greater blood loss in a four-study meta-analysis, and the limits of both estimates against future pathology and surveillance needs.[4][5]
Operative Principles
The following describes the shared sequence. Exact dissection, suture configuration and additional repairs depend on the variant, anatomy and surgeon's training.[2][3][7]
Some surgeons perform intraoperative cystoscopy with every colpocleisis, whether or not a concomitant anti-incontinence procedure is planned, since the anterior compartment can rotate the urethra or ureters forward with severe prolapse.[20] In a retrospective cohort of 700 women undergoing vaginal surgery for anterior or apical prolapse, cystoscopy had 94.4% sensitivity and 99.5% specificity for intraoperative ureteral obstruction; removing the offending suture relieved obstruction in 88% of cases, while six women (0.9%) had true ureteral injuries.[21]
Le Fort / partial colpocleisis
- Plan the epithelial excision. Identify the cervix or vault, urethral region and the anterior and posterior areas to be approximated. Preserve the lateral epithelial strips needed for channels and the distal anterior tissue protecting the bladder outlet.[18] As one chapter author's operative variant, Karram marks the anterior denuded rectangle from about 2 cm proximal to the cervical tip to roughly 5 cm below the external urethral meatus, with a matching posterior area.[18] Santos and Davila instead mark the distal edge of each rectangle at the hymeneal remnants and set the proximal extent by the degree and symmetry of the prolapse, leaving enough anterior epithelium to cover a retained cervix without tension; they note the rectangles should be asymmetric when the prolapse itself is asymmetric.[22]
- Develop the dissection carefully. Remove the planned epithelium while preserving supportive tissue and protecting the underlying bladder and rectum. Maintain visualization and hemostasis; hydrodissection is an adjunct, with agent and dose selected for the patient and local protocol.
- Reduce the proximal prolapse. Approximate the proximal margins, reducing the cervix or vault, and construct the lateral channels. Confirm that drainage channels have not been closed by the sutures.
- Approximate the supporting surfaces. Use successive layers of sutures to bring the denuded anterior and posterior tissues together, reduce the prolapse and close potential spaces without distorting the outlet. Santos and Davila describe closing the proximal half of each rectangle first, anterior to posterior, then completing the distal half, taking care with the deep submucosal potential spaces to limit hematoma and wound separation; they target an introitus of about 1 cm, though no comparative outcome data support that specific dimension.[22]
- Complete the distal closure and any planned perineal repair. Reassess hemostasis, channel patency and the relationship of the closure to the urethra. Tailor narrowing to the anatomy; no fixed final dimension is established.
Lateral channels are a core feature of a uterine-preserving Le Fort repair. One modified technique case describes a channel “wide enough for one finger.”[2][3][7]
Total colpocleisis
After identifying the vault and protecting the bladder, urethral region and rectum, remove the planned vaginal epithelium proximal to the preserved distal anterior segment. Reduce the vault and approximate the supporting tissue with layered sutures or serial purse strings, achieving hemostasis and avoiding residual spaces. Close the remaining epithelium and perform any individually planned perineal repair.[2][3] Total and partial repairs differ in extent.[2][3]
In a video report of total colpocleisis for post-hysterectomy prolapse, hydrodissection with lidocaine and epinephrine was followed by quadrant-based circumferential removal of the vaginal epithelium, serial purse-string sutures to reduce the vault with meticulous hemostasis, transverse epithelial closure and perineorrhaphy.[12]
Technique reports
These are descriptions from technical video abstracts and small series.
- Dissection and retraction. A video review of all colpocleisis types demonstrated electrosurgical marking of the epithelium to be removed, push-spread dissection, retraction with Allis clamps and rubber bands on hemostat clamps, and approximation of the anterior and posterior vaginal muscularis to close the existing space. The authors caution against dissecting past the urethrovesical junction, which can angulate the urethra, and describe levator myorrhaphy and perineorrhaphy as typical reinforcement.[8]
- Lateral channels in Le Fort repair. The same review describes creating the lateral tunnels with or without a urinary catheter in place.[8] In one 88-year-old patient, a blue vessel loop was laid across the cervix and through each lateral channel while the channels were sutured with figure-of-eight stitches, taking care to suture around and not through the loop. The loop was pulled out after the distal epithelium was closed, confirming patency.[9]
- Le Fort tips. A 79-year-old patient's video listed exclusion of underlying malignancy, lidocaine with epinephrine hydrodissection, adequate lateral channels, multilayer closure with hemostasis and an aggressive posterior repair. A retropubic synthetic midurethral sling was placed for occult stress incontinence in that case.[13]
- Rouhier colpocleisis. Vaginal hysterectomy is followed by total-style obliteration. The authors of one case video (a 62-year-old with metastatic endometrial cancer and comorbidities, with palliative intent) describe the operation as time-saving and reproducible when hysterectomy is needed in a patient who does not want vaginal intercourse.[10]
- Standardized purse-string technique. A Bern retrospective quality-control series of 88 women used purse-string sutures for both total and Le Fort colpocleisis and reported POP-Q stage 2 or higher in 14/88 (16%) overall and 3/46 (7%) without prior prolapse surgery; only 51/88 had an examination beyond six weeks, so later recurrence may be underestimated.[11]
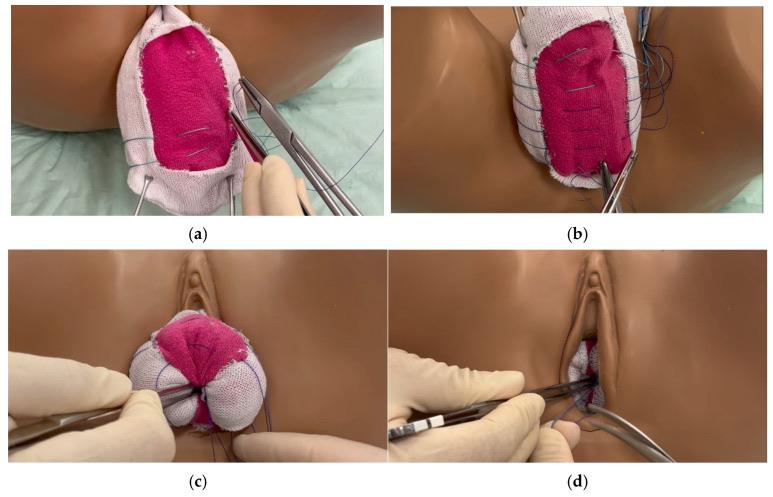
Purse-string colpocleisis, demonstrated on a pelvic model. (a) Purse-string stitches placed on the anterior vaginal wall, running anteriorly to posteriorly. (b) Six stitches set: two 2-0 polyester apically (green), three 2-0 polydioxanone and one distal 2-0 polyglactin. (c) The vagina is inverted with a blunt tip while the first apical suture is tied, followed by the next apical suture. (d) Complete inversion after the last suture is tied. From Hoehn D, et al. J Clin Med. 2025;14(20):7433, Figure 1 (CC BY).[11]
Concomitant Procedures
Hysterectomy
Hysterectomy is not routinely required. Discuss symptoms, suspected pathology, future evaluation, the patient's preferences and the added operative burden. Suspicion of malignancy requires an appropriate diagnostic and oncologic plan before an obliterative operation.[2]
The evidence is observational. A US inpatient study of 7,431 colpocleisis admissions found higher adjusted odds of an in-hospital complication with concomitant hysterectomy (OR 1.93, 95% CI 1.45–2.57).[4] A 2025 meta-analysis abstract, combining four retrospective studies and 1,423 patients, reported longer operations and greater blood loss with hysterectomy, without a statistically significant difference in overall complications. Different populations and definitions limit comparison.[4][5]
Stress-incontinence surgery
For bothersome SUI, discuss concomitant treatment versus a staged procedure after prolapse repair. Include the possibility of persistent or newly apparent stress leakage, urgency, catheterization or voiding difficulty, sling-specific complications and a later operation. NICE recommends considering concurrent SUI surgery in women with SUI and anterior or apical prolapse, with explicit discussion of the uncertainty of longer-term benefit and the risks of combined versus sequential surgery.[1]
A prolapse-reduction test estimates occult-leakage risk.[24] In a 2026 review of vaginal prolapse operations, a concomitant midurethral sling probably reduced postoperative SUI among women with occult SUI (RR 0.38, 95% CI 0.26–0.55; five trials, 369 women); adverse effects remained uncertain.[24] In patients without incontinence who are having prolapse surgery, NICE says not to offer surgery solely to prevent incontinence.[1] For women undergoing colpocleisis, equivalence between suburethral plication and a contemporary sling is unproven.[3] In a 50-woman randomized trial during reconstructive prolapse surgery for occult SUI, tension-free vaginal tape yielded higher subjective (96% versus 64%) and objective (92% versus 56%) continence than endopelvic fascia plication at median follow-up of 26 versus 24 months; applicability to colpocleisis is indirect.[28]
The colpocleisis-specific literature contains selected cohorts with different sling materials and indications. A multicenter trial of concomitant single-incision versus retropubic slings during vaginal prolapse repair included 19% obliterative repairs.[25] At 12 months, single-incision sling was noninferior for a composite of bothersome SUI, SUI retreatment or treatment for retention (25% versus 20%).[25] In the 2022 review, the often-quoted 14% revision for retention came from an autologous fascial sling series, not a synthetic midurethral-sling series.[2]
In a single-institution retrospective review of 210 Le Fort colpocleisis procedures, 161 women (77%) had a concurrent suburethral sling for overt or occult SUI; sling placement was associated with a 92.5% subjective stress-continent rate. Of the 56 patients presenting with voiding dysfunction, it resolved postoperatively in 91%, with de novo voiding dysfunction in 1.9% and sling revision in 0.6%. This is a single noncomparative cohort with median follow-up of 22 weeks.[23]
Outcomes: Keep the Endpoint and Follow-up Together
| Evidence | What was measured | Interpretation |
|---|---|---|
| Multicenter prospective cohort, 152 women | At 12 months, 75/103 examined women had POP-Q stage ≤1 and 96/103 had stage ≤2. Of 132 respondents, 125 were satisfied or very satisfied with their decision to undergo vaginal closure. | Only 103/152 had the one-year examination. Stage ≤2 is not equivalent to no prolapse beyond the hymen.[3] |
| Review of 49 studies, search through June 2020 | Reported anatomic results depended on definition: 62.5–100% for POP-Q stage ≤1, versus 87.5–100% for no prolapse beyond the hymen. | Heterogeneous, mostly observational series.[2] |
| Danish nationwide cohort, 2,228 women; published abstract | Median follow-up 5.6 years; cumulative repeat-prolapse-surgery incidence 6.5% at two years and 8.2% at ten years. | Reoperation differs from recurrent prolapse on examination; the ten-year incidence does not support a universal lifetime reoperation rate of 0–1.8%.[6] |
| Kaiser Permanente Southern California cohort, 9,681 women across four apical techniques, up to 14.8 years' follow-up | Reoperation for recurrent prolapse was lowest after colpocleisis, 1.4 events per 1,000 patient-years, versus 4.8 for sacrocolpopexy, 9 for uterosacral ligament suspension and 13.9 for sacrospinous ligament fixation. | Retrospective, multi-technique comparison; index procedure was the only significant predictor of reoperation for recurrence on multivariate analysis.[16] |
| California statewide cohort, 2,707 colpocleisis procedures (OSHPD data, 2005–2011) | At least one complication occurred in 11.1% and a serious complication in 2%. Frailty, not age, was the strongest predictor of morbidity. | Thirty-day administrative outcomes; does not capture longer-term function, satisfaction or complications beyond 30 days.[17] |
| US Medicare cohort, 4,089 women aged 65 or older; 809 colpocleisis procedures | Estimated cumulative reoperation risk through seven years after colpocleisis was 2.9% for recurrent prolapse, 5.3% for complications and 7.3% overall. | Retrospective comparison of four apical procedures.[26] |
Sources: prospective cohort,[3] narrative review,[2] Danish cohort abstract,[6] Kaiser Permanente cohort,[16] California statewide cohort,[17] and Medicare cohort.[26]
Urinary and bowel symptom scores generally improve, but persistent symptoms are clinically important. In the prospective cohort, bothersome SUI was reported by 18/130 and bothersome UUI/OAB symptoms by 20/131 at one year. Concomitant treatment varied by clinical selection and type, precluding an estimate of routine sling benefit from this cohort.[3]
Body image may improve: 80/131 respondents in that cohort reported that their body looked better, 49 the same and two worse.[3] Regret is often uncommon in selected cohorts, but estimates depend on the question, responders and follow-up. Discuss loss of vaginal intercourse separately from dissatisfaction caused by recurrence, urinary symptoms or other complications.[2][3]
Complications and Follow-up
Counsel about bleeding, infection, urinary retention, persistent or new urinary symptoms, bladder, ureteral or rectal injury, recurrent prolapse and medical complications including thromboembolism. Risk depends on frailty, concurrent procedures and how long outcomes are observed. UTI rates are especially sensitive to whether infection was culture-confirmed and whether the observation window was an admission, 30 days or a year.[2][3][4]
Document the postoperative voiding assessment and arrange a catheter or removal plan if emptying is inadequate. In a randomized trial including obliterative and apical suspension procedures, the intention-to-treat comparison of day-of-surgery versus postoperative-day-1 voiding trials did not reach statistical significance for time to spontaneous void (15.9 versus 28.4 hours; n = 57; p = 0.081).[15] Adjusted and per-protocol analyses favored the earlier trial.[15] Review wound healing, bleeding or discharge, bladder and bowel symptoms and any recurrent bulge. NICE recommends a postoperative review at six months including vaginal examination and ongoing access to review for recurrent symptoms or suspected complications. New postmenopausal bleeding after uterine-preserving closure still needs evaluation.[1][2][3]
Videos
References
1. NICE. Urinary incontinence and pelvic organ prolapse in women: management (NG123). Recommendations 1.3.15–1.3.16, 1.8 and 1.9. Recommendations.
2. Grzybowska ME, Futyma K, Kusiak A, Wydra DG. Colpocleisis as an obliterative surgery for pelvic organ prolapse: is it still a viable option in the twenty-first century? Narrative review. Int Urogynecol J. 2022;33(1):31-46. doi:10.1007/s00192-021-04907-7.
3. FitzGerald MP, Richter HE, Bradley CS, et al; Pelvic Floor Disorders Network. Pelvic support, pelvic symptoms, and patient satisfaction after colpocleisis. Int Urogynecol J Pelvic Floor Dysfunct. 2008;19(12):1603-1609. doi:10.1007/s00192-008-0696-6.
4. Raina J, Bastrash MP, Suarthana E, Larouche M. Perioperative complication rates of colpocleisis performed with or without concomitant hysterectomy: a large population-based study. Int Urogynecol J. 2023;34(5):1111-1118. doi:10.1007/s00192-023-05457-w.
5. Zacharakis D, Prodromidou A, Kathopoulis N, et al. Colpocleisis with or without hysterectomy: a systematic review and meta-analysis. Eur J Obstet Gynecol Reprod Biol. 2025;313:114583. doi:10.1016/j.ejogrb.2025.114583. Abstract reviewed.
6. Hammerbak-Andersen M, Klarskov N, Husby KR. Colpocleisis: reoperation risk and risk of uterine and vaginal cancer: a nationwide cohort study. Int Urogynecol J. 2023;34(10):2495-2500. doi:10.1007/s00192-023-05566-6. Abstract reviewed.
7. Lv H, Rong F. Modified LeFort partial colpocleisis. Int Urogynecol J. 2021;32(4):1043-1045. doi:10.1007/s00192-020-04545-5. Funding-number correction: doi:10.1007/s00192-021-04707-z.
8. Welch EK, Dengler KL, Wheat JE, et al. Colpocleisis techniques: an open-and-shut case for advanced pelvic organ prolapse. Urology. 2023;176:252. doi:10.1016/j.urology.2023.03.011. Abstract reviewed.
9. Dessie SG, Rosenblatt PL. Use of a vessel loop to ensure tunnel patency during LeFort colpocleisis. Int Urogynecol J. 2015;26(10):1541-1543. doi:10.1007/s00192-015-2694-9. Abstract reviewed.
10. Constantin F, Veit-Rubin N, Ramyead L, Dubuisson J. Rouhier's colpocleisis with concomitant vaginal hysterectomy: an instructive video for female pelvic surgeons. Int Urogynecol J. 2019;30(3):495-497. doi:10.1007/s00192-018-3765-5. Abstract reviewed.
11. Hoehn D, Egli H, Marak MC, et al. Colpocleisis: still a valuable option: a point of technique. J Clin Med. 2025;14(20):7433. doi:10.3390/jcm14207433.
12. Linder BJ, Gebhart JB, Occhino JA. Total colpocleisis: technical considerations. Int Urogynecol J. 2016;27(11):1767-1769. doi:10.1007/s00192-016-3034-4. Abstract reviewed.
13. Raju R, Occhino JA, Linder BJ. LeFort partial colpocleisis: tips and technique. Int Urogynecol J. 2020;31(8):1697-1699. doi:10.1007/s00192-019-04194-3. Abstract reviewed.
14. Bauer EC, Koch N, Erichsen CJ, et al. Survey of compartment syndrome of the lower extremity after gynecological operations. Langenbecks Arch Surg. 2014;399(3):343-8. doi:10.1007/s00423-014-1172-z
15. Carter-Brooks CM, Zyczynski HM, Moalli PA, Brodeur PG, Shepherd JP. Early catheter removal after pelvic floor reconstructive surgery: a randomized trial. Int Urogynecol J. 2018;29(8):1203-1212. doi:10.1007/s00192-018-3641-3
16. Shah NM, Berger AA, Zhuang Z, Tan-Kim J, Menefee SA. Long-term reoperation risk after apical prolapse repair in female pelvic reconstructive surgery. Am J Obstet Gynecol. 2022;227(2):306.e1-306.e16. doi:10.1016/j.ajog.2022.05.046
17. Dallas KB, Anger JT, Rogo-Gupta L, Elliott CS. Predictors of colpocleisis outcomes in an older population based cohort. J Urol. 2021;205(1):191-198. doi:10.1097/JU.0000000000001239
18. Karram MM. Obliterative procedures for the correction of pelvic organ prolapse. In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:705–712.
19. Wee WW, Wong HF, Lee LC, Han HC. Incidence of hydronephrosis in severe uterovaginal or vault prolapse. Singapore Med J. 2013;54(3):160-162. doi:10.11622/smedj.2013048
20. Karaman UR, Gomelsky A. Colpocleisis. In: Goldman HB, ed. Complications of Female Incontinence and Pelvic Reconstructive Surgery. 2nd ed. Springer (Humana Press); 2017:117-125. doi:10.1007/978-3-319-49855-3_11
21. Gustilo-Ashby AM, Jelovsek JE, Barber MD, Yoo EH, Paraiso MF, Walters MD. The incidence of ureteral obstruction and the value of intraoperative cystoscopy during vaginal surgery for pelvic organ prolapse. Am J Obstet Gynecol. 2006;194(5):1478-1485. doi:10.1016/j.ajog.2006.01.064
22. Santos E, Davila GW. Colpocleisis. In: Cardozo L, Staskin D, eds. Textbook of Female Urology and Urogynecology. Vol 2: Surgical Perspectives. 5th ed. CRC Press; 2023:957-964.
23. Smith AL, Karp DR, Lefevre R, Aguilar VC, Davila GW. LeFort colpocleisis and stress incontinence: weighing the risk of voiding dysfunction with sling placement. Int Urogynecol J. 2011;22(11):1357-1362. doi:10.1007/s00192-011-1441-0
24. Baessler K, Christmann-Schmid C, Haya N, et al. "Surgery for women with pelvic organ prolapse with or without stress urinary incontinence." Cochrane Database Syst Rev. 2026;2:CD013108. doi:10.1002/14651858.CD013108.pub2
25. Matthews CA, Rardin CR, Sokol A, et al. "A randomized trial of retropubic vs single-incision sling among patients undergoing vaginal prolapse repair." Am J Obstet Gynecol. 2024;231(2):261.e1-261.e10. doi:10.1016/j.ajog.2024.04.036
26. Berger AA, Bretschneider CE, Gregory WT, Sung VW. "Longitudinal reoperation risk after apical prolapse procedures in women aged 65 years and older." Obstet Gynecol. 2024;143(3):411-418. doi:10.1097/AOG.0000000000005511
27. Sullivan ME, Vendramini A, Cattani L, et al. "Patient Risk Factors for Incidental Pathology After Uterovaginal Surgery for Apical Prolapse: Systematic Review and Global Expert Consensus Statements." Int Urogynecol J. 2026. doi:10.1007/s00192-026-06849-4
28. Meschia M, Pifarotti P, Spennacchio M, Buonaguidi A, Gattei U, Somigliana E. "A randomized comparison of tension-free vaginal tape and endopelvic fascia plication in women with genital prolapse and occult stress urinary incontinence." Am J Obstet Gynecol. 2004;190(3):609-613. doi:10.1016/j.ajog.2003.09.027