Laparoscopic Lateral Suspension (LLS)
Laparoscopic lateral suspension (LLS) is a minimally invasive mesh-based technique for apical and anterior pelvic organ prolapse repair that suspends the vaginal vault or cervix toward the lateral abdominal wall via retroperitoneal tunneling of mesh arms, avoiding presacral dissection. The open lateral-suspension concept dates to Kapandji in 1967; Jean-Bernard Dubuisson adapted it for laparoscopy in 1997 and first reported it in 1998.[1][2][3][4][5][16] LLS is an option particularly studied for anterior-apical prolapse and uterine-preserving surgery.[1][2][3][4][5][16]
For the sacral-fixation alternative, see Sacrocolpopexy. For the Cooper's-ligament alternative, see Pectopexy. For the broader prolapse decision framework, see Prolapse Repair.
Definition and Rationale
LLS routes the lateral arms of a T-shaped mesh through retroperitoneal tunnels toward the lateral abdominal wall, bypassing the sacral promontory. Final arm placement or fixation varies: the original laparoscopic description uses lateral aponeurotic support, while a published robotic variant fixes the arms to abdominal-wall peritoneum with absorbable tacks; not all experts routinely attach the arms to muscle fascia.[2][3][6][16]
| Theoretical advantage | Detail |
|---|---|
| No presacral dissection | Avoids exposure of the sacral promontory and its presacral structures; other operative risks remain |
| Different operative field | Vesicovaginal dissection and lateral retroperitoneal tunnels replace presacral fixation; pelvic dissection and its risks remain |
| Shorter operative time | Reported in several comparisons, but affected by case mix, concomitant hysterectomy and high between-study heterogeneity[7][13] |
| Anterior operative field | May simplify access in selected anatomy |
| Suited to uterine preservation | Mesh fixed to cervical isthmus without requiring hysterectomy[1][2][3] |
Indications and Patient Selection
LLS has been studied for POP-Q stage ≥ 2 anterior and / or apical prolapse.[1][7][8] The 2026 AWMF S3 guideline says laparoscopic or robotic lateral mesh-arm suspension may be considered for apical prolapse, particularly when a laparoscopic operation is planned ; systematic long-term data remain lacking.[19] Situations in which it may be considered include:
- Anterior-apical prolapse. The T-mesh route addresses both compartments; comparative superiority is not established.[1][16]
- Uterine preservation. Mesh can be fixed to the cervical isthmus.[1][3][6] Before hysteropexy, assess unexplained uterine bleeding, uterine pathology, cervical dysplasia, and cervical elongation; the 2026 AWMF S3 guideline advises reconsidering uterine preservation and discussing hysterectomy for these findings, a BRCA1/2 mutation, Lynch syndrome, or tamoxifen use.[19]
- Obese patients. The non-sacral field may be useful, but an obesity-specific outcome advantage is not established.[1][16]
- Difficult promontory access. Selected altered anatomy or adhesions may favor considering a non-sacral route, but prior radiation or complex scarring requires individualized risk assessment.[2][16]
- Post-hysterectomy vault prolapse. Mesh fixed to vaginal cuff.[4]
Posterior prolapse needs separate assessment. LLS primarily targets anterior and apical support; significant posterior defects may need an additional repair.[1][9][12]
Surgical Technique — Illustrative Dubuisson-Style LLS
The details below combine published laparoscopic and robotic descriptions; trocar layout, mesh dimensions, tissue fixation and lateral-arm anchoring vary by approach and product.[2][6][9][16]
Positioning and ports[2][6]
- Dorsal lithotomy, steep Trendelenburg.
- Trocar plans differ. One published robotic case uses an 8-mm umbilical camera, two lateral 8-mm robotic ports about 5 cm above the ASIS and a 10-mm assistant port; a laparoscopic setup may use a suprapubic port and smaller lateral ports. Choose access and arm exits for the patient's anatomy and the actual technique.[2][6]
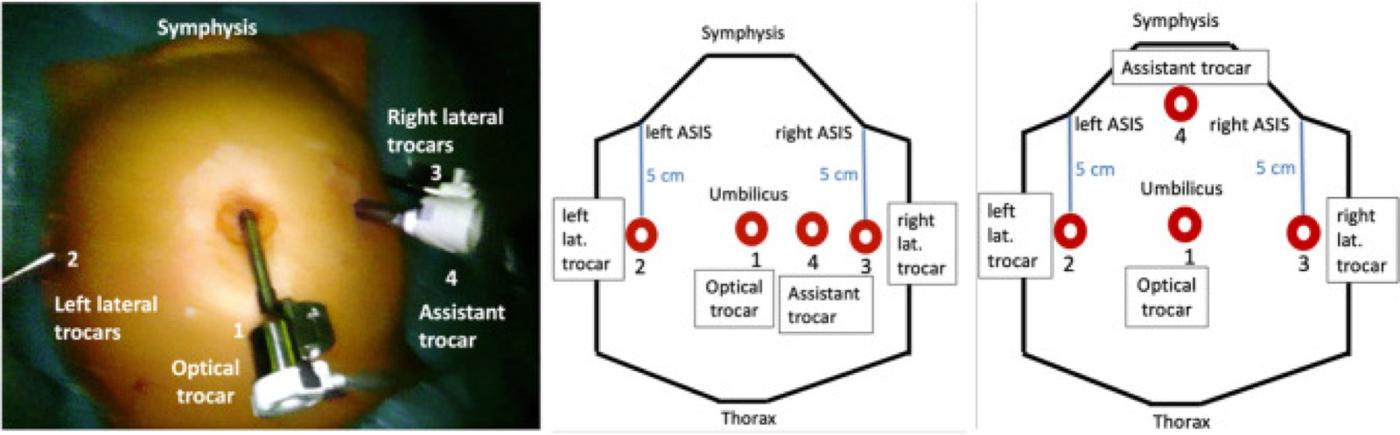
Trocar positions for robot-assisted laparoscopic lateral suspension. Left, intraoperative view. Center, layout for da Vinci S, Si and X systems, with the assistant trocar between the optical trocar and the right lateral trocar. Right, layout for the da Vinci Xi, with the assistant trocar placed suprapubically. 1, optical trocar; 2 and 3, lateral trocars (5 cm from the anterior superior iliac spine, ASIS); 4, assistant trocar. From Lange S, et al. Int Urogynecol J. 2023;34(5):1131-1134, Fig. 1 (CC BY 4.0).
Step-by-step
-
Vesicovaginal dissection. Incise the uterovesical peritoneal fold transversely. In the Lange robotic example, dissection extends to approximately 2 cm above the bladder neck, not 2 cm below it; identify the neck and individual tissue plane before proceeding.[2][6]
- Tip (Di Michele 2026 technical video abstract). A segment of Foley catheter has been described for bladder retraction and for anterior-vaginal-wall measurement for mesh tailoring.[2]
-
Mesh preparation. A T-shaped mesh has a central portion for the anterior vaginal wall and cervical isthmus or cuff, with two lateral arms tunneled retroperitoneally. Mesh dimensions vary by product and patient; Lange's robotic example uses a preformed 9 × 41.5-cm titanized mesh.[6][9]
-
Mesh material. Published variants use macroporous monofilament polypropylene (including titanized products). In one older 480-woman observational cohort, Type 3 mesh (macroporous with multifilamentous or microporous components) was associated with higher erosion odds than Type 1 mesh (adjusted OR 13.0; 95% CI 1.5–110.6).[10] The 13-fold estimate describes cohort-level erosion odds; product IFUs still govern material use.[6][9][10]
-
Central-arm fixation. Suture central arm to the vesicovaginal fascia with absorbable sutures (e.g., Vicryl 2-0). First stitch at the most distal point (near bladder neck); additional sutures proximally. Proximal end fixed to cervical isthmus (uterine-preserving) or vaginal cuff (post-hysterectomy), with non-absorbable sutures at the cervical stroma.[2][6][9]
-
Retroperitoneal tunneling (the defining LLS step). A laparoscopic grasper introduced through each lateral trocar or skin exit is advanced retroperitoneally toward the round ligament. The published robotic example keeps the forceps visible through the peritoneum and warns against external iliac-vessel injury; tunnel direction and exit are variant-specific. Identify and protect the gonadal and external iliac vessels, ureter and other nearby structures during grasper passage and mesh-arm retraction; use the visible anatomy rather than a single memorized boundary.[2][6][16] Lange et al. describe potential ilioinguinal and iliohypogastric nerve injury with the laparoscopic lateral transparietal passage; their robotic lateral-trocar route avoids that passage.[6]
The grasper creates a tunnel from the lateral abdominal wall to the vesicovaginal space; each lateral mesh arm is grasped and pulled retroperitoneally to exit at the lateral trocar site.
-
Tension adjustment and lateral support. In the 2024 Delphi panel's laparoscopic skin-exit technique, remove any vaginal retractor or manipulator, then draw both arms simultaneously to center the apex without excessive traction; inspect vaginally to tailor the lift and trim the arms at skin level.[16] Historical laparoscopic aponeurotic support and the Lange robotic abdominal-wall peritoneal fixation with absorbable tacks are different techniques; neither establishes a universal fascia-suture or tack instruction. A 2024 Delphi expert panel advised avoiding fixation of lateral arms to abdominal muscle fascia because it can cause pain; this is expert consensus, not comparative trial evidence.[16] Confirm the chosen mesh or device instructions and operative anatomy.[2][6][16]
-
Peritonization. Close peritoneum of the uterovesical fold over the mesh with running absorbable suture; round-ligament plication can be incorporated for additional support.[6]
-
Concomitants as needed. Posterior colporrhaphy (vaginally, native tissue) for a symptomatic posterior defect; Burch / midurethral sling for selected SUI; supracervical hysterectomy when indicated. The observed posterior-mesh erosion association in one cohort informs selection.[1][9][10] If the rectum is opened intraoperatively, the 2026 AWMF S3 guideline advises omitting synthetic mesh; after adequate repair of an accidental bladder injury, planned mesh placement may proceed .[19]
Mesh configurations
| Configuration | Use |
|---|---|
| T-shaped mesh (standard Dubuisson) | Standard anterior-apical prolapse[1][2] |
| Anterior-only mesh | Predominant cystocele[1] |
| Anterior + posterior mesh | An option in selected combined defects; posterior mesh placement was associated with higher erosion odds in one older observational cohort, so weigh this against native-tissue posterior repair.[10] |
| Titanized polypropylene | Standard at some centers[4] |
Robot-Assisted LLS
One published da Vinci case or video variant uses an 8-mm umbilical camera, two lateral 8-mm robotic trocars 5 cm above the ASIS and a 10-mm assistant trocar, with a standard laparoscopic forceps through the lateral trocars for retroperitoneal tunneling. The single robotic report fixes lateral arms to abdominal-wall peritoneum with absorbable tacks and describes 3D visualization and suturing ergonomics without comparative testing.[6]
Modifications
LLS combined with uterosacral ligament folding and shortening (LLS-ULFS, Xiong 2025) adds USL plication to LLS and is not LLS alone. In a retrospective cohort of 213 LLS-ULFS and 232 sacrocolpopexy patients, two-year apical anatomical success was 94.84% versus 96.98% (no detected difference); operative times were 85 versus 105 min (p < 0.001). Baseline age and BMI and concomitant procedures differed.[11]
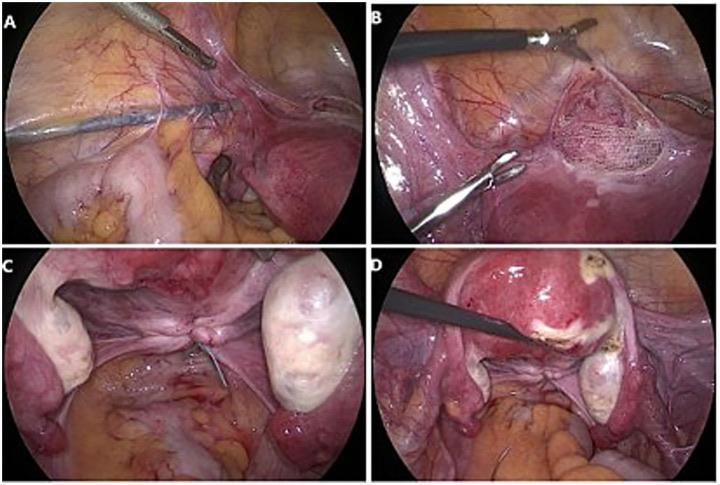
Laparoscopic lateral suspension combined with uterosacral ligament folding and shortening. (A) Extraperitoneal tunnel created at a 40 to 45° angle to the round ligament. (B) The shorter arm of the mesh sutured centrally to the lower uterine segment and anterior vaginal wall. (C, D) Both uterosacral ligaments plicated, shortened and sutured to the cervix with nonabsorbable sutures. From Xiong X, et al. Front Med (Lausanne). 2025;12:1626735, Figure 2 (CC BY).[11]
Outcomes (heterogeneous cohorts and reviews)
The Wang 2025 single-arm meta-analysis included 18 studies and 1,430 laparoscopic LLS patients; its estimated, sample-weighted mean follow-up of 20.27 months came from 1,382 patients in 17 studies.[12] Wang's heterogeneous single-arm studies used varying outcome definitions and follow-up, limiting comparisons with other operations and long-term durability estimates.[12]
| Endpoint | Result |
|---|---|
| Apical anatomical success, Wang pooled | 92.9% (95% CI 89.8–95.1; 1,127 patients in 16 studies; study-defined anatomical success)[12] |
| Anterior anatomical success, Wang pooled | 86.9% (95% CI 81.4–90.9; 1,093 patients in 16 studies); high heterogeneity[12] |
| Subjective success, Wang pooled | 88.9% (95% CI 85.3–91.7; 1,146 patients in 15 studies); the review defined success as no patient-reported bulge, not a uniform PGI-I endpoint[12] |
| Overall POP recurrence, Wang pooled | 9.6% (95% CI 7.0–13.2; 1,026 patients in 10 studies)[12] |
| Reoperation for recurrent POP, Wang pooled | 6.2% (95% CI 4.3–8.9; 69/1,135 patients in 13 studies)[12] |
| Anterior / apical / posterior success, Plotti study medians | 91.15% / 94.95% / 86.55% across 12 prospective or randomized reports (1,261 patients); medians of study rates, not pooled patient-level estimates[1] |
| Operative time, Plotti included studies | Reported range 71.13–254 min across heterogeneous procedures and concomitants[1] |
vs Laparoscopic Sacrocolpopexy
The Lombisani 2025 comparative review included six studies and 632 women with median follow-up about 14 months.[13] Most included studies excluded significant posterior prolapse; one included multicompartment prolapse in the sacrocolpopexy arm. No included patient had previous prolapse surgery, and concomitant hysterectomy was imbalanced between groups. The 2024 randomized study enrolled 93 women, with 89 completing 12 months and concomitant supracervical hysterectomy; another randomized comparison used concurrent total laparoscopic hysterectomy, a distinct operative context.[7][13][15]
| Parameter | LLS | LSC | Significance |
|---|---|---|---|
| Apical correction | No detected difference | — | OR 1.24, p = 0.55; equivalence not shown[13] |
| Anterior correction | No detected difference | — | OR 0.78, p = 0.39; equivalence not shown[13] |
| Subjective success | No detected difference | — | Definitions varied across studies[13] |
| Operative time | Mean 43.1 min shorter | — | Very high heterogeneity (I² = 97%); concomitant hysterectomy was more frequent in the sacrocolpopexy group[13] |
| Blood loss | No robust comparative advantage established | — | Only two studies contributed to this review outcome[13] |
| Complications and mesh events | No detected difference | — | Events were uncommon; no durable safety equivalence established[13] |
| De novo SUI, sexual and bowel function | Procedure-specific differences remain uncertain | — | Short follow-up, varying definitions and limited event counts[7][13] |
| Total vaginal length | May differ by technique | — | — |
Three-way comparison (sacropexy versus pectopexy versus LLS, n = 180): this observational cohort reported shorter operative time for LLS and no detected difference in its reported failure outcome.[5]
The multicenter non-inferiority trial reported preliminary results for 106 operated patients, with 182 planned and available follow-up of 1–12 months. It found no detected differences in the listed clinical scales and shorter operative time for LLS, but did not yet establish non-inferiority or long-term equivalence.[14]
Complications
| Complication | Rate |
|---|---|
| Overall complication rate, Wang pooled | 5.7% (95% CI 3.4–9.4; 75 recorded complications among 1,356 patients in 16 studies)[12] |
| Mesh-related complications, Wang pooled | 1.9% (95% CI 1.0–3.8; 28 recorded mesh-related complications among 1,339 patients in 15 studies)[12] |
| Abdominal or pelvic mesh pain after LLS | At the one-year assessment, abdominal-wall mesh pain was reported by 4/41 (9.8%) women in one cohort (overall postoperative follow-up median 12 months, range 12–37). A separate referral series described five patients undergoing total or subtotal mesh removal for chronic pain, two of whom later needed prolapse reoperation.[17][18] |
| Clavien-Dindo ≥ III, Wang review | 16/848 (1.9%) among studies reporting severity[12] |
| Mesh erosion, Dällenbach cohort | 18/480 (3.8%), mean follow-up 82.3 months[10] |
| Bladder injury / conversion | Reported but infrequent in the cited series; rates depend on case mix and reporting[1][4][7] |
Risk factors for mesh erosion (Dällenbach 2016: cohort n = 480; nested case-control sample 18 cases and 133 controls; mean follow-up 82 mo)[10]
| Factor | Adjusted OR |
|---|---|
| Type 3 mesh (macroporous + multifilamentous / microporous) | 13.0 (95% CI 1.5–110.6) |
| Smoking | 10.4 (95% CI 2.3–46.5) |
| Posterior mesh placement | 5.1 (95% CI 1.2–21.8) |
Counsel smokers about mesh exposure or erosion and cessation. Consider mesh characteristics, product instructions and native-tissue posterior options in shared decision-making.[10]
Advantages and Limitations
| Advantage | Limitation |
|---|---|
| Presacral dissection is avoided, and shorter operative time was observed in the comparative meta-analysis[13] | The time estimate has I² = 97% and imbalanced concomitant hysterectomy.[13] |
| Anterior/lateral access can be useful when promontory access is difficult.[2][16] | The lateral tunnels still require vascular and nerve awareness.[6][16] |
| Allows uterine preservation with cervical fixation in suitable patients[1][6] | Mesh exposure/erosion remains possible.[10][12] |
| Favorable short-term anatomical and subjective outcomes have been reported across cohorts.[1][12] | Follow-up in the Wang pooled analysis averaged about 20 months; comparative long-term durability and advanced-stage subgroups remain uncertain.[12][13] |
| Can be combined with compartment-specific native-tissue repairs when indicated.[1][9] | LLS primarily addresses anterior/apical support; posterior defects require separate assessment and mesh/fixation techniques vary.[1][10][16] |
Key Principles
- LLS suspends the vault or cervix to the lateral abdominal wall via retroperitoneal mesh tunneling, avoiding presacral dissection entirely.[1][2]
- The older observational cohort associated Type 3 mesh with higher erosion odds (adjusted OR 13.0); the 13-fold estimate concerns odds, not absolute risk.[10]
- Plan retroperitoneal tunnels according to the chosen technique and visible anatomy; protect the iliac vessels, ureter and nearby structures.[6][16]
- Adjust the lateral arms to restore apical and anterior support without excessive traction; published fixation approaches vary.[6][16]
- Assess posterior prolapse separately.[10] In one older cohort, posterior mesh placement was associated with higher erosion odds (adjusted OR 5.1; 95% CI 1.2–21.8); native-tissue repair is an option.[10]
- Counsel smokers about the observed association with mesh erosion (adjusted OR 10.4 in the cited cohort) and recommend preoperative smoking cessation.[10]
- Comparative studies found no detected difference in several short-term endpoints and reported shorter operative time.[7][13][14]
- Consider LLS in selected anterior-apical or uterine-preserving cases, or when sacral access is difficult.[1][16]
- Longer-term comparative evidence, especially for advanced stage III–IV prolapse, remains limited; discuss alternatives including sacrocolpopexy in the broader shared decision.[13]
Videos
References
1. Plotti F, Martinelli A, Terranova C, et al. Laparoscopic lateral suspension (LLS) for pelvic organ prolapse (POP): update and systematic review of prospective and randomised trials. J Clin Med. 2025;14(9):3056. doi:10.3390/jcm14093056.
2. Di Michele S, Caiazzo A, D'Alterio MN, Angioni S. Laparoscopic lateral suspension according to Dubuisson: technical video guide with tips and tricks. J Minim Invasive Gynecol. 2026. doi:10.1016/j.jmig.2026.01.044.
3. Yu T, Liu L. The standardized procedure, technical key points and latest progress of laparoscopic lateral suspension surgery. Arch Gynecol Obstet. 2024;310(3):1745-1748. doi:10.1007/s00404-024-07686-w.
4. Campagna G, Vacca L, Panico G, et al. Laparoscopic lateral suspension for pelvic organ prolapse: a systematic literature review. Eur J Obstet Gynecol Reprod Biol. 2021;264:318-329. doi:10.1016/j.ejogrb.2021.07.044.
5. Sánchez-Ferrer ML, Ñíguez-Sevilla I, Ruiz-Cotorruelo VL, Arense-Gonzalo JJ. A cohort-based comparative study of three minimally invasive apical prolapse surgeries: sacropexy, pectopexy, and lateral suspension. J Clin Med. 2025;14(17):6073. doi:10.3390/jcm14176073.
6. Lange S, Chatziioannidou K, Dällenbach P. Robotically assisted laparoscopic lateral suspension: a step-by-step approach aiming to standardize a novel procedure. Int Urogynecol J. 2023;34(5):1131-1134. doi:10.1007/s00192-023-05477-6.
7. Malanowska-Jarema E, Starczewski A, Melnyk M, et al. A randomized clinical trial comparing Dubuisson laparoscopic lateral suspension with laparoscopic sacropexy for pelvic organ prolapse: short-term results. J Clin Med. 2024;13(5):1348. doi:10.3390/jcm13051348.
8. Wang XX, Xu Y, Song YF, Lin CQ, Jiang XX. Laparoscopic lateral suspension with mesh for severe anterior and apical pelvic organ prolapse: an observational cohort study for safety and efficacy at 2-year follow-up. Arch Gynecol Obstet. 2024;310(6):3259-3265. doi:10.1007/s00404-024-07792-9.
9. Chatziioannidou K, Veit-Rubin N, Dällenbach P. Laparoscopic lateral suspension for anterior and apical prolapse: a prospective cohort with standardized technique. Int Urogynecol J. 2022;33(2):319-325. doi:10.1007/s00192-021-04784-0.
10. Dällenbach P, De Oliveira SS, Marras S, Boulvain M. Incidence and risk factors for mesh erosion after laparoscopic repair of pelvic organ prolapse by lateral suspension with mesh. Int Urogynecol J. 2016;27(9):1347-55. doi:10.1007/s00192-016-2974-z.
11. Xiong X, Xia L, Mei T, et al. Laparoscopic lateral suspension combined with uterosacral ligament folding and shortening versus laparoscopic sacrocolpopexy for the treatment of pelvic organ prolapse: a retrospective cohort study. Front Med. 2025;12:1626735. doi:10.3389/fmed.2025.1626735.
12. Wang Q, Manodoro S, Jiang X, Lin C. Efficacy and safety of laparoscopic lateral suspension with mesh for pelvic organ prolapse: a systematic review and meta-analysis. Acta Obstet Gynecol Scand. 2025. doi:10.1111/aogs.15170.
13. Lombisani A, Tius V, Ferraro C, et al. Lateral suspension vs sacral colpopexy for treating pelvic organ prolapse: a systematic review and meta-analysis. Arch Gynecol Obstet. 2025. doi:10.1007/s00404-025-08210-4.
14. Ñíguez-Sevilla I, Sánchez-Ferrer ML, Ruiz-Cotorruelo VL, et al. Preliminary results of a multicenter randomized clinical trial for laparoscopic repair of pelvic organ prolapse: sacropexy vs laparoscopic lateral suspension. J Clin Med. 2025;14(6):2069. doi:10.3390/jcm14062069.
15. Isenlik BS, Aksoy O, Erol O, Mulayim B. Comparison of laparoscopic lateral suspension and laparoscopic sacrocolpopexy with concurrent total laparoscopic hysterectomy for the treatment of pelvic organ prolapse: a randomized controlled clinical trial. Int Urogynecol J. 2023;34(1):231-238. doi:10.1007/s00192-022-05267-6.
16. Simoncini T, Panattoni A, Cadenbach-Blome T, et al. Role of lateral suspension for the treatment of pelvic organ prolapse: a Delphi survey of expert panel. Surg Endosc. 2024;38(8):4344-4352. doi:10.1007/s00464-024-10917-5.
17. Aksin Ş, Andan C. "Postoperative results of laparoscopic lateral suspension operation: A clinical trials study." Front Surg. 2023;10:1069110. doi:10.3389/fsurg.2023.1069110.
18. Frigerio M, Barba M, Cola A, et al. "Pelvic pain after laparoscopic lateral suspension for pelvic organ prolapse: an unrecognized problem?" Int Urogynecol J. 2023;34(4):951-955. doi:10.1007/s00192-022-05374-4.
19. AWMF/DGGG et al. Diagnostik und Therapie des Descensus genitalis der Frau. S3 guideline 015-006, version 6.0, March 2026, recommendation 6.E52. Official full guideline.