Pectopexy
Pectopexy (also called pectocolpopexy or pectocervicopexy) is an apical-prolapse repair that suspends the vaginal vault or cervix to the bilateral iliopectineal (Cooper's) ligaments with mesh or suture, rather than the sacral promontory. Banerjee and Noé's original technique was published online in 2010 and in the 2011 print volume. Its route avoids presacral dissection.[1][2][3][4][24]
For the sacral-fixation alternative, see Sacrocolpopexy. For the uterus-preserving sacral variant, see Sacrohysteropexy. For the broader prolapse decision framework, see Prolapse Repair.
Definition and Rationale
The iliopectineal ligament (Cooper's ligament) is a strong, well-defined anatomic structure familiar to surgeons from hernia repair. Pectopexy uses it as a bilateral fixation anchor for apical suspension.[1][2][3]
- Avoids presacral dissection. Does not expose the promontory and its presacral vessels and nerve plexus in the way sacrocolpopexy does.
- Avoids the rectosigmoid mesentery in a standard anterior approach.
- Anterior pelvic field may simplify access in selected anatomy; one single-surgeon series found a learning-curve turning point at case 12.[1]
- Bilateral fixation gives a different support vector.
- Operative time was shorter in several reported comparisons; interpretation depends on case mix and concomitant surgery.[1][8]
Indications and Patient Selection
Pectopexy has been studied in women with POP-Q stage ≥ 2 apical prolapse (uterovaginal or post-hysterectomy vault prolapse).[2][5] In the UK, NICE HTG464 recommends laparoscopic mesh pectopexy only in research because the safety and efficacy evidence is insufficient in quality and quantity; it says the procedure should be done only by surgeons experienced and trained in laparoscopic urogynecologic surgery.[25] Situations in which its non-sacral route may be considered include:
- Patients where presacral dissection is high risk: prior pelvic radiation, sacral anomalies, severe adhesions, deep pelvis.[3]
- Obese patients. An anterior route has been described.[4][6]
- Patients who desire uterine preservation (pectouteropexy / pectohysteropexy).[4][7]
Surgical Technique — Illustrative Laparoscopic Pectopexy
The descriptions below retain historical and published variants. Port sites, mesh shape, fixation and concomitant repairs vary by technique; Chuang's cohort used a 3 × 23 cm DynaMesh-PRS strip, V-Loc at the cervix or vault and either Ethibond sutures or absorbable AbsorbaTack at the pectineal ligaments.[1] Product-specific instructions and the chosen operative anatomy govern use.
Positioning and ports[9]
- Dorsal lithotomy with hip extension and knee flexion; 45° Trendelenburg.
- One 10-mm umbilical optical trocar and three 5-mm accessory trocars (two placed 2 cm above and medial to the ASIS bilaterally; one 5 cm below the umbilicus).
Step-by-step
- Bilateral identification and exposure of the iliopectineal ligaments. Begin on one side (typically left). Incise peritoneum in the center of a V-shaped area bordered laterally by the round ligament and medially by the obliterated umbilical artery (medial umbilical ligament). Dissect soft tissue to expose the iliopectineal ligament medial to the external iliac vessels in the Chuang description. Repeat contralaterally.[1][9][2]
- Structures to preserve: nearby external iliac vessels, a pubic anastomotic vessel (corona mortis) if present, and obturator neurovascular structures; confirm their relationship in the individual field. In seven cadavers, mean distance from the pectineal-ligament midpoint to the external iliac vein was 1.04 cm left and 1.25 cm right; these observations are not safe fixation margins.[27]
- Vaginal / cervical dissection. If hysterectomy planned, perform supracervical hysterectomy at this point. Dissect the vesicovaginal space anteriorly to expose the anterior vaginal wall / cervical stump. A vaginal retractor or assistant's finger tents the vaginal wall for identification.[9][4]
- Mesh fixation to vaginal wall or cervix. Suture the central portion of the mesh to the anterior vaginal wall and / or cervical stump. In one reported strip technique, V-Loc was used at the cervix or vault; another inverted-T variant extends anteriorly along the vesicovaginal septum for concurrent cystocele.[1][9][10]
- Bilateral mesh fixation to the iliopectineal ligaments. Bring the lateral arms to Cooper's ligaments bilaterally; the Chuang series used two interrupted Ethibond sutures or 2–3 absorbable AbsorbaTack tacks per side. Other described materials and devices require their own source and instructions. Elevate the vaginal apex without excessive traction.[1][9][12]
- Peritonization. The illustrated variant closes peritoneum over the mesh bilaterally with running absorbable suture (e.g., Vicryl 2-0), separating intraperitoneal bowel from the implant.[9]
- Concomitant procedures (as needed).
- Completion cystoscopy. Chuang's illustrative technique checked bladder integrity and bilateral ureteral urine jets at the end of surgery.[1]
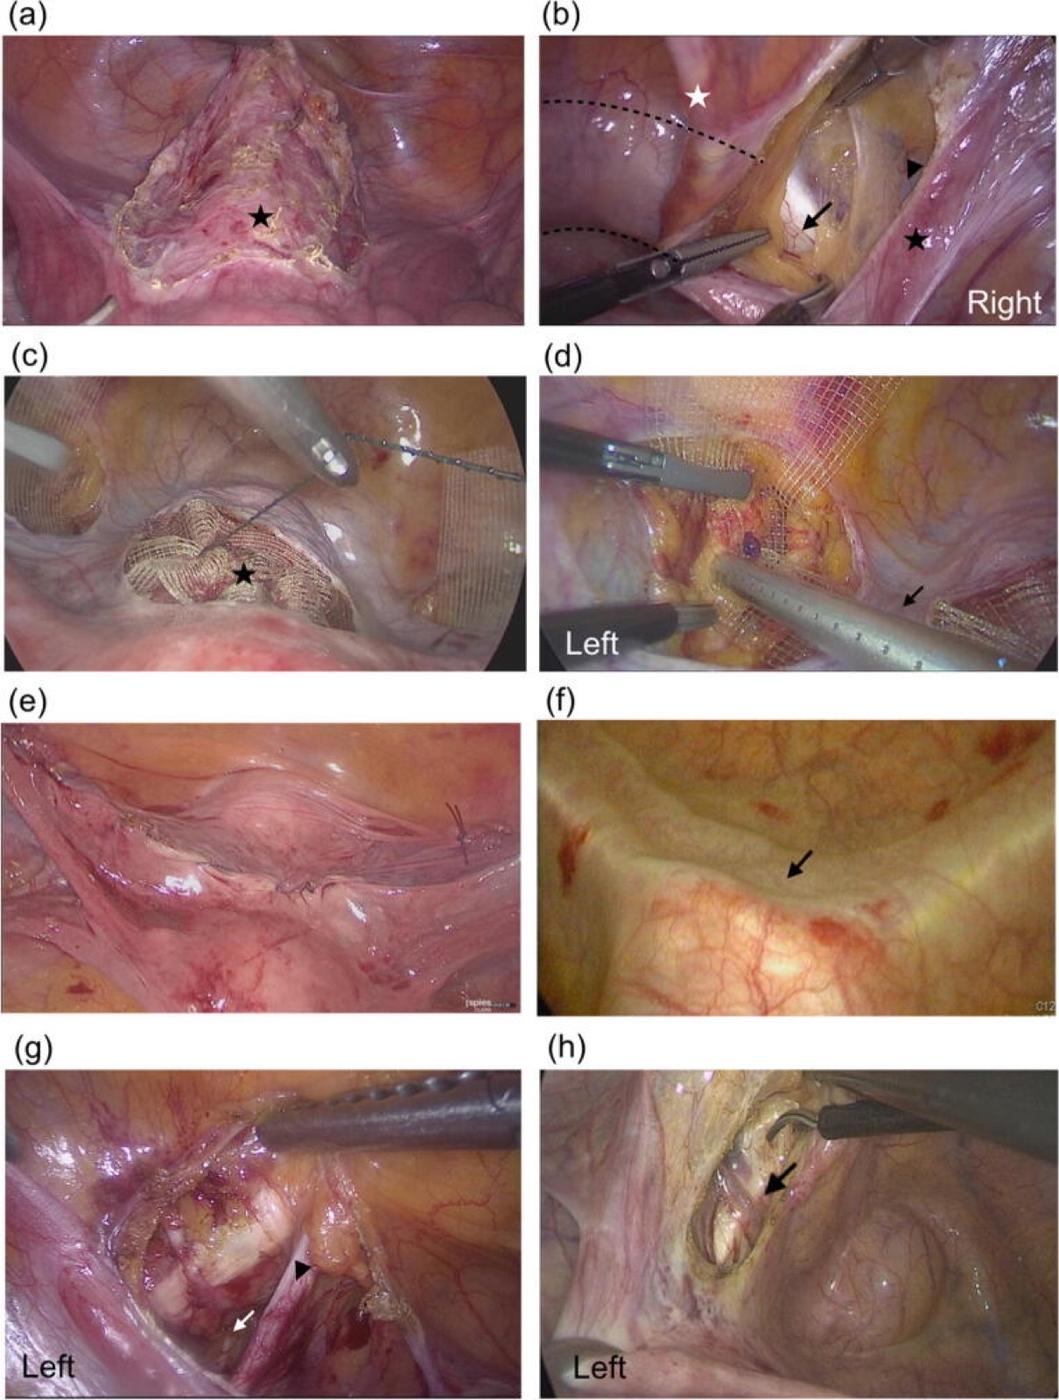
Steps of laparoscopic pectopexy. (a) Peritoneum opened and bladder dissected to expose the cervix (star). (b) Right side: peritoneum opened along the pubic bone (dotted line) between the round ligament (black star) and the medial umbilical ligament (white star) to expose the pectineal ligament (arrow), with the external iliac vessels superolateral to it (arrowhead). (c) Middle of the mesh fixed to the exposed cervix (star). (d) Left mesh arm anchored to the pectineal ligament with AbsorbaTack after passage through a retroperitoneal tunnel from the cervix (arrow). (e) Reperitonization after mesh fixation. (f) Intraoperative cystoscopy showing indentation of the mesh over the bladder dome (arrow). (g) Left obturator neurovascular bundle (white arrow) at the inferolateral edge of the pectineal ligament; arrowhead, medial umbilical ligament. (h) Pubic vein lying on the left pectineal ligament (arrow). From Chuang FC, et al. Int Urogynecol J. 2022;33(7):1949-1956, Fig. 2 (CC BY 4.0).
Mesh configurations
| Configuration | Dimensions | Material | Vaginal / cervical fixation | Lateral fixation | Best for |
|---|---|---|---|---|---|
| Horizontal strip (Noé/Chuang variants) | 3 × 15 cm in the Noé long-term cohort; 3 × 23 cm DynaMesh-PRS in Chuang's series | PVDF or polypropylene according to study/device | Central portion to vaginal cuff or cervix; fixation pattern varies | Bilateral iliopectineal ligaments | Apical prolapse with study-specific concomitant repair[1][16][19][20] |
| T-shaped mesh | 8 × 15 cm sheet cut to a T in one description | Polypropylene | Short (vertical) arm to anterior vaginal wall + cervical stump | Two lateral (horizontal) arms to bilateral Cooper's ligaments | One pectopexy configuration for apical + anterior prolapse[9][10] |
| Inverted T-mesh | Custom cut | PVDF or polypropylene | Anterior arm extended along the vesicovaginal septum + cervix | Bilateral iliopectineal ligaments | Advanced uterine + anterior prolapse[2][3][10] |
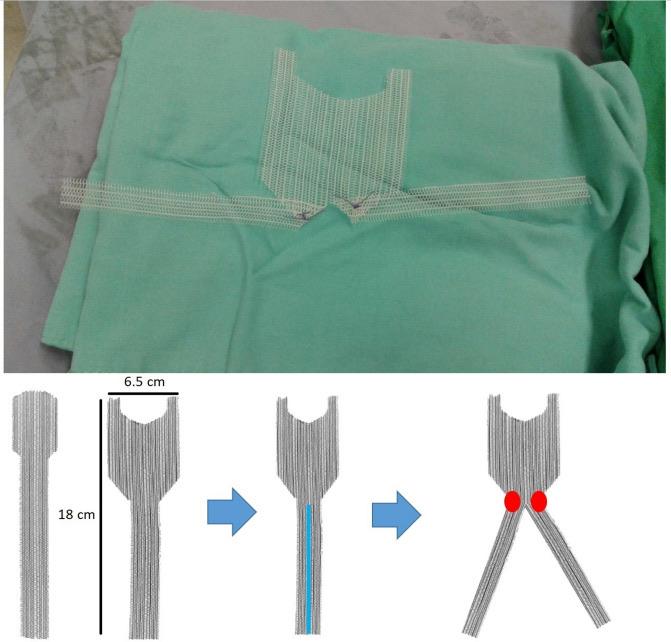
Construction of an inverted T-shaped mesh for pectopexy. The anterior piece of a PELVI-STOP mesh (6.5 × 18 cm) has its tail cut into two halves, and two sutures at the junction of the tail and the main piece form the inverted T. From Yang E, et al. Sci Rep. 2026;16(1):11202, Fig. 2 (CC BY).[10]
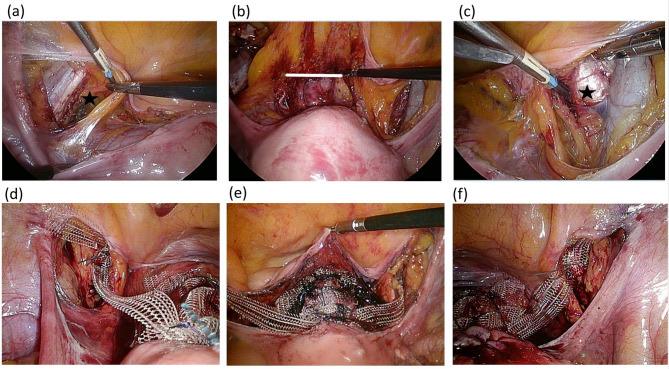
Laparoscopic pectopexy with an inverted T-mesh. (a) Peritoneum opened along the pubic bone between the left round ligament and the left medial umbilical ligament to expose the iliopectineal ligament (black star). (b) Anterior peritoneum of the uterus and bladder dissected distally to the level of the bladder neck (white line). (c) Right iliopectineal ligament exposed (black star). (e) With the uterus in its natural position without tension, the central portion of the mesh is sutured to the anterior cervix and the endopelvic fascia of the anterior vaginal wall with continuous 1-0 V-Loc. (d, f) The two lateral arms are fixed to the iliopectineal ligaments with interrupted 2-0 Ethibond. From Yang E, et al. Sci Rep. 2026;16(1):11202, Fig. 1 (CC BY).[10]
Y-shaped mesh. In the cited reports, Y-shaped mesh belongs to a different named route. Chen 2018 and Li 2021 describe transvaginal single-port sacral-promontory fixation, with a separate anterior attachment to the descending pubic ramus.[22][23] See Sacrocolpopexy.
Material choice. The 2025 pectopexy scoping review found polypropylene mesh in 46.7% of included studies.[2] PVDF appears in other reported variants.[2][3] In uterus-preserving pectopexy, anterior versus posterior cervical strip placement was examined in a separate cohort.[21]
Preparation and delivery. A mesh strip may be rolled for trocar introduction and unfolded intracorporeally; published dimensions, trocar choice and edge finishing are variant- or device-specific.[1][22][23]
A cadaveric biomechanical study found no significant difference in ultimate load or failure displacement between the tested continuous and interrupted sutures (see Biomechanical fixation note).[12]
Biomechanical fixation note
In eight fresh cadavers (16 ligaments, 33 material-specific tests), the tested mesh and single interrupted suture had ultimate load 35 ± 12 N, versus 48 ± 7 N with continuous suture; the difference was not statistically significant. The authors found the tested mesh limiting in their setup.[12]
Mesh-Free (Non-Mesh) Variants
| Variant | Technique | Outcomes |
|---|---|---|
| Laparoscopic Non-Mesh Cerclage Pectopexy (LNMCP), Zhang and Lyu | Permanent cervical cerclage sutures (non-absorbable) embedded along the round ligament bilaterally to the iliopectineal ligament | In 16 reported cases, OR time was 67.8 ± 15.5 min and EBL 73.1 ± 51.1 mL; at mean follow-up of 6.6 ± 3.8 months, author-defined objective success (no prolapse beyond the hymen, bothersome bulge or retreatment) was 100% and subjective success (PGI ≤2) was 93.8%, without a comparative arm.[13] |
| LNMCP, uterine-preserving variant (LNMCPUP) | Uterine preservation while retaining cerclage approach | In 14 cases (mean follow-up 19.71 ± 15.87 months), reported objective success was 100% and subjective success 92.86%; there was no comparative arm.[7] |
| Meshless pectopexy (Salman's modification) | Monofilament non-absorbable sutures (no mesh) to suspend uterus to bilateral iliopectineal ligaments | Single-group series of 40 women with stage 3–4 prolapse: mean C-point change −8.21 ± 3.03 cm at one year; reported apical recurrence 7.9%.[14] |
LESS and Robotic Pectopexy
| Variant | Notes |
|---|---|
| Laparoendoscopic Single-Site (LESS) pectopexy | The narrated single-patient video report used a single umbilical site and reported an ~80-minute operation, without a comparator for obesity-specific advantage.[6] |
| Robot-assisted pectouteropexy | A uterus-preserving robotic case report in an obese patient describes visualization and maneuverability advantages[4] |
Learning Curve
In one single-surgeon retrospective comparison of 18 initial pectopexies and 21 later-experience sacrocolpopexies, a CUSUM turning point occurred at the 12th pectopexy case. The groups differed in age and had short, unequal follow-up.[1]
Outcomes and Efficacy
The 2025 scoping review identified only four randomized trials among 30 studies and substantial outcome heterogeneity.[2]
| Endpoint | Result |
|---|---|
| Study-defined objective success | 16/16 in Zhang's non-mesh cerclage series (no prolapse beyond the hymen, bothersome bulge or retreatment; mean follow-up 6.6 months) and 14/14 in Lyu's uterine-preserving series (POP-Q Ba, Bp and C at or below 0; mean follow-up 19.71 months)[7][13] |
| Subjective success | 93.8% (15/16; mean follow-up 6.6 months) and 92.86% (13/14; mean follow-up 19.71 months) in separate non-mesh cerclage series; both defined success as PGI at or below 2[7][13] |
| Apical recurrence | 0–7.9% in selected short-term reports; Noé separately reported 8.0% in a longer combined-repair cohort[3][7][14][16] |
| 10-yr recurrence-free survival (median) | 9.34 yr[16] |
| No apical re-fixation in Noé's combined-repair cohort | 94.9% (42/832 re-fixed); distinct from all apical recurrence[16] |
| Reoperation during 4–10 yr follow-up | 81/832 (9.7%)[16] |
| OR time (illustrative LESS case) | Approximately 80 min in one published video case[6] |
| OR time (Chuang pectopexy cohort) | 182.9 ± 27.2 min in 18 early cases with other procedures frequently performed[1] |
| Patient-reported outcomes (including PFDI-20, PFIQ-7 and PISQ-12) | Improvement reported in selected series; instruments and follow-up differ, and the scoping review found heterogeneous reporting.[2][5][11][13] |
Comparative Outcomes
vs Sacrocolpopexy (2025 meta-analyses + comparative studies)
Lin's 2025 review pooled ten randomized and nonrandomized comparative studies (764 patients), with study follow-up ranging from 3 to 21.8 months.[8] Chuang's separate 18-versus-21 retrospective series had different ages and unequal mean follow-up (7.2 versus 16.2 months).[1]
| Parameter | Pectopexy | Sacrocolpopexy | Significance |
|---|---|---|---|
| Operative time | 34.4 min shorter in Lin's pooled estimate | — | 95% CI −47.12 to −21.69 min; p < 0.01[8] |
| Blood loss | 13.34 mL less in Lin's pooled estimate | — | 95% CI −21.37 to −5.32 mL; p < 0.01[8] |
| Hospital stay | 0.15 d shorter in Lin's pooled estimate | — | 95% CI −0.26 to −0.04 d; p < 0.01[8] |
| Postoperative bowel dysfunction | Lin reports fewer events with pectopexy | — | The abstract's RR 1.09 does not explain its comparison coding; avoid a quantitative patient-risk estimate from it alone[8] |
| Postoperative low back pain | 0/18 in Chuang's pectopexy group | 4/21 in its sacrocolpopexy group | p = 0.11; small, non-significant comparison[1] |
| Prolapse recurrence | No difference detected in Lin's pooled comparison[8] | — | — |
| Anatomical outcomes | No difference detected in Lin's pooled comparison[8] | — | — |
| Satisfaction | No difference detected in Lin's pooled comparison[8] | — | — |
| Sexual function | No difference detected in Lin's pooled comparison | — | No demonstrated superiority[8] |
| Quality of life | No difference detected in Lin's pooled comparison | — | Study instruments and follow-up differ[8] |
In a prospective cohort of 102 pectopexy and 101 sacrocolpopexy patients, Yang et al. reported urinary-symptom recurrence at one year in 13.7% versus 5.0% (OR 3.1, 95% CI 1.1–8.8). Concomitant hysterectomy differed (7 versus 40 patients).[17]
A separate nonrandomized pilot reported one-year all-compartment anatomical cure (POP-Q stage <2) in 33/42 inverted-T pectopexy patients and 23/25 selected sacral-repair patients. The authors also state that one and five patients, respectively, lacked a one-year pelvic examination, making those reported all-patient anatomical proportions difficult to reconcile with examination coverage.[10] Baseline prolapse pattern and patient characteristics differed.[10]
vs Sacrospinous Ligament Fixation
The cited pectopexy-versus-SSLF comparison reported operative time 151.8 versus 69 minutes and a vaginal-length difference, but its procedure selection and concomitant repairs limit causal interpretation.[15]
vs High Uterosacral Ligament Suspension (HUSLS)
Peng’s retrospective one-year comparison included 23 uterine-preserving pectopexies, 78 pectopexies with hysterectomy, and 69 HUSLS procedures with hysterectomy. The reported anatomical and sexual-function differences are associations in selected groups with different uterine status and concomitant surgery.[5]
Three-way comparison (Sánchez-Ferrer 2025, n = 180)
Sacropexy versus pectopexy versus lateral suspension: an observational cohort found no detected difference in its surgical-failure endpoint and shorter operative times for the non-sacral groups.[18]
Complications
During a mean 7.2-month follow-up, postoperative SUI occurred in 6/18 pectopexy patients in Chuang's retrospective cohort; 4 of the 6 had preoperative occult SUI and had not undergone a concomitant anti-incontinence procedure.[1]
| Complication | Rate |
|---|---|
| Major intraoperative complications (bladder, bowel, ureteral injury) | Chuang reported no major injury among 18 pectopexy patients.[1] In an exploratory randomized trial's 15-patient pectopexy arm, one bladder injury required intraoperative repair (Clavien-Dindo IIIb).[28] Szymczak reported one bowel injury among 53 pectopexy patients (1.9%); its 1.8% figure covered two severe events among 114 patients in both study arms.[15] The scoping review did not report a pooled injury rate.[2] |
| Mesh exposure | 1/40 (2.5%) at 3 months in Hai et al.'s single-center retrospective cohort[26] |
| Chronic pelvic pain | 2/40 (5.0%) during follow-up in Hai et al.'s single-center retrospective cohort[26] |
| Urinary retention | 1/40 (2.5%) postoperatively in Hai et al.'s single-center retrospective cohort[26] |
| Urinary-symptom recurrence (not de novo SUI) | 13.7% after pectopexy versus 5.0% after sacrocolpopexy at one year in Yang's prospective cohort; different from its de novo urinary-symptom endpoint[17] |
| Postoperative constipation / bowel dysfunction | Direction favored pectopexy in some comparative syntheses; Chuang's 0/18 versus 4/21 difference was not significant (p = 0.11)[1][8] |
| Postoperative low back pain | 0/18 versus 4/21 in Chuang's small, non-significant comparison (p = 0.11)[1] |
| Presacral hemorrhage | N/A (no sacral dissection) |
Postoperative Follow-Up
NICE NG123 recommends review six months after prolapse surgery, with vaginal examination and a mesh-exposure check when mesh was used.[29]
Long-Term Durability — 10-Year Data
The long-term single-center retrospective series (Noé 2026, n = 832) included laparoscopic pectopexy alone or with defect-oriented native-tissue repairs. Recurrence was defined as POP-Q stage II or higher in a previously treated compartment; de novo prolapse was stage II or higher in a compartment not involved in or treated at the index surgery. Together, these events occurred in 140/832 (16.8%).[16]
- Median recurrence-free survival: 9.34 yr (IQR 7.36–10.60).
- Median reoperation-free survival: 9.56 yr (IQR 7.68–10.71).
- In this cohort, 87.9% of observed events occurred within the first 4 years; the authors support attention through that interval.[16]
- 42/832 (5.05%) underwent apical re-fixation; this differs from any apical recurrence, reported separately as 8.0%.[16]
- Lateral defect severity was associated with recurrence in the cohort.[16]
Biomechanical Considerations
Cadaveric biomechanical testing of the iliopectineal ligament:[12]
- Mesh and single interrupted suture: 35 ± 12 N.
- Mesh and continuous suture: 48 ± 7 N (NS).
- The tested mesh was the limiting factor in this cadaver setup.
Limitations and Evidence Gaps
- Most evidence is from observational studies and small RCTs, with only 4 RCTs (13.3%) among 30 eligible studies in the most recent scoping review.[2]
- Studies are dominated by Asian centers (66.7%) and tertiary referral practice (86.7%).[2]
- PROMs underreported. No included study reported recurrence of prolapse symptoms.[2]
- Long-term data > 10 years remain limited.
- Higher urinary-symptom recurrence in one comparative study warrants further investigation.[17]
Key Principles
- Pectopexy uses bilateral Cooper's-ligament fixation as an alternative to sacrocolpopexy, using the same mesh-augmented apical-suspension principle with a different anchor.[1][3]
- Avoids presacral dissection.[1][3]
- Shorter operative time in several comparisons (Lin pooled mean difference −34.4 minutes); the 12-case CUSUM turning point came from one initial 18-patient, single-surgeon series.[1][8]
- Bowel and back-pain findings vary by cohort. In Chuang's series, defecation symptoms and low back pain were each reported in 0/18 pectopexy patients versus 4/21 sacrocolpopexy patients; mean follow-up was 7.2 versus 16.2 months, respectively. Neither comparison was significant.[1]
- Anatomic relationship: the iliopectineal ligament is medial to the external iliac vessels in the Chuang technique; preserve the vessels and obturator neurovascular structures.[1]
- Single-suture fixation was tested in cadavers.[12]
- In Noé's 832-patient retrospective cohort treated with laparoscopic pectopexy and defect-oriented native-tissue repair, 42 underwent apical re-fixation; the authors state that 85% of recurrences occurred within four years.[16]
- Higher urinary-symptom recurrence versus sacrocolpopexy in one comparative cohort; counsel and follow accordingly.[17]
- Mesh-free and meshless variants (cerclage pectopexy, Salman's modification) are emerging options for mesh-averse patients.[7][13][14]
Videos
References
1. Chuang FC, Chou YM, Wu LY, et al. Laparoscopic pectopexy: the learning curve and comparison with laparoscopic sacrocolpopexy. Int Urogynecol J. 2022;33(7):1949-1956. doi:10.1007/s00192-021-04934-4.
2. Jongjakapun A, Temtanakitpaisan T, Sothornwit J, Pattanittum P, Ngamjarus C. Pectopexy for pelvic organ prolapse: a scoping review. Int Urogynecol J. 2025. doi:10.1007/s00192-025-06232-9.
3. Noé KG, Spüntrup C, Anapolski M. Laparoscopic pectopexy: a randomised comparative clinical trial of standard laparoscopic sacral colpo-cervicopexy to the new laparoscopic pectopexy. Short-term postoperative results. Arch Gynecol Obstet. 2013;287(2):275-80. doi:10.1007/s00404-012-2536-7.
4. Usta T, Karacan T, Kale A, Mutlu S, Tıryakı T. Robot-assisted laparoscopic pectouteropexy: an alternative uterus-sparing technique for pelvic organ prolapse surgery. Int Urogynecol J. 2017;28(11):1751-1753. doi:10.1007/s00192-017-3326-3.
5. Peng J, Li S, Wang L, et al. Comparison of efficacy between laparoscopic pectopexy and laparoscopic high uterosacral ligament suspension in the treatment of apical prolapse — short-term results. Sci Rep. 2023;13(1):18519. doi:10.1038/s41598-023-45871-0.
6. Wang Q, Guan Z, Guo X, et al. Stepwise laparoendoscopic single-site pectopexy for pelvic organ prolapse. J Minim Invasive Gynecol. 2021;28(6):1142-1143. doi:10.1016/j.jmig.2020.10.008.
7. Lyu C, Cheon WC, Sheung Ngan HY, Wei Y, Zhang W. Laparoscopic non-mesh cerclage pectopexy with uterine preservation for pelvic organ prolapse. J Vis Exp. 2024;(212). doi:10.3791/67239.
8. Lin Y, Liu JJ, Fang K, Wu H, Li N. Pectopexy compared with sacrocolpopexy for the treatment of pelvic organ prolapse: a systematic review and meta-analysis of clinical outcomes. Eur J Obstet Gynecol Reprod Biol. 2025;312:114091. doi:10.1016/j.ejogrb.2025.114091.
9. Pirtea L, Balint O, Secoșan C, Grigoraș D, Ilina R. Laparoscopic pectopexy with Burch colposuspension for pelvic prolapse associated with stress urinary incontinence. J Minim Invasive Gynecol. 2020;27(5):1023-1024. doi:10.1016/j.jmig.2019.10.022.
10. Yang E, Tsai CP, Shen PS, et al. One-year outcomes of an innovative laparoscopic pectopexy procedure using inverted T-mesh for treatment of advanced uterine and anterior vaginal prolapse. Sci Rep. 2026;16(1):11202. doi:10.1038/s41598-026-40730-0.
11. Chang YT, Yang E, Tseng JJ, et al. Comparison of 1-year outcomes after uterine-preserving laparoscopic pectopexy using an inverted T-shaped mesh versus the horizontal DynaMesh: a retrospective, multicenter cohort study. Int J Gynaecol Obstet. 2026. doi:10.1002/ijgo.70915.
12. Sauerwald A, Niggl M, Puppe J, et al. Laparoscopic pectopexy: a biomechanical analysis. PLoS One. 2016;11(2):e0144143. doi:10.1371/journal.pone.0144143.
13. Zhang W, Cheon WC, Ngan HYS, Wei Y, Lyu C. Laparoscopic non-mesh cerclage pectopexy for pelvic organ prolapse. J Vis Exp. 2022;(187). doi:10.3791/64388.
14. Erdem B, Salman S, Usta ZK, et al. A novel approach for apical prolapse surgery: meshless pectopexy (Salman's modification). Int Urogynecol J. 2025. doi:10.1007/s00192-025-06107-z.
15. Szymczak P, Grzybowska ME, Sawicki S, Futyma K, Wydra DG. Perioperative and long-term anatomical and subjective outcomes of laparoscopic pectopexy and sacrospinous ligament suspension for POP-Q stages II-IV apical prolapse. J Clin Med. 2022;11(8):2215. doi:10.3390/jcm11082215.
16. Noé G, Farsaki E, Anapolski M, Pitsillidi A. Ten years of laparoscopic pectopexy: a case series analysis. Int Urogynecol J. 2026;37(3):757-764. doi:10.1007/s00192-025-06377-7.
17. Yang Y, Li Z, Si K, et al. Effectiveness of laparoscopic pectopexy for pelvic organ prolapse compared with laparoscopic sacrocolpopexy. J Minim Invasive Gynecol. 2023;30(10):833-840.e2. doi:10.1016/j.jmig.2023.06.011.
18. Sánchez-Ferrer ML, Ñíguez-Sevilla I, Ruiz-Cotorruelo VL, Arense-Gonzalo JJ. A cohort-based comparative study of three minimally invasive apical prolapse surgeries: sacropexy, pectopexy, and lateral suspension. J Clin Med. 2025;14(17):6073. doi:10.3390/jcm14176073.
19. Noé GK, Schiermeier S, Papathemelis T, et al. Prospective international multicenter pelvic floor study: short-term follow-up and clinical findings for combined pectopexy and native tissue repair. J Clin Med. 2021;10(2):217. doi:10.3390/jcm10020217.
20. Szymczak P, Grzybowska ME, Wydra DG. Comparison of laparoscopic techniques for apical organ prolapse repair — a systematic review of the literature. Neurourol Urodyn. 2019;38(8):2031-2050. doi:10.1002/nau.24115.
21. Biyik I, Gezer S, Karatas S, Grigoriadis G. Comparison of surgical outcomes of mesh placement anterior versus posterior to the cervix uteri in laparoscopic pectopexy with uterine preservation. Int Urogynecol J. 2026;37(3):749-755. doi:10.1007/s00192-025-06382-w.
22. Chen Y, Li J, Hua K. Transvaginal single-port laparoscopy pelvic reconstruction with Y-shaped mesh. J Minim Invasive Gynecol. 2018;25(7):1138-1141. doi:10.1016/j.jmig.2018.01.030.
23. Li J, Hu C, Wang X, Hua K, Chen Y. Transvaginal single-port laparoscopic pelvic reconstruction with Y-shaped mesh: experiences of 93 cases. Int Urogynecol J. 2021;32(4):905-911. doi:10.1007/s00192-020-04418-x.
24. Banerjee C, Noé KG. Laparoscopic pectopexy: a new technique of prolapse surgery for obese patients. Arch Gynecol Obstet. 2011;284(3):631-635. Published online October 13, 2010. doi:10.1007/s00404-010-1687-7.
25. National Institute for Health and Care Excellence. "Laparoscopic mesh pectopexy for apical prolapse of the uterus or vagina." HealthTech guidance HTG464. 2018; migrated from IPG608 in 2026 without change to recommendations. Guidance
26. Hai P, Tian Y, Wang L, et al. "Clinical application of laparoscopic pectopexy in the treatment of pelvic organ prolapse: efficacy and safety." Eur J Med Res. 2026;31:145. doi:10.1186/s40001-025-03735-5
27. Pulatoğlu Ç, Doğan O, Medisoğlu MS, et al. "Surgical anatomy of the pectineal ligament during pectopexy surgery: The relevance to the major vascular structures." Turk J Obstet Gynecol. 2020;17(1):21-27. doi:10.4274/tjod.galenos.2020.21284
28. Khoiwal K, Dash KC, Gaurav A, Chaturvedi J. "Comparison of laparoscopic pectopexy with the standard laparoscopic sacropexy for apical prolapse: an exploratory randomized controlled trial." J Turk Ger Gynecol Assoc. 2023;24(3):144-151. doi:10.4274/jtgga.galenos.2023.2022-12-15
29. National Institute for Health and Care Excellence. "Urinary incontinence and pelvic organ prolapse in women: management." NICE guideline NG123. 2019. Guidance