Sacrohysteropexy
Sacrohysteropexy is a uterine-sparing reconstructive operation that suspends the uterus (via the cervix) to the sacral promontory usually with synthetic mesh, restoring apical support while preserving the uterus. Open, laparoscopic and robotic techniques are described; biologic-graft variants have less supporting evidence.[1][2][3]
For the post-hysterectomy mesh equivalent, see Sacrocolpopexy. For the supracervical hysterectomy variant, see Supracervical Hysterectomy at Sacrocolpopexy. For native-tissue uterus-preserving operations, see Sacrospinous Hysteropexy and Manchester-Fothergill Procedure.
Definition and Rationale
Sacrohysteropexy attaches the cervix or uterine isthmus to the anterior longitudinal ligament of the sacrum using a synthetic or biologic graft, providing an abdominally placed suspension of the cervix or uterus.[1][4]
Rationale for uterine preservation:
- Some comparisons report less blood loss or shorter surgery than hysterectomy-based mesh repairs.[3][5]
- A 2018 review reported less mesh exposure after sacrohysteropexy than hysterectomy plus mesh sacrocolpopexy; a 2014 review reported less mesh exposure after sacrocervicopexy with subtotal hysterectomy than after total-hysterectomy sacrocolpopexy, although mesh complications still occur.[3][6] A 2025 meta-analysis of nine observational studies did not detect a mesh-related complication difference between hysterectomy plus sacrocolpopexy and sacrohysteropexy (P = 0.53).[28]
- Retains the uterus.[7]
- Patient preference is an independent reason to discuss uterine preservation.[5]
Indications and Patient Selection
ACOG and AUGS describe hysteropexy as a viable alternative to hysterectomy in women with uterine prolapse, although there is less available evidence on its safety and efficacy than for hysterectomy (Level B).[1][8] The 2025 AUGS Clinical Practice Statement recommends offering uterine-preserving prolapse surgery to adults with a uterus considering apical suspension who have no previous or current uterine or cervical pathology and are at low or average risk of current or future pathology , after an individualized benefit-risk discussion that includes the cancer-detection benefit of hysterectomy.[25]
| Criterion | Detail |
|---|---|
| Stage | Bothersome apical prolapse; several trials recruited POP-Q stage ≥ 2[9][10] |
| Uterine preservation | Patient desires uterine preservation (fertility, personal preference, cultural reasons)[7] |
| Childbearing | Most comparative evidence concerns completed childbearing; future pregnancy requires a separate discussion[11] |
| Uterine status | Appropriate cervical screening and assessment of abnormal bleeding or suspected uterine/cervical disease[7][12] |
Findings requiring additional assessment or an alternative plan
- Abnormal uterine bleeding requiring evaluation.[7][12]
- Uterine or cervical premalignancy or malignancy.[12]
- A hereditary cancer syndrome for which retaining the uterus is contraindicated.[27]
- Significant uterine pathology (fibroids requiring treatment, endometrial hyperplasia).[7]
- Cervical elongation without comparable descent of the uterine body.[12] Consider the anatomy and alternatives, including Manchester repair.[12]
Surgical Technique — Laparoscopic / Robotic
The operation shares the sacral exposure of sacrocolpopexy while retaining the uterus. The sequence below summarizes published laparoscopic or robotic sacrohysteropexy descriptions; port layout, graft configuration and fixation details vary.[2][13][24]
- Port placement and exposure. Use the chosen laparoscopic or robotic access and patient positioning; retract the sigmoid as needed to expose the promontory.[2][14]
- Sacral promontory dissection. Incise peritoneum over the promontory; identify and expose the anterior longitudinal ligament (ALL) of S1. Identify the iliac vessels, middle sacral vessels, right ureter and nearby autonomic structures before fixation. Presacral vascular injury can cause major hemorrhage; the exposure and fixation site must follow the individual anatomy rather than a fixed distance or blind placement.[2][14] Izett-Kay and Price describe two hazards specific to their Oxford Hysteropexy technique: a low great-vessel bifurcation can place vessels near the presumed fixation site, and pneumoperitoneum with steep Trendelenburg can empty and flatten the left common iliac vein until it resembles peritoneum.[26] They describe a soft "pillow sign" on instrument palpation as a prompt for careful tissue identification.[26]
- Peritoneal tunnel. Create a peritoneal tunnel from the promontory to the cervix along the right pelvic sidewall, lateral to the rectum, to house the mesh and allow subsequent peritonization.[2][14]
- Cervical / uterine dissection.
- Standard (wrap) technique: incise anterior and posterior peritoneum overlying cervical stroma; create broad-ligament windows under direct visualization, identifying and protecting the uterine vessels; no region should be assumed avascular from a generic landmark alone; dissect vesicovaginal and rectovaginal spaces to expose cervical stroma.[13][14] Izett-Kay and Price note that anomalous veins may occupy a pelvic-sidewall or broad-ligament window that otherwise appears avascular, and describe lifting the peritoneum from the sidewall before incision and inspecting an uncertain broad-ligament window from both sides, by anteversion and retroversion, before proceeding.[26]
- Simplified posterior-only technique (Jan 2018): only the posterior aspect of the cervix is dissected, which limits anterior dissection.[15]
- Mesh selection and preparation. See table below.
- Mesh attachment to the cervix.
- Y-shaped or cervix-encircling configuration: anterior arm sutured to anterior cervical stroma / vaginal wall; posterior arm to posterior cervical stroma, using interrupted non-absorbable or delayed-absorbable sutures; arms wrap around cervix and meet at the sacral arm.[13]
- Flat strip (simplified): single posterior strip with interrupted sutures, extending directly to the promontory.[15]
- Anterior and posterior extension: in multicompartment prolapse, extend anterior arm along vesicovaginal septum and posterior arm along rectovaginal septum (full sacrocolpopexy-style).[17]
- Sacral fixation. Secure the sacral end of the mesh to the ALL at S1 using the fixation method described for the selected technique; avoid fixation into the disc and excessive tension; uterus elevated to anatomic position without excess tension.[13][4] 8.[2][15] Peritonization. Close peritoneum over the mesh with a running absorbable suture to separate the graft from bowel; bowel obstruction remains possible; tunneling technique reduces peritoneal defect size.[2][15]
- Cystoscopy. After apical mesh placement, survey the bladder and assess efflux from both ureteral orifices while the patient is under anesthesia (ACOG/AUGS Level C).[8]
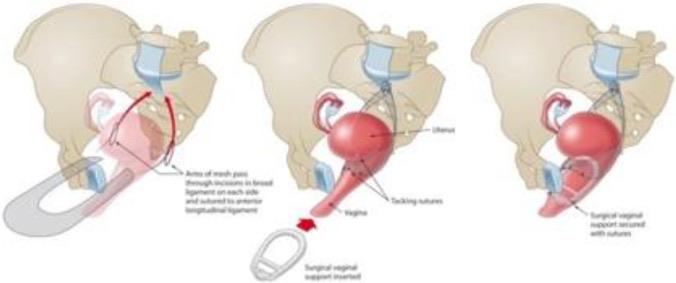
Mesh hysteropexy as described by Gopinath and colleagues. A U-shaped mesh passes through the broad-ligament windows and suspends the uterus and upper vagina from the sacral promontory, and a supporting pessary is placed in the vagina. From Gopinath D, et al. Int Urogynecol J. 2023;34(1):105-113, Fig. 2 (CC BY).[24]
Mesh selection
| Mesh | Configuration | Notes |
|---|---|---|
| Type-1 polypropylene (macroporous, monofilament) | Y-shaped or flat strip | Common in published techniques; weight, pore structure and handling differ by product[1][2] |
| PVDF (polyvinylidene fluoride) | Posterior cervical strip, square weave | Described in Jan and colleagues' simplified technical video; graft geometry and handling are product-specific[15] |
| SERATEX SlimSling | Narrow strip | Reported in a named retrospective sacrohysteropexy series[16] |
| Biologic graft | Geometry not specified | Described for abdominal or laparoscopic cervix-to-ALL suspension; comparative durability remains uncertain[8] |
For their bifurcated ProLite mesh, typically a 15 cm by 4 cm piece secured with two to three 5 mm helical fasteners, Izett-Kay and Price orient the weave's higher-tensile axis from sacral promontory to uterus (cranial to caudal) to limit stretch in that configuration. This is specific to their described technique and implant; product instructions govern handling of any selected mesh.[26]
Concomitant procedures
Assess anterior and posterior compartment defects separately. For significant apical or anterior prolapse, ACOG/AUGS (2019, Level C) recommends preoperative occult stress-incontinence assessment with reduced-prolapse cough stress testing or urodynamics.[8] A 2026 consensus for primary uterovaginal prolapse advises a reduced full-bladder stress test and advises against urodynamics solely to diagnose stress incontinence.[27] For women without preoperative urinary incontinence, explain the risk of postoperative leakage and possible later treatment; NICE NG123 recommends against continence surgery solely to prevent incontinence.[29] In women with occult stress incontinence undergoing vaginal prolapse repair, a 2026 Cochrane review of five randomized trials (n = 369) found that a concomitant midurethral sling probably reduced patient-reported postoperative stress incontinence (RR 0.38, 95% CI 0.26–0.55); adverse effects remained uncertain.[30] Colporrhaphy or treatment for stress incontinence may be added when indicated.[8] Published series report differing combinations.[9][16][17] For cervical elongation, AUGS advises considering trachelectomy at the time of uterus-preserving surgery once childbearing is complete (grade C; the statement's table defines elongation as cervical length above 4 cm), with caution in reproductive-age patients because partial trachelectomy may affect future pregnancy.[25]
Operative planning
Operating time, blood loss and length of stay vary with surgical route, concomitant repairs, surgeon experience and local recovery pathways. Compared with vaginal hysteropexy, sacrohysteropexy adds abdominal access and mesh dissection; operating times are trial-specific.[9][18]
Outcomes: retain the endpoint and denominator
| Source | Reported result | How to interpret it |
|---|---|---|
| Izett-Kay cross-sectional cohort | 1,121/1,766 women responded (63.5%), median 46-month follow-up; 4/1,121 (0.4%) reported a mesh complication requiring removal, confirmed from records | Mesh-removal surgery. Follow-up intervals were unequal.[20] |
| Same cohort | Reoperation for apical POP 3.7%; any POP 13.6%; 81.4% reported being much/very much better | Separate apical retreatment, any-compartment retreatment and patient-reported improvement; none is a universal anatomical cure rate.[20] |
| Izett-Kay randomized-trial follow-up | 62 of 101 randomized women attended long-term review, mean 100 months | Small surviving sample and attrition constrain the comparison; see below.[19] |
Comparative Outcomes
vs Vaginal Hysterectomy with Apical Suspension
7-year RCT follow-up (Izett-Kay 2022; 62 of 101 randomized participants attended long-term review):[19]
- Apical reoperation was 6.1% versus 17.2% (p = 0.17).[19]
- Significantly higher apical suspension (point C −5 versus −4.25, p = 0.02).
- Longer total vaginal length among those assessed (9 cm versus 6 cm, p < 0.001).
In a 2024 randomized noninferiority trial, minimally invasive sacrohysteropexy and vaginal hysterectomy with uterosacral suspension had one-year composite recurrence in 16.4% and 15.8% of 73 analyzed women per group, respectively; sacrohysteropexy had longer operating time and more pain from one week to one month.[10]
The Brennand 2025 prospective cohort (n = 321) compared native-tissue uterine-preserving and hysterectomy-based repairs. It found associations with lower composite recurrence (adjusted RR 0.47, 95% CI 0.32–0.69) and fewer procedural complications (adjusted RR 0.19).[5]
vs Sacrospinous Hysteropexy — LAVA trial
In LAVA's 12-month intention-to-treat analysis using last observation carried forward, apical composite surgical failure occurred in 1/64 women (1.6%) assigned laparoscopic mesh sacrohysteropexy and 2/61 (3.3%) assigned vaginal native-tissue sacrospinous hysteropexy, meeting the prespecified noninferiority criterion. Six women assigned laparoscopic repair received vaginal surgery; overall surgical failure, which also counted prolapse in other compartments, was 42/64 (65.6%) versus 38/61 (62.3%).[9] Bothersome overactive bladder and fecal incontinence were more frequent after sacrohysteropexy; dyspareunia was more frequent after sacrospinous hysteropexy. The 126 participants had stage 2 or greater uterine prolapse and no previous pelvic-floor surgery.[9]
vs Sacrocolpopexy with Subtotal Hysterectomy
A 2025 meta-analysis of nine observational studies associated laparoscopic sacrocolpopexy with concomitant total or supracervical hysterectomy with higher objective apical and anterior and subjective success than minimally invasive sacrohysteropexy; it did not detect a reoperation difference. Hysteropexy had shorter operating time and hospital stay.[28]
In a retrospective propensity-matched comparison (44 per arm), stage 2 or greater recurrence during up to 60 months of follow-up was 2/44 after laparoscopic sacrocolpopexy with subtotal hysterectomy and 5/44 after robotic sacrohysteropexy. At 12 months, PGI-I <3 was reported by 43/44 (97.8%) versus 36/44 (81.8%), respectively (p = 0.034).[22]
Cochrane 2023
The review found differences in awareness of prolapse, repeat surgery, recurrent prolapse and several adverse outcomes uncertain or small for vaginal versus sacral hysteropexy.[18]
Complications
| Issue | Relevant assessment and counseling |
|---|---|
| Mesh exposure, erosion or pain | Possible even with uterine preservation. |
| Bladder, ureter or bowel injury | Related to the dissection, anatomy and associated procedures. |
| Presacral hemorrhage | A potentially serious hazard during promontory exposure and fixation. |
| Lumbosacral spondylodiscitis | Persistent low-back or radiating leg pain after sacral mesh fixation warrants assessment for spinal infection; a reported sacrohysteropexy case required mesh removal, antibiotics and spinal debridement.[31] |
| Bowel obstruction | May result from adhesions or exposed material despite peritoneal coverage. |
| Urinary, bowel or sexual symptoms | May persist, improve or arise after repair; assess them separately from apical support. |
| Recurrent prolapse / reoperation | May involve the apex or another compartment, with risk accumulating during follow-up. |
These categories are reported in clinical series and reviews; use source-specific denominators when quoting rates.[3][17][19][20][21]
Long-Term Durability
In a retrospective series of 270 patients, 242 had at least one year of follow-up, 76 at least five years and only 18 at least ten years; the maximum observed follow-up was 14.5 years. Its success estimates varied over time. PFDI-20 and PFIQ-7 scores remained significantly improved across follow-up. Anal incontinence and constipation rates decreased significantly after surgery.[17]
Fertility and Pregnancy
A 2025 systematic review of pregnancy after laparoscopic sacrohysteropexy:[11]
- The review reported cesarean delivery for all included cases; mean gestational age was 38 weeks where reported.[11]
- The small published case literature included recurrent uterine prolapse postpartum.
- Anterior-compartment prolapse was also described after birth.
A meta-analysis compared reported pregnancies after different uterus-preserving operations.[23] In the cited 2025 laparoscopic-hysteropexy review, all 26 reported pregnancies ended by cesarean section.[11] A 2026 review separately analyzed 14 case reports after mesh sacrohysteropexy: 12 deliveries were by cesarean and two were vaginal; one cesarean report described anterior mesh preventing bladder dissection.[32] Discuss repair choice and delivery planning with urogynecology and obstetrics.[11][23]
Posterior-only configurations have been described with the intention of avoiding cervical encirclement.[15]
Mesh-Free Alternative — Suture Hysteropexy
Laparoscopic / robotic suture-based hysteropexy (uterosacral ligament plication) is a distinct mesh-free option. In a retrospective single-surgeon comparison, composite success beyond one year was 60/71 (84.5%) after suture hysteropexy and 98/120 (81.7%) after mesh sacrohysteropexy. Success required point C above the hymen, no bulge, and no repeat uterine-prolapse surgery or pessary.[24] Mesh was associated with a greater one-year improvement in POP-Q point C in this retrospective cohort (change from baseline −7.20 versus −4.92 cm, p < 0.001).[24]
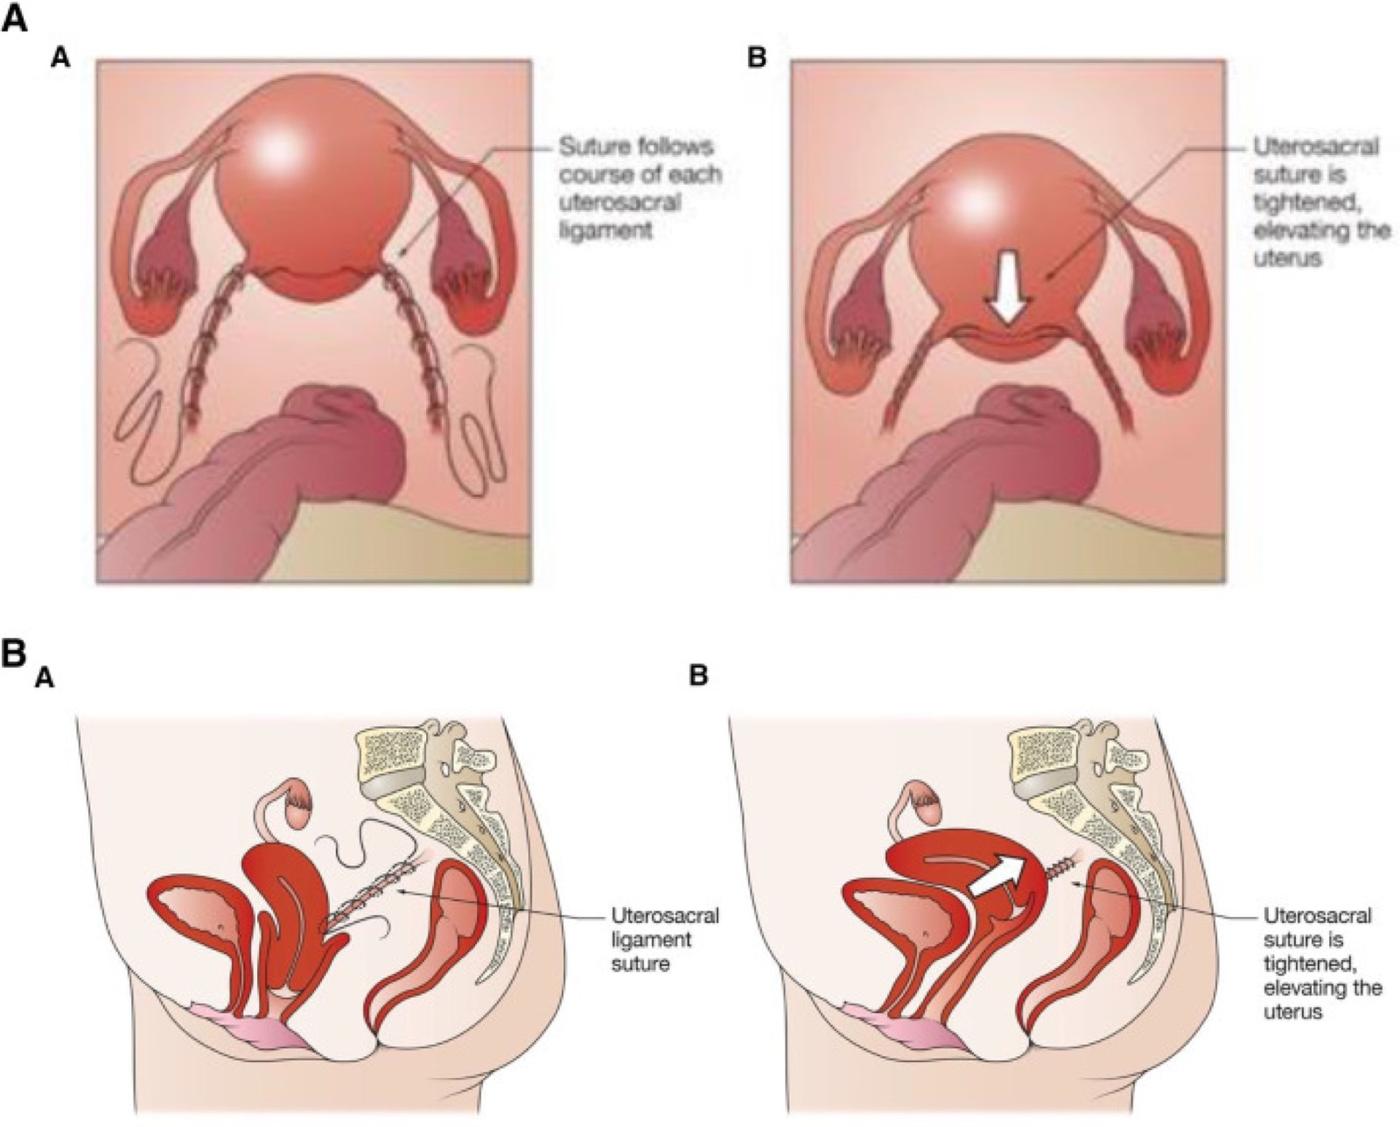
Suture hysteropexy. (A) Sutures placed into the posterior cervix and along each uterosacral ligament dorsally toward the sacrum (left); when tied (right), they shorten the ligaments and resupport the uterus and upper vagina. (B) Lateral view of the uterosacral sutures before tensioning and tying (left) and after tying (right). From Gopinath D, et al. Int Urogynecol J. 2023;34(1):105-113, Fig. 1 (CC BY 4.0).
Counseling and follow-up
- Clarify whether the goal is uterine preservation, future pregnancy, avoidance of vaginal surgery, or a combination; these are different decisions.
- Explain the permanent graft, operative route, native-tissue alternatives, and the possibility of mesh-related or prolapse retreatment. NICE NG123 recommends recording the mesh procedure and subsequent short- and long-term outcomes in a national registry and giving the patient written implant information with the device name, manufacturer, insertion date, and implanting surgeon's name and contact details.[29]
- Continue appropriate cervical screening and evaluate new abnormal bleeding rather than imposing routine endometrial surveillance on every asymptomatic patient.
- Offer a six-month review with vaginal examination and, if mesh was used, a mesh-exposure check, as NICE NG123 recommends; assess recurrent bulge, pain, urinary, bowel and sexual symptoms separately.[29]
Podcasts
Videos
References
1. Committee on Practice Bulletins—Gynecology and American Urogynecologic Society. Pelvic organ prolapse: ACOG Practice Bulletin, Number 214. Obstet Gynecol. 2019;134(5):e126-e142. doi:10.1097/AOG.0000000000003519.
2. Labanca L, Centini G, Lazzeri L, et al. Sacrohysteropexy: a way to spare the uterus. J Minim Invasive Gynecol. 2020;27(6):1254-1255. doi:10.1016/j.jmig.2019.12.006.
3. Meriwether KV, Antosh DD, Olivera CK, et al. Uterine preservation vs hysterectomy in pelvic organ prolapse surgery: a systematic review with meta-analysis and clinical practice guidelines. Am J Obstet Gynecol. 2018;219(2):129-146.e2. doi:10.1016/j.ajog.2018.01.018.
4. Leron E, Stanton SL. Sacrohysteropexy with synthetic mesh for the management of uterovaginal prolapse. BJOG. 2001;108(6):629-33. doi:10.1111/j.1471-0528.2001.00138.x.
5. Brennand EA, Scime NV, Huang B, et al. Hysterectomy versus uterine preservation for pelvic organ prolapse surgery: a prospective cohort study. Am J Obstet Gynecol. 2025;232(5):461.e1-461.e20. doi:10.1016/j.ajog.2024.10.021.
6. Rosati M, Bramante S, Conti F. A review on the role of laparoscopic sacrocervicopexy. Curr Opin Obstet Gynecol. 2014;26(4):281-9. doi:10.1097/GCO.0000000000000079.
7. Ridgeway BM. Does prolapse equal hysterectomy? The role of uterine conservation in women with uterovaginal prolapse. Am J Obstet Gynecol. 2015;213(6):802-9. doi:10.1016/j.ajog.2015.07.035.
8. American College of Obstetricians and Gynecologists and American Urogynecologic Society. Pelvic organ prolapse (joint publication of ACOG Practice Bulletin No. 214). Female Pelvic Med Reconstr Surg. 2019;25(6):397-408. doi:10.1097/SPV.0000000000000794.
9. van IJsselmuiden MN, van Oudheusden A, Veen J, et al. Hysteropexy in the treatment of uterine prolapse stage 2 or higher: laparoscopic sacrohysteropexy versus sacrospinous hysteropexy — a multicentre randomised controlled trial (LAVA Trial). BJOG. 2020;127(10):1284-1293. doi:10.1111/1471-0528.16242.
10. Hwang WY, Jeon MJ, Suh DH. Minimally invasive sacrohysteropexy versus vaginal hysterectomy with uterosacral ligament suspension for pelvic organ prolapse: a prospective randomized non-inferiority trial. J Minim Invasive Gynecol. 2024;31(5):406-413. doi:10.1016/j.jmig.2024.01.018.
11. Pitsillidi A, Vona L, Bettocchi S, Schiermeier S, Noé GK. Pregnancy after laparoscopic hysteropexy: a systematic review. J Clin Med. 2025;14(8):2777. doi:10.3390/jcm14082777.
12. Enklaar RA, Schulten SFM, van Eijndhoven HWF, et al. Manchester procedure vs sacrospinous hysteropexy for treatment of uterine descent: a randomized clinical trial. JAMA. 2023;330(7):626-635. doi:10.1001/jama.2023.13140.
13. Warehime J, Cope Z, Feroz R, et al. Robotic sacrohysteropexy: an instructional video for uterovaginal prolapse repair in patients with desired uterine preservation. Int Urogynecol J. 2022;33(12):3585-3586. doi:10.1007/s00192-022-05260-z.
14. Acsinte OM, Rabischong B, Bourdel N, Canis M, Botchorishvili R. Laparoscopic promontofixation in 10 steps. J Minim Invasive Gynecol. 2018;25(5):767. doi:10.1016/j.jmig.2017.10.020.
15. Jan H, Ghai V, Thakar R. Simplified laparoscopic sacrohysteropexy. J Minim Invasive Gynecol. 2018;25(7):1134. doi:10.1016/j.jmig.2018.01.014.
16. Rotem R, Alkeesh Y, Hirsch A, Ben-Shachar I, Marcus N. Long-term outcomes of laparoscopic sacrohysteropexy with SERATEX SlimSling mesh: a retrospective case series. Int Urogynecol J. 2025;36(3):655-661. doi:10.1007/s00192-024-06037-2.
17. Rusavy Z, Grinstein E, Gluck O, Abdelkhalek Y, Deval B. Long-term development of surgical outcome of laparoscopic sacrohysteropexy with anterior and posterior mesh extension. Int Urogynecol J. 2023;34(1):191-200. doi:10.1007/s00192-022-05102-y.
18. Maher C, Yeung E, Haya N, et al. Surgery for women with apical vaginal prolapse. Cochrane Database Syst Rev. 2023;7:CD012376. doi:10.1002/14651858.CD012376.pub2.
19. Izett-Kay ML, Rahmanou P, Cartwright RJ, Price N, Jackson SR. Laparoscopic sacrohysteropexy versus vaginal hysterectomy and apical suspension: 7-year follow-up of a randomized controlled trial. Int Urogynecol J. 2022;33(7):1957-1965. doi:10.1007/s00192-021-04932-6.
20. Izett-Kay ML, Aldabeeb D, Kupelian AS, et al. Long-term mesh complications and reoperation after laparoscopic mesh sacrohysteropexy: a cross-sectional study. Int Urogynecol J. 2020;31(12):2595-2602. doi:10.1007/s00192-020-04396-0.
21. Nightingale G, Phillips C. Long-term safety and efficacy of laparoscopically placed mesh for apical prolapse. Int Urogynecol J. 2021;32(4):871-877. doi:10.1007/s00192-020-04374-6.
22. Arcieri M, Morlacco A, Montebelli F, et al. Sacrocolpopexy after sub-total hysterectomy vs sacral hysteropexy for advanced urogenital prolapse: a propensity-matched study. Int J Gynaecol Obstet. 2023;163(3):847-853. doi:10.1002/ijgo.14959.
23. Barba M, Schivardi G, Manodoro S, Frigerio M. Obstetric outcomes after uterus-sparing surgery for uterine prolapse: a systematic review and meta-analysis. Eur J Obstet Gynecol Reprod Biol. 2021;256:333-338. doi:10.1016/j.ejogrb.2020.11.054.
24. Gopinath D, Yong C, Harding-Forrester S, et al. Laparoscopic and robot-assisted suture versus mesh hysteropexy: a retrospective comparison. Int Urogynecol J. 2023;34(1):105-113. doi:10.1007/s00192-022-05283-6.
25. Chang OH, Carter Ramirez A, Edwards A, et al. The role of uterine preservation at the time of pelvic organ prolapse surgery. Urogynecology (Phila). 2025;31(5):482–495. doi:10.1097/SPV.0000000000001667. AUGS Clinical Practice Statement.
26. Izett-Kay M, Price N. Laparoscopic Sacrohysteropexy. In: Cardozo L, Staskin D, eds. Textbook of Female Urology and Urogynecology. Vol 2: Surgical Perspectives. 5th ed. CRC Press; 2023:1088-1097. doi:10.1201/9781003144243-109
27. Gupta A, Grimes CL, Badlani G, et al. "A global consensus conference on surgical management of primary uterovaginal prolapse and lower urinary tract dysfunction: Combining evidence with expert opinion." Int Urogynecol J. 2026. doi:10.1007/s00192-026-06758-6.
28. Tius V, Arcieri M, Taliento C, et al. "Laparoscopic sacrocolpopexy with concurrent hysterectomy or uterine preservation: A metanalysis and systematic review." Int J Gynaecol Obstet. 2025;168(2):456-471. doi:10.1002/ijgo.15891.
29. National Institute for Health and Care Excellence. "Urinary incontinence and pelvic organ prolapse in women: management." NICE guideline NG123. Published April 2, 2019; updated June 24, 2019. Recommendations.
30. Baessler K, Christmann-Schmid C, Haya N, et al. "Surgery for women with pelvic organ prolapse with or without stress urinary incontinence." Cochrane Database Syst Rev. 2026;2(2):CD013108. doi:10.1002/14651858.CD013108.pub2
31. Qu DC, Chen HB, Yang MM, Zhou HG. "Management of lumbar spondylodiscitis developing after laparoscopic sacrohysteropexy with a mesh: A case report and review of the literature." Medicine (Baltimore). 2019;98(49):e18252. doi:10.1097/MD.0000000000018252
32. Bhatia R, Ahuja A, Siddique M. "Pregnancy After Uterine-Preserving Prolapse Surgery: Obstetric Outcomes and Prolapse Recurrence Following Native Tissue and Mesh-Augmented Repairs." Int Urogynecol J. 2026. doi:10.1007/s00192-026-06812-3