Sacrospinous Ligament Fixation (SSLF)
Sacrospinous ligament fixation suspends the vaginal apex to one or both sacrospinous ligaments using sutures. The uterine-preserving sacrospinous procedure is sacrospinous hysteropexy; adding a prolapse graft changes the procedure and its risk profile.[1]
SSLF offers a vaginal operation without a prolapse mesh implant and can usually be performed without entering the peritoneal cavity. The main decisions are the patient's goals, the compartments requiring repair, prior surgery, vaginal length, and the balance between recurrent prolapse and procedure-specific complications. NICE offers vaginal SSLF with sutures or abdominal or laparoscopic sacrocolpopexy with mesh for vault prolapse after discussion of their benefits and risks.[1][2] For the origin of the operation, see the History of Prolapse Surgery & Urogynecology.
Choosing the Operation
- SSLF or uterosacral suspension: both are established vaginal native-tissue options. OPTIMAL did not demonstrate superior composite success for either operation. Neurologic pain requiring additional treatment was more frequent after SSLF, while intraoperative ureteral obstruction occurred in the uterosacral group.[3][4]
- SSLF or sacrocolpopexy: discuss sacrocolpopexy's greater durability in relevant vault-prolapse evidence alongside its abdominal access, mesh exposure and other procedure-specific risks. The newer ASPIRe trial compared sacrocolpopexy with a native-tissue group that included both SSLF and uterosacral suspension.[2][6]
- Uterine prolapse: decide whether the patient wants uterine preservation and whether uterine or cervical assessment affects that choice. See prolapse repair principles for the SAVE U and other uterine-preservation comparisons.[1][2]
- Concomitant procedures: assess anterior and posterior support, stress incontinence, emptying, bowel symptoms and sexual goals. Agree on a continence strategy before surgery; a native-tissue prolapse repair does not itself require a midurethral sling. See the POP evaluation and management page.[2]
Anatomy and Suture Placement
The sacrospinous ligament extends from the ischial spine toward the lateral sacrum and coccyx. It is closely associated with the coccygeus muscle, but fixation through coccygeus alone is not confirmed SSLF: the ligament must be incorporated. The ischial spine is the palpable lateral landmark.[1][7]
| Structure | Operative implication |
|---|---|
| Pudendal nerve and internal pudendal vessels | Lie close to the ischial spine and lateral ligament; lateral needle passage risks neurovascular injury. |
| Sacral nerve branches supplying coccygeus/levator ani | May cross the region used for fixation, including medial portions of the ligament. Moving medially does not create a nerve-free zone. |
| Superior ligament border and tissues behind it | Sacral nerves and vessels can be very close; control the depth and trajectory of both needle entry and exit. |
| Rectum and pararectal vessels | Identify the operative plane, protect the rectum and maintain exposure during dissection and suture passage. |
Descriptions commonly place sutures approximately 2–3 cm medial to the ischial spine, with variation across techniques. Cadaveric work found substantial variation in ligament thickness and adjacent nerve position; deeply penetrating or superiorly directed bites can capture structures beyond the intended ligament.[1][7][8][10]
For an illustrated procedural orientation, see Figure 5 in the AUGS/IUGA terminology report.[1]
Operative Framework
The following describes a conventional posterior vaginal approach; anterior, apical, left-sided and bilateral approaches are recognized variants.[1]
- Plan exposure and support. Confirm the compartments to repair and the intended vaginal apex. Position in dorsal lithotomy with boot or candy-cane stirrups, protect pressure points and decompress the bladder with a catheter. Ensure adequate lighting, retraction, suction and access to cystoscopy. Prolonged lithotomy is associated with lower-extremity compartment syndrome; in Bauer's retrospective gynecologic survey, 16 of 21 reported cases followed operations longer than 4 hours. Gill et al.'s 2019 guideline (key recommendations 4, 6, 9 and 10) advises limiting uninterrupted leg elevation to 4 hours, followed by at least 15 minutes below heart level. Any postoperative leg pain after pelvic surgery in lithotomy should raise suspicion for well-leg compartment syndrome; suspected cases require immediate orthopaedic or vascular surgery referral, and definite or likely cases require emergency open four-compartment fasciotomy with treatment under way within 1 hour of diagnosis.[23] Fleisch et al.'s 2021 S2k consensus (E.28, E.43 and E.49; consensus ++) advises minimizing lithotomy time and avoiding hip flexion above 90 degrees during longer vaginal procedures, but advises against routine timed leg repositioning.[1][2][15][23][24]
- Develop the posterior plane. Incise the posterior vaginal wall and separate the vaginal wall from the underlying rectovaginal tissue to enter the pararectal space. Identify and protect the rectum while approaching the ischial spine. Exposure should be sufficient to identify the target before passing sutures.[1][7]
- Identify the ligament. Palpate the ischial spine, trace the ligament medially and clear the overlying tissue as needed for controlled visual or palpation-guided placement. Confirm that the fixation incorporates the ligament itself.[1]
- Place suspension sutures. Use a controlled bite in the identified ligament, with attention to adjacent nerves, vessels and penetration depth. The number and material depend on the technique; one to four sutures are described, commonly two. Permanent and delayed-absorbable materials are used. Neither a particular distance nor a suture-capturing device eliminates nerve or vascular risk.[1][7][8]
- Attach the vaginal apex. Incorporate its fibromuscular layer. For permanent sutures, keep the material covered and avoid exposed vaginal epithelial bites; techniques that tie sutures within the vaginal lumen use absorbable material. Assess the suspension before final tying to avoid unnecessary tension, shortening or narrowing. For a prominent enterocele with a foreshortened true apex that will not reach the planned fixation site, Karram describes attaching the vaginal wall over the enterocele to preserve vaginal length.[1][7][17]
- Complete the planned repair. Coordinate anterior, posterior and perineal repairs with apical suspension according to the defects and goals. Confirm hemostasis and exclude rectal penetration, including a digital rectal examination. Close the vaginal incision with the suspension under control.[1][7]
- Check the urinary tract. Perform cystoscopy with inspection of the bladder and urethra and confirmation of bilateral ureteral efflux after reconstructive prolapse surgery. Normal efflux does not exclude every injury, including a delayed injury. The AUGS exception for an isolated posterior repair does not apply to SSLF.[9] When jets are sluggish or absent, removing or revising the SSLF sutures is unlikely to restore them; Dielubanza and Pizarro-Berdichevsky describe retrograde pyelography or ureteral cannulation with a guidewire when hysterectomy has also been performed, and, with a concomitant anterior repair, removing the anterior plication sutures and reassessing for return of efflux.[19]
- Assess recovery. Evaluate pain pattern, bleeding and bladder emptying before discharge, with a documented voiding and catheter plan.[16] A randomized trial of pelvic floor reconstructive surgery that included apical suspension procedures found a day-of-surgery voiding trial did not prolong catheter use compared with a postoperative-day-1 trial.[16] Severe focal buttock, perineal or leg pain, sensory change or weakness warrants prompt assessment rather than reassurance based only on the expectation of temporary postoperative pain.[3][10]
No SSLF-specific VTE recommendation exists; apply the general risk framework (age, obesity, prior VTE, malignancy, prolonged operation or immobility) on the VTE Prophylaxis page.
Suture Devices and Technical Variants
A suture-passing or suture-capturing device can facilitate access in a deep operative field. Comparative device evidence is heterogeneous.[1][7] Karram describes his preferred Capio technique as fingertip-guided placement under direct palpation, passed from the superior side of the coccygeus-sacrospinous complex downward into the perirectal space, with the device positioned about 2–3 cm medial to the ischial spine and approximately 0.5 cm below the superior edge of the coccygeus-sacrospinous complex on the right side.[17]
A retrospective review of 240 women undergoing SSLF found postoperative complications suspected from the suture-passage technique in 18% of the Deschamps-ligature-carrier group (n=173) versus 2% of the direct-visualization group (n=46, p=0.002); the Miya-hook group (n=21) and intraoperative complication rates did not differ significantly among the three techniques.[18]
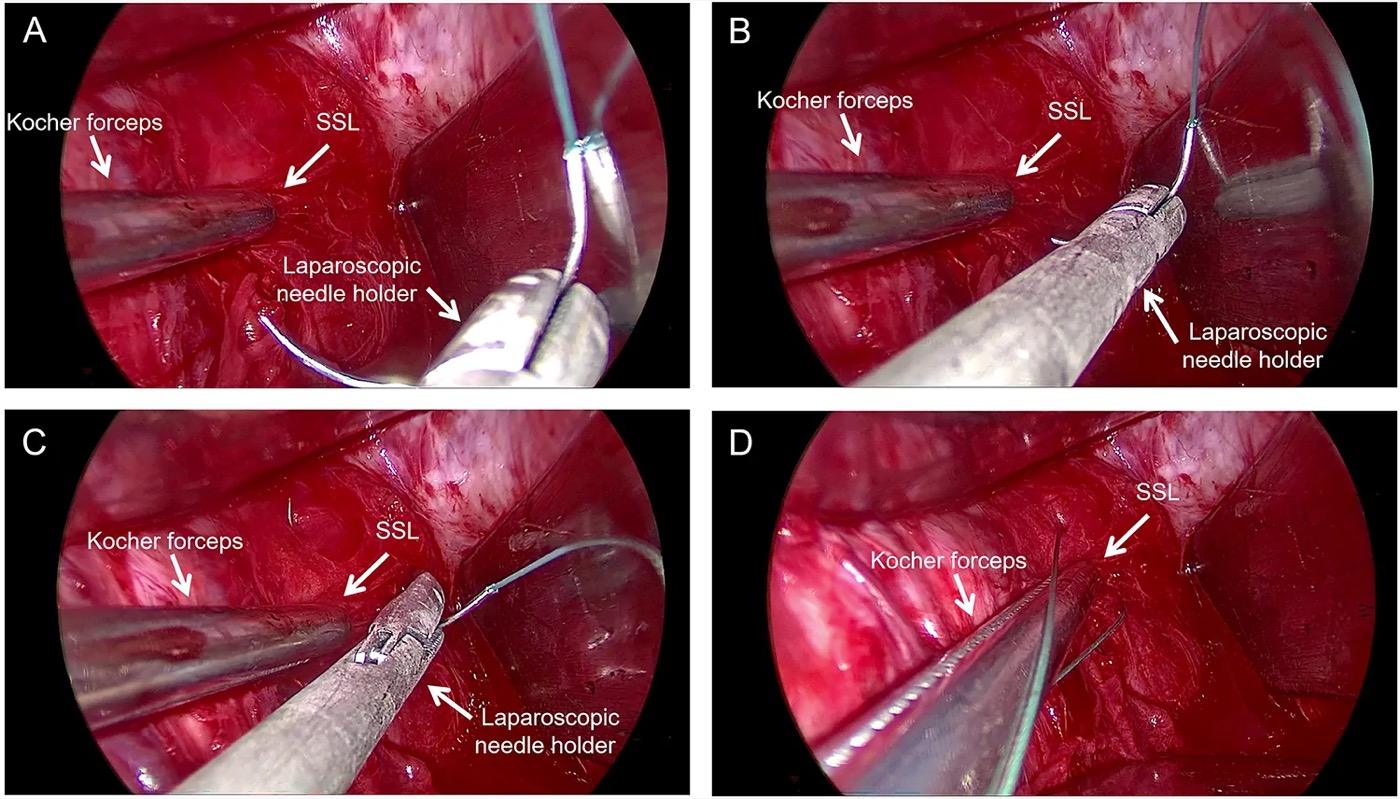
Kocher forceps-guided laparoscopic transvaginal sacrospinous ligament fixation. A, a Kocher forceps grasps the right sacrospinous ligament (SSL) with a laparoscopic needle holder nearby. B-D, sequential suturing of the ligament with the laparoscopic needle holder. From Xue B, et al. Int J Womens Health. 2026;18:623390, Figure 1 (CC BY-NC 4.0).[22]
Outcomes: Use the Trial's Endpoint
OPTIMAL: SSLF Versus Uterosacral Suspension
OPTIMAL randomized 374 women with stage II–IV apical prolapse and demonstrable, symptomatic stress incontinence to uterosacral suspension or SSLF. All were scheduled for a retropubic midurethral sling; 371 actually received one. Women with uterine prolapse underwent concomitant vaginal hysterectomy, so the trial did not test uterine-preserving suspension. Thus, its safety results reflect the combined surgical setting, including concomitant procedures.[3][4]
The corrected two-year composite success endpoint required adequate apical, anterior and posterior support, no bothersome vaginal bulge and no prolapse retreatment. The anatomical criteria included no apical descent greater than one-third of vaginal length and no anterior or posterior wall beyond the hymen.[3][4]
| Corrected two-year outcome | SSLF | Uterosacral suspension |
|---|---|---|
| Composite surgical success | 94/149 (63.1%) | 100/155 (64.5%) [3] |
| Anterior wall beyond the hymen | 20/153 (13.1%) | 20/155 (12.9%) [3] |
| Prolapse retreatment with surgery or pessary | 8/155 (5.2%) | 8/161 (5.0%) [3] |
| Serious adverse event | 31/186 (16.7%) | 31/188 (16.5%) [3] |
| Perioperative neurologic pain requiring additional treatment | 23/186 (12.4%) | 13/188 (6.9%) [3] |
| Intraoperative ureteral obstruction | 0/186 | 6/188 (3.2%) [3] |
The adjusted odds ratio for success was 1.1 (95% CI 0.7–1.7) for uterosacral suspension versus SSLF.[3] Outcome-specific denominators vary because of missing assessments; the ureteral count above comes from the corrected supplement's adverse-event table. One additional delayed ureteral injury occurred in the uterosacral group.[3][4]
E-OPTIMAL: Five-Year Follow-up
Of the original 374 participants, 285 enrolled in the extension and 244 completed it. Modeled five-year first composite failure was 70.3% after SSLF and 61.5% after uterosacral suspension; the adjusted difference for uterosacral suspension minus SSLF was −8.8 percentage points (95% CI −24.2 to 6.6).[5]
The trial counted the first qualifying anatomical finding, bothersome bulge or retreatment as failure and retained that classification thereafter. Prolapse symptom scores remained substantially improved. Discuss anatomical recurrence, current symptoms and retreatment separately.[5]
Comparison With Sacrocolpopexy
ASPIRe (2024) is the higher-yield contemporary vault-prolapse trial: 376 women were randomized, 360 contributed to the primary analysis and 358 to the two superiority comparisons. Three-year modeled composite failure was 28% with sacrocolpopexy versus 43% with vaginal native-tissue repair (adjusted HR 0.57, 99% CI 0.33–0.98; P=.008). Among 134 native-tissue procedures actually performed, including crossovers, 110 (82%) were SSLF and 24 (18%) were uterosacral suspension. The result supports counseling about durability after total-hysterectomy vault prolapse.[6]
The smaller SALTO-2 study randomized 64 women and also followed a separate, self-selected cohort of 115. At 12 months, it detected no difference in its primary disease-specific quality-of-life outcome. Apical composite success in the randomized comparison was 89.3% after laparoscopic sacrocolpopexy versus 86.2% after vaginal SSLF.[11]
Longer-term observational data add context. A 9,681-patient US cohort found fewer reoperations for recurrent prolapse after sacrocolpopexy, but more reoperations for complications; all-cause reoperation was not significantly different between the reconstructive procedures. A 2026 Danish cohort of 1,374 women with prior hysterectomy also found higher long-term reoperation after SSLF, with different results by compartment.[12][13]
In a 2023 Cochrane review, randomized trials of vault prolapse showed more repeat prolapse surgery after a variety of vaginal procedures than after sacral colpopexy (six RCTs, 497 women; follow-up six months to four years; RR 2.33, 95% CI 1.34–4.04; moderate-certainty evidence).[25] This pooled estimate is neither SSLF-specific nor an all-cause reoperation rate.[25] Older pooled comparisons mixed open and laparoscopic sacrocolpopexy, uterine and vault populations, concomitant procedures and varying success definitions. Avoid using their aggregate cure, dyspareunia or complication percentages as a direct prediction for a modern isolated native-tissue SSLF.[14]
Complications and Follow-up
| Problem | Assessment and counseling |
|---|---|
| Buttock, groin or leg pain | Often improves during recovery, but severe, focal, persistent or neurologic symptoms need examination. In OPTIMAL, neurologic pain requiring additional treatment occurred after both procedures, more often after SSLF; 8/186 SSLF participants still had pain at 4–6 weeks. Three of 186 SSLF participants returned to the operating room for suture removal to treat neurologic pain during the perioperative period.[3] |
| Suspected nerve entrapment | Consider the timing, distribution, examination and other causes of pain. Specialist assessment and possible suture removal may be needed. A 2024 French national guideline addressing complications after synthetic-mesh prolapse surgery recommends reoperation for suspension-suture removal when acute sciatic or pudendal neuropathic pain after sacrospinous fixation persists despite level I and II analgesics .[26] Karram describes unilateral vulvar pain or numbness as possible pudendal nerve injury and posterior leg pain as possible sacral-root injury, and recommends immediate reoperation to remove the implicated suture when either is suspected. |
| Hemorrhage or hematoma | Maintain exposure and recognize significant pararectal/neurovascular bleeding promptly. Avoid blind attempts at deep hemostasis; escalate according to the bleeding source and local surgical resources. |
| Urinary tract injury or emptying difficulty | Use the intraoperative cystoscopy and postoperative emptying checks above; assess new urinary symptoms rather than attributing them automatically to the repair. |
| Suture exposure, granulation or dyspareunia | Examine for exposed material, focal tenderness, scarring or excessive narrowing; distinguish these findings from recurrent prolapse and other causes of pelvic pain. |
| Recurrent prolapse | Record the affected compartment, bulge bother, urinary/bowel function and treatment preference. |
These risks and checks are supported by the randomized surgical data, operative consensus and complication literature.[1][2][3][4][7][9][10]
Described first-response bleeding sequences vary by context and are not validated by comparative trial. For bleeding around the coccygeus-sacrospinous complex during fixation, Karram describes initial pressure with a sponge stick held for five minutes by the clock; if bleeding persists, he advises obtaining visualization and considering clips, sutures or thrombin products, noting that abdominal access and selective embolization can be difficult at this location.[17] Roberts and Rogers describe directed sponge compression at the ligament's ischial-spine insertion, with a suggested minimum hold of 10 minutes and limited evidence on duration, drawing on a case-report and literature review of SSLF vascular injury; if bleeding continues, they describe hemostatic agents for venous or capillary oozing, then improved visualization with a narrow malleable or Breisky retractor before suturing or clipping an identified vessel.[20][21] For small venous-plexus bleeding encountered during dissection rather than at fixation, Dielubanza and Pizarro-Berdichevsky describe firm vaginal packing for five minutes, then systematic removal to inspect and cauterize or place hemostatic sutures or clips, followed by correction of the dissection plane once hemostasis is adequate; for suspected major vascular injury not controlled vaginally, they describe considering selective interventional-radiology embolization.[19]
For severe or persistent pain, a selected retrospective referral series of 21 women reported complete relief after suture removal in 12/21 and partial improvement in 8/21. Sutures were removed at a median of 414 days (range 8–1855) after placement, so removal can still help months to years later. Recurrence was assessed only at 6–8 weeks, not long-term. Two women developed new symptomatic prolapse for which further surgery was indicated; one removal caused 520 mL blood loss. These findings support discussing specialist removal when appropriate.[10]
Videos
References
1. Developed by the Joint Writing Group of the American Urogynecologic Society and the International Urogynecological Association. "Joint report on terminology for surgical procedures to treat pelvic organ prolapse." International Urogynecology Journal. 2020;31:429–463. doi:10.1007/s00192-020-04236-1.
2. NICE. "Urinary incontinence and pelvic organ prolapse in women: management." NG123. Recommendations 1.8.10–1.8.16 (uterine and vault prolapse).
3. Barber MD, Brubaker L, Burgio KL, et al. "Comparison of 2 Transvaginal Surgical Approaches and Perioperative Behavioral Therapy for Apical Vaginal Prolapse: The OPTIMAL Randomized Trial." JAMA. 2014;311:1023–1034. doi:10.1001/jama.2014.1719. Corrected article and supplement, June 25, 2015.
4. "Incorrect Outcomes Data." Correction to the OPTIMAL trial. JAMA. 2015. doi:10.1001/jama.2015.4817.
5. Jelovsek JE, Barber MD, Brubaker L, et al. "Effect of Uterosacral Ligament Suspension vs Sacrospinous Ligament Fixation With or Without Perioperative Behavioral Therapy for Pelvic Organ Vaginal Prolapse on Surgical Outcomes and Prolapse Symptoms at 5 Years in the OPTIMAL Randomized Clinical Trial." JAMA. 2018;319:1554–1565. doi:10.1001/jama.2018.2827.
6. Menefee SA, Richter HE, Myers D, et al. "Apical Suspension Repair for Vaginal Vault Prolapse: A Randomized Clinical Trial." JAMA Surgery. 2024;159:845–855. doi:10.1001/jamasurg.2024.1206.
7. Athanasiou S, Prodromidou A, Zacharakis D, et al. "Technical Challenges and Surgical Considerations in Sacrospinous Ligament Fixation for Apical Prolapse Repair." Journal of Clinical Medicine. 2026;15:4209. doi:10.3390/jcm15114209.
8. Florian-Rodriguez ME, Hare A, Chin K, et al. "Inferior Gluteal and Other Nerves Associated With Sacrospinous Ligament: A Cadaver Study." American Journal of Obstetrics and Gynecology. 2016;215:646.e1–646.e6. doi:10.1016/j.ajog.2016.06.025.
9. American Urogynecologic Society. "Consensus Statement: Cystoscopy at the Time of Prolapse Repair." Female Pelvic Medicine & Reconstructive Surgery. 2018;24:258–259. doi:10.1097/SPV.0000000000000529.
10. Vodegel EV, van Delft KWM, Nuboer CHC, et al. "Surgical Management of Pudendal Nerve Entrapment After Sacrospinous Ligament Fixation." BJOG. 2022;129:1908–1915. doi:10.1111/1471-0528.17145.
11. van Oudheusden AMJ, van IJsselmuiden MN, Menge LF, et al. "Laparoscopic Sacrocolpopexy Versus Vaginal Sacrospinous Fixation for Vaginal Vault Prolapse: A Randomised Controlled Trial and Prospective Cohort (SALTO-2 Trial)." BJOG. 2023;130:1542–1551. doi:10.1111/1471-0528.17525.
12. Shah NM, Berger AA, Zhuang Z, et al. "Long-Term Reoperation Risk After Apical Prolapse Repair in Female Pelvic Reconstructive Surgery." American Journal of Obstetrics and Gynecology. 2022;227:306.e1–306.e16. doi:10.1016/j.ajog.2022.05.046.
13. Teilmann-Jørgensen D, Gommesen D, Wu C, et al. "Long-Term Risk of Reoperation After Vaginal Vault Suspension by Surgical Technique: A Nationwide Cohort Study." BJOG. 2026;133:1046–1055. doi:10.1111/1471-0528.70138.
14. Zhang W, Cheon WC, Zhang L, et al. "Comparison of the Effectiveness of Sacrospinous Ligament Fixation and Sacrocolpopexy: A Meta-Analysis." International Urogynecology Journal. 2022;33:3–13. doi:10.1007/s00192-021-04823-w.
15. Bauer EC, Koch N, Erichsen CJ, et al. "Survey of Compartment Syndrome of the Lower Extremity After Gynecological Operations." Langenbecks Arch Surg. 2014;399(3):343-8. doi:10.1007/s00423-014-1172-z
16. Carter-Brooks CM, Zyczynski HM, Moalli PA, Brodeur PG, Shepherd JP. "Early Catheter Removal After Pelvic Floor Reconstructive Surgery: A Randomized Trial." Int Urogynecol J. 2018;29(8):1203-1212. doi:10.1007/s00192-018-3641-3
17. Karram MM. Vaginal Native Tissue Suture Repair of Vaginal Vault Prolapse. In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:671-704.
18. Pollak J, Takacs P, Medina C. "Complications of Three Sacrospinous Ligament Fixation Techniques." International Journal of Gynaecology and Obstetrics. 2007;99(1):18-22. doi:10.1016/j.ijgo.2007.04.028.
19. Dielubanza E, Pizarro-Berdichevsky J. Sacrospinous Ligament Suspension. In: Goldman HB, ed. Complications of Female Incontinence and Pelvic Reconstructive Surgery. 2nd ed. Springer (Humana Press); 2017:85-90. doi:10.1007/978-3-319-49855-3_8
20. Roberts BL, Rogers RG. Genital Tract Prolapse. In: Hoffman M, Hull TL, Bochner BH, eds. Major Complications of Female Pelvic Surgery: A Multidisciplinary Approach. Springer; 2025:73-80. doi:10.1007/978-3-031-66772-5_7
21. Pahwa AK, Arya LA, Andy UU. "Management of Arterial and Venous Hemorrhage During Sacrospinous Ligament Fixation: Cases and Review of the Literature." International Urogynecology Journal. 2016;27(3):387-391. doi:10.1007/s00192-015-2818-2.
22. Xue B, Huang X, Zhou Y, Zhu Q. "A Pilot Study of Kocher Forceps-Guided Laparoscopic Transvaginal Sacrospinous Ligament Fixation: Technique and Initial Clinical Experience." International Journal of Women's Health. 2026;18:623390. doi:10.2147/IJWH.S623390.
23. Gill M, Fligelstone L, Keating J, et al. "Avoiding, Diagnosing and Treating Well Leg Compartment Syndrome After Pelvic Surgery." Br J Surg. 2019;106(9):1156-1166. doi:10.1002/bjs.11177.
24. Fleisch MC, Bader W, Balzer K, et al. "The Prevention of Positioning Injuries During Gynecologic Surgery. Guideline of the DGGG, OEGGG and SGGG (S2k Level, AWMF Registry Number 015/077, October 2020)." Geburtshilfe Frauenheilkd. 2021;81(4):447-468. doi:10.1055/a-1378-4209.
25. Maher C, Yeung E, Haya N, et al. "Surgery for women with apical vaginal prolapse." Cochrane Database Syst Rev. 2023;2023(7):CD012376. doi:10.1002/14651858.CD012376.pub2
26. Deffieux X, Perrouin-Verbe MA, Campagne-Loiseau S, et al. "Diagnosis and management of complications following pelvic organ prolapse surgery using a synthetic mesh: French national guidelines for clinical practice." Eur J Obstet Gynecol Reprod Biol. 2024;294:170–179. doi:10.1016/j.ejogrb.2024.01.015