Uterosacral Ligament Suspension (USLS)
USLS is a native-tissue operation that supports the vaginal apex from the uterosacral ligaments, usually bilaterally. It can accompany hysterectomy for prolapse or repair an existing vaginal vault prolapse. Uterine-preserving variants require a separate operative plan. The central safety issues are ureteral obstruction and injury to adjacent nerves, vessels or rectum.[1][3][4] USLS can cause buttock or leg pain.[1][3][4]
For overall procedure selection and nonsurgical options, see Prolapse Repair Principles.
Choosing USLS
USLS is reasonable when a patient wants a reconstructive repair without a prolapse mesh implant and the ligaments can be identified and used safely. Selection depends on symptoms, compartment defects, previous surgery, tissue accessibility, medical fitness and patient priorities.
| Alternative | How to frame the discussion |
|---|---|
| Sacrospinous ligament fixation | OPTIMAL did not detect superior composite success for either vaginal repair. The complication patterns differ. |
| Sacrocolpopexy | A 2023 review of seven randomized trials, most involving posthysterectomy vault prolapse, found less prolapse awareness, repeat prolapse surgery and recurrent prolapse on examination after sacrocolpopexy than after mixed vaginal repairs over six months to four years.[41] Sacrocolpopexy adds an abdominal operation and mesh-related risks. |
| Uterine preservation | Before hysterectomy consent, discuss the benefits and risks of hysterectomy and uterine-preserving repair, offering preservation as an option unless contraindicated; explain continued cervical screening and evaluation of abnormal uterine bleeding.[42] At 10 years in SAVE-U, which enrolled women with stage 2 or greater uterine prolapse and no previous pelvic-floor surgery, apical failure (stage 2 or greater descent with bothersome bulge symptoms, or repeat apical surgery) occurred in 3/44 after sacrospinous hysteropexy and 7/49 after vaginal hysterectomy with USLS; only 93/208 randomized women had long-term follow-up, and the difference was not statistically clear.[43] Uterosacral hysteropexy is a separate operation. |
| McCall culdoplasty | Provides apical support and cul-de-sac management during vaginal hysterectomy. The precise distinction from high USLS depends on the operative modification used. |
These choices should incorporate the patient's preference about mesh, uterine retention, vaginal function and the possibility of later retreatment.[1][2][8][9][15][20]
Anatomy and safe fixation
The uterosacral complex is a visceral support structure containing connective tissue, vessels, fat and autonomic nerves. It is not an isolated cord with a uniform attachment to sacral bone. Its deep portion is closely related to the pelvic plexus; sacral nerve trunks lie beneath the posterior and intermediate region. The rectum is medial and the ureter is generally anterolateral.[3][4]
The ischial spine helps orient the surgeon to the intermediate ligament. Buller's original cadaver study specifically cautioned against using the spine as a fixed measuring point because ligament width and position vary.[3]
| Relationship | Operative implication |
|---|---|
| Ureter nearer the cervical end | Low or anterior fixation can capture or distort the ureter. Traction can kink it even when the needle does not directly penetrate it. |
| Neural structures deep to the ligament | Deep or lateral passes into the pelvic sidewall can entrap sacral or autonomic nerves. |
| Rectum medial to the support complex | Identify the tissue being incorporated and protect the rectal wall; avoid blind posterior or medial passes. |
| Variable ligament appearance after prolapse or previous surgery | Obtain adequate exposure and identify the actual ligament. Change the plan if its course and neighboring structures cannot be established safely. |
These principles come from anatomical studies and surgical descriptions; no measured offset guarantees freedom from ureteral or nerve injury.[3][4]
Karram describes a modified high USLS as his preferred vaginal technique: two or three delayed-absorbable sutures are placed in the uppermost uterosacral ligament, medial and slightly cephalad to the ischial spine, with the bite possibly including the coccygeus-sacrospinous complex, and in large anterior prolapse one set is brought through the proximal anterior vaginal wall. He reports palpating the ureter 1–5 cm ventral and lateral to the spine and states that this technique creates a deeper vagina and reduces ureteral compromise, without supplying a patient count, complication rate or comparison.[25]
A cadaveric study of uterosacral ligament suspension in 10 unembalmed specimens found sacral nerve roots encircled by the suspension suture in 7 of 10 cadavers. No nerve entrapment occurred when the suture was placed while the ligament was tented ventrally with an Allis clamp, whereas a dorsal-and-posterior needle arc entrapped a nerve in 6 of 10 cadavers regardless of needle size.[26] This anatomic study establishes a mechanism and a technique associated with fewer cadaveric entrapments.
Operative framework
Vaginal intraperitoneal suspension
The AUGS/IUGA terminology report distinguishes ipsilateral fixation from midline plication of the uterosacral ligaments. Both require actual ligament incorporation; simply closing peritoneum or reattaching the cuff to distal cut ligament ends is not the same high suspension.[22]
Shull and colleagues (2000) described transvaginal native-tissue repair of apical and associated support defects with the uterosacral ligaments in 302 consecutive women operated on from 1994 to 1998, graded with the Baden-Walker halfway system. Of 289 (96%) with at least one postoperative visit, 251 (87%) had no persistent or recurrent defect at any site and 14 (5%) had grade 2 or greater defects; the anterior segment was the least durable site. Transfusion and ureteral injury or kinking each occurred in 1%, and postoperative death in 0.3%.[35]
The sequence below describes the decisions in a high vaginal vault suspension. Details depend on previous hysterectomy, associated repairs and the selected technique.[1][3][7][22]
- Confirm the agreed operation. Perform hysterectomy only when it is part of the treatment plan. Establish safe access to the cul-de-sac and adequate exposure; account for adhesions and previous repairs.
- Identify both uterosacral ligaments and adjacent structures. Use palpation, visualization and appropriate retraction. The ischial spine is an orientation landmark.
- Place controlled suspension sutures in identified ligament tissue. The terminology report describes posteromedial ligament incorporation proximal to the ischial-spine level. Avoid incorporating the lateral pelvic wall or taking blind deep passes. Protect the ureter, rectum and nearby nerves. Published techniques use different suture numbers and materials.
- Attach the sutures to adequate apical supportive tissue. Incorporate the relevant vaginal fibromuscular or fascial layers. Keep permanent material away from exposed vaginal epithelium. Choose cuff closure and tissue purchase appropriate to the suture material.[22]
- Restore bilateral support without excessive tension. Coordinate apical suspension, cuff closure, enterocele management and clinically indicated compartment repairs. Assess the resulting vaginal length, caliber and axis. When an enterocele sac is closed at the same operation, Sussman and colleagues describe placing both uterosacral suspension sutures under direct visualization before closing the sac, then plicating the central pubocervical and/or rectovaginal fascia and passing the double-armed suspension sutures through the plicated fascia before tying them to resuspend the apex. This is the chapter authors' described sequence, without a stated advantage over other sequencing.[32]
- Perform cystoscopy after the final suspension and relevant repairs. Inspect the bladder and urethra and confirm bilateral ureteral efflux. If further suturing could alter ureteral patency, reassess after that step.[5][16] Cystoscopy with the sutures under tension before cuff closure had 50% sensitivity (95% CI 1.26–98.74) for obstruction among the 40 of 551 patients in whom this maneuver was used in one retrospective cohort, although a normal result was reassuring.[5][16]
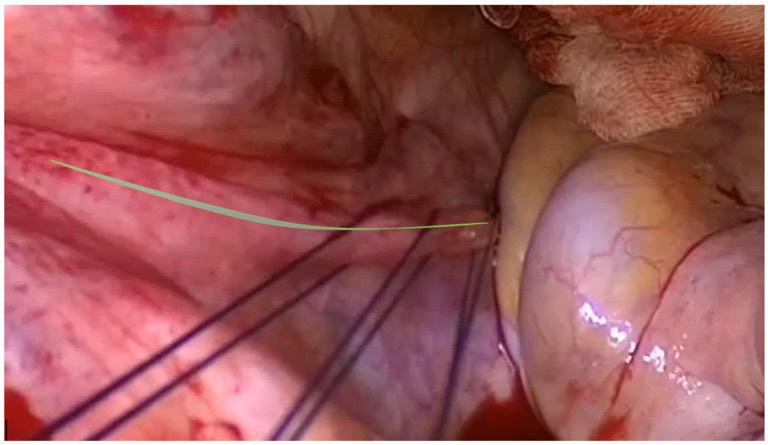
High uterosacral ligament transfixion on the right side (green line), photographed through a laparoscopic camera introduced by the vaginal route for teaching purposes. From Barba M, et al. Healthcare. 2026;14(15):2399, Figure 1 (CC BY 4.0).[33]
Suture choice
Permanent and delayed-absorbable sutures are both used; there is no single mandatory count or material for every USLS. A 2023 systematic review found no clear difference in medium-term success between materials across native vaginal suspensions, but the evidence combines USLS and SSLF, varied techniques and mostly nonrandomized studies. Permanent sutures carry exposure or granulation considerations.[6]
The long-term Cola series used two or three delayed-absorbable monofilament sutures on each side.[7]
Extraperitoneal suspension
An extraperitoneal approach reaches the support complex without opening the peritoneal cavity vaginally. It requires specific familiarity with the pararectal dissection and protection of the urinary tract.[13][14]
Karmakar's observational series included 472 women with posthysterectomy vault prolapse, many with previous prolapse surgery. At mean follow-up of approximately five years, objective vault-support success was 420/472 (89%). Among 138 women who had mesh augmentation, 17% had mesh exposure.[13] The same series reported a 1% ureteral-injury rate, with injuries occurring mainly early in the series. There was no randomized comparison establishing superiority or elimination of ureteral risk.[13]
Laparoscopic, robotic and vNOTES approaches
Laparoscopy permits magnified identification of the ureter and access to the retroperitoneal anatomy. Common descriptions of laparoscopic or open USLS include mobilizing the ureter laterally away from planned suture sites; careful dissection, avoidance of thermal injury and final cystoscopy remain necessary.[22][5]
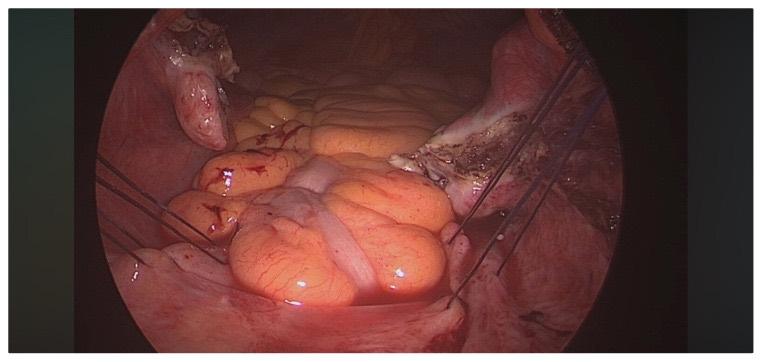
vNOTES high uterosacral ligament suspension: bilateral nonabsorbable sutures placed near the intermediate portions of the uterosacral ligaments at the level of the ischial spine, four stitches in total. From Adan R, et al. Turk J Med Sci. 2026;56(3):838-846, Figure (CC BY 4.0).[34]
Vermeulen's 2023 review included 13 nonrandomized cohorts with 933 patients and an average follow-up of 22 months.[10] Its 90.2% pooled success estimate, based on 10 studies with 654 patients, referred to apical anatomical support, with substantial heterogeneity.[10]
Comparative reviews published in 2024 and 2025 suggest possible advantages of laparoscopic approaches for some recurrence or perioperative outcomes. Their conclusions remain limited by observational evidence, different concomitant hysterectomy and repair patterns and short or variable follow-up.[11][12]
For an abdominally approached suspension, Whiteside and Karram describe applying outward traction to the lateral vaginal-cuff edges at approximately 30 degrees from horizontal with the patient supine to tension and expose the uterosacral ligaments, using vaginal examination to help estimate the ischial-spine level when it is uncertain from above.[27]
Positioning and Room Setup
The vaginal approach uses dorsal lithotomy with boot or candy-cane stirrups; laparoscopic, robotic and vNOTES approaches may use Trendelenburg for exposure.[36][37] Prolonged lithotomy is associated with lower-extremity compartment syndrome: a 2014 survey found 21 cases, all in lithotomy and 16 after operations longer than 4 hours, while responding departments lacked a common prevention protocol. The 2021 S2k gynecologic positioning guideline advises minimizing time in lithotomy and Trendelenburg, avoiding hip flexion beyond 90 degrees during longer vaginal operations, and assessing postoperative symptoms promptly after lengthy procedures.[23][38] A urethral catheter is placed to decompress the bladder for dissection and the final cystoscopic ureteral-efflux check. In a 57-patient randomized trial including apical and obliterative procedures, a day-of-surgery voiding trial did not significantly shorten time to spontaneous void in the intention-to-treat analysis (15.9 versus 28.4 hours; P=.081); adjusted and per-protocol analyses favored earlier testing, which did not prolong catheter use.[24] No USLS-specific VTE recommendation exists; apply the general risk framework (age, obesity, prior VTE, malignancy, prolonged operation or immobility) on the VTE Prophylaxis page.
Ureteral assessment and complications
AUGS recommends cystoscopy for prolapse reconstructive surgery except operations confined to the posterior compartment. USLS requires assessment of bilateral ureteral efflux after repair. Visualization of the ureter or apparent peristalsis during laparoscopy is not an equivalent test of drainage into the bladder.[5]
If efflux is absent or concerning, first establish a clear view of both orifices and consider urine output, visualization and possible anatomical variation. Investigate obstruction promptly. When a suspension or anterior-repair suture is implicated, release or revise it and repeat the assessment. For uterosacral suspension specifically, one chapter describes releasing the ipsilateral sutures sequentially, beginning with the most distal suture and proceeding medially, then repeating cystoscopy; a released stitch can be replaced more medially if needed.[28] A 983-patient single-center retrospective review of uterosacral colpopexy found that among patients requiring unilateral suture removal to resolve ureteral kinking, 63.6% did not undergo suture replacement, and nonreplacement was not associated with a higher rate of recurrent prolapse.[29] Persistent concern requires further urinary-tract evaluation and appropriate urologic assistance; do not finish the case with unexplained suspected obstruction.[5][17]
New flank pain, fever, oliguria or anuria, renal dysfunction or suspicious vaginal urinary leakage warrants prompt investigation even after intraoperative efflux was seen.[5][17]
| Complication | Evidence and practical response |
|---|---|
| Ureteral obstruction | OPTIMAL recorded six intraoperative obstructions among 188 women assigned USLS (3.2%): five resolved by suture removal and one needed a stent. None occurred with SSLF. One further ureteral injury was recognized after surgery.[1] In a 551-patient single-center cohort, 4.3% had obstruction on cystoscopy and 0.4% a delayed injury.[16] Rates vary with setting and definition. |
| Buttock, groin or leg pain | OPTIMAL recorded new neurologic pain requiring additional treatment in 13/188 USLS patients (6.9%) and 23/186 SSLF patients (12.4%). It was still present at the 4–6-week visit in 1 USLS versus 8 SSLF patients.[1] New severe buttock or posterior-thigh pain, numbness or weakness soon after USLS warrants prompt assessment for suture-related neuropathy and close follow-up. If entrapment is suspected, consider early removal of the implicated ipsilateral suture; selected retrospective patients improved after removal, while others were managed medically.[39][40] |
| Suture exposure or granulation | Can cause bleeding, discharge or discomfort. Examine the cuff and assess exposed material; a native-tissue prolapse repair can still have suture complications. |
| Rectal or vascular injury | Protect the structures adjoining the ligament and reassess if dissection, bleeding or needle passage raises concern. |
| Voiding dysfunction or incontinence | Assess postoperative emptying and symptoms. Concomitant continence surgery changes the risk profile and should be considered separately from apical support. A 484-patient comparison of prolapse-repair routes found postoperative urinary retention, defined by failure of the postoperative retrograde-fill voiding trial, in 128 patients (26.4%): 113 of 333 after transvaginal high USLS versus 15 of 151 after robotic sacrocolpopexy (odds ratio 3.26, 95% CI 1.72–6.18); older age was also associated with retention (OR 1.03 per year, 95% CI 1.01–1.05). Keep the procedure mix and retention definition attached to this figure.[30] |
The OPTIMAL pain outcome required altered care;many participants also underwent hysterectomy and a retropubic midurethral sling.[1][4][6]
Cystoscopic adjuncts may help show efflux, but agent selection follows patient factors and institutional protocols. In a 925-patient historical cohort comparing different calendar periods, mannitol bladder distension was associated with fewer postoperative unrecognized ureteral injuries than saline; delayed obstruction occurred in the mannitol group.[17] Intravenous sodium fluorescein (10% solution, 0.25–1 mL) is another reported option for prompt, visible ureteral efflux; the ureteral orifices should be identified before it is given, because fluorescent urine can rapidly opacify the bladder and obscure them.[31]
Outcomes: keep the endpoint and population visible
Randomized vaginal-repair evidence
| Study | Result | Interpretation |
|---|---|---|
| OPTIMAL, corrected two-year analysis | Composite success: 100/155 (64.5%) USLS versus 94/149 (63.1%) SSLF; adjusted OR 1.1, 95% CI 0.7–1.7. | Neither procedure was superior in this trial. The composite required anatomical support, absence of bothersome bulge and no retreatment.[1] |
| E-OPTIMAL, five-year extension | Estimated first composite failure: 61.5% USLS versus 70.3% SSLF; adjusted difference −8.8 percentage points, 95% CI −24.2 to 6.6. | No statistically clear difference. The endpoint counted a first failure even if later symptoms or anatomy improved.[2] |
OPTIMAL enrolled women with apical prolapse and stress urinary incontinence, with planned concomitant retropubic sling surgery. E-OPTIMAL enrolled 285 of the original participants and 244 completed extended follow-up. Symptom improvement persisted despite the increasing cumulative composite-failure estimates.[1][2]
The ASPIRe trial also informs counseling for selected women with posthysterectomy vault prolapse: sacrocolpopexy had lower adjusted composite failure than its native-tissue group. The latter included both USLS and SSLF. See Sacrocolpopexy for the trial population and full comparison.[21]
Long-term cohort evidence
Cola and colleagues evaluated 287 women at approximately ten years after vaginal hysterectomy with high USLS. There were 55 anatomical recurrences, 18 reports of bulge symptoms and six repeat prolapse operations. The anatomical definition included stage II or greater prolapse in any compartment. Of 353 eligible women, 66 were lost to long-term follow-up.[7]
Premenopausal status and concomitant compartment repair were associated with outcomes in that cohort.[7]
Large observational reoperation studies add longer follow-up but measure a different outcome from anatomical recurrence. Shah's nearly 10,000-patient cohort found lower recurrence-related reoperation after sacrocolpopexy, while all-cause reoperation was not clearly different among reconstructive procedures. A 2026 Danish cohort likewise reported compartment-specific differences across techniques, with selection and residual confounding remaining important.[18][19]
Comparison with sacrocolpopexy
In Lavelle's retrospective cohort, stage III recurrence was more frequent after USLS than sacrocolpopexy. Stage II events were few, and only eight stage IV patients underwent USLS. Follow-up duration and patient characteristics differed between groups. These findings support a discussion about durability.[8]
Campagna's matched retrospective comparison also favored laparoscopic sacrocolpopexy for all-compartment anatomical success. The groups still differed in compartment severity, hysterectomy type and associated repairs.[9]
Follow-up and operative documentation
Record the route, ligament identification, suture material and configuration, attachment sites, concomitant procedures, final support and urinary-tract assessment. Document any released or replaced sutures and the findings after reassessment.
At follow-up, assess bulge symptoms, vaginal support, voiding and bowel symptoms, pain, vaginal healing and sexual-function concerns. Explain that an examination finding, bothersome recurrence, pessary treatment and repeat surgery are separate outcomes.[1][2][7] Manage recurrent prolapse according to symptoms, anatomy and patient goals.[1][2][7]
Videos
References
1. Barber MD, Brubaker L, Burgio KL, et al. "Comparison of 2 Transvaginal Surgical Approaches and Perioperative Behavioral Therapy for Apical Vaginal Prolapse: The OPTIMAL Randomized Trial." JAMA. 2014;311(10):1023-1034. doi:10.1001/jama.2014.1719 Corrected June 2015; correction notice.
2. Jelovsek JE, Barber MD, Brubaker L, et al. "Effect of Uterosacral Ligament Suspension vs Sacrospinous Ligament Fixation With or Without Perioperative Behavioral Therapy for Pelvic Organ Vaginal Prolapse on Surgical Outcomes and Prolapse Symptoms at 5 Years in the OPTIMAL Randomized Clinical Trial." JAMA. 2018;319(15):1554-1565. doi:10.1001/jama.2018.2827
3. Buller JL, Thompson JR, Cundiff GW, et al. "Uterosacral Ligament: Description of Anatomic Relationships to Optimize Surgical Safety." Obstetrics & Gynecology. 2001;97(6):873-879. doi:10.1016/S0029-7844(01)01346-1
4. Ramanah R, Berger MB, Parratte BM, DeLancey JO. "Anatomy and Histology of Apical Support: A Literature Review Concerning Cardinal and Uterosacral Ligaments." International Urogynecology Journal. 2012;23(11):1483-1494. doi:10.1007/s00192-012-1819-7
5. Cohen SA, Carberry CL, Smilen SW. "American Urogynecologic Society Consensus Statement: Cystoscopy at the Time of Prolapse Repair." Female Pelvic Medicine & Reconstructive Surgery. 2018;24(4):258-259. doi:10.1097/SPV.0000000000000529
6. Pollack BL, Popiel P, Toaff MC, et al. "Permanent Compared With Absorbable Suture in Apical Prolapse Surgery: A Systematic Review and Meta-analysis." Obstetrics & Gynecology. 2023;141(2):268–283. doi:10.1097/AOG.0000000000005032
7. Cola A, Marino G, Milani R, et al. "Native-Tissue Prolapse Repair: Efficacy and Adverse Effects of Uterosacral Ligaments Suspension at 10-Year Follow Up." International Journal of Gynecology & Obstetrics. 2022;159(1):97-102. doi:10.1002/ijgo.14096
8. Lavelle ES, Giugale LE, Winger DG, et al. "Prolapse Recurrence Following Sacrocolpopexy vs Uterosacral Ligament Suspension: A Comparison Stratified by Pelvic Organ Prolapse Quantification Stage." American Journal of Obstetrics and Gynecology. 2018;218(1):116.e1-116.e5. doi:10.1016/j.ajog.2017.09.015
9. Campagna G, Vacca L, Panico G, et al. "Laparoscopic High Uterosacral Ligament Suspension vs. Laparoscopic Sacral Colpopexy for Pelvic Organ Prolapse: A Case-Control Study." Frontiers in Medicine. 2022;9:853694. doi:10.3389/fmed.2022.853694
10. Vermeulen CKM, Schuurman B, Coolen AWM, et al. "The Effectiveness and Safety of Laparoscopic Uterosacral Ligament Suspension: A Systematic Review and Meta-Analysis." BJOG. 2023;130(13):1568-1578. doi:10.1111/1471-0528.17565
11. Douligeris A, Kathopoulis N, Zachariou E, et al. "Laparoscopic Versus Vaginal Uterosacral Ligament Suspension in Women With Pelvic Organ Prolapse: A Systematic Review and Meta-Analysis of the Literature." Journal of Minimally Invasive Gynecology. 2024;31(6):477-487. doi:10.1016/j.jmig.2024.03.007
12. Azadi A, Ulibarri H, Arroyo A, et al. "Meta-Analysis of Laparoscopic Versus Vaginal Uterosacral Ligament Suspension." Journal of Minimally Invasive Gynecology. 2025;32(10):877–888. doi:10.1016/j.jmig.2025.07.001
13. Karmakar D, Dwyer PL, Thomas E, Schierlitz L. "Extraperitoneal Uterosacral Suspension Technique for Post Hysterectomy Apical Prolapse in 472 Women: Results From a Longitudinal Clinical Study." BJOG. 2019;126(4):536-542. doi:10.1111/1471-0528.15560
14. Ow LL, Walsh CE, Rajamaheswari N, Dwyer PL. "Technique of Extraperitoneal Uterosacral Ligament Suspension for Apical Suspension." International Urogynecology Journal. 2016;27(4):637-639. doi:10.1007/s00192-015-2873-8
15. Meriwether KV, Antosh DD, Olivera CK, et al. "Uterine Preservation vs Hysterectomy in Pelvic Organ Prolapse Surgery: A Systematic Review With Meta-Analysis and Clinical Practice Guidelines." American Journal of Obstetrics and Gynecology. 2018;219(2):129-146.e2. doi:10.1016/j.ajog.2018.01.018
16. Chang OH, Tewari S, Sun JY, Ferrando CA. "Risk Factors for Ureteral Obstruction and the Diagnostic Value of the 'Cysto-Under-Tension' Technique at the Time of Uterosacral Colpopexy." International Urogynecology Journal. 2021;32(11):2985-2992. doi:10.1007/s00192-020-04650-5
17. Barba M, Cola A, Costa C, Frigerio M. "Impact of Mannitol Bladder Distension in the Intraoperative Detection of Ureteral Kinking During Pelvic Floor Surgery." International Urogynecology Journal. 2024;35(3):689-694. doi:10.1007/s00192-024-05745-z
18. Shah NM, Berger AA, Zhuang Z, Tan-Kim J, Menefee SA. "Long-Term Reoperation Risk After Apical Prolapse Repair in Female Pelvic Reconstructive Surgery." American Journal of Obstetrics and Gynecology. 2022;227(2):306.e1-306.e16. doi:10.1016/j.ajog.2022.05.046
19. Teilmann-Jorgensen D, Gommesen D, Wu C, Klarskov N, Rudnicki M. "Long-Term Risk of Reoperation After Vaginal Vault Suspension by Surgical Technique: A Nationwide Cohort Study." BJOG. 2026;133(5):1046-1055. doi:10.1111/1471-0528.70138
20. Spelzini F, Frigerio M, Manodoro S, et al. "Modified McCall Culdoplasty Versus Shull Suspension in Pelvic Prolapse Primary Repair: A Retrospective Study." International Urogynecology Journal. 2017;28(1):65-71. doi:10.1007/s00192-016-3016-6
21. Menefee SA, Richter HE, Myers D, et al. "Apical Suspension Repair for Vaginal Vault Prolapse: A Randomized Clinical Trial." JAMA Surgery. 2024;159(8):845–855. doi:10.1001/jamasurg.2024.1206
22. Developed by the Joint Writing Group of the American Urogynecologic Society and the International Urogynecological Association. "Joint Report on Terminology for Surgical Procedures to Treat Pelvic Organ Prolapse." International Urogynecology Journal. 2020;31:429–463. doi:10.1007/s00192-020-04236-1.
23. Bauer EC, Koch N, Erichsen CJ, et al. "Survey of Compartment Syndrome of the Lower Extremity After Gynecological Operations." Langenbecks Arch Surg. 2014;399(3):343-8. doi:10.1007/s00423-014-1172-z
24. Carter-Brooks CM, Zyczynski HM, Moalli PA, Brodeur PG, Shepherd JP. "Early Catheter Removal After Pelvic Floor Reconstructive Surgery: A Randomized Trial." Int Urogynecol J. 2018;29(8):1203-1212. doi:10.1007/s00192-018-3641-3
25. Karram MM. Vaginal Native Tissue Suture Repair of Vaginal Vault Prolapse. In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:671-704.
26. Siddiqui NY, Mitchell TRT, Bentley RC, Weidner AC. "Neural Entrapment During Uterosacral Ligament Suspension: An Anatomic Study of Female Cadavers." Obstetrics & Gynecology. 2010;116(3):708-713. doi:10.1097/AOG.0b013e3181ec658a
27. Whiteside JL, Karram MM. Native Tissue Suture Repair of Vaginal Vault Prolapse: Laparoscopic, Robotic, and Open Abdominal Approaches. In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:481-488.
28. Roberts BL, Rogers RG. Genital Tract Prolapse. In: Hoffman M, Hull TL, Bochner BH, eds. Major Complications of Female Pelvic Surgery: A Multidisciplinary Approach. Springer; 2025:73-80. doi:10.1007/978-3-031-66772-5_7
29. Unger CA, Walters MD, Ridgeway B, Jelovsek JE, Barber MD, Paraiso MF. "Incidence of Adverse Events After Uterosacral Colpopexy for Uterovaginal and Posthysterectomy Vault Prolapse." American Journal of Obstetrics and Gynecology. 2015;212(5):603.e1-603.e7. doi:10.1016/j.ajog.2014.11.034
30. Yune JJ, Cheng JW, Wagner H, Kim J, Hardesty JS, Siddighi S. "Postoperative Urinary Retention After Pelvic Organ Prolapse Repair: Vaginal Versus Robotic Transabdominal Approach." Neurourology and Urodynamics. 2018;37(5):1794-1800. doi:10.1002/nau.23526
31. Doyle PJ, Lipetskaia L, Duecy E, Buchsbaum G, Wood RW. "Sodium Fluorescein Use During Intraoperative Cystoscopy." Obstetrics & Gynecology. 2015;125(3):548-550. doi:10.1097/AOG.0000000000000675
32. Sussman RD, Brown ET, Dmochowski RR. Enterocele Repair. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:700-705.
33. Barba M, Cola A, Melocchi T, De Vicari D, Frigerio M. "Focused Training in Pelvic Floor Surgery: A CUSUM Analysis of the Learning Curve in Uterosacral Ligament Suspension." Healthcare. 2026;14(15):2399. doi:10.3390/healthcare14152399
34. Adan R, Şahin F, Üskent U, Çulha MG, Tekin AB. "vNOTES High Uterosacral Ligament Suspension Versus Laparoscopic Lateral Suspension in the Management of Vaginal Vault Prolapse: Initial Experience in a Single Tertiary Center." Turkish Journal of Medical Sciences. 2026;56(3):838-846. doi:10.55730/1300-0144.6218
35. Shull BL, Bachofen C, Coates KW, Kuehl TJ. "A Transvaginal Approach to Repair of Apical and Other Associated Sites of Pelvic Organ Prolapse With Uterosacral Ligaments." American Journal of Obstetrics and Gynecology. 2000;183(6):1365-1374. doi:10.1067/mob.2000.110910
36. Jaresova A, Warda H, Macharia A, Hacker MR, Li J. "Comparison of Trendelenburg Angles in Vaginal, Laparoscopic, and Robotic Uterovaginal Apical Prolapse Repairs." J Minim Invasive Gynecol. 2021;28(11):1868-1875. doi:10.1016/j.jmig.2021.04.001.
37. Ba Khamis F, Bashir H, Manea H, Margossian H. "Successful Vaginal Natural Orifice Transluminal Endoscopic Surgery (V-NOTES) Hysterectomy Under Spinal Anesthesia for an Obese Patient." Cureus. 2025;17(11):e97149. doi:10.7759/cureus.97149.
38. Fleisch MC, Bader W, Balzer K, et al. "The Prevention of Positioning Injuries During Gynecologic Surgery. Guideline of the DGGG, OEGGG and SGGG (S2k Level, AWMF Registry Number 015/077, October 2020)." Geburtshilfe Frauenheilkd. 2021;81(4):447-468. doi:10.1055/a-1378-4209.
39. Flynn MK, Weidner AC, Amundsen CL. "Sensory Nerve Injury After Uterosacral Ligament Suspension." Am J Obstet Gynecol. 2006;195(6):1869-1872. doi:10.1016/j.ajog.2006.06.059.
40. Montoya TI, Luebbehusen HI, Schaffer JI, Wai CY, Rahn DD, Corton MM. "Sensory Neuropathy Following Suspension of the Vaginal Apex to the Proximal Uterosacral Ligaments." Int Urogynecol J. 2012;23(12):1735-1740. doi:10.1007/s00192-012-1810-3.
41. Maher C, Yeung E, Haya N, et al. "Surgery for women with apical vaginal prolapse." Cochrane Database Syst Rev. 2023;2023(7):CD012376. doi:10.1002/14651858.CD012376.pub2
42. Chang OH, Carter Ramirez A, Edwards A, et al. "The role of uterine preservation at the time of pelvic organ prolapse surgery." Urogynecology (Phila). 2025;31(5):482-495. doi:10.1097/SPV.0000000000001667
43. Oegema K, Schulten SFM, Stekelenburg J, Kluivers KB, van Eijndhoven HWF. "Sacrospinous hysteropexy versus vaginal hysterectomy in women with uterine prolapse: 10-year follow-up of a randomised controlled trial." Int Urogynecol J. Published online August 13, 2026. doi:10.1007/s00192-026-06822-1