Vaginal Hysterectomy
Vaginal hysterectomy (VH) removes the uterus and cervix through the vagina. For benign disease, ACOG recommends the vaginal route when feasible; laparoscopic hysterectomy is an alternative when vaginal access is unsuitable. Route selection also depends on the planned operation, anatomy, surgeon experience and the informed patient's preferences.[1]
For uterine prolapse, the 2026 Febrasgo statement strongly recommends apical suspension when hysterectomy is performed (grade A).[2] Uterine preservation remains an option to offer surgical candidates without contraindications, and hysterectomy is not an obligatory component of prolapse treatment.[2][19] In the 10-year SAVE-U follow-up, the prespecified endpoint of symptomatic stage 2 or greater apical descent or repeat apical surgery occurred in 3/44 women (7%) after sacrospinous hysteropexy and 7/49 (14%) after vaginal hysterectomy with uterosacral suspension; the difference was −6.6 percentage points (95% CI −19.9 to 6.7), and the reduced follow-up sample limits certainty.[32] Counseling should include the cancer detection and prevention benefit of hysterectomy, weighed against the patient's own risk and values; after uterine-preserving prolapse surgery, cervical screening continues when indicated and abnormal uterine bleeding warrants evaluation.[19]
For treatment selection, see Prolapse Repair. In a 2026 review of primary uterovaginal prolapse, pooled retreatment proportions were 1.59% across 19 hysterectomy-plus-sacrocolpopexy study arms and 10.23% across four vaginal-hysterectomy-plus-native-tissue study arms (range 4–23%). Mean follow-up was 22.0 versus 18.3 months, and the evidence was mostly retrospective and heterogeneous. The authors favored considering sacrocolpopexy for patients at higher recurrence risk who prioritize fewer failures and retreatments, while noting mesh-exposure and small-bowel-injury tradeoffs.[27] Operative companions include McCall Culdoplasty, Uterosacral Ligament Suspension, Sacrospinous Ligament Fixation, and the uterus-preserving Sacrospinous Hysteropexy and Manchester-Fothergill Procedure pages.
Indications and route selection
Establish the indication for hysterectomy before choosing its route. Common benign settings include symptomatic prolapse when hysterectomy is selected, persistent abnormal uterine bleeding, symptomatic fibroids and adenomyosis after discussion of appropriate alternatives. A diagnosis of cervical dysplasia or endometrial hyperplasia alone is not an automatic indication for this operation; premalignant or malignant disease requires its own diagnostic and treatment pathway.[1][3]
| Assessment | Implication for planning |
|---|---|
| Uterine size, shape, mobility and descent | Assess exposure and safe extraction |
| Vaginal access | Evaluate working space |
| Prior cesarean or pelvic surgery | Neither is an absolute contraindication; distorted bladder planes and adhesions can change the operative plan |
| Extrauterine disease or adnexal pathology | Endometriosis, adhesions and required concurrent procedures may favor laparoscopic assistance or another route |
| Prolapse and patient goals | Agree on uterine preservation versus removal, the apical repair, and any additional compartment or continence procedure |
| Expertise and resources | Choose an approach the team can perform safely, with a plan for additional exposure or conversion if necessary |
Vaginal candidacy depends on these factors together; selected expert-center series show feasibility.[1][2][4]
For apparent complete uterine prolapse, Karram recommends determining whether the finding reflects true uterine descent or a markedly elongated cervix, and assessing associated support defects by compartment before choosing the operation; for a markedly elongated cervix, he describes multiple extraperitoneal paracervical bites until the anterior and posterior peritoneal reflections are reached.[24] He also cautions that chronic traction in advanced prolapse, particularly with a large cystocele, can distort the expected ureteral position relative to the cervix.
Operative framework
The sequence changes with anatomy and the planned suspension. These are the core stages of conventional VH, with detailed apical reconstruction on the linked technique pages.[4][5][6]
- Exposure and preparation. Position in supported lithotomy and drain the bladder. Prepare the vagina with povidone-iodine. ACOG describes chlorhexidine gluconate solutions with low concentrations of alcohol (for example, 4% alcohol) as an off-label alternative; check the selected product's labeling, and do not apply high-alcohol chlorhexidine skin preparations to vaginal mucosa.[29][30] Establish adequate lighting and retraction, and confirm the planned adnexal and prolapse procedures.
- Cervicovaginal incision and dissection. Incise at the cervicovaginal junction and develop the vesicocervical plane with controlled dissection. Prior cesarean delivery may distort this plane.
- Peritoneal entry. Identify and enter the anterior and posterior reflections under controlled exposure. When access is difficult, posterior-first entry or staged extraperitoneal pedicle control may help; do not force entry through an uncertain plane. Linder describes bladder illumination as an additional troubleshooting aid.[6]
- Pedicle control. Secure, divide and confirm hemostasis of the uterosacral and cardinal attachments, uterine vessels and upper pedicles as exposure permits. Keep the bladder, ureters and bowel clear of the clamp, needle and active energy jaws. The upper pedicle differs when the ovaries are preserved versus removed. Karram describes alternating pedicles from side to side during division to improve uterine mobility and exposure; when ligating each pedicle, he passes the suture through tissue just beyond the clamp tip, then makes a second pass through the previously secured pedicle above it, incorporating the new ligature into it to close the gap between successive pedicles that he associates with a risk of bleeding or tissue tearing.[25] This is the chapter author's suture variant; no comparative outcome evidence is reported for it.
- Specimen delivery. Remove the uterus intact when feasible.[1] If vaginal debulking or manual fragmentation is contemplated, establish an appropriate preoperative malignancy assessment, extraction plan and consent.[1]
- Hemostasis, suspension and closure. Reassess all pedicles, complete the chosen apical repair and close the cuff without compromising the planned vaginal length or support. The 2017 SGS review reported about 1 cm greater vaginal length with vertical than with horizontal cuff closure, and either peritoneum or vaginal epithelium can be used to close the colpotomy. Evidence for many individual steps was limited.[2][4] As an alternative when the cuff is left open at the end of the case, Baggish describes hemostasis with a continuous "baseball" or "reefing" stitch, optionally locked, rather than immediate formal closure.[26]
- Urinary-tract assessment. For vaginal hysterectomy with apical or anterior prolapse reconstruction, perform intraoperative cystoscopy to inspect the bladder and urethra and assess bilateral ureteral efflux; this includes McCall culdoplasty and vaginal uterosacral suspension.[31] For vaginal uterosacral suspension, assess efflux after the suspension sutures are tied. Follow the specific repair's technique and injury-evaluation pathway.[2]
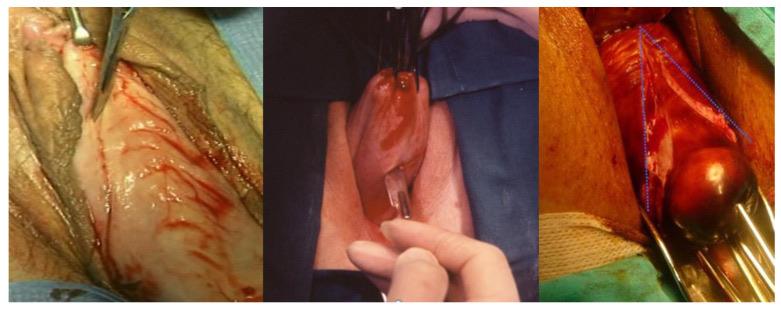
Vaginal incisions for vaginal hysterectomy. Left, incision on the anterior vaginal wall. Center, incision on the posterior vaginal wall. Right, drop-like anterior vaginal incision in a patient with cystocele. From Stark M, et al. Int J Environ Res Public Health. 2022;19(18):11381, Figure 1 (CC BY).[5]
Injected vasopressin decreased blood loss by about 130 mL in the 2017 SGS review.[4] Routine postoperative vaginal packing is not supported by the same review. Selective packing for a defined clinical reason requires an explicit removal plan.[4]
Vessel sealing vs suture ligation
Clamp-cut-ligate and bipolar vessel sealing are alternative methods of pedicle control. A vessel sealer can shorten this part of the operation.
The 2024 Society of Gynecologic Surgeons systematic review included 19 comparative pedicle-sealing studies. Its supplemental evidence table reports approximately 16 minutes shorter surgery (mean difference −15.9; 95% CI −23.3 to −8.5) and 37 mL less blood loss (−36.9; −56.9 to −17.0). Stay and pain differences were modest and heterogeneous; pooled opioid use did not show a clear reduction.[7]
The randomized evidence before and after that review points the same way for bipolar sealers.
- Kroft and Selk's meta-analysis included 7 randomized trials with 662 women. Energy-based sealing shortened operative time by a mean of 17.2 minutes (7 trials, 662 women; 95% CI 7.5–27.0) and reduced blood loss by a mean of 47.7 mL (5 trials, 437 women; 95% CI 15.5–79.9), without a detected increase in complications. No study examined mortality or quality of life.[8]
- Bonavina network meta-analysis (10 randomized and 7 observational studies, 1,577 women). LigaSure and BiClamp both lowered blood loss compared with conventional suturing; operative time, postoperative hemoglobin change and pain were reduced only in the LigaSure group. Intraoperative complication risk was comparable across techniques.[9]
- Cronjé randomized trial (68 women). Bipolar sealing used a median of 1 ligature versus 7 with suturing, and median operating time was 32 versus 40 minutes.[10]
- Elhao randomized trial (103 women). LigaSure shortened operative time and reduced blood loss without a significant change in complication rates, and the blood-loss advantage was more pronounced in the more difficult procedures.[11]
- Ultrasonic shears. In a randomized trial of 40 women, the Harmonic scalpel reduced blood loss (mean 62.6 versus 136.1 mL) but did not shorten operative time or reduce analgesic use.[12]
- Hefni randomized trial (116 women). LigaSure shortened operating time. Perioperative hemorrhagic complications occurred in none of the LigaSure group and in 6.8% of the suture group (P = 0.057); no LigaSure patient had bleeding from an unsecured pedicle.[13]
Use the selected device within its instructions, under direct exposure, and avoid incorporating adjacent structures. Inadequate sealing (tissue too thick, wet or poorly grasped) and unintended thermal injury to the ureter, bladder or bowel are distinct hazards; suture hemostasis must remain available, and suture is still needed for cuff closure and apical suspension.[7][34]
Concurrent procedures
- Apical suspension. It is part of hysterectomy for uterine prolapse. Choose the specific repair according to support defects and patient goals.[2]
- Other compartment and continence procedures. Plan them from symptoms, examination and shared decisions.
- Opportunistic salpingectomy. Discuss it when appropriate. It should not by itself change the intended hysterectomy route.[1]
- Ovarian conservation or oophorectomy. Decide separately according to indication, age, ovarian pathology, cancer risk and preferences. Technical ability to remove the ovaries is not itself an indication for bilateral oophorectomy.[1]
Comparative outcomes
| Evidence | Clinically useful interpretation |
|---|---|
| Cochrane 2023: 63 RCTs, 6,811 participants across all route comparisons | VH versus abdominal hysterectomy probably permits earlier return to normal activities (about 11 days, four trials/274 women) and fewer wound infections. Differences in operating time, transfusion and uncommon visceral injuries remain uncertain.[3] |
| Meyer 2026: NSQIP 2012–2022 observational analysis | Among 83,436 matched patients, 30-day complications were 8.2% after VH versus 6.4% after laparoscopic/robotic hysterectomy (adjusted OR 1.23, 95% CI 1.15–1.31).[14] |
| Cassani 2026: 63-RCT urinary-injury network review | The review supports a ureter-injury signal for laparoscopic versus abdominal hysterectomy; rare events, wide intervals, overlapping older trials and inconsistencies between text and supplements limit rankings of vaginal, robotic and vNOTES approaches.[15] |
| Settnes 2020: Danish Hysterectomy Database, 2004–2015 | Among 51,141 benign hysterectomies, major (Clavien-Dindo III–V) 30-day complications occurred after 4.9% of VH for non-prolapse, 2.3% of VH for prolapse, 4.1% of laparoscopic, and 10.3% of abdominal procedures. Relative to VH for non-prolapse, adjusted major-complication risk was lower after laparoscopic hysterectomy (RR 0.78, 95% CI 0.68–0.90) and VH for prolapse (RR 0.55, 95% CI 0.41–0.75). The laparoscopic association differed by period (RR 0.96 in 2004–2009 versus 0.72 in 2010–2015); confounding by indication remains possible.[21] |
| LAVA 2025 randomized trial | Compared laparoscopic with abdominal hysterectomy, not VH. Only 75 of 3,250 planned participants were randomized and 62 underwent surgery; the planned noninferiority conclusion could not be made.[16] |
Conventional VH and vNOTES
The 2026 VANH randomized trial analyzed 113 patients at two Dutch centers. Same-day discharge occurred in 87.3% after vaginal-assisted NOTES versus 71.4% after conventional VH (OR 2.76; 95% CI 1.04–7.25).[17] Reported complications and readmissions did not differ significantly.[17] In a separate 60-patient randomized trial for apical prolapse, mean total surgical time was 77 versus 93 minutes and mean estimated blood loss was 60 versus 143 mL after vNOTES hysterectomy with uterosacral suspension compared with conventional vaginal hysterectomy with the same suspension.[33] See vNOTES and robotic platforms for the distinctions between techniques.
Complications and perioperative care
Counsel about bleeding, infection, bladder, ureter or bowel injury, retention, VTE, vaginal healing and the outcomes of any concomitant prolapse repair.
| Complication | Reported estimate |
|---|---|
| Infection | 13.0% after vaginal hysterectomy, 10.5% after abdominal and 9.0% after laparoscopic hysterectomy (narrative review)[22] |
| Estimated blood loss | Median range 215–287 mL for vaginal hysterectomy; transfusion was more likely after laparoscopic than vaginal hysterectomy (OR 2.07, 95% CI 1.12–3.81)[22] |
| Vaginal cuff dehiscence | 0.08% after total vaginal hysterectomy, compared with 0.15% after total abdominal, 0.28% after laparoscopic-assisted vaginal and 1.35% after total laparoscopic hysterectomy[22] |
| Neuropathy | 0.2–2% after major pelvic surgery[22] |
| Ureteral and bladder injury | In 296,130 California benign hysterectomies (all routes), 1.0% had ureteral and 0.7% bladder injury; an exclusively vaginal approach had lower odds of genitourinary injury than an abdominal approach (OR 0.56, 95% CI 0.53–0.64). Concomitant prolapse repair (OR 1.44) and an incontinence procedure (OR 1.40) were associated with higher odds[23] |
| Fistula after injury | Subsequent genitourinary fistula was less frequent when the injury was identified immediately than when it was delayed (ureteral 0.7% vs 3.4%; bladder 2.5% vs 6.5%)[23] |
| Major and total complications | 2.6% and 11.7% after vaginal hysterectomy in the Finnish FINHYST cohort[18] |
In FINHYST, prior cesarean delivery and uterine weight at least 500 g were associated with bladder injury (OR 4.01 and 2.88 respectively). These were adjusted associations across a mixed-route cohort, not VH-specific absolute risks or contraindications. Urinary injury can be recognized after surgery; new flank pain, urinary leakage, fever or unexpected recovery warrants evaluation.[18]
| Element | Practical approach |
|---|---|
| Infection prevention | Use hysterectomy-appropriate prophylaxis, with agent, allergy, weight and redosing decisions in Perioperative Antibiotic Prophylaxis |
| Analgesia | Individualized multimodal treatment; acetaminophen/NSAIDs when suitable, selected regional techniques and rescue opioids. Routine new gabapentin is not a default. See Analgesia |
| VTE prevention | Early mobilization and mechanical/pharmacologic measures matched to thrombotic and bleeding risk; see VTE Prophylaxis |
| Discharge and recovery | Confirm pain/nausea control, mobility and a voiding or catheter plan. Individualize graded activity and vaginal-healing advice to the complete operation, especially concurrent prolapse repair. The 2025 AUGS consensus statement recommends that surgeons allow patients to resume activity liberally after urogynecologic surgery, because the evidence does not support routine lifting or activity restrictions.[20] Vaginal intercourse after cuff closure: many surgeons advise 6–12 weeks of pelvic rest, but dehiscence triggered by intercourse occurs outside that window, and no study shows that a longer delay lowers risk; a 2023 review summarizing a 2021 meta-analysis of laparoscopic and robotic hysterectomy reports intercourse as the trigger in 64% of vaginal cuff dehiscence cases and a mean time from surgery to evisceration of 68.5 days (range 5–512 days).[20][28] |
Videos
References
1. Committee on Gynecologic Practice. Committee Opinion No. 701: Choosing the route of hysterectomy for benign disease. Obstet Gynecol. 2017;129(6):e155-e159. doi:10.1097/AOG.0000000000002112.
2. Sartori MGF, Brito LGO, Schreiner L, et al. Surgical treatment of apical prolapse: Number 9 – 2026. Rev Bras Ginecol Obstet. 2026;48:e-FPS9. Febrasgo position statement. doi:10.61622/rbgo/2026FPS9. Full text.
3. Pickett CM, Seeratan DD, Mol BWJ, et al. Surgical approach to hysterectomy for benign gynaecological disease. Cochrane Database Syst Rev. 2023;8:CD003677. doi:10.1002/14651858.CD003677.pub6.
4. Jeppson PC, Balgobin S, Rahn DD, et al. Comparison of vaginal hysterectomy techniques and interventions for benign indications: a systematic review. Obstet Gynecol. 2017;129(5):877-886. doi:10.1097/AOG.0000000000001995.
5. Stark M, Malvasi A, Mynbaev O, Tinelli A. The renaissance of the vaginal hysterectomy — a due act. Int J Environ Res Public Health. 2022;19:11381. doi:10.3390/ijerph191811381. Full text.
6. Linder BJ, Gebhart JB. Entry into the anterior cul-de-sac during vaginal hysterectomy. Int Urogynecol J. 2018;29(8):1223-1225. doi:10.1007/s00192-018-3646-y.
7. Balgobin S, Balk EM, Porter AE, et al; Society of Gynecologic Surgeons Systematic Review Group. Enabling technologies for gynecologic vaginal surgery: a systematic review. Obstet Gynecol. 2024;143:524–537. doi:10.1097/AOG.0000000000005522. Supplemental evidence tables and analyses.
8. Kroft J, Selk A. Energy-based vessel sealing in vaginal hysterectomy: a systematic review and meta-analysis. Obstet Gynecol. 2011;118(5):1127-1136. doi:10.1097/AOG.0b013e3182324306.
9. Bonavina G, Bonitta G, Busnelli A, et al. Vaginal hysterectomy: a network meta-analysis comparing short-term outcomes of surgical techniques and devices. J Minim Invasive Gynecol. 2024;31(10):825-835. doi:10.1016/j.jmig.2024.07.013.
10. Cronjé HS, de Coning EC. Electrosurgical bipolar vessel sealing during vaginal hysterectomy. Int J Gynaecol Obstet. 2005;91(3):243-245. doi:10.1016/j.ijgo.2005.08.019.
11. Elhao M, Abdallah K, Serag I, El-Laithy M, Agur W. Efficacy of using electrosurgical bipolar vessel sealing during vaginal hysterectomy in patients with different degrees of operative difficulty: a randomised controlled trial. Eur J Obstet Gynecol Reprod Biol. 2009;147(1):86-90. doi:10.1016/j.ejogrb.2009.07.011.
12. Fitz-Gerald AL, Tan J, Chan KW, et al. Comparison of ultrasonic shears and traditional suture ligature for vaginal hysterectomy: randomized controlled trial. J Minim Invasive Gynecol. 2013;20(6):853-857. doi:10.1016/j.jmig.2013.05.019.
13. Hefni MA, Bhaumik J, El-Toukhy T, et al. Safety and efficacy of using the LigaSure vessel sealing system for securing the pedicles in vaginal hysterectomy: randomised controlled trial. BJOG. 2005;112(3):329-333. doi:10.1111/j.1471-0528.2004.00325.x.
14. Meyer R, Hamilton KM, Ezike O, et al. Vaginal hysterectomy vs laparoscopic hysterectomy for benign indications: complications and length of stay in a national analysis of contemporary data. Am J Obstet Gynecol. 2026;234(3):620-631. doi:10.1016/j.ajog.2025.10.027.
15. Cassani C, Spinillo A, Dominoni M, Gardella B. Revisiting urological injury risks in minimally invasive hysterectomy for benign indications: a rare-events network meta-analysis with sensitivity analyses. Int Urogynecol J. 2026. doi:10.1007/s00192-026-06566-y.
16. Antoun L, Woolley R, Middleton L, et al. Comparison of complications and recovery after laparoscopic and abdominal hysterectomy for benign disease: the LAparoscopic Versus Abdominal hysterectomy (LAVA) randomised controlled trial. BMJ Open. 2025;15:e096265. doi:10.1136/bmjopen-2024-096265. Full text.
17. Bekkers IPW, Wintraecken FRM, Smeets NAC, et al. Vaginal hysterectomy versus vaginal assisted natural orifice transluminal endoscopic surgery hysterectomy; results of a randomised controlled trial. BJOG. 2026. doi:10.1111/1471-0528.70260.
18. Brummer TH, Jalkanen J, Fraser J, et al. FINHYST, a prospective study of 5279 hysterectomies: complications and their risk factors. Hum Reprod. 2011;26(7):1741-51. doi:10.1093/humrep/der116.
19. Chang OH, Carter Ramirez A, Edwards A, et al. The role of uterine preservation at the time of pelvic organ prolapse surgery. Urogynecology (Phila). 2025;31(5):482–495. doi:10.1097/SPV.0000000000001667. AUGS Clinical Practice Statement.
20. Mueller MG, Das D, Davis-Wilson H, et al. Postoperative activity instructions following urogynecologic surgery. Urogynecology (Phila). 2025;31(10):913–925. doi:10.1097/SPV.0000000000001750. AUGS Clinical Consensus Statement (Q20 and discussion).
21. Settnes A, Moeller C, Topsoee MF, et al. Complications after benign hysterectomy, according to procedure: a population-based prospective cohort study from the Danish Hysterectomy Database, 2004-2015. BJOG. 2020;127(10):1269-1279. doi:10.1111/1471-0528.16200.
22. Clarke-Pearson DL, Geller EJ. Complications of hysterectomy. Obstet Gynecol. 2013;121(3):654-673. doi:10.1097/AOG.0b013e3182841594.
23. Dallas KB, Rogo-Gupta L, Elliott CS. Urologic injury and fistula after hysterectomy for benign indications. Obstet Gynecol. 2019;134(2):241-249. doi:10.1097/AOG.0000000000003353.
24. Karram MM. Vaginal Hysterectomy. In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:596-622.
25. Karram MM. Vaginal Hysterectomy. In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:596-622.
26. Baggish MS. Suture Material, Suturing Techniques, and Knot Tying. In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:111-130.
27. Huffman JA, Ashmore S, Kim S, et al. "Hysterectomy with Minimally Invasive Sacrocolpopexy Versus Native Tissue Repair for Primary Uterovaginal Prolapse: A Systematic Review and Meta-Analysis." Int Urogynecol J. 2026. doi:10.1007/s00192-026-06863-6
28. Jaime Moens B, Buonomo A, De Sutter P. "Vaginal Cuff Dehiscence: Two Case Reports and a Review of the Literature." J Clin Med. 2023;12(13):4187. doi:10.3390/jcm12134187
29. American College of Obstetricians and Gynecologists. "Committee Opinion No. 571: Solutions for Surgical Preparation of the Vagina." Obstet Gynecol. 2013;122(3):718–720. doi:10.1097/01.AOG.0000433982.36184.95
30. American College of Obstetricians and Gynecologists. "ACOG Committee Opinion No. 750: Perioperative Pathways: Enhanced Recovery After Surgery." Obstet Gynecol. 2018;132(3):e120–e130. doi:10.1097/AOG.0000000000002818
31. Cohen SA, Carberry CL, Smilen SW. "American Urogynecologic Society Consensus Statement: Cystoscopy at the Time of Prolapse Repair." Female Pelvic Med Reconstr Surg. 2018;24(4):258–259. doi:10.1097/SPV.0000000000000529
32. Oegema K, Schulten SFM, Stekelenburg J, Kluivers KB, van Eijndhoven HWF. "Sacrospinous hysteropexy versus vaginal hysterectomy in women with uterine prolapse: 10-year follow-up of a randomised controlled trial." Int Urogynecol J. Published online August 13, 2026. doi:10.1007/s00192-026-06822-1
33. Lowenstein L, Mor O, Matanes E, Justman N, Stuart A, Baekelandt J. "Conventional vaginal approach vs. transvaginal natural orifice transluminal endoscopic surgery for treating apical prolapse, a randomized controlled study." Eur J Obstet Gynecol Reprod Biol. 2024;303:180-185. doi:10.1016/j.ejogrb.2024.10.032
34. Davidson ERW, Kho R. Use of vessel-sealing devices during vaginal hysterectomy. J Minim Invasive Gynecol. 2019;26(2):362. doi:10.1016/j.jmig.2018.04.018.