Anal Sphincteroplasty
Anal sphincteroplasty is a surgical repair of a disrupted anal sphincter, most commonly performed for fecal incontinence (FI) due to obstetric anal sphincter injury (OASIS). Within fistula reconstruction, it is used in three settings: as a simultaneous component of ERAF + sphincteroplasty for low RVF with anterior sphincter defect, as the sphincter-reconstruction step of episioproctotomy, and as a staged procedure for residual fecal incontinence after fistula closure. Short-term improvement can be substantial, but benefit often declines. ASCRS cites some series with as few as 10–14% maintaining improvement after five years.[1]
For fecal-incontinence-pathway context (sacral neuromodulation, biofeedback, PTNS, bulking agents, slings), the broader incontinence procedures live under Incontinence Procedures.
Indications
| Setting | Notes |
|---|---|
| Established OASI-related FI | Consider delayed repair of a clinically relevant sphincter defect after appropriate nonoperative treatment; distinguish this from immediate repair of an acute birth injury.[1][2] |
| Other traumatic sphincter injury | Iatrogenic post-anorectal surgery, perineal trauma[3] |
| Component of RVF + sphincter-defect repair | Selected obstetric RVF with a documented defect may require sphincter reconstruction.[14] |
| Residual FI after fistula closure | Reassess bowel function and sphincter anatomy after healing; timing is individualized rather than a mandatory 3–6-month wait. |
Position in the pathway: address stool consistency and other reversible causes first. For persistent bothersome FI, use endoanal ultrasonography to define a residual defect when available, and digital rectal examination to assess contractility; discuss repair and SNM according to anatomy, function, presentation and patient preference.[13][1] The IUGA 2026 pathway considers secondary repair for a significant residual defect with bothersome fecal incontinence and contractility on digital rectal examination, and directs referral for pelvic health physiotherapy and/or SNM without contractility.[13] A prior failed sphincteroplasty is not required before SNM.[13][1][3] Early postpartum referral and the frequency of secondary repair in clinic cohorts are covered under Postpartum Perineal Clinic.
Preoperative Evaluation
| Modality | Role |
|---|---|
| Anorectal manometry | Selectively characterize pressures, sensation and coordination when results will inform management; it does not reliably predict who benefits from SNM or colostomy.[1] |
| Endoanal ultrasound | Useful for defining a repairable sphincter defect (ASCRS conditional, very low certainty). Defect size does not necessarily correlate with FI severity[1] |
| MRI | Consider alternative or dynamic imaging for selected patients when EAUS is unavailable or does not explain symptoms; MRI is not mandatory for every repair.[1] |
| PNTML | Not routinely recommended (ASCRS)[1] |
| Continence scoring | Wexner / Cleveland Clinic Incontinence Score or St. Mark's score documented preoperatively for objective comparison[1] |
Surgical Technique
Overlapping anterior sphincteroplasty (delayed / secondary repair)
An option for selected established sphincter defects; discuss durability limitations, the neuromodulation alternative and future childbirth. The IUGA 2026 OASI algorithm recommends cesarean delivery for subsequent pregnancies after secondary repair of an OASI clinically diagnosed at delivery.[13]
A reported delayed-repair approach includes the following principles:[6]
- Expose the anterior defect through the perineum and distinguish anal mucosa, IAS, EAS and vaginal tissues.
- Mobilize enough viable sphincter for a tension-free repair while protecting the anterolateral neurovascular supply.
- Assess scar selectively. Traditional overlap techniques retain scar as a suture anchor; Ong's variant excised excess nonfunctional scar and sutured mobilized muscle.
- Identify an associated IAS defect and plan separate end-to-end repair when feasible. Reconstruct the EAS using the selected technique and restore the deficient perineal body.
- For patients without a colostomy, use postoperative stool softeners; arrange close clinical follow-up and intervene early if sepsis develops.[6] Diversion is individualized for fistula, contamination, major reconstruction or patient needs and is not routine for every delayed sphincteroplasty.
Described exposure and closure variants differ between authors. One describes an inverted-U incision from about the 9 to 3 o'clock position, performed with a finger in the rectum for guidance; when the retracted sphincter ends lie within dense scar, a nerve stimulator or low-power electrosurgery can help identify viable muscle, and the scar is divided centrally while left attached to the sphincter ends as a suture anchor.[16] Another describes an inverted-V incision extending about 3–4 cm to each side of the midline, with the mobilized ends overlapped in the midline using 4–6 standing mattress sutures in two layers of slow-resorbing PDS, restitution of the perineal body without excessive narrowing to limit dyspareunia, and an inverted-Y skin closure left open centrally for drainage.[17] Neither incision or closure sequence is established as superior.
For step 4, authors differ on managing a combined IAS/EAS defect in delayed repair. One author repairs an identified IAS defect separately from the EAS, as above. Another treats an injured IAS and EAS as one unit, incorporating small bites of the anterior rectal wall into the overlap repair and placing about six mattress sutures (three on each side) along the sphincter length, rather than dissecting out and repairing the IAS separately.[16] Whether the IAS should be separated from the EAS in delayed repair remains debated, and no comparative continence or safety outcome has been shown to favor either configuration.[17]
Absorbable polydioxanone or polyglactin sutures and several configurations have been used. In primary OASI repair, IUGA advises against rapidly absorbing polyglactin for sphincter muscle because it loses all tensile strength within 14 days.[13] For acute OASI repair, ACOG lists 3-0 polyglactin, 3-0 polydioxanone or 2-0 polyglactin for the EAS by expert opinion, and the only randomized trial it cites found no difference between 3-0 polydioxanone and 3-0 polyglactin in suture-related morbidity at 6 weeks or continence at 3 months.[5] In a nonrandomized case series, 40 women completed a symptom questionnaire at a mean 50 months after overlapping sphincteroplasty.[18] Loss of solid stool was reported by 50% in each suture group, while the permanent-suture group had a lower Fecal Incontinence Severity Index (15.9 versus 24.0); overall quality-of-life impact did not differ.[18] Selective levator plication was common in the Cerdán series, but its independent continence benefit and effect on dyspareunia were not established.[7]
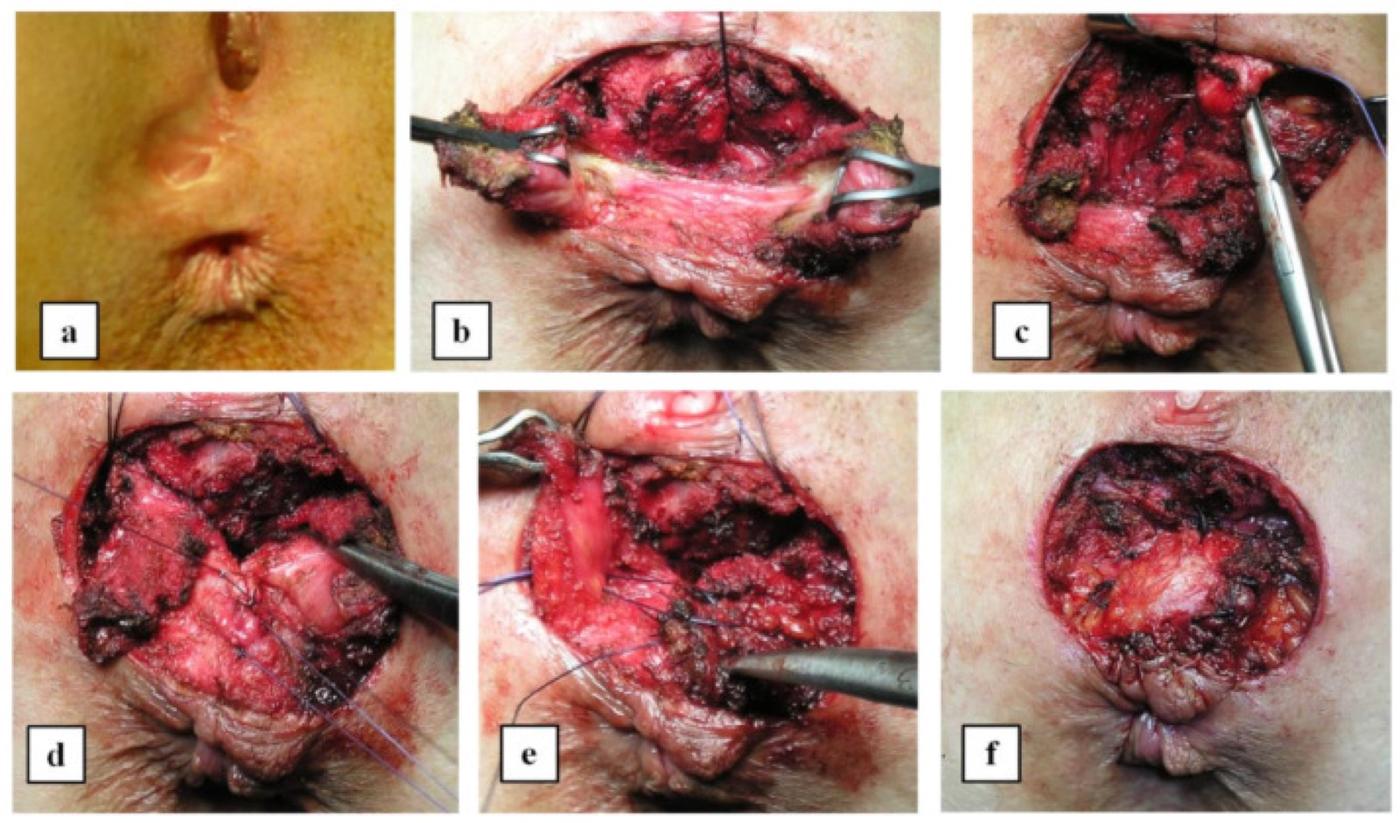
Overlapping sphincteroplasty. (a) Preoperative inspection showing episiotomy scar and flattening of the anal margin. (b) Dissection of both puborectalis limbs and the ends of the external anal sphincter. (c) Levatorplasty with interrupted sutures. (d) Internal anal sphincter plication. (e) Overlapping sphincteroplasty. (f) Final result; the wound is left fully or partly open, without drains. From Cerdán Santacruz C, et al. J Clin Med. 2022;11(13):3755, Figure 1 (CC BY 4.0).
End-to-end repair (acute / primary repair)
The July 2026 IUGA OASI guideline recommends end-to-end repair for partial-thickness EAS injuries (3a and partial 3b; grade D).[13] For full-thickness, full-length EAS tears, either end-to-end or overlap repair has equivalent outcomes (grade A).[13] Identify and repair a torn IAS separately, end-to-end (grade C); do not overlap the IAS.[13] The 2015 RCOG Green-top Guideline No. 29 reaches the same conclusions: end-to-end repair for partial-thickness tears (grade D), either method for full-thickness EAS tears with equivalent outcomes (grade A), and separate repair of an identifiable IAS with interrupted or mattress sutures and no overlap (grade C).[15] It advises against figure-of-eight sutures and recommends a rectal examination after repair to exclude a suture through the anorectal mucosa (good practice points).[15] RCOG cites randomized trials reporting residual EAS defects in 19% to 36% of women after repair and 60% to 80% asymptomatic at 12 months.[15] IUGA 2026 recommends intravenous broad-spectrum antibiotic prophylaxis within one hour before primary OASI repair (grade B).[13]
End-to-end vs overlap
ACOG accepts end-to-end or overlap repair for full-thickness EAS lacerations at primary repair (Level A); the meta-analysis it cites (six randomized trials of variable quality, 588 women across heterogeneous OASI grades, including partial EAS tears)[21] found lower fecal urgency and anal incontinence scores with overlap at 12 months in one 52-woman trial and no difference in anal incontinence symptoms at 36 months in one 68-woman trial.[5]
Dehiscence after primary OASI repair
IUGA 2026 supports specialist assessment and selected early secondary repair, with counseling about infection, repeat dehiscence and fistula (Grade C). This differs from late reconstruction of a healed chronic defect. Avoid early secondary repair with obvious active infection; optimal timing and continence outcomes relative to later repair remain uncertain.[13]
Outcomes
| Source | Findings and limitations |
|---|---|
| ASCRS 2023 synthesis | Historical short-term good/excellent results reached 85% in some series, but definitions varied and benefit often deteriorated. The cited 10–14% five-year sustained-improvement estimates are at the low end of individual reports.[1] |
| ACOG PB 210 (2019) | Continence deteriorates over time after end-to-end or overlapping repair; one half of women report FI symptoms 5–10 years after repair, yet 74% remain satisfied with the result.[2] |
| Haug 2021 | Twenty of 33 operated women were followed at median 5, 102 and 220 months. Median scores changed from 11.5 before surgery to 5.5, 10 and 12; 45% reported a better outcome at the last assessment. Attrition and small size limit generalization.[9] |
| Cerdán Santacruz 2022 | Retrospective series of 120 repairs; 105 patients (87.5%) were available at median ten-year follow-up, and 42 received ancillary treatment. Among assessed patients, 93.3% rated the outcome good or excellent.[7] |
The 2013 Cochrane review found only nine small trials involving 264 patients across surgical comparisons; it could not establish clinically important differences between techniques.[4] A 2023 review of eight observational series (355 women after overlapping repair for obstetric injury) found worsening continence over time in seven studies, yet long-term symptom improvement relative to preoperative status persisted; the quality-of-life trend was less clear.[22]
Complications
Counsel about wound infection or breakdown, persistent or recurrent FI, pain or dyspareunia and evacuation difficulty.[2][6] For sphincteroplasty for fecal incontinence, ACOG reports overall surgical complication rates of 5% to 27% from a systematic review of repair outcomes, with wound infection the most common (6% to 35%); fecal impaction, wound hematoma, urinary tract infection, dyspareunia and defecatory dysfunction also occur.[2]
Jain 2023 audit (n = 239 OASIS): structural failure on EAUS in 41.8%; only 20% of structural failures were symptomatic at mean 23 mo. No investigated repair variable was significantly associated with structural failure in this observational cohort.[10]
Prognostic Factors
Technical and patient factors are not clearly established:[8]
- Age, sex, extent of sphincter injury
- Etiology and duration of FI
- Pudendal neuropathy
- Surgical technique (end-to-end versus overlap)
Some signals:
- Haug found no score improvement in five patients with neuropathy and five with more than ten years of symptoms.[9] ASCRS does not recommend routine PNTML testing to select patients.[1]
- The multifactorial nature of post-OASIS FI (mechanical disruption, neuropathy, pelvic-floor dysfunction and altered rectal sensation) likely explains the high long-term failure rate[1]
Sphincteroplasty vs Sacral Neuromodulation (SNM)
The role of sphincteroplasty has been increasingly challenged:
- ASCRS 2023 states that SNM may be considered as a first-line surgical option for incontinent patients with or without sphincter defects (conditional, low certainty).[1]
- Emile (online 2025; 2026 issue) pooled ten studies with 779 patients. SNM was associated with greater continence improvement than repair (OR 1.68, P = 0.006), but the authors judged the comparison insufficient for firm conclusions.[11] Complication rates did not differ significantly.[11] Across the sphincter-defect SNM cohorts, pooled complication and device-removal rates were 18.5% (95% CI 8.7–28.2) and 9.1% (95% CI 3.4–14.7), respectively.[11]
- Rodrigues compared 13 matched patients per group retrospectively. Scores improved within the SNM group, but the between-group improvement comparison was not statistically significant (P = 0.06); comparing the two within-group P values would overstate superiority.[12]
- Successful SNM has been reported with sphincter defects up to 120°.[1]
- US sphincteroplasty volume decreased 7-fold between 2009–2015.[1]
- Previous repair, defects over 120° and low resting pressure were associated with less SNM improvement in the newer synthesis.[11]
In the 2025 sham-controlled SUBSoNIC trial of adults with refractory FI, subsensory SNM did not establish a reduction in weekly FI episodes versus sham (mean difference −0.795; 95% CI −1.5 to 0.0; P = 0.06); only 16 of 39 recruited patients had complete primary-outcome data.[19] See Fecal Incontinence for the broader SNM evidence.
Repeat Sphincteroplasty
For ASCRS 2023, repeat sphincteroplasty after a failed overlapping sphincteroplasty should generally be avoided (conditional, very low certainty):[1]
- In a retrospective repeat-sphincteroplasty series, 56/84 patients were available at median 74 months; mean Wexner score decreased from 16.5 to 11.9 at last follow-up (P < 0.001). At that follow-up, 28.6% met composite long-term success criteria (no further continence surgery, no stoma and score <9); 21.4% underwent further continence surgery, and 5.4% had a permanent stoma.[1][20]
- Consider only when a specific failure cause is identified (e.g., recurrent sphincter injury from repeat vaginal delivery).[1]
- Reassess symptoms, bowel consistency, anatomy and other causes of FI. A residual ultrasound defect alone is not an automatic indication for another operation.[1]
Treatment Selection for Established FI
Begin with individualized bowel management, then consider pelvic-floor rehabilitation or biofeedback. If symptoms remain unacceptable, discuss SNM or selected sphincter reconstruction. ASCRS says SNM may be considered as a first-line surgical option for fecal incontinence with or without a sphincter defect ; colostomy is an option when other treatments fail or the patient does not wish to pursue them. Anal bulking injections are not routinely recommended.[1]
Place in the RVF Repair Atlas
- Concurrent with ERAF + sphincteroplasty for selected low RVF with a defect. ASCRS cites 52 patients with simple obstetric RVF (48% with varying FI) undergoing 62 procedures: healing was 11/27 after ERAF and 28/35 after sphincteroplasty with or without levatorplasty.[14] A 2025 network meta-analysis of 32 nonrandomized obstetric-RVF studies (595 women and/or procedures) reported higher odds of anatomical closure for Musset and transvaginal or transperineal excision with layered closure than for ERAF.[23] Fecal incontinence data were insufficient for meta-analysis.[23]
- Built into Episioproctotomy. Reconstruction of the disrupted anterior sphincter accompanies layered fistula repair.
- Residual FI after fistula closure. Reassess the healed anatomy and all contributors to incontinence, then individualize timing and discuss durability and SNM.
Key Takeaways
- Short-term results are good and deteriorate progressively over time.
- An AGA expert review advises considering sphincteroplasty for postpartum FI or a recent sphincter injury; for persistent FI, weigh defect anatomy, residual contractility, other symptom contributors and patient preference. Symptom duration alone is not a validated cutoff.[8][13][9]
- For patients decades after obstetric trauma, SNM may be the more appropriate first surgical option.
- Additional treatment may help residual symptoms.
- Repeat sphincteroplasty should generally be avoided unless a specific correctable failure cause is identified.
References
1. Bordeianou LG, Thorsen AJ, Keller DS, et al. "The American Society of Colon and Rectal Surgeons clinical practice guidelines for the management of fecal incontinence." Dis Colon Rectum. 2023;66(5):647–661. doi:10.1097/DCR.0000000000002776
2. ACOG Committee on Practice Bulletins—Gynecology. "ACOG practice bulletin no. 210: fecal incontinence." Obstet Gynecol. 2019;133(4):e260–e273. doi:10.1097/AOG.0000000000003187
3. Wald A, Bharucha AE, Limketkai B, et al. "ACG clinical guidelines: management of benign anorectal disorders." Am J Gastroenterol. 2021;116(10):1987–2008. doi:10.14309/ajg.0000000000001507
4. Brown SR, Wadhawan H, Nelson RL. "Surgery for faecal incontinence in adults." Cochrane Database Syst Rev. 2013;(7):CD001757. doi:10.1002/14651858.CD001757.pub4
5. ACOG Committee on Practice Bulletins—Obstetrics. "ACOG practice bulletin no. 198: prevention and management of obstetric lacerations at vaginal delivery." Obstet Gynecol. 2018;132(3):e87–e102. doi:10.1097/AOG.0000000000002841. Interim update; reaffirmed 2025.
6. Ong F, Phan-Thien KC. "How to do it: delayed sphincteroplasty for obstetric anal sphincter injury." ANZ J Surg. 2022;92(5):1208–1210. doi:10.1111/ans.17650
7. Cerdán Santacruz C, Cerdán Santacruz DM, Milla Collado L, Ruiz de León A, Cerdán Miguel J. "Multimodal management of fecal incontinence focused on sphincteroplasty: long-term outcomes from a single center case series." J Clin Med. 2022;11(13):3755. doi:10.3390/jcm11133755
8. Bharucha AE, Rao SSC, Shin AS. "Surgical interventions and the use of device-aided therapy for the treatment of fecal incontinence and defecatory disorders." Clin Gastroenterol Hepatol. 2017;15(12):1844–1854. doi:10.1016/j.cgh.2017.08.023
9. Haug HM, Carlsen E, Johannessen HO, Johnson E. "Short-, long-, and very long-term results of secondary anterior sphincteroplasty in 20 patients with obstetric injury." Int J Colorectal Dis. 2021;36(12):2775–2778. doi:10.1007/s00384-021-04026-1
10. Jain A, Lew C, Thungathruthi K, et al. "Incidence and risk factors for secondary failure after acute obstetric sphincter injury repair — an audit of 239 women." Colorectal Dis. 2023;25(1):95–101. doi:10.1111/codi.16313
11. Emile SH, Wignakumar A, Horesh N, et al. "Efficacy of sacral neuromodulation in treatment of fecal incontinence associated with anal sphincter defects: a systematic review and meta-analysis." World J Surg. 2026;50(1):48–57. Published online November 22, 2025. doi:10.1002/wjs.70152
12. Rodrigues FG, Chadi SA, Cracco AJ, et al. "Faecal incontinence in patients with a sphincter defect: comparison of sphincteroplasty and sacral nerve stimulation." Colorectal Dis. 2017;19(5):456–461. doi:10.1111/codi.13510
13. Sultan AH, Okeahialam NA, De Leeuw J, et al. IUGA International Guidelines on Obstetric Anal Sphincter Injuries. Int Urogynecol J. 2026;37:2223–2280. Published July 10, 2026. doi:10.1007/s00192-026-06642-3. PMID: 42429937.
14. Gaertner WB, Burgess PL, Davids JS, et al. The American Society of Colon and Rectal Surgeons clinical practice guidelines for the management of anorectal abscess, fistula-in-ano, and rectovaginal fistula. Dis Colon Rectum. 2022;65(8):964–985. doi:10.1097/DCR.0000000000002473.
15. Royal College of Obstetricians and Gynaecologists. The Management of Third- and Fourth-Degree Perineal Tears. Green-top Guideline No. 29. London: RCOG; June 2015.
16. Karram MM. Anal Sphincter Repair and Perineal Reconstruction. In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:1169-1180.
17. Schultz JK, Øresland T. Management of Fecal Incontinence, Constipation, and Rectal Prolapse. In: Martins FE, Holm HV, Sandhu JS, McCammon KA, eds. Female Genitourinary and Pelvic Floor Reconstruction. Springer; 2023:1013-1029.
18. Parnell BA, Whitehead WE, Geller EJ, Jannelli ML, Connolly A. Overlapping anal sphincteroplasty: impact of suture selection on bowel symptoms. J Reprod Med. 2011;56(5-6):187-191. PMID: 21682111.
19. Vollebregt PF, Goh YL, Bagul A, et al. "Clinical efficacy of subsensory sacral neuromodulation in adults with faecal incontinence: The SUBSoNIC crossover randomised controlled trial and cohort follow-up study." Colorectal Dis. 2025;27(11):e70308. doi:10.1111/codi.70308
20. Hong K, Dasilva G, Dollerschell JT, et al. "Redo sphincteroplasty: are the results sustainable?" Gastroenterol Rep (Oxf). 2016;4(1):39–42. doi:10.1093/gastro/gov025
21. Fernando RJ, Sultan AH, Kettle C, Thakar R. "Methods of repair for obstetric anal sphincter injury." Cochrane Database Syst Rev. 2013;2013(12):CD002866. doi:10.1002/14651858.CD002866.pub3
22. Mongardini FM, Cozzolino G, Karpathiotakis M, Cacciatore C, Docimo L. "Short- and long-term outcomes of sphincteroplasty for anal incontinence related to obstetric injury: a systematic review." Updates Surg. 2023;75(6):1423–1430. doi:10.1007/s13304-023-01609-1
23. Venara A, Houlet E, Poupard E, et al. "Sphincter repair procedures may be favored in the treatment of obstetrical recto-vaginal fistula: a systematic review of the literature and meta-analysis." Tech Coloproctol. 2025;29(1):95. doi:10.1007/s10151-025-03133-3