Endoscopic Management of Vesicovaginal Fistula
Endoscopic management of vesicovaginal fistula (VVF) covers a spectrum of minimally invasive, endoscopy-guided techniques, from purely cystoscopic interventions (fulguration, laser ablation, tissue-adhesive injection) for small fistulae to advanced laparoendoscopic and transvesicoscopic suture repairs for more complex cases.[1][2]
For the underlying clinical evaluation, classification, and decision algorithm, see the vesicovaginal fistula clinical page. For repair-route selection across the female-fistula spectrum, see the Female Fistula Repair atlas.
Cystoscopy in Diagnosis and Preoperative Planning
Cystoscopy in VVF evaluation allows direct visualization of the bladder-side fistula orifice, assessment of size and location relative to the ureteral orifices and trigone, and evaluation of surrounding-tissue quality. A combined vaginoscopy-cystoscopy technique with simultaneous dual-image (picture-in-picture) display has been described to improve fistula identification and surgical planning in diagnostically challenging cases.[1] The EAU Robotic Urology Section consensus on robotic VVF repair recommends preoperative cystoscopic marking of the fistula with a guidewire or ureteral catheter to guide the robotic repair.[2]
Endoscopic Fulguration (Electrocoagulation)
Fulguration has been reported for selected small VVFs.[3] In the 15-case series, a Bugbee electrode was inserted cystoscopically or vaginally for defects 3.5 mm or smaller.[3]
Technique
- Insert a Bugbee electrode into the fistula tract cystoscopically or vaginally.[3]
- Electrocoagulation of the epithelial lining.
- Continuous Foley drainage for 2–3 weeks postoperatively.
- Anticholinergics to suppress detrusor contraction during healing.
Outcomes
- Stovsky series (n = 15, all fistulae ≤3.5 mm): 75% primary-treatment success (9/12) and 2/3 after failed open repair; 11/15 (73%) overall.[3]
- A five-patient series of defects less than 7 mm reported closure in 4/5.[4]
Fulguration has been described as initial treatment for selected fistulae a few millimeters wide and for small residual fistulae after failed open repair.[3] In a review, fulguration with a thin vesicovaginal septum, large fistula or substantial tract inflammation was noted to risk failure, enlargement of the fistula and devitalization of adjacent tissue.[21]
Laser Ablation / Laser Welding
| Modality | Setting | Outcome |
|---|---|---|
| Laser welding: one Nd:YAG, seven holmium:YAG cases | Single-center n = 8, mean fistula 3 mm (range 2–4 mm) | 7/8 dry after catheter removal; mean follow-up 47 months (range 2–110). One procedure was abandoned for bleeding.[5] |
| Holmium ablation + concurrent vaginal repair | Single case report | Cystoscopic laser ablates the bladder-side opening while transvaginal excision addresses the vaginal side.[6] |
| Laser dissection + pneumovesical laparoscopic closure | Single case after colpectomy in a transmasculine patient | Demonstrated feasibility in that anatomy; comparative tissue-injury or efficacy advantages have not been established.[7] |
These small reports support feasibility in selected cases.[5]
Tissue Adhesive Injection (Fibrin Glue / Cyanoacrylate / PRP)
| Approach | Outcome |
|---|---|
| Retrograde endoscopic fibrin glue | 6/8 successes in a mixed urinary-pathology series: seven fistulas of different types (only two VVF) and one caliceal diverticulum.[8] |
| Tissue-adhesive review (84 women; 81 VVF) | Fourteen heterogeneous reports, summarized narratively: 12/84 failures/recurrences. Mean follow-up was about 11.5 months; no controlled comparison established superiority of a sealant. Reported complications included septic pelvic thrombosis.[9] |
| Autologous PRP injection + platelet-rich-fibrin glue interposition | Cystoscopic de-epithelialization of the fistula edges, peri-fistula PRP injection, fibrin glue in the tract. 91.7% (11/12) clinical cure at 6 mo.[10] |
Sealants and platelet products remain selectively used options with limited evidence. The review included defects of 0.1–3.9 cm.
Transurethral NOTES
A transurethral endoscopic suture repair using barbed suture has been described for VVFs after hysterectomy for morbidly adherent placenta. In 3 patients, 2 achieved complete resolution; the third had reduction in fistula size and required subsequent laparotomy. The three-case report describes feasibility without comparing initial approaches.[11]
Transvesicoscopic Repair
Direct placement of laparoscopic ports into the bladder (vesicoscopy) for intravesical visualization and repair:
- Combined vaginal and vesicoscopic repair for complex VVF (n = 9): 89% success at median 30 mo. Four patients required ureteric reimplantation for ureteric involvement. The approach supplements the vaginal route for fistulae not suitable for pure vaginal repair, and pairs the laparoscopic urologist with the vaginal surgeon.[12]
- Robot-assisted transvesical repair via mini cystotomy has been described, particularly when prior surgical planes have been used in failed repairs.[13]
V-NOTES (Vaginal Natural Orifice Transluminal Endoscopic Surgery)
For selected apical VVFs, V-NOTES provides endoscopic visualization through the vaginal route. The 17-patient modified-technique series excluded sepsis, fecaluria and fistulas >2 cm. Initial closure was reported in 15/17 (88.2%), defined by no cystographic leakage on postoperative day 14; both initial failures were cured after a second repair. Mean operative time was 104 min, mean blood loss 10.5 mL and mean stay 3.3 d.[14] See vNOTES & Robotic vNOTES for the broader platform context.
Laparoscopic and Robotic-Assisted Endoscopic Repair
Laparoscopic and robotic repairs are not purely cystoscopic. Reports include:
- Reported closure is 80–100% across selected laparoscopic and robotic series; no randomized comparison establishes equivalence to open repair.[15][16]
- The 2015 review reported 95.9% transvesical and 98.0% extravesical closure across heterogeneous reports, almost entirely case reports/series.[15]
- Laparoendoscopic single-site surgery (LESS) has feasibility reports, including five VVF cases and a mixed GU-fistula cohort.[17][18]
- In a 78-patient retrospective abdominal-repair cohort, closure without leakage at three months was 25/31 after open, 28/31 after laparoscopic and 14/16 after robotic repair. Minimally invasive groups had shorter operations and less blood loss. Prior repair history and timing differed by group; approach was not an independent closure predictor. These are associations within selected groups.[16]
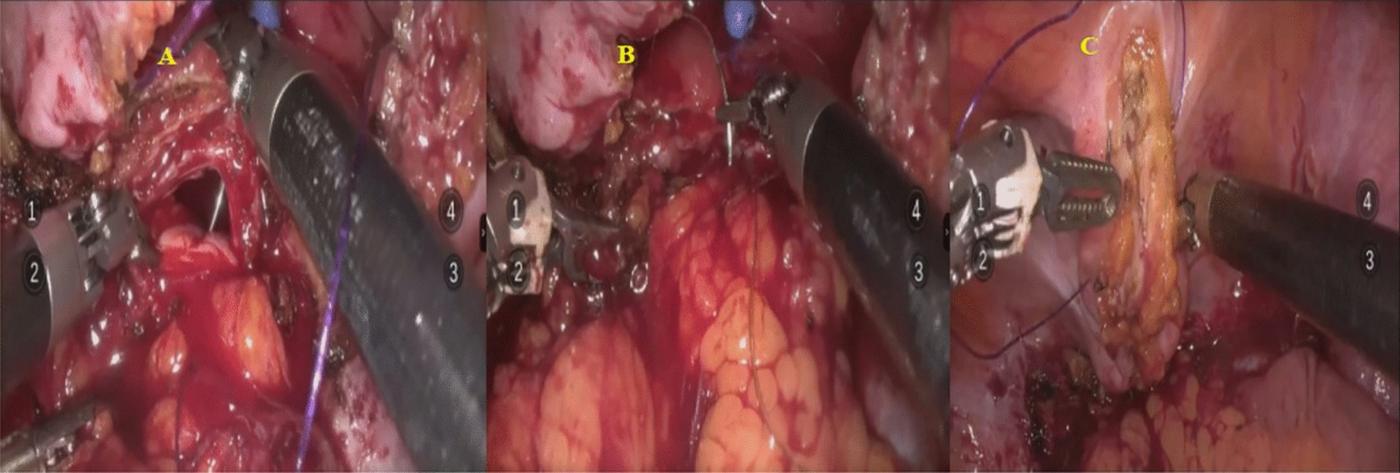
Robotic vesicovaginal fistula repair. (A) Repair of the vaginal wall. (B) Flap interposition. (C) Bladder closure. From Wang Z, et al. Eur J Med Res. 2026;31(1):341, Fig. 2 (CC BY).[16]
Patient Selection and Limits of the Evidence
Select the intervention using defect size, tissue quality, ureteral proximity, access, prior radiation or repair and patient goals.[2][3][5][16]
The 2026 Cochrane item cited below is a protocol for a future review, not completed comparative evidence. Much of the existing endoscopic literature consists of uncontrolled case reports or small series.[19][20]
Common Principles Across Endoscopic Approaches
For reconstructive suture repairs, the common goals are:[2][20]
- Tension-free, watertight closure.
- Well-vascularized tissue.
- Adequate mobilization.
- Protect the ureteral orifices. For robotic repair, the ERUS consensus recommends preoperative ureteral stents, especially when the fistula lies close to an orifice.[2]
- Tailor continuous bladder drainage to the repair and tissue until healing is confirmed. The EAU 2026 guideline gives this a weak recommendation; its expert-opinion durations are 10–14 days for simple or postsurgical fistulae and 14–21 days for complex or postradiation fistulae.[22] For robotic repair, the ERUS consensus describes Foley drainage for 10–14 days and cystography before removal.[2] Cystography may miss a persistent fistula if it omits a voiding phase or the fistula is at the bladder neck.[22] Stovsky used at least two weeks of drainage and Dogra three weeks in small endoscopic series.[3][5] See source-specific drainage guidance.
- Plan the first attempt carefully and refer when the necessary reconstructive expertise is unavailable.
See Also
- Vesicovaginal Fistula (clinical)
- Female Fistula Repair (atlas)
- Fistula Repair Principles
- vNOTES & Robotic vNOTES
- Martius Flap
Videos
References
1. Andreoni C, Bruschini H, Truzzi JC, Simonetti R, Srougi M. Combined vaginoscopy-cystoscopy: a novel simultaneous approach improving vesicovaginal fistula evaluation. J Urol. 2003;170(6 Pt 1):2330–2332. doi:10.1097/01.ju.0000096343.03276.75
2. Randazzo M, Lengauer L, Rochat CH, et al. Best practices in robotic-assisted repair of vesicovaginal fistula: a consensus report from the European Association of Urology Robotic Urology Section Scientific Working Group for Reconstructive Urology. Eur Urol. 2020;78(3):432–442. doi:10.1016/j.eururo.2020.06.029
3. Stovsky MD, Ignatoff JM, Blum MD, et al. Use of electrocoagulation in the treatment of vesicovaginal fistulas. J Urol. 1994;152(5 Pt 1):1443–1444. doi:10.1016/s0022-5347(17)32441-2
4. Shah SJ. Role of day-care vesicovaginal fistula fulguration in small vesicovaginal fistula. J Endourol. 2010;24(10):1659–1660. doi:10.1089/end.2009.0557
5. Dogra PN, Saini AK. Laser welding of vesicovaginal fistula — outcome analysis and long-term outcome: single-centre experience. Int Urogynecol J. 2011;22(8):981–984. doi:10.1007/s00192-011-1389-0
6. Singh R, Schmitt JJ, Knoedler JJ, Occhino JA. Management of a vesicovaginal fistula using holmium laser ablation. Int Urogynecol J. 2016;27(6):969–971. doi:10.1007/s00192-016-3002-z
7. Han G, Zhao R, Liu K, et al. Endoscopic laser dissection combined with laparoscopic pneumovesical repair of vesicovaginal fistula: a novel technique and case report. Urology. 2023;175:223–228. doi:10.1016/j.urology.2023.02.036
8. Sharma SK, Perry KT, Turk TM. Endoscopic injection of fibrin glue for the treatment of urinary-tract pathology. J Endourol. 2005;19(3):419–423. doi:10.1089/end.2005.19.419
9. Bouchard ME, Stairs J, Hickling D, Clancy A, Khalil H. The use of tissue adhesive in management of genitourinary fistulas: a systematic review and case report. Int Urogynecol J. 2023;34(2):445–451. doi:10.1007/s00192-022-05297-0
10. Shirvan MK, Alamdari DH, Ghoreifi A. A novel method for iatrogenic vesicovaginal fistula treatment: autologous platelet-rich plasma injection and platelet-rich fibrin glue interposition. J Urol. 2013;189(6):2125–2129. doi:10.1016/j.juro.2012.12.064
11. Duque-Galán M, Hidalgo-Cardona A, López-Girón MC, Nieto-Calvache AJ. Natural orifice transluminal endoscopic surgery for correction of vesicovaginal fistulas after hysterectomy due to morbidly adherent placenta. J Obstet Gynaecol Can. 2021;43(2):237–241. doi:10.1016/j.jogc.2020.06.029
12. Grange P, Giarenis I, Rouse P, et al. Combined vaginal and vesicoscopic collaborative repair of complex vesicovaginal fistulae. Urology. 2014;84(4):950–954. doi:10.1016/j.urology.2014.06.020
13. Occhino JA, Hokenstad ED, Linder BJ. Robot-assisted vesicovaginal fistula repair via a transvesical approach. Int Urogynecol J. 2019;30(2):327–329. doi:10.1007/s00192-018-3843-8
14. Song X, Jiang C, Lv JW. Transvaginal repair of apical vesicovaginal fistula via vaginal natural orifice transluminal endoscopic surgery (V-NOTES): a modified surgical technique and its outcomes. Sci Rep. 2024;14(1):31095. doi:10.1038/s41598-024-82366-y
15. Miklos JR, Moore RD, Chinthakanan O. Laparoscopic and robotic-assisted vesicovaginal fistula repair: a systematic review of the literature. J Minim Invasive Gynecol. 2015;22(5):727–736. doi:10.1016/j.jmig.2015.03.001
16. Wang Z, Pokhrel G, Yu S, et al. Vesicovaginal fistula repair: comparative analysis of perioperative outcomes and predictors of success in open, laparoscopic, and robotic approaches. Eur J Med Res. 2026. doi:10.1186/s40001-026-03937-5
17. Abdel-Karim A, Elmissiry M, Moussa A, et al. Laparoscopic repair of female genitourinary fistulae: 10-year single-center experience. Int Urogynecol J. 2020;31(7):1357–1362. doi:10.1007/s00192-019-04002-y
18. Abdel-Karim AM, Moussa A, Elsalmy S. Laparoendoscopic single-site surgery extravesical repair of vesicovaginal fistula: early experience. Urology. 2011;78(3):567–571. doi:10.1016/j.urology.2011.05.036
19. Okada Y, Matsushita T, Hasegawa T, et al. Surgical interventions for treating vesicovaginal fistula in women. Cochrane Database Syst Rev. 2026;1:CD015413. Protocol. doi:10.1002/14651858.CD015413
20. Ramphal SR. Laparoscopic approach to vesicovaginal fistulae. Best Pract Res Clin Obstet Gynaecol. 2019;54:49–60. doi:10.1016/j.bpobgyn.2018.06.008
21. Stamatakos M, Sargedi C, Stasinou T, Kontzoglou K. "Vesicovaginal fistula: diagnosis and management." Indian J Surg. 2014;76(2):131–136. doi:10.1007/s12262-012-0787-y
22. European Association of Urology. "EAU Guidelines on Non-neurogenic Female LUTS: Disease Management, section 4.8, Urinary Fistula." 2026. Official guideline