Endorectal Advancement Flap (ERAF) for Rectovaginal Fistula
The endorectal advancement flap (ERAF), with or without sphincteroplasty, is the ASCRS 2022 procedure of choice for most patients with rectovaginal fistulas (RVFs), a strong recommendation based on low-quality evidence (grade 1C). The operation closes the rectal opening and covers it with mobilized, vascularized rectal tissue, so the repair sits on the high-pressure rectal side. Anatomy, anal continence, sphincter integrity, inflammation and previous repairs determine whether a flap alone is appropriate.[1]
See Rectovaginal Fistula and the Female Fistula treatment atlas.
Fistula height, openings, scar, continence and the sphincter complex are assessed. For a new obstetric RVF, ASCRS 2022 typically recommends initial nonoperative care . The guideline describes a usual period of 3 to 6 months to allow acute inflammation and infection to resolve.[1]
A local flap is an option for accessible low or mid-level RVFs of obstetric, cryptoglandular, selected postoperative or selected Crohn's origin when adequate tissue is available. An RVF after a colorectal anastomotic complication often requires transabdominal repair .[1] Fistula height, openings, scar, continence and the sphincter complex are assessed. Endoanal ultrasound or pelvic MRI can delineate sphincter defects and complex tracts. Imaging, examination and continence assessment together guide the choice between a flap alone and repair that includes sphincter reconstruction. Active proctitis and malignancy are contraindications (Jones 1987), and anorectal stricture, poorly perfused irradiated tissue and uncontrolled infection call for a different strategy.[1][4]
- Drain sepsis before elective closure. A draining seton can help a narrow or branching RVF with associated inflammation or abscess.[1]
- Bowel preparation. A mechanical bowel preparation the day before surgery is customary in many practices.
- Coordinate Crohn's treatment. ECCO 2024 supports medical treatment and selected surgical closure of anogenital or rectogenital fistulas through an experienced multidisciplinary team.[3] Its advancement-flap recommendation for complex perianal Crohn's fistulas selects patients without proctitis or anal stenosis.[3]
- Individualize diversion. A stoma may aid symptom control or complex reconstruction, but available RVF flap studies have not established a routine healing benefit for all patients.[1]
In Sonoda's mixed anorectal/RVF cohort, prior abscess drainage and seton placement were associated with healing. These observational findings support attention to infection control.[5]
Operative Framework
The core steps are tract preparation, closure of the internal opening and advancement of a well-perfused rectal flap over it.[1][4] Jones described the operation as elevation of a broad-based rectal flap, curettage of the tract, and advancement and primary suture of the flap over the internal opening.[4]
Positioning and exposure. The prone jackknife position is commonly used for anterior fistulas, and lithotomy is an alternative. A self-retaining anal retractor such as the Lone Star gives circumferential exposure of the anal canal and distal rectum. The internal opening usually lies on the anterior rectal wall at or just above the dentate line.
- Identify the tract and prepare the opening. Curette the fistula tract to remove granulation tissue and epithelialized lining, protecting the remaining sphincter and rectovaginal tissue. Hydrogen peroxide or methylene blue instilled through the vaginal opening can help localize the tract.
- Close the internal opening. Close the rectal side with absorbable suture, commonly 2-0 or 3-0 polyglactin in a figure-of-eight or interrupted pattern. Suture size and pattern are technique choices without a validated prescription.[6]
- Mobilize a broad-based flap. A trapezoid flap is designed with its base proximal and its apex at or just distal to the internal opening. A base at least twice the apex width is a common rule for preserving perfusion, and the flap is elevated several centimeters above the opening (4 to 6 cm in many descriptions) to allow coverage without tension. Some techniques include internal-sphincter or rectal-muscle fibers. Neither maximal thickness nor a fixed flap length is established as optimal for all RVFs.
- Advance and secure the flap. Advance the flap distally over the repaired opening without tension. Offset the flap suture line from the closure of the internal opening so that the two do not overlap. Secure the flap with interrupted absorbable sutures to the surrounding anoderm and mucosa. The donor site heals by secondary intention or is loosely approximated.
- Manage the vaginal side. The vaginal opening is commonly left open for drainage, and some surgeons debride it without closure. The choice depends on drainage needs and the chosen reconstruction.
- Address very low anatomy separately. A rectal mucosal flap brought too distally can cause ectropion. For a very low opening, an anoderm or perianal skin flap or another repair can be used instead of the same rectal flap.[1]
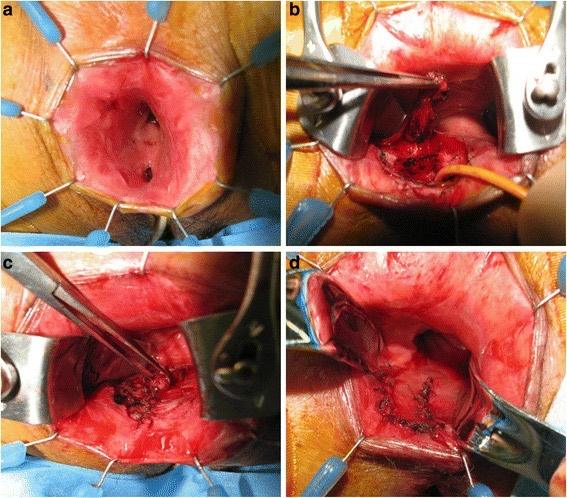
Endorectal advancement flap for rectovaginal fistula through a retracted anal canal: (a) the internal opening seen from the anus; (b) a flap of mucosa, submucosa and circular muscle is raised; (c) the circular muscle is closed with horizontal mattress sutures; (d) the flap is advanced over the repair and sutured at its apex and along its sides. From Kobayashi H, Sugihara K. SpringerPlus. 2015;4:21, Figure 2 (CC BY 4.0).[9]
| Flap variant | Composition | Trade-off |
|---|---|---|
| Full thickness | Mucosa, submucosa and internal sphincter or rectal-wall muscle | Better blood supply; possible greater effect on continence |
| Partial thickness | Mucosa and submucosa only | Less sphincter disruption; possibly a higher failure rate |
ASCRS notes that an advancement flap for fistula-in-ano may include internal-sphincter fibers to preserve blood flow.[1] The choice between full-thickness and partial-thickness flaps is unresolved.[1]
Muscular-plication variant. de Parades described closure of the internal opening with a figure-of-eight absorbable suture, plication of the anorectal muscular layer and mucosal flap advancement in 23 consecutive women. Patients with external-sphincter defects, active Crohn's proctitis, anorectal stricture, malignancy or radiation-related fistulas were excluded. Healing was 15/23 (65%) at mean 14 months; mean Wexner scores were 1.3 before and 0.6 afterward.[6]
When the Sphincter Also Requires Repair
A symptomatic anterior sphincter defect changes the reconstructive goal, because fistula closure and anal continence both need treatment. Options include a flap combined with tailored sphincter reconstruction or episioproctotomy.[1]
Combined technique (commonly described). After the flap is completed, a curvilinear perineal incision exposes the external anal sphincter. The sphincter ends are mobilized from scar and repaired in an overlapping fashion with delayed-absorbable mattress sutures (2-0 polydioxanone or polyglactin in many descriptions). Levatorplasty, which plicates the levator ani anterior to the rectum, is added in some cases to reinforce the rectovaginal septum. The perineal body is then reconstructed.[1][2] See Anal Sphincteroplasty for the sphincter repair itself.
The frequently cited 41% versus 80% healing comparison comes from 52 patients with simple obstetric RVF (48% with varying FI) undergoing 62 procedures: 11/27 advancement-flap procedures and 28/35 sphincteroplasty procedures with or without levatorplasty.[1] The comparison was not randomized and did not add sphincteroplasty to an otherwise identical flap.[1] A 2025 network meta-analysis of 32 low-quality obstetric RVF studies (595 women or procedures) found higher anatomical closure with the Musset procedure and transvaginal or transperineal excision with layered closure than with ERAF. Only 13 studies reported functional outcomes.[10]
Khanduja's 20-patient obstetric series combined mucosal advancement with different sphincter reconstructions, including two-layer repair, one-layer overlap and one isolated internal-sphincter repair. Vaginal stool/flatus discharge resolved in all 20; 14/20 regained perfect anal continence, while six retained liquid-stool or flatus incontinence. Nineteen rated the result excellent or good, and no complications were reported in this small series.[2]
In Li's 2025 retrospective cohort, a fistula diameter greater than 1 cm was associated with flap failure, and two failures were subsequently healed by sphincter repair about six months later. The authors suggested sphincteroplasty as a better choice for these fistulas. The cohort is too small to set a 1-cm threshold or a fixed interval.[7]
Evidence and Counseling
| Study | Population and denominator | What the results support |
|---|---|---|
| Jones 1987 | 39 mixed anorectal fistulas, including 23 RVFs | Overall healing was 27/39 (69.2%). Within the RVF subgroup, healing was 60% with Crohn's disease versus 76.9% with other causes; these are small observational subgroups.[4] |
| Sonoda 2002 | 105 enrolled; 99 followed, including 37 RVFs and 62 anorectal fistulas; median follow-up 17.1 months (range 0.4–66.9) | 63.6% primary healing applies to the whole mixed cohort. Crohn's disease and RVF location were associated with failure.[5] |
| de Parades 2011 | 23 selected RVFs without external-sphincter defects | 15/23 healed after the muscular-plication variant; no controlled comparison establishes its advantage.[6] |
| Li 2025 | 57 simple low/mid RVFs; 19 congenital and 19 obstetric | First-repair success 66.7%; overall 70.2% after repetition of the technique. Larger diameter was associated with failure.[7] |
Corte's 72% overall healing at mean 33 months represents 57/79 patients treated with 286 procedures of many types, only 46 of which were rectal advancement flaps. Major procedures (OR 6.4), a diverting stoma (OR 3.5) and under 9 months between diagnosis and first surgery (OR 2.3) were independent factors associated with per-procedure success. These associations are open to selection and repeated-procedure effects, and the study gives no ERAF-specific success rate.[8]
Factors associated with failure and healing
In Sonoda's retrospective cohort, Crohn's disease (P = 0.027) and RVF as opposed to anorectal fistula (P = 0.002) were associated with failure. Prednisone showed a trend toward failure, and no patient on more than 20 mg/day achieved long-term healing.[5] That finding is not a validated cutoff and is not an instruction to stop steroids abruptly. Increased age (P = 0.011), a history of abscess drainage (P = 0.010), a previous seton (P = 0.025) and short fistula duration (P = 0.003) were associated with healing. No association with healing was detected for diversion or length of hospital stay in that retrospective cohort.[1][5]
Counsel about recurrent fistula, infection or abscess, flap breakdown, septal abscess, ectropion, altered continence and scar-related dyspareunia.[11] After a combined sphincter repair, advise avoiding strong straining during early healing; this advice is consensus based without definitive studies.[11] Closure of vaginal leakage is distinct from anal continence and sexual function. Crohn's activity, prior irradiation, failed repairs and sphincter dysfunction can reduce the likelihood of healing.[1][3][5]
References
1. Gaertner WB, Burgess PL, Davids JS, et al. "The American Society of Colon and Rectal Surgeons clinical practice guidelines for the management of anorectal abscess, fistula-in-ano, and rectovaginal fistula." Dis Colon Rectum. 2022;65(8):964–985. doi:10.1097/DCR.0000000000002473
2. Khanduja KS, Padmanabhan A, Kerner BA, Wise WE, Aguilar PS. "Reconstruction of rectovaginal fistula with sphincter disruption by combining rectal mucosal advancement flap and anal sphincteroplasty." Dis Colon Rectum. 1999;42(11):1432–1437. doi:10.1007/BF02235043
3. Adamina M, Minozzi S, Warusavitarne J, et al. "ECCO Guidelines on Therapeutics in Crohn’s Disease: Surgical Treatment." J Crohns Colitis. 2024;18(10):1556–1582. doi:10.1093/ecco-jcc/jjae089
4. Jones IT, Fazio VW, Jagelman DG. "The use of transanal rectal advancement flaps in the management of fistulas involving the anorectum." Dis Colon Rectum. 1987;30(12):919–923. doi:10.1007/BF02554276
5. Sonoda T, Hull T, Piedmonte MR, Fazio VW. "Outcomes of primary repair of anorectal and rectovaginal fistulas using the endorectal advancement flap." Dis Colon Rectum. 2002;45(12):1622–1628. doi:10.1007/s10350-004-7249-y
6. de Parades V, Dahmani Z, Blanchard P, et al. "Endorectal advancement flap with muscular plication: a modified technique for rectovaginal fistula repair." Colorectal Dis. 2011;13(8):921–925. doi:10.1111/j.1463-1318.2010.02338.x
7. Li X, Shao W, Sun G. "A single-center retrospective analysis of endorectal advancement flaps used for the treatment of simple rectovaginal fistulas." Scand J Gastroenterol. 2025;60(4):307–311. doi:10.1080/00365521.2025.2468493
8. Corte H, Maggiori L, Treton X, et al. "Rectovaginal fistula: what is the optimal strategy? An analysis of 79 patients undergoing 286 procedures." Ann Surg. 2015;262(5):855–860; discussion 860–861. doi:10.1097/SLA.0000000000001461
9. Kobayashi H, Sugihara K. "Successful management of rectovaginal fistula treated by endorectal advancement flap: report of two cases and literature review." SpringerPlus. 2015;4:21. doi:10.1186/s40064-015-0799-8
10. Venara A, Houlet E, Poupard E, et al. "Sphincter repair procedures may be favored in the treatment of obstetrical recto-vaginal fistula: a systematic review of the literature and meta-analysis." Tech Coloproctol. 2025;29(1):95. doi:10.1007/s10151-025-03133-3
11. Ommer A, Herold A, Berg E, Fürst A, Schiedeck T, Sailer M. "German S3-Guideline: rectovaginal fistula." GMS Ger Med Sci. 2012;10:Doc15. doi:10.3205/000166