Urethrovaginal Fistula Repair
Urethrovaginal fistula (UVF) connects the urethra to the vagina. Repair must address closure, continence and unobstructed emptying separately. A vaginal approach is usually feasible; EAU recommends it preferentially, with a weak recommendation. Urethral loss, stricture, radiation injury and associated bladder-neck disease may require more extensive reconstruction.[1][2]
See the Female Fistula treatment atlas and Female Slings & Suspensions.
Define the defect and the functional problem
Prior continence surgery, diverticulectomy, vaginal surgery, obstetric trauma and urethral instrumentation are relevant causes. In Neu's 41-patient referral series, 17 fistulas followed SUI surgery and seven followed diverticulum repair.[3]
Obstetric trauma and vaginal surgery cause most UVFs.[2] Location and complexity guide the plan. After diverticulectomy, a distal fistula beyond the sphincter may present with vaginal voiding or a split stream and may not require repair.[1] A distal fistula lies below the sphincteric mechanism, a mid-urethral fistula at it, and a proximal or bladder-neck fistula may coexist with a VVF. A simple fistula is small and single, with adequate surrounding tissue. A complex fistula is large, has an associated stricture or tissue loss, follows a failed repair or radiation, or coexists with a VVF.
Record the urethral level and length involved, fistula number and size, residual urethral tissue, stricture, vaginal access, radiation, previous repairs and any retained mesh.[1][2] Leakage may be continuous or intermittent.[1][2] A proximal or mid-urethral fistula may present with continuous vaginal leakage or intermittent positional wetness, while a fistula distal to the external sphincter may leak only during or after voiding, with the patient otherwise continent.[23]
| Assessment | Purpose |
|---|---|
| Vaginal examination and observed dye leakage | Identify the vaginal opening and assess tissue quality and access |
| Cystoscopy with careful urethroscopy | Localize the urethral defect, mesh or diverticulum and any additional bladder fistula |
| Urethrogram / VCUG | Clarify a difficult-to-see tract or associated urethral narrowing |
| MRI or CT | Selective imaging for uncertain anatomy, diverticulum, complex disease or suspected upper-tract injury; routine CT urography is unnecessary for every isolated UVF. Because a concomitant ureterovaginal fistula or obstruction can coexist, some sources recommend including upper-tract imaging, such as retrograde, antegrade or CT-urographic pyelography, in the workup of any lower urinary tract fistula rather than only when independently suspected.[25] |
| Continence and emptying assessment | Distinguish leakage through the tract from coexisting SUI, urgency incontinence and obstruction; use urodynamics selectively when it will change reconstruction or sling planning |
The clinical or endoscopic evaluation and selective imaging approach were used in Neu's series.[3] In a double-dye test, upper-tract orange leakage can suggest a ureterovaginal source. Both bladder and urethral fistulas can transmit blue urine from the bladder;[1][4] Examination under anesthesia may help when access is limited; instruments should not be forced through scarred or poorly defined anatomy.
One author favors a lighted speculum during intravesical dye testing to directly observe the leak site and assess tissue mobility and quality. Described troubleshooting includes compressing the urethral meatus with gauze to prevent dye egress there, filling the bladder in 60-mL aliquots, and, if no leak is seen, asking the patient to cough or Valsalva and repositioning the catheter balloon so it does not mask a bladder-neck opening.[23] When anatomic closure needs confirmation in a patient with persistent leakage, occluding the urethral meatus and asking the patient to strain while examining for leakage has also been described as an adjunctive bedside maneuver to distinguish transurethral incontinence from a urethrovaginal fistula.[28]
Timing and initial management
Control infection, protect the skin and assess tissue viability before elective closure. EAU advises individual timing after edema, inflammation, necrosis and infection resolve; it sets no mandatory interval for every etiology.[1]
Described intervals vary by source and clinical context, and none displaces this individualized approach. One source describes proceeding immediately in a nonirradiated patient recognized within 7–10 days of injury, delaying at least 12 weeks when recognition is delayed, waiting a minimum of 2 months after an early recurrent fistula, and delaying definitive repair at least 3–6 months for large or high-risk ischemic, infected or radiation-associated disease.[25] Another describes delaying repair by approximately six weeks after trauma, prior vaginal surgery or recurrence from a previous repair.[24] A third reports that some groups have advocated waiting about 2–3 months when a fistula is discovered a few days after the inciting injury.[23] A chapter addressing UVF after urethral diverticulectomy states that repair should be delayed until at least 3–6 months after the index operation to allow tissue regrowth.[26]
Selected small, recent defects may close with effective urinary drainage, but a reliable UVF-specific spontaneous-closure rate is unavailable. Neither the mixed urogenital-fistula estimate nor the bladder-fistula case report provides a 15% UVF cure rate.[5] An established epithelialized tract, mesh erosion, urethral loss or stricture requires a plan addressing the underlying defect; prolonged drainage alone may not do so.[4][5]
Operative framework
The plan should preserve urethral lumen and length, achieve viable tension-free closure, and provide a separate vaginal cover.[1][2] Route and tissue choice depend on actual anatomy.[1][2]
Transvaginal layered repair
- Identify the defect with urethroscopy and vaginal exposure. A small catheter through a suitable tract can aid localization and traction. When the introitus is too narrow for adequate exposure, a posterolateral vaginal relaxing incision has been described as an option.[29]
- Separate the vaginal wall from the urethral closure plane, preserving viable tissue. Avoid imposing a fixed excision margin that unnecessarily enlarges a tissue-deficient defect.
- Close the urethral defect with absorbable suture, preserving caliber and avoiding tension. Choose orientation according to the defect.
- Provide additional viable coverage with available periurethral tissue and/or selected vascularized interposition, then close the vagina with separated suture lines where possible.
- Maintain dependable urinary drainage, with a urethral catheter and selective suprapubic drainage.
Clifton describes tract localization and layered closure[6]; Neu reports multilayer transvaginal repairs, selective Martius interposition in 9/41 patients and either urethral drainage alone or combined suprapubic and urethral drainage.[3]
One extends vaginal dissection laterally and posteriorly to mobilize the urethra, entering the retropubic space vaginally if needed for additional mobility, approximates the urethral edges extramucosally with fine interrupted delayed-absorbable sutures, inverts that line with a second layer incorporating pubocervical fascia, and closes the vaginal incision separately.[21] Another describes a broad-based inverted-U vaginal flap with its apex beside the cranial fistula margin, lateral and caudal undermining, transverse interrupted absorbable sutures for the first urethral layer incorporating the fistula edges and urethral mucosa, a vertically oriented second periurethral layer, and a leak test injecting methylene blue beside the urethral catheter; a related inverted-U advancement with circumferential mobilization to healthy urethral tissue has also been described.[24][23] A further description identifies and cannulates the tract with a guidewire, ureteral catheter or small catheter, uses saline hydrodissection and broad mobilization for exposure, closes the tract circumferentially with a watertight running absorbable suture (typically 4-0 multifilament) tested by distending the urethra with saline around the catheter while its balloon is drawn back to the bladder neck, then adds a running through-and-through or imbricating second layer; for a defect proximal to the external sphincter, mobilizing the bladder neck or proximal urethra as an advancement cover has also been described to reduce tension.[25]
Interposition and reconstruction options
| Situation | Option and evidence boundary |
|---|---|
| Adequate viable urethral and vaginal tissue | Layered closure may suffice; interposition is not automatically required for every UVF |
| Tenuous closure, tissue deficit, recurrence or radiation injury | A modified Martius labial fat-pad flap can separate closure planes; it is an adjunct to urethral repair, not a standalone closure. EAU recommends an interposition graft for radiation-associated fistula repair . Preserve the bulb and bulbospongiosus in the modified fat-only harvest.[1][7][8] |
| Severe periurethral deficit with SUI | A fascial patch plus autologous pubovaginal sling has been described; Golomb's report was a single patient.[9] In obstetric UVF, a bulbocavernosus muscle flap or wrap has also been used as an anti-incontinence adjunct when bladder-neck or proximal urethral injury leaves sphincter incompetence, with reasonable reported success; the supporting reports concern VVF rather than UVF specifically, so treat this as a source-limited lead rather than demonstrated UVF-specific effectiveness. This muscle flap/wrap is distinct from the modified fat-only Martius harvest above, which preserves the bulb and muscle.[27] |
| Selected refractory defects after prior Martius failure | Bruce's pedicled rectus-muscle series achieved closure in six women, with five continent and emptying fully at mean 23 months. Consider abdominal donor morbidity and flap bulk.[10] |
| UVF with stricture or urethral loss | Individualized anastomosis, flap/graft urethroplasty or neourethral reconstruction; the remaining urethra, vagina and continence mechanism determine feasibility.[11][12] |
| Pelvic-fracture-associated obliteration | A transpubic reconstruction is an option in selected severe injuries. Xu's eight-patient series included one postoperative dilation and one transient SUI.[13] |
See Martius flap for VVF for flap selection, donor morbidity and the distinction between simple-VVF trial evidence and UVF case series.[7] Rangnekar reported UVF closure in 7/8 with Martius versus 1/4 with anatomical repair; the groups were nonrandomized.[7]
Martius flap steps
The steps below follow the standard description of the flap.[8]
- Make a vertical incision over the labium majus on the side of the fistula.
- Dissect the fibroadipose pad from the overlying skin and the underlying bulbospongiosus. Wilson and colleagues describe staying lateral to the bulbocavernosus and ischiocavernosus during posterior mobilization; a medial plane risks significant bleeding, and a superficial plane risks scar deformity.[8] The modified fat-only harvest preserves the bulb and muscle. The pad is generally 8–15 cm long in total, with the length harvested determined by the reach needed to cover the repair.[29]
- Mobilize the pad on an anterior pedicle (external pudendal vessels, for anterior rotation) or a posterior pedicle (internal pudendal vessels, for posterior rotation).
- Create a subcutaneous tunnel from the labial incision to the vaginal field and widen it so the pedicle is not compressed; Wilson and colleagues describe a tunnel admitting at least two fingers.[8]
- Pass the flap and suture it over the urethral closure, between the urethral and vaginal suture lines.
- Close the labial incision primarily.
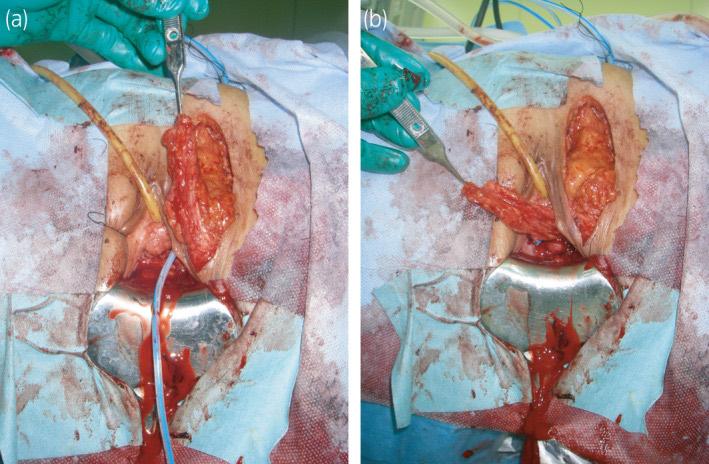
Second urethrovaginal fistula closure with a Martius flap: (a) the flap is raised through a left labial skin incision, with its blood supply monitored by Doppler ultrasound; (b) the flap is passed through a tunnel from the left labium to the vaginal incision and interposed between the urethra and the vaginal wall. From Kato K, et al. IJU Case Rep. 2021;4(6):433-435, Fig. 3 (CC BY 4.0).[30]
Fascial patch with pubovaginal sling
Golomb's single-patient technique addressed recurrent UVF with coexisting SUI after removal of an eroded TVT and a failed repair.[9]
- Make an inverted-U vaginal flap. Identify the prior Martius flap and separate it from the urethra.
- Close the friable, attenuated periurethral tissue in one layer.
- Harvest a 15 × 2 cm strip of rectus fascia through a low transverse abdominal incision.
- Excise a 2 × 2 cm patch from the strip and transfix it to the periurethral tissue over the closure.
- Reposition the Martius flap over the patch and place a pubovaginal sling with the remaining fascia.
Rectus abdominis muscle flap
After transvaginal closure, Bruce's series interposed a pedicled rectus abdominis flap on the inferior epigastric vessels between the fistula closure and the vaginal suture line. The flap also supports the urethra, bladder neck and bladder base.[10] Tunneling of the flap through the retropubic space to the pelvis has been described.
Reconstruction for extensive posterior urethral-wall loss
One description addresses extensive loss of the posterior urethral wall extending toward the trigone. The anterior vaginal wall is mobilized widely beyond the pubic ramus, and the retropubic space is entered bilaterally to gain urethral mobility. The urethral tube is closed over a 10F or 12F catheter with interrupted extramucosal 4-0 delayed-absorbable sutures, reinforced with a periurethral tissue layer and, when usable, a pubocervical-fascia layer. A Martius fat pad is described for vascular support when local tissue is damaged, and a proximal suburethral sling when the urethra including the bladder neck has sloughed, in an effort to preserve continence. When loss of the anterior vaginal wall prevents tension-free vaginal closure, swinging a labial flap into the vagina has been described; sources differ on whether this flap is fibrofatty tissue or skin.[22]
Urethroplasty for UVF with stricture or urethral loss
Xu's 44 patients had five reconstructions chosen by fistula location, stricture length and vaginal anatomy.[11]
| Technique | n | Notes |
|---|---|---|
| Labial pedicle flap urethroplasty | 24 | Xu 2013 described labial pedicle flap urethroplasty as reliable for complex strictures. The 18–22 Fr stent detail comes from Xu 2009: a single labial flap was tubularized over that stent in five of eight pelvic-fracture cases.[11][13] |
| Anterior vaginal flap urethroplasty | 11 | Vaginal-wall flap rolled into a tube or used as an onlay. Blaivas reconstructed 10 women with total or partial urethral loss and extensive vesical-neck/trigonal damage after operative complications, using a vaginal flap rolled into a tube with a labial fat pad over the anastomosis. Nine had a satisfactory neourethra, three required meatotomy, two temporary intermittent self-catheterization, and six were completely continent after one reconstruction that included an anti-incontinence repair.[12] |
| Vulvar flap urethroplasty | 3 | Island vulvar-skin flap, with colpoplasty in 3 patients |
| End-to-end anastomosis | 4 | Short strictures |
| Bladder flap urethroplasty | 2 | Extensive urethral loss |
Latzko partial colpocleisis and Sims-Simon dissection and layered repair are distinct techniques.[14] A Latzko–Martius UVF repair has been reported.[14]
Continence surgery: concurrent or staged
AUA/SUFU 2023 statement 17 says not to use a synthetic midurethral sling during concomitant UVF repair, urethral diverticulectomy or urethral mesh excision .[15] If concurrent SUI surgery is needed, an autologous fascial sling is a described option.[3] Statement 18 says to strongly consider avoiding mesh when radiation, substantial scarring or poor tissue quality compromises healing .[15]
In Neu's retrospective series, 19/41 received a concurrent autologous fascial sling for bothersome SUI established through history, examination and urodynamics. No fistula recurred in that subgroup; two patients had transient retention.[3] This was a selected, single-surgeon cohort.[3]
A staged approach is reasonable when SUI is uncertain, tissue is unsuitable, emptying is problematic or the patient prefers reassessment after closure. Discuss retention, persistent incontinence and later procedures. Prior surgery alone does not prohibit every future synthetic sling; a healed reconstruction still requires individualized tissue-risk assessment.[3][15]
For mesh-associated UVF, define the intraluminal or eroded mesh and associated urethral damage before planning excision and reconstruction. The extent of mesh removal and interposition must match the lesion.[16] One case of diverticulum, mesh excision and Martius repair was successful.[16]
Outcomes and counseling
| Study | Population and result | Interpretation |
|---|---|---|
| Pushkar 2006 | 71 UVFs: 64 closed after the first repair, 70 after a second; SUI reported in 37/71 | The very long follow-up subgroup contained only 21 patients, not all 71.[2] |
| Neu 2021 | 41 UVF repairs, two recurrences; median follow-up 21 months | Retrospective referral cohort, including 12 previous repair failures; 19 concurrent autologous slings.[3] |
| Xu 2013 | 44 selected UVFs with stricture: 41/44 anatomical and 40/44 functional successes, mean follow-up 42.3 months | Five reconstruction types selected by anatomy; no randomized comparison establishing a superior flap.[11] |
| Lee & Zimmern 2016 | 18 nonirradiated UVFs, 95% closure; six underwent subsequent procedures during mean 52-month follow-up | Subsequent procedures addressed incontinence, residual mesh or stricture.[17] |
In Ockrim's mixed tertiary cohort (32 VVF, 9 UVF), fistula size above 3 cm (P = 0.02) and unavailable tissue for interposition were the main determinants of failure. Transvaginal repair closed 8 of 9 UVFs.[19]
A 2024 systematic review encompassing VVF, UVF and bladder neck–vaginal fistulas (46 studies) found insufficient evidence to determine whether interposition or a fascial sling improves fistula closure; neither showed a statistically significant benefit in the available comparisons.[20]
Persistent leakage after closure also needs reassessment for SUI, urgency incontinence or another tract before assuming recurrent UVF.
Drainage and follow-up
Maintain drainage until healing is adequately assessed; tailor duration to the urethral repair, tissue and complications. A randomized trial of 524 women with simple genital fistulas already closed at postoperative day seven supported seven rather than fourteen days in that selected population.[18]
Plan catheter removal with clinical assessment and selective imaging, including a voiding phase when needed to demonstrate a urethral or bladder-neck leak. Reassess vaginal leakage, wound healing, emptying and PVR, continence and pain after removal. Treat infection when present and address catheter obstruction or troublesome bladder spasms promptly. Vaginal intercourse and heavy straining are deferred until healing is confirmed, with the interval set by the surgeon. Later cystourethroscopy is driven by suspected residual mesh, stricture, persistent leakage or other findings rather than an obligatory schedule for every uncomplicated repair.[1][3]
One leaves both urethral and suprapubic catheters after repair, with the suprapubic tube plugged and opened for drainage if the urethral catheter stops draining; the urethral catheter is removed at about 2–3 weeks with a voiding cystourethrogram, and if extravasation persists, the suprapubic tube is left to gravity drainage with imaging repeated about two weeks later without reinserting the urethral catheter, then the suprapubic tube is removed once residuals are consistently below 100 mL.[24] A separate description similarly keeps the urethral catheter for 2–3 weeks even when a suprapubic catheter is present, then checks repair integrity with a voiding cystourethrogram or, without a suprapubic tube, a peri-catheter retrograde urethrogram before removal.[25]
Videos
References
1. European Association of Urology. "Non-neurogenic Female LUTS: urinary fistula." 2026. Official guideline, sections 4.8.3–4.8.4.
2. Pushkar DY, Dyakov VV, Kosko JW, Kasyan GR. "Management of urethrovaginal fistulas." Eur Urol. 2006;50(5):1000–1005. doi:10.1016/j.eururo.2006.08.002
3. Neu S, Locke J, Goldenberg M, Herschorn S. "Urethrovaginal fistula repair with or without concurrent fascial sling placement: a retrospective review." Can Urol Assoc J. 2021;15(5):E276–E280. doi:10.5489/cuaj.6786
4. Rogers RG, Jeppson PC. "Current diagnosis and management of pelvic fistulae in women." Obstet Gynecol. 2016;128(3):635–650. doi:10.1097/AOG.0000000000001519
5. Hillary CJ, Osman NI, Hilton P, Chapple CR. "The aetiology, treatment, and outcome of urogenital fistulae managed in well- and low-resourced countries: a systematic review." Eur Urol. 2016;70(3):478–492. doi:10.1016/j.eururo.2016.02.015
6. Clifton MM, Goldman HB. "Urethrovaginal fistula closure." Int Urogynecol J. 2017;28(1):157–158. doi:10.1007/s00192-016-3111-8
7. Rangnekar NP, Imdad Ali N, Kaul SA, Pathak HR. "Role of the Martius procedure in the management of urinary-vaginal fistulas." J Am Coll Surg. 2000;191(3):259–263. doi:10.1016/s1072-7515(00)00351-3
8. Wilson A, Pillay S, Greenwell T. "How and why to take a Martius labial interposition flap in female urology." Transl Androl Urol. 2017;6(Suppl 2):S81–S87. doi:10.21037/tau.2017.04.38
9. Golomb J, Leibovitch I, Mor Y, Nadu A, Ramon J. "Fascial patch technique for repair of complicated urethrovaginal fistula." Urology. 2006;68(5):1115–1118. doi:10.1016/j.urology.2006.06.001
10. Bruce RG, El-Galley RE, Galloway NT. "Use of rectus abdominis muscle flap for the treatment of complex and refractory urethrovaginal fistulas." J Urol. 2000;163(4):1212–1215. PubMed. doi:10.1016/s0022-5347(05)67726-9
11. Xu YM, Sa YL, Fu Q, et al. "A rationale for procedure selection to repair female urethral stricture associated with urethrovaginal fistulas." J Urol. 2013;189(1):176–181. doi:10.1016/j.juro.2012.09.005
12. Blaivas JG. "Vaginal flap urethral reconstruction: an alternative to the bladder flap neourethra." J Urol. 1989;141(3):542–545. doi:10.1016/s0022-5347(17)40887-1
13. Xu YM, Sa YL, Fu Q, et al. "Transpubic access using pedicle tubularized labial urethroplasty for the treatment of female urethral strictures associated with urethrovaginal fistulas secondary to pelvic fracture." Eur Urol. 2009;56(1):193–200. doi:10.1016/j.eururo.2008.04.046
14. Zilberlicht A, Lavy Y, Auslender R, Abramov Y. "Transvaginal repair of a urethrovaginal fistula using the Latzko technique with a bulbocavernosus (Martius) flap." Int Urogynecol J. 2016;27(12):1925–1927. doi:10.1007/s00192-016-3085-6
15. Kobashi KC, Vasavada S, Bloschichak A, et al. "Updates to surgical treatment of female stress urinary incontinence (SUI): AUA/SUFU guideline (2023)." J Urol. 2023;209(6):1091–1098. doi:10.1097/JU.0000000000003435 Full guideline, statements 17–18.
16. Smith A, Burton L, Mama S. "Surgical approach to urethral diverticulum and urethrovaginal fistula with mesh erosion." Int Urogynecol J. 2024;35(6):1327–1329. doi:10.1007/s00192-024-05787-3
17. Lee D, Zimmern PE. "Long-term functional outcomes following non-radiated urethrovaginal fistula repair." World J Urol. 2016;34(2):291–296. doi:10.1007/s00345-015-1601-9
18. Barone MA, Widmer M, Arrowsmith S, et al. "Breakdown of simple female genital fistula repair after 7 day versus 14 day postoperative bladder catheterisation: a randomised, controlled, open-label, non-inferiority trial." Lancet. 2015;386(9988):56–62. doi:10.1016/S0140-6736(14)62337-0
19. Ockrim JL, Greenwell TJ, Foley CL, Wood DN, Shah PJ. "A tertiary experience of vesico-vaginal and urethro-vaginal fistula repair: factors predicting success." BJU Int. 2009;103(8):1122–1126. doi:10.1111/j.1464-410X.2008.08237.x
20. Thompson JC, Halder GE, Jeppson PC, et al. "Repair of vesicovaginal fistulae: a systematic review." Obstet Gynecol. 2024;143(2):229–241. doi:10.1097/AOG.0000000000005468
21. Karram MM. Repair of Urethrovaginal Fistula. In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:1031-1036.
22. Karram MM. Martius Fat Pad Transposition and Urethral Reconstruction. In: Baggish MS, Karram MM, eds. Atlas of Pelvic Anatomy and Gynecologic Surgery. 5th ed. Elsevier; 2021:1049-1056.
23. Gonzales-Alabastro C, Goyette B, Kielb SJ. Urethrovaginal Fistula Repair. In: Martins FE, Holm HV, Sandhu JS, McCammon KA, eds. Female Genitourinary and Pelvic Floor Reconstruction. Springer; 2023:693-705.
24. Uberoi P, Kobashi KC. Management of Urethrovaginal Fistula. In: Cardozo L, Staskin D, eds. Textbook of Female Urology and Urogynecology. Vol 2: Surgical Perspectives. 5th ed. CRC Press; 2023:1185-1188.
25. Goldenberg MG, Ginsberg DA. Urethrovaginal Fistula. In: Sotelo R, Polotti CF, Arriaga J, eds. Urinary Fistula. Springer; 2022:161-174.
26. Lee R, Dreyfuss L. Urethral Diverticulectomy. In: Hoffman M, Hull TL, Bochner BH, eds. Major Complications of Female Pelvic Surgery: A Multidisciplinary Approach. Springer; 2025:93-101. doi:10.1007/978-3-031-66772-5_9
27. Ndoye M, Greenwell T. Obstetric Fistula. In: Sotelo R, Polotti CF, Arriaga J, eds. Urinary Fistula. Springer; 2022:197-228. doi:10.1007/978-3-031-15317-4_16
28. Mourad MS, Higazy AMGA. Complications of Vaginal Fistula Repair. In: Sotelo R, Polotti CF, Arriaga J, eds. Urinary Fistula. Springer; 2022:333-341. doi:10.1007/978-3-031-15317-4_24
29. Kobashi KC, Lee EW, Rapp DE, Chen A. Urethrovaginal Fistula Repair. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:660-664.
30. Kato K, Suzuki A, Hayashi Y, et al. "Urethrovaginal fistula 11 years after a bone anchor sling using woven polyester and treatment with a Martius flap." IJU Case Rep. 2021;4(6):433–435. doi:10.1002/iju5.12374