York-Mason Posterior Transsphincteric Repair for Rectourethral Fistula
The York–Mason repair exposes a rectourethral fistula (RUF) through a posterior transsphincteric incision. It is an established option for selected, usually nonirradiated iatrogenic fistulas when the rectal defect can be closed through posterior exposure; urinary-side closure depends on the technique variant.[18] The operation deliberately divides and reconstructs the anal sphincter. In a study using patient questionnaires, 2 of 10 respondents reported rare fecal incontinence despite a low mean symptom score.[2][3][4]
Route selection depends on fistula level, tissue quality, radiation injury, urinary outlet function, baseline bowel function and previous repairs. Compare Transperineal RUF Repair, Endorectal Advancement Flap and Transanal Minimally Invasive Repair.
Selection and Preparation
The posterior route can provide access to the anterior rectal fistula opening while avoiding some previously operated anterior tissues. It is most attractive when the urinary defect can be closed without extensive urethral reconstruction and the rectal and urinary tissues are suitable for healing. Radiation damage, active infection, major tissue loss, outlet stenosis and multiple previous repairs may require vascularized interposition, another route or, in a devastated urinary or intestinal system, definitive diversion. No validated size-based algorithm exists; these decisions are individualized.[2][8][11][15][16]
Before repair, define the urinary and rectal openings by directed endoscopy and appropriate imaging, assess continence and sphincter function, and establish drainage and control of infection. Discuss possible persistent urinary incontinence even after successful fistula closure. Fecal diversion varies among centers: the original Utah rectourinary series (13 rectourethral and 11 rectovesical fistulas) included 11 of 24 patients treated without prior urinary or fecal diversion, whereas the 2025 Dutch cohort used colostomy before or during repair in all 12 patients.[2][4][5]
Bowel preparation, antimicrobial prophylaxis and urinary drainage should follow the planned colorectal and urinary operation and local protocols. A fixed three-month trial of catheterization before all repairs is not established by comparative evidence; the prolonged catheterization pathway in the 2025 report was that institution's practice.[2]
Surgical Technique
The following outlines the shared operative principles. Published modifications differ in incision, closure and interposition; the 2025 technical description uses a right-sided U-shaped incision rather than a classic posterior midline incision.[2]
- Position and expose. Use a prone position with hip flexion and buttock retraction to expose the posterior anal region, with careful pressure protection and an agreed plan for urinary access.
- Identify and mark the divided layers. Enter through the posterior or paraposterior approach. As sphincter and rectal-wall layers are divided, tag corresponding edges so they can be matched during reconstruction. Accurate matching of the layers is needed for sphincter repair.
- Expose the fistula on the anterior rectal wall. Define the communication and develop the plane between rectal and urinary tissues under direct vision. Excise the tract and mobilize suitable tissue while preserving enough vascularized wall for tension-free closure; avoid indiscriminate removal of scar that would enlarge the defect unnecessarily.
- Close the defects according to the selected variant. In the 2025 technique, close the urinary side and leak-test it before separate rectal closure.[2] The Montsouris modification instead leaves the urethral side open and closes only the anterior rectal wall in nonoverlapping layers.[18] Minimize tension and preserve viable tissue; selected variants add an interposition graft or flap.
- Reconstruct the posterior access. Reapproximate the divided rectal and sphincter layers using the marking sutures to match the original anatomy, then close the superficial tissues.[2][3][5][6]
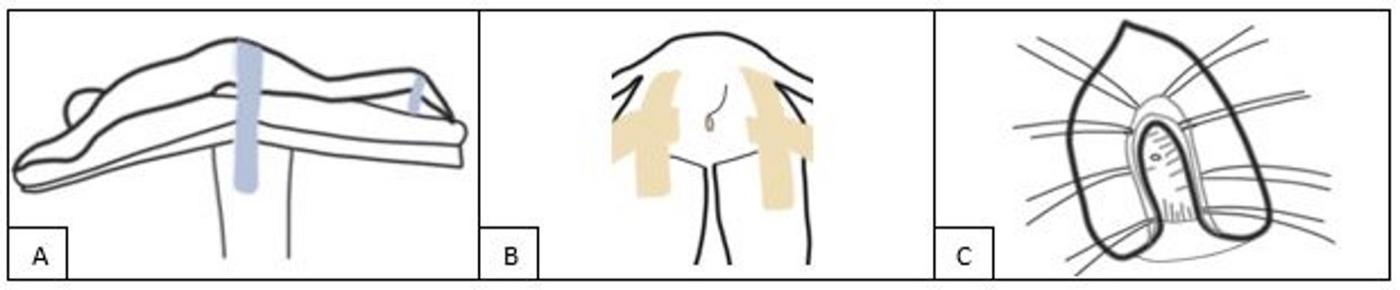
York-Mason positioning and access: (A) prone position with fixation straps (blue); (B) incision (gray) extending from the anus, with both gluteal regions held back by adhesive tape; (C) rectal wall, puborectalis and the internal and external sphincter layers, with multiple sutures placed to identify the fistula. From van der Graaf SH, et al. World J Urol. 2025;43(1):604, Fig. 2 (CC BY 4.0).
Postoperative Management
Maintain urinary drainage and document healing before catheter removal. For example, the Dutch series used a Foley catheter and cystogram at three weeks, with selected proctoscopy. Persistent leakage warrants reassessment and continued drainage rather than automatic catheter removal.[2]
Stoma reversal requires confirmation of fistula healing and assessment of bowel function, urinary status and fitness for another operation. The Dutch protocol considered reversal at least three months after successful repair, but actual reversal timing varied and some patients retained their colostomy. Closure, stoma reversal and continence should be recorded as separate outcomes.[2][5][9]
Modifications and Their Evidence
- Free gluteal fat graft. McKibben et al. interposed buttock fat between the urinary and rectal closures. This is a free graft, not a vascularized pedicled flap. Fistula closure occurred in 16 of 17 patients, with an additional harvest wound; this uncontrolled series had no closure-alone comparator.[3]
- Dartos flap. Dafnis reported vascularized scrotal dartos interposition combined with York–Mason repair in five patients, all with closure at median 70 months. All were diverted; only three had undergone reversal when bowel continence was assessed. The Dafnis series had no comparator and assessed bowel continence after reversal in only three patients.[9]
- Modified Montsouris technique. In a 30-patient nonirradiated series, closure was 80% after the first procedure, 97% after two and 100% after three. Success after repeat repair is a different quantity from first-operation success.[6]
Outcomes by Series
These are heterogeneous retrospective reports.[4][7][5][9] The Utah reports overlap, and the 2024 Dafnis dartos series includes a case from his 2018 cohort.[4][7][5][9]
| Series | Population and closure result | Follow-up and interpretation |
|---|---|---|
| Renschler & Middleton 2003 | 24 rectourinary fistulas (13 rectourethral, 11 rectovesical); 22 closed with York–Mason, including one repeat procedure; another closed after perineal salvage | “30 years” describes the experience/recruitment period, not 30-year follow-up for every patient. No fecal incontinence or anal stenosis was reported.[4] |
| Hadley 2012 | Update to the Utah experience: 51 patients with rectourethral or rectovesical fistulas, including 27 additional patients; 25 of those 27 closed after one York–Mason procedure | “40 years” is the center's experience period. The updated failures involved radiation. The earlier 24 patients overlap the preceding report.[7] |
| Falavolti 2013 | 39 iatrogenic fistulas; more than 50% remained fistula-free during follow-up overall, and almost 90% of patients with only one previous operation remained fistula-free during follow-up | Previous-operation burden was associated with outcome.[1] |
| Bergerat 2018 | 30 nonirradiated patients; 80% first-procedure closure, 100% after up to three procedures | Median 76 months; no acquired urinary or durable fecal incontinence reported.[6] |
| Dafnis 2018 | 18 of 20 closed | Among the 18 successful repairs, median follow-up was 84.7 months. All 20 had diversion before or during repair; 13 had stoma reversal and were reported continent.[5] |
| McKibben 2018 | 16 of 17 closed after modified repair with a free fat graft | Median 39.4 months; only 10 completed the fecal-continence questionnaire. Two reported rare fecal incontinence and two frequent flatal incontinence; mean Wexner score 1.4/20.[3] |
| Dal Moro 2011 | 14 initially closed; one patient with Crohn's disease developed recurrence 11 years later | “20 years” is the experience period.[10] |
| van der Graaf 2025 | 12 total patients; 8 nonirradiated patients receiving York–Mason as their first fistula operation all closed | Median 5.1 years applies to that eight-patient subgroup. Only five underwent colostomy reversal; their LARS scores were 0–20. Other patients had prior failed repairs and/or radiation, with mixed results.[2] |
| Fengler & Abcarian 1997 | Eight patients, including five with radiation exposure; all closed | Small historical series; reported stool continence.[14] |
| Dafnis 2024 | Five patients with dartos interposition; all closed | Median 70 months; all diverted, three reversed. No comparative group.[9] |
Continence and Other Harms
Older series often report no fecal incontinence. In McKibben's questionnaire study, the low average Wexner score coexisted with symptoms in individual respondents. None sought treatment or reported lifestyle impairment, which is different from reporting no symptoms.[3]
Counsel about recurrent fistula, wound complications, potential sphincter dysfunction, anal narrowing and persistent urinary incontinence. Classic York–Mason avoids a remote muscle-flap harvest, but added fat grafts or dartos flaps introduce donor-site considerations. Complication risks remain imprecise in small series reporting none.[2][3][4][9][10]
Radiation, Previous Repairs and Route Selection
Radiation can impair tissue vascularity and complicate both urinary and rectal reconstruction. In the 2025 study, one patient irradiated before prostatectomy healed and one irradiated afterward did not.[2][7][14]
The 37-patient Hanna cohort illustrates treatment selection: irradiated patients more often needed tissue interposition or exenteration and had lower stoma-reversal rates than nonirradiated patients.[15] Vanni's 74-patient transperineal muscle-interposition series reported one-operation closure in 100% of nonirradiated and 84% of irradiated or ablated patients.[12]
| Operative consideration | York–Mason | Transperineal reconstruction with interposition |
|---|---|---|
| Access | Direct posterior transsphincteric exposure of the anterior rectal defect | Perineal access to urinary and rectal tissues |
| Anal sphincter | Deliberately divided and reconstructed | Usually avoids deliberate division of the anal sphincter |
| Interposition | Classic repair may omit it; graft/flap modifications exist | Facilitates vascularized tissue interposition and selected urinary reconstruction |
| Main decision | Suitability of the defect and tissues for closure through this exposure | Need for broader reconstruction, tissue support or management of compromised tissue |
| Outcomes | Closure and bowel function require separate assessment | Closure, bowel function and urinary continence likewise require separate assessment |
The 2022 transperineal gracilis series achieved closure in 20 of 21 patients, but 11 of 18 questionnaire respondents reported significant urinary incontinence. Its mean St Mark's bowel score was 5 out of 24 points. This is another reason to avoid cross-series claims that one approach guarantees better function.[13]
Among the 90% of 416 patients assigned to four repair categories in the 2013 systematic review, 15.7% underwent transsphincteric repair and 65.9% transperineal repair.[8] More recent reviews continue to find heterogeneous, largely retrospective evidence and no single operation appropriate for every fistula. A 2026 four-center retrospective comparison (27 York–Mason, 30 transperineal gracilis repairs) reported first-attempt closure of 44% versus 77% and 12-month reintervention-free survival of 68.2% versus 94.7%, respectively, with unequal median follow-up (27 versus 53 months).[17] Within the York–Mason group, complex morphology was associated with failure (HR 6.5, 95% CI 1.15–36.8).[17] The 2026 post-prostatectomy review included 455 patients and reported surgical closure ranging from 41% to 100%.[16]
Videos
References
1. Falavolti C, Sergi F, Shehu E, Buscarini M. "York Mason procedure to repair iatrogenic rectourinary fistula: our experience." World J Surg. 2013;37(12):2950–2955. doi:10.1007/s00268-013-2199-y
2. van der Graaf SH, Wit EMK, Beets GL, et al. "Management in robot-assisted radical prostatectomy patients with recto-urethral fistulas: the York-Mason technique." World J Urol. 2025;43(1):604. doi:10.1007/s00345-025-05996-5
3. McKibben MJ, Fuchs JS, Rozanski AT, et al. "Modified transanosphincteric (York Mason) repair of nonradiated rectourinary fistulae: patient-reported fecal continence outcomes." Urology. 2018;118:220–226. doi:10.1016/j.urology.2018.05.010
4. Renschler TD, Middleton RG. "30 years of experience with York-Mason repair of recto-urinary fistulas." J Urol. 2003;170(4 Pt 1):1222–1225. doi:10.1097/01.ju.0000082013.58783.17
5. Dafnis G. "Transsphincteric repair of rectourethral fistulas: 15 years of experience with the York Mason approach." Int J Urol. 2018;25(3):290–296. doi:10.1111/iju.13518
6. Bergerat S, Rozet F, Barret E, et al. "Modified York Mason technique for repair of iatrogenic recto-urinary fistula: 20 years of the Montsouris experience." World J Urol. 2018;36(6):947–954. doi:10.1007/s00345-018-2212-z
7. Hadley DA, Southwick A, Middleton RG. "York-Mason procedure for repair of recto-urinary fistulae: a 40-year experience." BJU Int. 2012;109(7):1095–1098. doi:10.1111/j.1464-410X.2011.10472.x
8. Hechenbleikner EM, Buckley JC, Wick EC. "Acquired rectourethral fistulas in adults: a systematic review of surgical repair techniques and outcomes." Dis Colon Rectum. 2013;56(3):374–383. doi:10.1097/DCR.0b013e318274dc87
9. Dafnis G. "Transsphincteric repair of rectourethral fistulas in combination with dartos muscle flap interposition following radical prostatectomy." Urology. 2024;191:130–135. doi:10.1016/j.urology.2024.05.041
10. Dal Moro F, Secco S, Valotto C, et al. "Twenty-year experience with surgical management of recto-urinary fistulas by posterior sagittal transrectal approach (York-Mason)." Surgery. 2011;150(5):975–979. doi:10.1016/j.surg.2011.04.004
11. Lo Re M, Pezzoli M, Garcia Rojo E, et al. "A systematic review on the surgical management of acquired rectourethral fistula." Int J Impot Res. 2026;38(3):214–225. doi:10.1038/s41443-025-01100-y
12. Vanni AJ, Buckley JC, Zinman LN. "Management of surgical and radiation-induced rectourethral fistulas with an interposition muscle flap and selective buccal mucosal onlay graft." J Urol. 2010;184(6):2400–2404. doi:10.1016/j.juro.2010.08.004
13. Sbizzera M, Morel-Journel N, Ruffion A, et al. "Rectourethral fistula induced by localised prostate cancer treatment: surgical and functional outcomes of transperineal repair with gracilis muscle flap interposition." Eur Urol. 2022;81(3):305–312. doi:10.1016/j.eururo.2021.09.017
14. Fengler SA, Abcarian H. "The York Mason approach to repair of iatrogenic rectourinary fistulae." Am J Surg. 1997;173(3):213–217. doi:10.1016/s0002-9610(96)00015-3
15. Hanna JM, Turley R, Castleberry A, et al. "Surgical management of complex rectourethral fistulas in irradiated and nonirradiated patients." Dis Colon Rectum. 2014;57(9):1105–1112. doi:10.1097/DCR.0000000000000175
16. de Angelis M, Scilipoti P, Leni R, et al. "Clinical and surgical management of recto-urinary fistula after radical prostatectomy: a systematic review on current evidence." Prostate Cancer Prostatic Dis. 2026. doi:10.1038/s41391-026-01114-7
17. Long Depaquit T, Michel F, Madec FX, et al. "Comparison of rectourethral fistula repairs: york mason vs. transperineal repair with gracilis flap interposition." World J Urol. 2026;44(1):198. doi:10.1007/s00345-026-06316-1
18. Kasraeian A, Rozet F, Cathelineau X, Barret E, Galiano M, Vallancien G. "Modified York-Mason technique for repair of iatrogenic rectourinary fistula: the montsouris experience." J Urol. 2009;181(3):1178–1183. doi:10.1016/j.juro.2008.10.160