Interposition Flap Options for Vaginal Fistula Repair
Choose tissue interposition according to the fistula's location, vascularity, tissue loss, prior repairs and the patient's functional priorities. A vascularized flap brings its own blood supply; a free graft must take on a suitable recipient bed. Sealants, scaffolds and platelet preparations are different adjuncts. None substitutes for exposure, viable tissue, control of infection, tension-free reconstruction and appropriate drainage.[2][3][4]
Operative steps belong in the dedicated Martius, O'Conor, extravesical, Latzko and Sims–Simon pages.
When Does a Flap Help?
Interposition can separate closure lines, fill dead space and replace deficient vascularized tissue. These advantages must be weighed against harvest morbidity, added dissection, bulk and whether the flap reaches without tension or pedicle compromise. Radiation, recurrence, urethral loss and vaginal stenosis often increase the need for additional tissue. The 2026 EAU Non-neurogenic Female LUTS guideline gives a weak recommendation to use an interposition graft when repairing radiation-associated urinary fistulae; it does not require a particular flap.[2][4][5][53]
The Kapriniotis review found that interposition has been almost completely abandoned in obstetric fistulas, where large series report closure above 90% with graftless repair.[2] Most simple, non-irradiated iatrogenic fistulas close in 86% to 100% with or without interposition.[2] The Martius fat pad is valued when tension-free layered closure is difficult, when tissue loss is significant, when the urethra is involved and in poorly vascularized irradiated tissue, with reported success of 80% to 97% in those settings.[2] Woo and colleagues considered interposition likely to improve outcome and named omentum as the first-choice tissue in a transabdominal repair.[5]
Randomized evidence exists for simple VVF. Singh et al. randomized 126 patients to flap or no flap within the clinically selected vaginal or abdominal route. Vaginal closure occurred in 27/29 with Martius versus 27/28 without; abdominal closure in 34/35 with omentum versus 33/34 without. Neither comparison was statistically significant. Mean follow-up was 39.6 months; 9/29 Martius recipients reported harvest-site numbness or pain versus none without Martius. The trial excluded complex and complicated fistulas, including previous failed repairs and radiation-associated cases.[51]
The 2026 Cochrane item is a review protocol.[1] Most complex-fistula evidence remains observational. A 2024 comparative systematic review did not demonstrate a difference in vaginal fistula closure with interposition versus no flap (six studies, n = 924; RR 0.98, 95% CI 0.96–1.01).[52]
| Evidence | What it supports |
|---|---|
| Mörgeli: 50 nonradiogenic urogenital fistulas, including 34 VVF | All 47 modified Sims–Simon repairs succeeded; the 47 were not an exclusively VVF cohort.[6] |
| Miklos: 44 laparoscopic extravesical VVF repairs | Overall closure was 43/44; 42/43 repairs without omentum succeeded.[7] The systematic review also comprised heterogeneous, predominantly small observational reports.[8] |
| Evans: retrospective abdominal VVF series | In benign cases, closure was 10/10 with versus 12/19 without interposition. The often-quoted 12/12 flap total includes two malignant cases. Selection and small numbers prevent a universal flap mandate.[9] |
| Rangnekar: 46 urinary–vaginal fistulas, including 34 VVF and 12 urethrovaginal | Recurrent-fistula closure was 11/12 with Martius versus 3/7 without. This was not a randomized comparison.[10] |
| Eilber: 207 vaginal VVF repairs, 159 with previous repair | Interposition was used in 120: 83 peritoneal, 34 Martius and 3 full-thickness labial. Initial-repair cure rates were 96%, 97% and 33%, respectively; very different selection and denominators preclude ranking these flaps.[11] |
The ERUS robotic report is expert consensus informed by published series.[12]
Native Vaginal-Wall Reconstruction
Local vaginal tissue may provide an additional layer without a separate labial, thigh or abdominal donor incision. It still requires adequate vascularity and mobility and can cause local scarring or distortion.
- Shoukry vaginal flap reinforcement. A circumferential incision is made around the fistula and the tract is excised. A rectangular vaginal flap is raised just proximal to the fistula. After bladder closure, the flap's distal edges are dissected, and the flap is mobilized and interposed between bladder and vagina as a third layer, and the vagina is closed over it. All 20 low VVFs were dry at mean 16 ± 9 months with no added morbidity; comparative benefit and sexual-function preservation were not established.[37]
- Wang flap-transfer coverage. The patient is placed in a prone split-leg position for exposure, and a lateral free vaginal flap is transferred so that the fistula lies away from the incision suture line. The authors regard that displacement as the key to success and note that vaginal length is maintained. Primary healing occurred in 34/37; the three recurrences closed after repeat repair.[17]
- Tang annular vaginal flap. A retrospective comparison of 17 transvaginal and 40 transvesical repairs reported initial success of 82.3% and 75%, respectively. The transvaginal group had shorter operative time, less blood loss, shorter stay, lower cost and fewer minor complications (p < 0.05). Route selection was not randomized.[38]
- Vaginal cuff flap. In the robotic technique the vaginal apex is dissected, the VVF excised and the bladder closed, and a cuff flap is harvested and interposed between bladder and vagina. The authors propose it when omentum is unavailable. The reported patient had a radiation-associated VVF and RVF and also received 37 hyperbaric sessions and a later transvesical endoluminal closure before sustained healing at 30-month follow-up.[39]
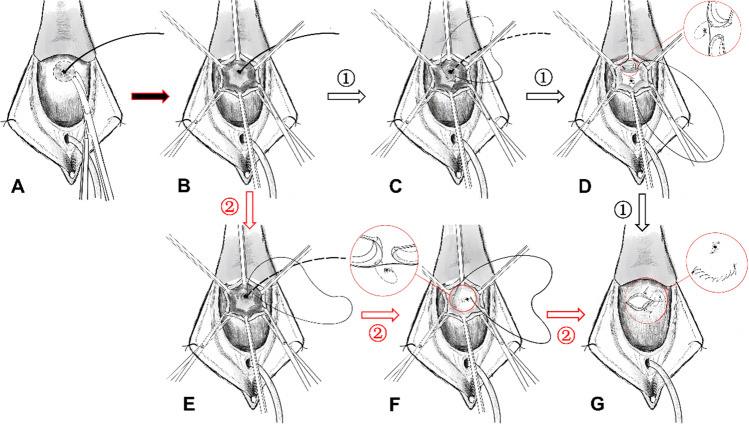
Flap-transfer coverage of vesicovaginal fistula. (A) Circumferential incision at least 0.5 cm from the fistula opening. (B) The surrounding vaginal flap freed by at least 2 to 3 cm. (C, E) Continuous closure of the fistula. (D, F) The fistula suspended and buried behind the transferred apical (pathway 1) or lateral (pathway 2) free flap. (G) Vaginal mucosa closed with the suture lines offset. From Wang X, et al. Int Urogynecol J. 2023;34(8):1797-1802, Fig. 2 (CC BY).[17]
Latzko partial colpocleisis de-epithelializes tissue around the fistula and imbricates the underlying tissue; it does not bury intact vaginal epithelium as its reinforcing layer. Vaginal shortening depends on the defect and extent of closure. Discuss vaginal access, length and sexual goals before choosing the repair. See the Latzko technique.
Transvaginal Interposition and Vaginal Replacement
Martius labial fat-pad flap
The modified Martius flap uses vascularized labial fibrofatty tissue. It is distinct from a bulbocavernosus muscle flap. An anterior or posterior pedicle can be retained according to the required reach; protect the vascular plexus and avoid a tight tunnel.[4][13][14]
The flap is fibrofatty tissue from the labium majus with a prominent fibrous component and abundant blood supply; the Leach and Gebhart technique divides it at its anterior or posterior pedicle, passes it through a subepithelial tunnel and sews it to the underlying fascia without tension.[4] Indications reported by Kapriniotis and colleagues are listed above; in Eilber's series it was used for distal fistulas.[2][11]
Donor symptoms deserve explicit counseling. Lee et al. identified 122 eligible reconstructions but assessed 97 after exclusions. No perioperative complications were recorded. At mean 85 months, 79 (81%) had normal sensation, five (5%) reported pain, 13 (14%) numbness and nine reported distortion of the labia majora.[15] Only 26 completed the sexual-function questionnaire.[15] See Martius for VVF for selection and harvest.
Peritoneal and local fat-pad options
In Eilber's transvaginal series, interposition was reserved for complex (over 2 cm or radiation-induced) fistulas and failed prior repairs. A peritoneal flap was used for proximal fistulas, a Martius flap for distal fistulas and a full-thickness labial flap when vaginal epithelium was insufficient. The peritoneal flap is created transvaginally from the cul-de-sac or vesicouterine fold, adds no incision and no donor site, and has less bulk than Martius tissue. The authors described minimal morbidity, but the series did not compare morbidity directly with Martius. Choice depends on prior surgery, peritoneal availability and safe mobilization.[11] A genito-gluteal fold fat-pad flap closed two radiation-associated VVFs near the bladder neck at one year in Heo's report. The authors describe easier dissection, lower donor-site morbidity and a larger flap than Martius tissue, particularly for vaginal-cuff fistulas. This is a specialist alternative supported by a very small experience.[16]
Replacing vaginal lining as well as adding tissue
A fasciocutaneous flap or skin-containing reconstruction may be needed when vaginal lining is missing or severely stenotic. Labia majora fasciocutaneous flaps incorporate the labial fat pad with overlying skin, which supplies epithelial cover as well as bulk. Gupta's indications were a non-capacious rigid vagina, irradiated and inflamed tissue, a urethrovaginal fistula with anterior vaginal-wall loss and stenosis, and a vesicolabial fistula. In Gupta's seven complex urogenital cases, one radiation-associated VVF required subsequent colpocleisis to achieve dryness. Margolis combined the Martius fat pad with a full-thickness medial-thigh skin patch for large obstetric fistulas with extensive vaginal-wall destruction, in four full-thickness Martius reconstructions: all skin grafts took initially, but one VVF recurred. Early graft take, fistula closure and return to intercourse are separate outcomes.[40][41]
The Singapore pudendal-thigh flap is a fasciocutaneous flap based on the posterior labial artery, raised along the labiocrural fold, that supplies skin for vaginal reconstruction and can be combined with gracilis in complex obstetric fistulas. Pope's technical report describes its use in obstetric vaginal stenosis.[27] Browning's series included 45 women undergoing fistula repair (46% dry against an expected 19%) and 24 with leakage after an already closed fistula (71% dry against an expected 26%); the comparison was with historical expectations, not a concurrent control group.[28] A separate 69-patient series used Singapore (32), gracilis (20) or both (17) according to the defect; its authors noted a possible advantage of adding gracilis even when Singapore alone seemed sufficient.[23]
Abdominal Interposition
Omentum can supply mobile vascularized tissue between repaired organs when its pedicle and reach are suitable. It is based on the right or left gastroepiploic artery and reaches the deep pelvis. It is mobilized off the transverse colon, brought into the pelvis and sutured between the bladder and vaginal closures; in laparoscopic or robotic repair it can be mobilized before the robot is docked. Ileus and abdominal pain are the recognized drawbacks, it is unavailable after omentectomy and it adds dissection time. Published laparoscopic and robotic technical cases show feasibility.[5][18][51]
Peritoneal flaps, including the “rainbow-shaped” technique, offer another local option. Yang's 15-patient robotic series (seven with a failed prior repair) reported closure in all patients at mean follow-up of 7.8 months, with mean operative time 137 minutes and blood loss 14 mL; it did not compare this flap with omentum or flap-free repair.[19] Sigmoid epiploic tissue has also been described in the abdominal reconstructive literature. Available length, tissue viability and the neighboring bowel determine feasibility; none of these options should be assumed to match omentum in a deficient or irradiated bed.[5][12]
Muscle and Myocutaneous Flaps for Complex Defects
Gracilis and rectus-based flaps can provide vascularized bulk when local tissue is insufficient. The gracilis has a proximal dominant pedicle arising variably from the deep femoral artery, its adductor branch or the medial circumflex femoral artery, with mean entry about 10 cm from the ischiopubic attachment; the actual pedicle is identified during harvest before the muscle is tunneled subcutaneously to the perineum or vagina.[54][55] The VRAM flap is based on the deep inferior epigastric artery and is tunneled into the pelvis with a vertical skin paddle when vaginal reconstruction is needed. Plan harvest and pelvic inset jointly with the reconstructive team, accounting for previous abdominal operations, stomas, radiation, functional loss and the need for a skin paddle. See the foundations gracilis and VRAM anatomy pages.
Paprottka reported 13 flaps in 12 patients with heterogeneous urogenital fistulas: eight gracilis and five VRAM. All had at least two failed prior repairs and ongoing incontinence. Paprottka et al. reported that final surgical treatment by VRAM or gracilis flap could be achieved in all cases, with mean operative time 5 h 31 min for VRAM and 3 h 11 min for gracilis.[20] At long follow-up, the ten survivors included three VRAM recipients with some urinary leakage and seven gracilis recipients described as continent.[20] Ryan's six-patient report combined urinary fistulas and nonhealing wounds; Chong's 16 patients underwent reconstruction after oncologic pelvic or perineal resection.[21][22]
The VRAM-versus-gracilis proportional meta-analysis concerned vulvoperineal reconstruction after cancer surgery. Pooled donor-site complications were 57.6% for VRAM and 16.0% for gracilis, with similar flap necrosis and similar minor and major complication rates.[24]
Two unusual salvage reports require particular care:
- Horch described one woman receiving two consecutive rectus-based reconstructions for radiation-associated vesicovaginal and pouch-vaginal fistulas.[25]
- Sværdborg described a rectus muscle flap without a skin paddle in three radiation-associated VVFs, with reported closure at five to eight years.[26] Their modification omitted direct closure of the fistula defects.[26]
Rectovaginal Advancement Flaps
Rectal and vaginal advancement flaps mobilize adjacent tissue over a repaired communication. The rectal side is the higher-pressure side, not the vagina. In a vaginal advancement flap, a U-shaped or trapezoidal flap of vaginal wall is raised with its base distal, the tract is excised or curetted, the rectal side is closed with absorbable sutures, and the flap is advanced without tension over the closure; a Martius or gracilis flap can be interposed for reinforcement. In an endorectal advancement flap, a flap of rectal mucosa, submucosa and internal sphincter is raised, the tract is curetted, the vaginal side is left open and the flap is advanced over the internal opening.[43][44] Selection depends on location, rectal inflammation, sphincter integrity, vaginal tissue and previous repairs. The 2022 ASCRS guideline recommends endorectal advancement with or without sphincteroplasty for most RVFs and a gracilis muscle or bulbocavernosus (Martius) flap for recurrent or otherwise complex RVFs.[44] Both are strong recommendations based on low-quality evidence (1C); these are distinct operations.[44]
Control Crohn's activity and sepsis before elective reconstruction. In Nosti's six Crohn's patients, four vaginal advancement repairs with an additional flap did not recur during short, variable follow-up. Ruffolo's review of Crohn's disease RVF included 219 flap procedures from 11 observational studies, with pooled primary closure of 54.2% (range 33.3% to 100%) for rectal and 69.4% (range 0% to 92.9%) for vaginal advancement (p = 0.13).[42][43] In Li's retrospective cohort of 57 patients with simple RVF, closure was 66.7% among patients undergoing a first endorectal advancement repair and 70.2% overall after repeat repair.[45] A fistula diameter over 1 cm was associated with lower success for the first and overall repair (p < 0.05), and two such failures healed after a later sphincter repair; the authors suggest sphincteroplasty may be the better choice for these fistulas.[45]
Grafts, Sealants and Investigational Adjuncts
These materials do not bring a vascular pedicle. Evidence is largely small uncontrolled series, co-interventions, technical cases or laboratory work.
| Material | Evidence and practical boundary |
|---|---|
| Fibrin-coated collagen patch (TachoSil) | A biologic hemostatic/sealing patch, not a synthetic vascularized flap. In Giusti's laparoscopic extravesical repairs, two 4 × 4 cm layers were placed between the vesical and vaginal suture lines after two-layer closure. All 16 patients were continent at one month and reported good quality of life at three months; Erdogru reported no recurrence at six months after repairing one previously recurrent case.[29][30] |
| Small intestinal submucosa | In a 23-patient pilot, 21 were dry at six months: 7/7 vaginal and 14/16 abdominal repairs.[31] |
| Platelet-rich plasma / fibrin | Shirvan's protocol de-epithelialized around the fistula until slight bleeding occurred, injected PRP into the surrounding tissue and interposed platelet-rich fibrin glue in the tract; 11 of 12 patients considered themselves cured at six months, and one improved but declined a second injection. Streit-Ciećkiewicz's 16-patient report combined PRP with later Latzko repair; the subsequent eight-patient histology study measured tissue changes. Neither isolates a clinical PRP effect.[32][46][47] |
| Buccal mucosa | Taha reported ten vaginal repairs dry at six months.[48] Rafetto's radiation-associated case combined buccal mucosa with omentum, with early cystographic/endoscopic assessment.[49] |
| Amniotic scaffolds / regenerative glue | The cited amnion study used rabbits.[35] The reinforcement study used mechanical testing with a 2-N design threshold.[36] The regenerative bioglue report used pigs.[50] |
A radiation-associated PRP case required multiple repairs and eventual Martius interposition.[34] Mourad's 2026 multinational report covered 1,185 female genital fistula repairs, with overall closure of 82%.[33] Adjuncts (PRP, SIS, fibrin glue and buccal grafts) were used in 71% of complex or recurrent repairs, with 72% closure in that subgroup.[33]
Selection Summary
The table summarizes what the cited series report.
| Scenario | Tissue commonly described | Basis and limits |
|---|---|---|
| Simple, non-irradiated primary VVF | Often none | The review reports 86% to 100% closure for simple, non-irradiated iatrogenic urogenital fistulas repaired with or without interposition. The randomized simple-VVF trial excluded complex fistulas.[2][51] |
| Recurrent or radiation-associated fistula, transvaginal | Martius (distal) or peritoneal (proximal) | Observational: Rangnekar reported 11/12 with versus 3/7 without Martius for recurrent urinary–vaginal fistulas. Eilber reported initial-repair cure rates of 96% peritoneal and 97% Martius in selected complex or previously failed VVF repairs; these were not radiation-specific subgroup rates.[10][11] |
| Transabdominal repair | Omentum or peritoneum, or none | Evans 10/10 with versus 12/19 without in benign VVF; Miklos 42/43 without omentum.[7][9] |
| Large defect or extensive tissue loss | Gracilis, with or without Singapore flap | Small selected series; lower donor-site complications than VRAM in oncologic vulvoperineal data.[20][24] |
| Repeated failure, extensive radiation, combined fistulas | VRAM | Small series; more donor-site complications than gracilis in the same data.[20][24][25] |
| Obstetric fistula with vaginal stenosis | Singapore flap, with or without gracilis | Case series with historical comparison.[23][27][28] |
| Scarred or short vagina with no dependable second layer | Buccal mucosa, with or without a vascularized flap | Ten-patient series and a case report.[48][49] |
Four principles recur across the native-vaginal-wall techniques. The fistula repair is separated from the vaginal suture line (Wang). Latzko has been reported to shorten the vagina. For obstetric urinary pelvic floor fistula repair, the IUGA/ICS consensus considers flap splitting less likely to reduce vaginal capacity, although no direct comparative studies have been published.[56] Native vaginal-wall flaps are enough for many simple fistulas. Tissue from outside the field is imported for recurrent, irradiated or tissue-deficient repairs.[17][37][6]
Planning and Counseling
Start with the repair that provides safe exposure and viable closure, then decide whether interposition or replacement tissue addresses a specific deficiency. Preserve ureteral safety, vaginal access and desired sexual function. For RVF, evaluate continence and the sphincter before selecting advancement alone. In radiation injury or repeated failure, discuss whether reconstruction, a more extensive flap or diversion best serves the patient's goals.[2][3][12][44]
Report anatomic closure, urinary or fecal continence, donor-site symptoms, sexual function, reoperation and diversion reversal separately, with their actual follow-up.
See Also
- Martius Flap for VVF. This is the dedicated VVF Martius page.
- O'Conor (Transvesical) VVF Repair
- Extravesical VVF Repair
- Transvaginal Latzko Repair
- Transvaginal Sims-Simon Multilayered Closure
- Vesicovaginal Fistula (clinical)
- Female Fistula Repair (atlas)
- Fistula Repair Principles
- Foundations: Martius · Omental · Gracilis · VRAM
Videos
References
1. Okada Y, Matsushita T, Hasegawa T, et al. Surgical interventions for treating vesicovaginal fistula in women (protocol). Cochrane Database Syst Rev. 2026;1:CD015413. doi:10.1002/14651858.CD015413
2. Kapriniotis K, Loufopoulos I, Gresty HCM, Greenwell TJ, Ockrim JL. The utility of Martius fat pad in the repair of urogenital fistulae: review of current evidence. BJU Int. 2024;134(3):365–374. doi:10.1111/bju.16350
3. Rafetto AN, Wei N, Linder BJ. Principles and techniques of vesicovaginal fistula repair. Int Urogynecol J. 2026. doi:10.1007/s00192-026-06576-w
4. Leach DA, Gebhart JB. Martius labial fat pad graft (use in rectovaginal fistula repair). Int Urogynecol J. 2020;31(11):2427–2429. doi:10.1007/s00192-020-04315-3
5. Woo HH, Rosario DJ, Chapple CR. The treatment of vesicovaginal fistulae. Eur Urol. 1996;29(1):1–9. doi:10.1159/000473709
6. Mörgeli C, Tunn R. Vaginal repair of nonradiogenic urogenital fistulas. Int Urogynecol J. 2021;32(9):2449–2454. doi:10.1007/s00192-020-04496-x
7. Miklos JR, Moore RD. Laparoscopic extravesical vesicovaginal fistula repair: our technique and 15-year experience. Int Urogynecol J. 2015;26(3):441–446. doi:10.1007/s00192-014-2458-y
8. Miklos JR, Moore RD, Chinthakanan O. Laparoscopic and robotic-assisted vesicovaginal fistula repair: a systematic review of the literature. J Minim Invasive Gynecol. 2015;22(5):727–736. doi:10.1016/j.jmig.2015.03.001
9. Evans DH, Madjar S, Politano VA, et al. Interposition flaps in transabdominal vesicovaginal fistula repairs: are they really necessary? Urology. 2001;57(4):670–674. doi:10.1016/s0090-4295(01)00933-5
10. Rangnekar NP, Imdad Ali N, Kaul SA, Pathak HR. Role of the Martius procedure in the management of urinary-vaginal fistulas. J Am Coll Surg. 2000;191(3):259–263. doi:10.1016/s1072-7515(00)00351-3
11. Eilber KS, Kavaler E, Rodríguez LV, Rosenblum N, Raz S. Ten-year experience with transvaginal vesicovaginal fistula repair using tissue interposition. J Urol. 2003;169(3):1033–1036. doi:10.1097/01.ju.0000049723.57485.e7
12. Randazzo M, Lengauer L, Rochat CH, et al. Best practices in robotic-assisted repair of vesicovaginal fistula: a consensus report from the European Association of Urology Robotic Urology Section Scientific Working Group for Reconstructive Urology. Eur Urol. 2020;78(3):432–442. doi:10.1016/j.eururo.2020.06.029
13. Elkins TE, DeLancey JO, McGuire EJ. The use of modified Martius graft as an adjunctive technique in vesicovaginal and rectovaginal fistula repair. Obstet Gynecol. 1990;75(4):727–733. PMID 2314794
14. Marina T, Lago V, Padilla P, Matute L, Domingo S. Vesicovaginal fistula repair by modified Martius flap: a step-by-step surgical technique video. Ann Surg Oncol. 2021;28(2):1002–1006. doi:10.1245/s10434-020-09020-5
15. Lee D, Dillon BE, Zimmern PE. Long-term morbidity of Martius labial fat pad graft in vaginal reconstruction surgery. Urology. 2013;82(6):1261–1266. doi:10.1016/j.urology.2013.08.032
16. Heo C, Eun S, Baek R, Minn K. Vesicovaginal fistula repair with genito-gluteal fold fat pad flap. J Plast Reconstr Aesthet Surg. 2008;61(3):323–325. doi:10.1016/j.bjps.2007.09.005
17. Wang X, Gao Z, Li L, et al. Clinical efficacy of flap transfer coverage in the treatment of vesicovaginal fistula. Int Urogynecol J. 2023;34(8):1797–1802. doi:10.1007/s00192-023-05465-w
18. Watts KL, Ho R, Ghavamian R, Abraham N. Robot-assisted extravesical vesicovaginal fistula repair utilizing laparoscopically mobilized omental flap interposition. Int Urogynecol J. 2017;28(4):641–644. doi:10.1007/s00192-016-3218-y
19. Yang Y, Chenchen H, Shiliang W, Yuke C, Cheng S. Robot-assisted vesicovaginal fistula repair with "rainbow-shaped" peritoneal flap: a single-center experience. Arch Gynecol Obstet. 2025;311(6):1697–1703. doi:10.1007/s00404-024-07919-y
20. Paprottka FJ, Krezdorn N, Lohmeyer JA, et al. Plastic reconstructive surgery techniques using VRAM or gracilis flaps in order to successfully treat complex urogenital fistulas. J Plast Reconstr Aesthet Surg. 2016;69(1):128–137. doi:10.1016/j.bjps.2015.08.026
21. Chong TW, Balch GC, Kehoe SM, Margulis V, Saint-Cyr M. Reconstruction of large perineal and pelvic wounds using gracilis muscle flaps. Ann Surg Oncol. 2015;22(11):3738–3744. doi:10.1245/s10434-015-4435-1
22. Ryan JA, Gibbons RP, Correa RJ. Urologic use of gracilis muscle flap for nonhealing perineal wounds and fistulas. Urology. 1985;26(5):456–459. doi:10.1016/0090-4295(85)90153-0
23. Pope R, Hollier PC, Brown RH, et al. A retrospective review to identify criteria for incorporating the Singapore flap and gracilis muscle flap into obstetric fistula repair. Int J Gynaecol Obstet. 2020;148(Suppl 1):37–41. doi:10.1002/ijgo.13038
24. Eseme EA, Scampa M, Viscardi JA, et al. Surgical outcomes of VRAM vs gracilis flaps in vulvo-perineal reconstruction following oncologic resection: a proportional meta-analysis. Cancers (Basel). 2022;14(17):4300. doi:10.3390/cancers14174300
25. Horch RE, Gitsch G, Schultze-Seemann W. Bilateral pedicled myocutaneous vertical rectus abdominus muscle flaps to close vesicovaginal and pouch-vaginal fistulas with simultaneous vaginal and perineal reconstruction in irradiated pelvic wounds. Urology. 2002;60(3):502–507. doi:10.1016/s0090-4295(02)01823-x
26. Sværdborg M, Birke-Sørensen H, Bek KM, Nielsen JB. A modified surgical technique for treatment of radiation-induced vesicovaginal fistulas. Urology. 2012;79(4):950–953. doi:10.1016/j.urology.2011.10.077
27. Pope RJ, Brown RH, Chipungu E, Hollier LH, Wilkinson JP. The use of Singapore flaps for vaginal reconstruction in women with vaginal stenosis with obstetric fistula: a surgical technique. BJOG. 2018;125(6):751–756. doi:10.1111/1471-0528.14952
28. Browning A, Williams G, Petros P. Skin-flap vaginal augmentation helps prevent and cure post-obstetric-fistula-repair urine leakage: a critical anatomical analysis. BJOG. 2018;125(6):745–749. doi:10.1111/1471-0528.14953
29. Giusti G, Lucci Chiarissi M, Abate D, et al. Early repair of post-hysterectomy vesicovaginal fistulae through a laparoscopic transperitoneal extravesical approach: experience of a single center. Urology. 2018;119:44–48. doi:10.1016/j.urology.2018.05.021
30. Erdogru T, Sanli A, Celik O, Baykara M. Laparoscopic transvesical repair of recurrent vesicovaginal fistula using a fleece-bound sealing system. Arch Gynecol Obstet. 2008;277(5):461–464. doi:10.1007/s00404-007-0499-x
31. Farahat YA, Elbendary MA, Elgamal OM, et al. Application of small intestinal submucosa graft for repair of complicated vesicovaginal fistula: a pilot study. J Urol. 2012;188(3):861–864. doi:10.1016/j.juro.2012.05.019
32. Shirvan MK, Alamdari DH, Ghoreifi A. A novel method for iatrogenic vesicovaginal fistula treatment: autologous platelet-rich plasma injection and platelet-rich fibrin glue interposition. J Urol. 2013;189(6):2125–2129. doi:10.1016/j.juro.2012.12.064
33. Mourad MS, Malallah M, Mahfouz W, et al. Sixteen years of multinational experience in female genital fistula repair: integrating traditional and innovative surgical approaches across 12 countries. Neurourol Urodyn. 2026;45(3):583–590. doi:10.1002/nau.70226
34. Kołodyńska A, Streit-Ciećkiewicz D, Kot A, Kuliniec I, Futyma K. Radiation-induced recurrent vesicovaginal fistula — treatment with adjuvant platelet-rich plasma injection and Martius flap placement: case report and review of literature. Int J Environ Res Public Health. 2021;18(9):4867. doi:10.3390/ijerph18094867
35. Kurniawati EM, Santoso B, Rantam FA, et al. Does freeze-dried amnion useful as scaffold for mesenchymal stem cell for repair of vesicovaginal fistula? An overview of proliferative and remodeling phase in the wound healing process. Eur J Obstet Gynecol Reprod Biol. 2022;274:113–116. doi:10.1016/j.ejogrb.2022.05.017
36. Maljaars LP, Guler Z, Roovers JWR, Bezuidenhout D. Mechanical reinforcement of amniotic membranes for vesicovaginal fistula repair. J Mech Behav Biomed Mater. 2023;139:105680. doi:10.1016/j.jmbbm.2023.105680
37. Shoukry MS, Hassouna ME, El-Salmy S, Abdel-Karim AM. Vaginal flap re-enforcement of vesicovaginal fistula repair. Int Urogynecol J. 2010;21(7):829–833. doi:10.1007/s00192-010-1124-2
38. Tang M, Li P, Wang C, Zhang Q, Meng X. Clinical application of single-layer annular vaginal flap in transvaginal repair for vesicovaginal fistula. World J Urol. 2023;41(1):249–255. doi:10.1007/s00345-022-04222-w
39. Sayegh AS, La Riva A, Perez LC, et al. Robotic-assisted vesicovaginal fistula repair using a vaginal cuff flap. Int Urogynecol J. 2022;33(9):2581–2585. doi:10.1007/s00192-022-05144-2
40. Gupta P, Kalra S, Dorairajan LN, et al. Labia majora fasciocutaneous flap reconstruction in complex urogynecological fistulas with vaginal deficit — a versatile approach. Urology. 2022;167:241–246. doi:10.1016/j.urology.2022.05.017
41. Margolis T, Elkins TE, Seffah J, Oparo-Addo HS, Fort D. Full-thickness Martius grafts to preserve vaginal depth as an adjunct in the repair of large obstetric fistulas. Obstet Gynecol. 1994;84(1):148–152. PMID 8008312
42. Nosti PA, Stahl TJ, Sokol AI. Surgical repair of rectovaginal fistulas in patients with Crohn's disease. Eur J Obstet Gynecol Reprod Biol. 2013;171(1):166–170. doi:10.1016/j.ejogrb.2013.08.011
43. Ruffolo C, Scarpa M, Bassi N, Angriman I. A systematic review on advancement flaps for rectovaginal fistula in Crohn's disease: transrectal vs transvaginal approach. Colorectal Dis. 2010;12(12):1183–1191. doi:10.1111/j.1463-1318.2009.02029.x
44. Gaertner WB, Burgess PL, Davids JS, et al. The American Society of Colon and Rectal Surgeons clinical practice guidelines for the management of anorectal abscess, fistula-in-ano, and rectovaginal fistula. Dis Colon Rectum. 2022;65(8):964–985. doi:10.1097/DCR.0000000000002473
45. Li X, Shao W, Sun G. A single-center retrospective analysis of endorectal advancement flaps used for the treatment of simple rectovaginal fistulas. Scand J Gastroenterol. 2025;60(4):307–311. doi:10.1080/00365521.2025.2468493
46. Streit-Ciećkiewicz D, Futyma K, Miotła P, et al. Platelet-rich plasma as adjuvant therapy for recurrent vesicovaginal fistula: a preliminary report. J Clin Med. 2019;8(12):2122. doi:10.3390/jcm8122122
47. Streit-Ciećkiewicz DE, Knapik A, Rechberger T, et al. Influence of platelet-rich plasma on recurrent vesicovaginal fistula: histological and immunohistochemical study. J Clin Med. 2024;13(2):370. doi:10.3390/jcm13020370
48. Taha KM, Mohammed GF, Hafez R, et al. Buccal mucosal graft as a second layer in the vaginal repair of vesicovaginal fistulas. Neurourol Urodyn. 2025;44(2):287–293. doi:10.1002/nau.25657
49. Rafetto AN, Lehner KP, Reynolds EA, Langstraat CL, Warner JN. Robotic vesicovaginal fistula repair with buccal graft interposition. Int Urogynecol J. 2026. doi:10.1007/s00192-026-06717-1
50. Kim HJ, Turner D, Shi R, et al. Preclinical evaluation of a regenerative immiscible bioglue for vesico-vaginal fistula. Acta Biomater. 2021;125:183–196. doi:10.1016/j.actbio.2021.02.037
51. Singh V, Mehrotra S, Bansal A, Akhtar A, Sinha RJ. Prospective randomized comparison of repairing vesicovaginal fistula with or without the interposition flap: Result from a tertiary care Institute in Northern India. Turk J Urol. 2019;45(5):377–383. doi:10.5152/tud.2019.85233
52. Thompson JC, Halder GE, Jeppson PC, et al. "Repair of vesicovaginal fistulae: a systematic review." Obstet Gynecol. 2024;143(2):229–241. doi:10.1097/AOG.0000000000005468
53. European Association of Urology. "EAU Guidelines on Non-neurogenic Female LUTS: Disease management." 2026. Official guideline.
54. Magden O, Tayfur V, Edizer M, Atabey A. "Anatomy of gracilis muscle flap." J Craniofac Surg. 2010;21(6):1948–1950. doi:10.1097/SCS.0b013e3181f4ed81
55. Macchi V, Vigato E, Porzionato A, et al. "The gracilis muscle and its use in clinical reconstruction: an anatomical, embryological, and radiological study." Clin Anat. 2008;21(7):696–704. doi:10.1002/ca.20685
56. Maljaars LP, Corcos J, Ghoniem G, et al. "Consensus statements on the definition of surgical success following obstetric urinary pelvic floor fistula repair: an IUGA-ICS proposal." Int Urogynecol J. 2026;37(5):1193–1205. doi:10.1007/s00192-025-06413-6