Non-Infectious Complications of Penile Prosthesis Surgery
Infection, the most consequential complication, is covered in its own article. Revision-specific scenarios (SST, crossover, perforation) are covered in revision scenarios.
The Cocci systematic review of 151 studies (92,777 patients) summarizes contemporary complication evidence.[2]
Rate Summary
The ranges below come from heterogeneous literature.
| Complication | Rate | Timing |
|---|---|---|
| Acute postoperative pain (severe) | 46.2% on postoperative day 2 and 11.1% on day 30 in one prospective 96-man penoscrotal IPP cohort[36] | Early |
| Infection | 0.03–14.3% across studies, mostly under 5%[2] | Weeks to months |
| Mechanical failure | Above 15% in about half of studies with 5–11 years of follow-up[2] | Late |
| Prosthesis erosion | 0.02–32.5% across studies, most below 5%[2] | Weeks to years |
| Pump erosion | Uncommon | Years |
| Reservoir erosion (bladder) | Rare | Variable |
| Cylinder aneurysm or bulge | 0.7% (2/300) in the AMS 700 pivotal trial[13] | 110–1,780 days (mean 945 days) |
| Penile shortening (subjective) | Highly variable | Immediate |
| Glans ischemia/necrosis | Rare | 1–14 days |
| Chronic pain | Poorly characterized | Weeks to years |
| Sensory change | 2.3% (7/300) decreased penile sensation in the AMS 700 pivotal trial; approach-specific rates remain uncertain[13] | Variable |
Manufacturer label data (AMS 700). The pivotal trial enrolled 300 men with devices that did not carry InhibiZone and reported, across the study, urogenital pain 53.3%, edema 35.3%, ecchymosis 10.0%, reservoir encapsulation 6.3%, auto-inflation 5.7%, mechanical malfunction 4.3%, impaired urination 3.7%, decreased penile sensation 2.3%, infection 2.0%, penile curvature 1.7%, erosion or extrusion 1.3%, device migration 1.0% and cylinder aneurysm 0.7%.[13] Among 126 men followed to 5 years and 16 additional men revised before that exam, 22 of 142 (15.5%) underwent 26 revisions; mean time to first revision was 15 months, and mechanical malfunction was the commonest reason (7 of 26).[13] The MS pump and TENACIO pump were not available when the trial ran. Separate manufacturer revision tables (parts-replacement forms, 2019 label edition) gave 5-year revision rates of 11.6% for the CX (n = 12,080) and 9.8% for the Ultrex, including mechanical revision 5.6% and 4.8%, removal for infection 2.2% and 2.0% and removal for erosion 1.4% and 1.0%; these rely on voluntary reporting and probably undercount.[13][14]
Erosion and Extrusion
Cylinder erosion through the glans or urethra
Distal glans erosion (cylinder tip protrudes through the glans) presents as visible device, glans pain, bleeding, or bloody discharge. Urethral erosion presents as hematuria, dysuria, recurrent UTI, palpable cylinder in the urethra on exam, or cylinder visible on cystoscopy.[3] In a single-surgeon retrospective cohort of 797 IPP placements, 26 impending or complete cylinder extrusion events (about 3%; two occurred in the same patient) were identified: 46.2% lateral shaft, 34.6% distal urethral, 7.7% glanular, 7.7% midshaft and 3.8% coronal-sulcus.[16] Mean time from initial placement to repair was 8.4 years (median 5.5); 17 of 26 (65.4%) underwent repair or replacement and 9 (34.6%) had device removal.[16]
Risk factors:
- Diabetes. Impaired tissue integrity.
- Pelvic radiation. Reduces tissue quality and is a recognized risk factor.
- Spinal cord injury with impaired sensation, so the patient does not feel the developing erosion.
- Aggressive distal dilation with cylinder oversizing.
- Long-indwelling catheter against the cylinder.
- Prior glanular or urethral surgery reducing local vascular supply.
- Poorly fitted rear-tip extenders creating distal cylinder pressure.
Management:
- Confirmed distal erosion through the glans: cylinder explantation on the affected side; contralateral cylinder may be retained or explanted depending on the scenario. The glans is allowed to heal 3–6 months before considering reimplantation.
- Urethral erosion: complete device explantation, primary urethral repair if feasible (versus marsupialization or urethrostomy), Foley drainage, delayed reimplantation 3–6 months after complete healing.
- Counseling: reimplantation carries a higher risk of re-erosion, particularly after radiation or in severe diabetes.
Impending distal extrusion
Several repair options have been described for a threatened distal cylinder tip before it fully erodes through the glans or urethra:
- Capsule-based redirection. Mulcahy's distal corporoplasty opens the existing fibrotic capsule and creates a new, more medial and secure cavity for the cylinder behind the back wall of the capsule; in the original 14-patient series, all had a satisfactory result with no recurrence at up to 2 years.[17] Carson and Noh compared this approach (18 men) with Gore-Tex windsock reinforcement (10 men) in 28 patients with impending extrusion: no infection or recurrent extrusion occurred after corporoplasty, versus one infection and two extrusion recurrences (at 6 and 18 months) after windsock repair, with a shorter mean operative time for corporoplasty (52.8 versus 89.6 minutes).[18] The comparison was not randomized and had no stated overall follow-up.[18]
- Distal anchoring stitch. Antonini and colleagues extract the distal cylinder through a lateral subcoronal corporotomy, create a new true distal corporal channel, and anchor the cylinder in it with a 4-0 PDS suture passed through the glans and buried. In a 53-patient series (14 distal crossovers, 39 lateral extrusions), 2 patients (3.8%) had recurrent lateral herniation at median 46.8-month follow-up, with no infection, wound-healing defect or device replacement for extrusion, infection or mechanical failure reported.[19]
- Distal biologic cap. Karpman and colleagues describe checking for urethral microperforation by cystoscopy, then folding a graft of at least 4 x 2 cm over the distal cylinder tip to provide about 1.5 cm of coverage, oversewing the lateral edges. In a small case series undergoing IPP replacement, none had recurrent impending erosion or loss of function at short-term follow-up.[20]
- Proximal extracapsular tunneling. For impending erosion related to corporal dilation, Clavell-Hernández describes opening the surgical capsule, exposing sinusoidal tissue behind its posterior wall, and developing a new extracapsular plane before cylinder replacement; in a 6-patient series (mixed indications including impending erosion, glans hypermobility and cylinder aneurysm), none had recurrent malposition, malfunction or infection at mean 6.6-month follow-up.[21]
These are small, uncontrolled or single-comparison reports; none establishes one technique as superior, and none changes management of confirmed erosion, urethral involvement or infection.
Delayed reconstruction after complete distal erosion
For a deficient distal tunica after complete erosion, Egydio and Kuehhas describe a "double-windsocks" reconstruction: the neurovascular bundle is elevated through a circumcision incision, lateral 3- and 9-o'clock tunical incisions are made, and paired neocorporal channels are fashioned over dilators from polypropylene mesh (malleable implants) or a polypropylene/PTFE composite (IPP), separated by a nonabsorbable septum to prevent crossover, with Buck's fascia and the neurovascular bundle covering the mesh. In their 69-patient series (45 prior distal erosions, 24 other corporal fibrosis; 57 malleable and 12 inflatable devices), mean follow-up was 22.5 months (range 6–48), satisfaction was 88.4%, and no extrusion, infection or skin dehiscence was reported; delayed orgasm occurred in 17 patients (24.6%) and recovered within about 4 months.[22]
Pump erosion
Less common than cylinder erosion; presents as tender, erythematous scrotal skin tenting or frank erosion. Risk factors include thin scrotal tissue, radiation, and pump migration up against a poorly-dependent scrotal pocket.
Management: assess for implant infection and plan operative treatment of exposed hardware. Complete device removal with delayed reimplantation is one option; in a six-patient retrospective pilot, all IPP components were removed and a malleable implant was substituted immediately in men without penile pain on palpation or overwhelming sepsis.[37]
Reservoir erosion into the bladder
Rare but severe. Presents as hematuria, cystitis-like symptoms, device deflation, or findings on cystoscopy. Managed with reservoir explantation, cystorrhaphy, Foley drainage, and delayed reimplantation; see reservoir placement.
Extrusion at the wound
Cylinder or tubing visible through a wound dehiscence. Usually managed by explantation and delayed reimplantation; simple debridement and closure over exposed device rarely succeeds.
Purulent drainage, or an early opening with bloody hematoma clots from a scrotal hematoma, calls for a return to the operating room for source control.[23] For carefully selected clean, nonpurulent wound separation without those features, office closure with oral antibiotics has been reported to preserve the implant: one high-volume implanter’s experience preserved the device in 13 of 14 selected patients. A separate observational series of 15 patients with localized clinical wound or implant infection used close observation and oral antibiotics without immediate surgery; 13 had total symptom resolution over 21 to 141 days (mean 76.2), two remained under observation, and nine bacterial isolates were recovered from seven cultured patients.[33]
Glans Ischemia and Necrosis
Clinical picture
Glans pallor, cyanosis or frank necrosis typically presents as a dusky glans on the first postoperative day.[4][8] Onset is occasionally delayed to 7–14 days. Ischemia may involve part of the glans (dorsal tip pallor) or the entire glans.
Mechanisms
- Distal cylinder oversizing. Mechanical compression of glans vasculature.
- Dorsal neurovascular bundle injury. Partial or complete transection during dissection.
- Glans crossover. Cylinder perforating the glans or crossing the midline through the septum.
- Aggressive distal dilation. Direct arterial injury.
- Preexisting glans hypovascularity. In Wilson's 21 cases, atherosclerotic cardiovascular disease (90%), diabetes (81%), smoking (81%), prior explantation (57%) and prior radiation (48%) were common.[4]
- Adjunctive maneuvers. The same series found a subcoronal incision (86%), an occlusive elastic penile wrap (62%), a sliding technique for lengthening (33%) and concurrent distal urethral repair (29%).[4] Park reported no glans ischemia or necrosis in 898 subcoronal implants by one surgeon.[4][7]
- Hematoma compressing the glans from within.
Management
- Immediate recognition. Deflate the device, remove a compressive penile dressing, and remove a urethral catheter if feasible; reassess glans color and sensation promptly.[8] Persistent ischemia warrants urgent consideration of explantation, with removal within 24 hours advised in the case literature: in Wilson's 21-case series, 17 men managed expectantly with the device in place lost glans tissue, whereas four who underwent immediate removal healed without sequelae.[4][8]
- Hyperbaric oxygen therapy. Reported as an adjunct to debridement in one post-implant penile gangrene case.[34]
- Warm compresses, topical nitroglycerin. Adjuncts with limited evidence.
- Urgent prosthesis removal. When glans ischemia develops, urgently consider removal of the entire implant; the cited 21-case series found major glans loss in 17 of 21 patients managed with device preservation versus no sequelae in four who underwent immediate removal.[4]
- Glans debridement or partial amputation only if necrosis is established and unsalvageable. Counsel the patient about the cosmetic consequences.
Prevention
- Careful distal corporal dilation to the subcoronal recess, not through it
- Preservation of the dorsal neurovascular bundle in infrapubic and subcoronal approaches
- Appropriate cylinder sizing with intraoperative measurement
- Avoiding occlusive elastic penile wraps and high-risk adjunctive maneuvers (sliding technique, concurrent distal urethral repair) in patients with the risk factors above[4]
- Postoperative glans assessment at the end of the case and again at 2 hours and 24 hours
Cylinder Aneurysm
Definition
Focal bulging or ballooning of the cylinder wall, visible and palpable during inflation. The cylinder shell has developed a weak point where fluid pressure expands the wall beyond its original contour.
Presentation
Patient notices an abnormal asymmetry or focal bulge during erection. May be painful. Most commonly reported several years after implantation in heavily cycled devices.
Management
Management is cylinder replacement (isolated cylinder exchange, or complete device replacement if other components show wear). Aneurysms do not resolve and progressively enlarge.
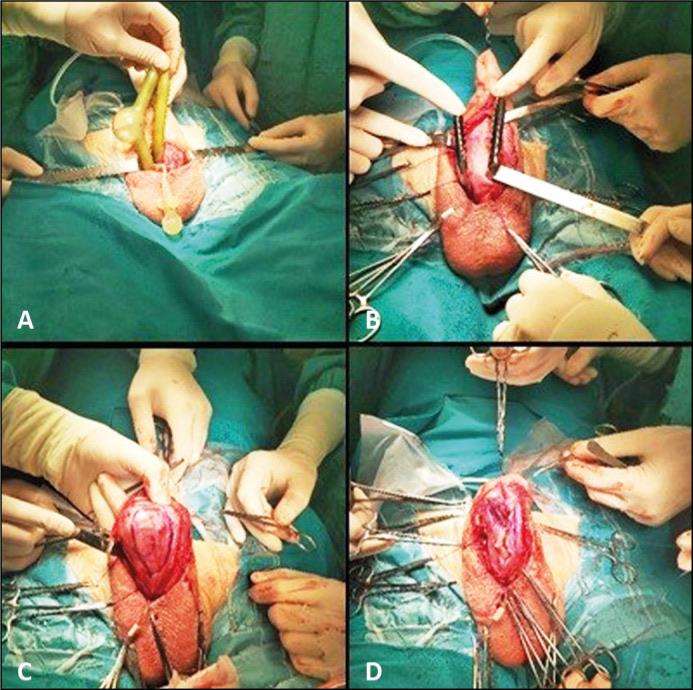
Revision for a Titan cylinder aneurysm. (A) Right cylinder aneurysm. (B) Septal defect showing communication between the right and left sides. (C) Redundant tunica marked with a pen for excision. (D) Tunical closure with 6-0 polydioxanone (PDS) sutures. From Tavares C, et al. Cent European J Urol. 2021;74(2):255-258, Figure 2 (CC BY-NC-SA).[12]
Prevention
Appropriate cylinder sizing and avoidance of overly aggressive inflation during patient use. Aneurysms have been reported as case reports with contemporary parylene-coated AMS 700 CX and Coloplast Titan cylinders.[11][12]
Reservoir Vascular Compression
A reservoir placed too laterally, or overfilled, can compress an adjacent external iliac vessel. Venous compression may present days to weeks after surgery with ipsilateral leg edema and progress to iliac-vein thrombosis; arterial compression has caused acute limb ischemia in a case report.[39] Case reports describe successful thrombectomy or vein repair combined with repositioning the reservoir more medially, to the contralateral side, or to an ectopic location.[24][25] New unilateral leg edema or ischemic symptoms after IPP warrant urgent vascular evaluation.
Mechanical Failure
Rates
- Mechanical failure rates exceed 15% in about half of studies with 5–11 years of follow-up, and neurological comorbidity is associated with a higher risk of mechanical failure.[2] A long-term multicenter study of 372 AMS 700CX recipients (implanted 1987–1996, up to 134 months of follow-up, median 47.7 months) reported device malfunction in 17.5% and mechanical reliability of 92.1% at 3 years and 86.2% at 5 years.[15]
- In a 2,384-patient series of first-time implants spanning older device generations, estimated all-cause revision-free survival was 68.5% at 10 years and 59.7% at 15 years.[31]
- Coloplast Titan and AMS 700 have comparable long-term mechanical reliability in most reported series
Failure modes
- Cylinder tubing disconnection or rupture. Fluid loss; device does not inflate
- Reservoir-to-pump tubing disconnection. Device does not inflate, or inflates partially
- Reservoir-to-pump tubing torsion ("telephone cord syndrome"). Patient cannot inflate the device; a 5-year multi-institutional experience of 974 implants (612 with alternative/ectopic reservoir placement, 362 with traditional space-of-Retzius placement) described 4 cases, mostly involving ectopic reservoirs, with caudal tubing migration and increased abdominal-wall pressure proposed as a contributing mechanism.[26]
- Pump valve failure. Fluid cycles asymmetrically; device does not deflate fully
- Cylinder shell rupture. Progressive aneurysm followed by rupture; loss of inflation
- Reservoir leak. Gradual deflation over weeks to months
- Autoinflation. In devices without a lock-out valve, increased abdominal pressure can move reservoir fluid into the cylinders.[40] The TENACIO pump's valving resists elevated reservoir pressure but does not eliminate postoperative autoinflation; the earlier AMS 700 pivotal trial, predating the MS and TENACIO pumps, recorded 17/300 events (5.7%).[13] Confirm deflation technique and assess reservoir position and filling before attributing autoinflation to valve failure.[13]
Management
- Complete mechanical workup: imaging (ultrasound of pump, x-ray of reservoir with contrast in selected cases), direct test of each component
- Isolated component replacement versus complete device exchange is a judgment call; many surgeons replace the entire device after 10+ years of service. In a systematic review of 11 studies of revision for noninfected malfunction, partial exchange (n = 234) had infection in 6.3% and overall complications in 23.9%, versus 2.7% and 11.3% after complete exchange (n = 12,202); these nonrandomized groups had differing follow-up.[38]
Urinary Retention
Incidence
Approximately 5–6% of patients require postoperative catheterization for retention, usually within 24–48 hours of surgery.[2]
Causes
- Narcotic analgesics
- Local edema near the bladder neck
- Prior BPH or mild BOO revealed in the perioperative period
- Reservoir compression (usually mild, rarely the primary cause)
Management
- Intermittent catheterization (one or two insertions usually sufficient)
- For patients with BPH symptoms: tamsulosin 0.4 mg orally once daily is the labeled BPH dose; a fixed 7–14-day post-implant course is not established.[35]
- Rarely requires prolonged catheter drainage
Hematoma
Scrotal hematoma
Most common early complication location. In a prospective single-center cohort using chlorhexidine-alcohol skin preparation and fibrin sealant without a drain, hematoma occurred in 1.0% (1/103) versus 5.2% (6/115) in historical controls using povidone-iodine preparation and routine drains.[5]
- Compressive scrotal dressing is standard.
- Partial device inflation for 24 hours to 2 weeks reduces dead space and is used by many implanters for hematoma reduction.
- Fibrin sealant. A historical-cohort comparison reported fewer hematomas with a bundled protocol using Evicel, chlorhexidine-alcohol preparation and no drain (1/103 versus 6/115).[5]
- Drains are omitted in many contemporary protocols. In a retrospective comparison of 410 primary three-piece implants, a 24-hour closed-suction drain was not associated with lower hematoma or infection rates, and hematoma was associated with infection (OR 29.0 on postoperative day 3).[9] A multi-institution series of 425 implants with 12–24 hour scrotal drainage reported a 3.3% infection rate and 0.7% hematoma rate.[10]
Pelvic hematoma
Associated with infrapubic approach or difficult reservoir placement; typically self-limited. CT imaging if concern for ongoing bleeding or expanding hematoma.
Management
- Small or stable: observation, compressive dressing, ice, appropriate analgesia
- Large, expanding or infected: operative evacuation, reassessment of bleeding source, device evaluation
Chronic Pain
Persistent pain after penile prosthesis implantation can range from pain only during activation to daily pain with the device inactive. Its incidence beyond 6 weeks is poorly characterized.[27]
Causes
- Inadequate distal cylinder seating: glans pain with inflation
- Pump or reservoir positioning causing neuralgia or dartos irritation
- Chronic corporal inflammation or sterile bursa formation around components
- Unrecognized Peyronie's disease with incomplete correction
- Psychological pain amplification
Management
- Expectant management for mild pain; most improves over 6–12 months
- Pump or cylinder repositioning for component-localized pain
- Pudendal nerve block as a diagnostic or therapeutic maneuver in selected cases
- Device exchange or explantation in refractory cases when pain does not resolve. In a retrospective two-center series, pain persisted in 18 of 31 patients (58%) after revision or explantation undertaken for chronic pain; improvement occurred only in those with device malposition.[32]
Sensory Changes
Rates and mechanism
- Infrapubic approach carries the highest sensory-change risk; the dorsal neurovascular bundle is in the direct dissection field
- Penoscrotal approach has the lowest rate; the dorsal bundle is not routinely exposed
- Subcoronal approach carries moderate risk; the bundle is exposed during degloving but visible throughout
Decreased penile sensation was reported in 7 of 300 men (2.3%) in the AMS 700 pivotal trial.[13]
Management
- Counseling preoperatively about the risk
- Expectant management; most improve over 3–12 months
- Refractory complete sensory loss has no effective surgical solution
Penile Shortening
Subjective shortening varies by cohort and may occur despite no significant change in measured stretched flaccid length, as in the prospective cohort described below.[28] In a 20-man prospective IPP cohort, 14 men (70%) had shorter measured penile length at 6 weeks when postoperative inflated length was compared with preoperative pharmacologically induced erect length; median individual loss was 0.5 cm.[41] Subjective complaint and objective measurement often differ, so preoperative measurement and counseling address the complaint directly. In one prospective cohort of 56 men measured before and 1 and 6 months after first-time implantation, 72% reported a subjective decrease in penile length, but there was no statistically significant difference in measured stretched flaccid length compared with preoperative measurements; men who complained of length loss had lower treatment-satisfaction scores despite similar erectile-function scores.[28]
Addressed by
- Length-expanding cylinder (AMS 700 LGX; Rigicon Infla10 Pulse AX). The AMS 700 IFU cautions that LGX cylinders in Peyronie's disease may not give a satisfactory result.
- Preoperative traction therapy (vacuum device, penile traction device): limited evidence but used by some practices
- Adequate corporal dilation to maximal stretched length at primary implant
- Early implantation after acute ischemic priapism. It may limit fibrosis-associated shortening; discuss its risks and benefits against delayed placement .[30]
The Counseling Framework for Complications
Effective consent discussion frames complications in three groups the patient can understand:
- Things that resolve on their own (most hematomas, most pain, most retention, most sensory change)
- Things that require another operation (mechanical failure, autoinflation, malposition, cylinder aneurysm, most infections)
- Things that end the implant journey for this patient (severe erosion with irreparable tissue loss, profound glans necrosis, unsalvageable infection with multiple failed salvage attempts)
Revision is common over the life of the device (see the revision rate under Mechanical Failure) and is part of the normal device lifecycle.
Documentation After Complications
Every non-routine postoperative event should generate a note that captures:
- Date of primary operation, device details (manufacturer, model, size, RTE)
- Date of presentation and clinical findings
- Imaging and labs obtained
- Decision and treatment provided
- Patient-expressed concerns in their own words
- Plan and follow-up interval
Contemporaneous documentation of informed consent, technique, timely recognition and management supports the medicolegal record.
Implantation After PFUI Urethroplasty
Chapter authors describing their own single-center experience report 41 men who received a penile implant after pelvic fracture urethral injury (PFUI) anastomotic urethroplasty between 2013 and 2023 (38 semirigid, 3 three-piece inflatable devices; mean interval after urethroplasty 47 months). They report two intraoperative septal perforations and one proximal crural perforation; postoperative events were two hematomas, two glans extrusions described only as salvaged without further detail, and one proximal urethral erosion leading to implant removal. Mean IIEF-5 rose from 3.27 before to 21.88 after implantation, without a stated follow-up interval.[29] The cohort was uncontrolled.[29]
See Also
- Penile implants: overview
- Infection: evolution and modern prevention
- Reservoir placement
- Revision scenarios
Videos
References
1. Van Renterghem K, De Bruyn H, Yebes A, et al. Early complications after penile prosthesis surgery: findings from the PHOENIX multicenter registry. Int J Impot Res. 2026;38(1):30-36. Originally published online May 7, 2025; corrected July 23, 2026. doi:10.1038/s41443-025-01080-z
2. Cocci A, Capogrosso P, Minhas S, et al. Penile prosthesis implantation: a systematic review of intraoperative and postoperative complications. Int J Impot Res. 2026;38(2):93–122. doi:10.1038/s41443-025-01108-4
3. Carlos EC, Sexton SJ, Lentz AC. Urethral injury and the penile prosthesis. Sex Med Rev. 2019;7(2):360–368. doi:10.1016/j.sxmr.2018.06.003
4. Wilson SK, Mora-Estaves C, Egydio P, et al. Glans necrosis following penile prosthesis implantation: prevention and treatment suggestions. Urology. 2017;107:144–148. doi:10.1016/j.urology.2017.06.020
5. Fathollahi A, Razdan S, Razdan S. Zero infection protocol in inflatable penile prosthesis surgery: a prospective cohort study using chlorhexidine-alcohol skin preparation and fibrin sealant hemostasis. Int J Impot Res. 2026;38(4):363–367. doi:10.1038/s41443-025-01174-8
6. Van Renterghem K, De Bruyn H, Yebes A, et al. Correction to: Early complications after penile prosthesis surgery: findings from the PHOENIX multicenter registry. Int J Impot Res. Published July 23, 2026. doi:10.1038/s41443-026-01235-6.
7. Park SH, Wilson SK, Wen L. Subcoronal incision for inflatable penile prosthesis does not risk glans necrosis. J Urol. 2023;210(4):678–687. doi:10.1097/JU.0000000000003619
8. Hebert KJ, Kohler TS. Glans ischemia following inflatable penile prosthesis surgery. Transl Androl Urol. 2020;9(2):824–827. doi:10.21037/tau.2020.01.04
9. Ortaç M, Cetin B, Onuk O, et al. Does a 24-h closed-suction drain reduce infection and hematoma after inflatable penile prosthesis surgery? A comparative study. J Sex Med. 2026;23(6):qdag152. doi:10.1093/jsxmed/qdag152
10. Sadeghi-Nejad H, Ilbeigi P, Wilson SK, et al. Multi-institutional outcome study on the efficacy of closed-suction drainage of the scrotum in three-piece inflatable penile prosthesis surgery. Int J Impot Res. 2005;17(6):535–538. doi:10.1038/sj.ijir.3901354
11. Kaufman JM, Weldon TE. Cylinder aneurysm of parylene-coated American Medical System (AMS) 700CX penile prosthesis. J Sex Med. 2008;5(11):2713–2715. doi:10.1111/j.1743-6109.2008.00975.x
12. Tavares C, Djinovic R, Spiridonescu B, et al. When Titans become weak: penile prosthesis cylinder aneurysm, a case report. Cent European J Urol. 2021;74(2):255–258. doi:10.5173/ceju.2021.0098
13. Boston Scientific. AMS 700 Inflatable Penile Prosthesis with TENACIO Pump: Instructions for Use. 51558342-01A (US English). Adverse events and clinical studies (300-man trial, January 1995 to October 2002).
14. Boston Scientific (American Medical Systems). AMS 700 with MS Pump Penile Prosthesis Product Line: Instructions for Use. 92162915-01B (global edition, English section). Revision-rate tables 3 and 4.
15. Carson CC, Mulcahy JJ, Govier FE. Efficacy, safety and patient satisfaction outcomes of the AMS 700CX inflatable penile prosthesis: results of a long-term multicenter study. AMS 700CX Study Group. J Urol. 2000;164(2):376-380. doi:10.1016/s0022-5347(05)67364-8. PMID 10893589
16. Fuentes JL, Yi YA, Davenport MT, et al. Long-term sequelae of inflatable penile prosthesis: clinical characteristics of patients who develop distal cylinder tip extrusion. Transl Androl Urol. 2020;9(1):38-42. doi:10.21037/tau.2019.08.30
17. Mulcahy JJ. Distal corporoplasty for lateral extrusion of penile prosthesis cylinders. J Urol. 1999;161(1):193-195. doi:10.1016/s0022-5347(01)62094-9. PMID 10037396
18. Carson CC, Noh CH. Distal penile prosthesis extrusion: treatment with distal corporoplasty or Gortex windsock reinforcement. Int J Impot Res. 2002;14(2):81-84. doi:10.1038/sj.ijir.3900829
19. Antonini G, Busetto GM, Del Giudice F, et al. Distal Corporal Anchoring Stitch: A Technique to Address Distal Corporal Crossovers and Impending Lateral Extrusions of a Penile Prosthesis. J Sex Med. 2017;14(6):767-773. doi:10.1016/j.jsxm.2017.04.669
20. Karpman E, DiGiorgio L, Carrion RE. Distal Biologic Cap for Impending Distal Erosion. J Sex Med. 2020;17(3):551-555. doi:10.1016/j.jsxm.2019.11.265
21. Clavell-Hernández J. Proximal Extracapsular Tunneling: A Simple Technique for the Management of Impending Cylinder Erosion and Complications Related to Corporal Dilation. Sex Med. 2021;9(3):100379. doi:10.1016/j.esxm.2021.100379
22. Egydio PH, Kuehhas FE. Distal penile shaft reconstruction and reinforcement: the "double-windsocks" technique. J Sex Med. 2013;10(10):2571-2578. doi:10.1111/jsm.12263
23. Köhler TS, Gupta NK, Wilson SK. Incision Dehiscence and Wound Drainage Following IPP. In: Köhler TS, Gupta NK, Wilson SK, eds. Wilson's Pearls, Perils and Pitfalls of Penile Prosthesis Surgery. 2nd ed. Calvert McBride Publishers; 2018:124-126.
24. da Justa DG, Bianco FJ Jr, Ogle A, Dhabuwala CB. Deep venous thrombosis due to compression of external iliac vein by the penile prosthesis reservoir. Urology. 2003;61(2):462. doi:10.1016/s0090-4295(02)02115-5
25. Brison D, Ilbeigi P, Sadeghi-Nejad H. Reservoir repositioning and successful thrombectomy for deep venous thrombosis secondary to compression of pelvic veins by an inflatable penile prosthesis reservoir. J Sex Med. 2007;4(4 Pt 2):1185-1187. doi:10.1111/j.1743-6109.2006.00266.x
26. Hernández JC, Trost L, Köhler T, et al. Emerging Complications Following Alternative Reservoir Placement during Inflatable Penile Prosthesis Placement: A 5-Year Multi-Institutional Experience. J Urol. 2019;201(3):581-586. doi:10.1016/j.juro.2018.10.013
27. Reinstatler L, Shee K, Gross MS. Pain Management in Penile Prosthetic Surgery: A Review of the Literature. Sex Med Rev. 2018;6(1):162-169. doi:10.1016/j.sxmr.2017.05.005
28. Deveci S, Martin D, Parker M, Mulhall JP. Penile length alterations following penile prosthesis surgery. Eur Urol. 2007;51(4):1128-1131. doi:10.1016/j.eururo.2006.10.026
29. Joshi PM, Navarro J, Kulkarni SB, Aubé-Peterkin M. Penile Prosthesis Insertion After Urethroplasty. In: Joshi PM, Aubé-Peterkin M, Kulkarni SB, Datar G, eds. Surgical Atlas of Urethroplasty. Springer; 2024:383-388.
30. American Urological Association/Sexual Medicine Society of North America. The Diagnosis and Management of Priapism: an AUA/SMSNA Guideline. 2022, statement 15 and discussion. Companion publication: Bivalacqua TJ, Allen BK, Brock GB, et al. The Diagnosis and Management of Recurrent Ischemic Priapism, Priapism in Sickle Cell Patients, and Non-Ischemic Priapism: An AUA/SMSNA Guideline. J Urol. 2022;208(1):43–52. doi:10.1097/JU.0000000000002767
31. Wilson SK, Delk JR, Salem EA, Cleves MA. "Long-term survival of inflatable penile prostheses: single surgical group experience with 2,384 first-time implants spanning two decades." J Sex Med. 2007;4(4 Pt 1):1074-1079. doi:10.1111/j.1743-6109.2007.00540.x
32. Campbell JD, Chan EP, Di Pierdominico A, et al. "Chronic pain associated with penile prostheses may persist despite revision or explantation." Can Urol Assoc J. 2022;16(2):42-46. doi:10.5489/cuaj.7391
33. Henry G, et al. “Observation of local clinical penile prostheses infections instead of immediate salvage rescue/removal: multicenter study with surprising results.” J Urol. 2014;191(4 Suppl):e612–e613. doi:10.1016/j.juro.2014.02.1694
34. Bejany DE, Perito PE, Lustgarten M, Rhamy RK. “Gangrene of the penis after implantation of penile prosthesis: case reports, treatment recommendations and review of the literature.” J Urol. 1993;150(1):190–191. doi:10.1016/S0022-5347(17)35433-2
35. DailyMed. Tamsulosin Hydrochloride Capsules: Prescribing Information. Updated April 22, 2026. Drug label.
36. Xiang A, Braun AE, Chang C, Swerdloff D, Gross MS, Simhan J. "Penoscrotal inflatable penile prosthesis recipients often fully recover from pain at two weeks following placement." Int J Impot Res. 2025;37(2):133-138. doi:10.1038/s41443-024-00871-0
37. Köhler TS, Modder JK, Dupree JM, Bush NC, McVary KT. "Malleable implant substitution for the management of penile prosthesis pump erosion: a pilot study." J Sex Med. 2009;6(5):1474-1478. doi:10.1111/j.1743-6109.2009.01236.x
38. El-Achkar A, Khalafalla K, Nguyen TT, Wang R. "A systematic review comparing different approaches for inflatable penile prosthesis revision: partial-component exchange, complete-component exchange, or reservoir "drain and retain"." Sex Med Rev. 2024;12(3):519-527. doi:10.1093/sxmrev/qeae035
39. Deho' F, Henry GD, Marone EM, et al. "Severe vascular complication after implantation of a three-piece inflatable penile prosthesis." J Sex Med. 2008;5(12):2956-2959. doi:10.1111/j.1743-6109.2008.01012.x
40. Wilson SK, Henry GD, Delk JR Jr, Cleves MA. "The Mentor Alpha 1 penile prosthesis with reservoir lock-out valve: effective prevention of auto-inflation with improved capability for ectopic reservoir placement." J Urol. 2002;168(4 Pt 1):1475-1478. doi:10.1016/S0022-5347(05)64477-1
41. Osterberg EC, Maganty A, Ramasamy R, Eid JF. "Pharmacologically induced erect penile length and stretched penile length are both good predictors of post-inflatable prosthesis penile length." Int J Impot Res. 2014;26(4):128-131. doi:10.1038/ijir.2013.50