Plaque Incision / Excision with Grafting
Plaque incision or excision with grafting (PIG / PEG) is the tunical lengthening arm of the Peyronie's disease (PD) surgical algorithm. It corrects curvature by releasing or partially removing the contracted plaque on the concave side and patching the tunical defect with a graft. Unlike plication, PIG/PEG releases the concave side and aims to limit shortening while correcting severe or complex deformity. Long-term length gain is uncommon, supplemental plication may shorten the penis, and postoperative erectile dysfunction is a substantial risk.[1][2][24]
Tunical lengthening is an option for men with normal erectile function, inadequate penile length, severe curvature or complex deformity .[24] Curvature >60° is a proposed, unvalidated threshold; erectile rigidity, deformity and length guide selection.[24]
Terminology — incision vs excision
The terms PIG and PEG are used interchangeably in the literature but describe distinct plaque-management approaches:
| Term | Definition | Current role |
|---|---|---|
| Plaque incision (PIG) | Plaque is incised (cut through) but not removed; resulting tunical defect is grafted | Most commonly performed today — preserves native tissue, smaller defects |
| Partial plaque excision (PEG) | Most fibrotic / calcified portion of plaque excised; surrounding tunica preserved | Levine's preferred approach — removes the dominant scar without sacrificing peripheral tunica |
| Complete plaque excision | Entire plaque removed | Rarely performed today — larger defects, higher ED rates, no demonstrated superiority |
The AUA Guideline uses the inclusive phrase "plaque incision or excision and/or grafting" to encompass all variants.[1]
Indications
The AUA 2015 PD Guideline allows plaque incision or excision and/or grafting for men with deformities whose rigidity is adequate for coitus, with or without pharmacotherapy and/or vacuum device therapy , and bases surgical candidacy on stable disease .[1] PIG/PEG is appropriate for:[1][2][3][11]
- Curvature > 60° where plication would produce unacceptable shortening
- Complex deformity. Hourglass, hinge effect, compound or biplanar curvature. For selected hourglass or hinge indentation, consider extratunical grafting with or without plication as a tunica-preserving alternative; supporting series are small.[24][36]
- Short penis where length preservation is the dominant goal
- Adequate erectile rigidity for coitus (with or without pharmacotherapy or VED under AUA statement 19); the AUA discussion identifies intact erectile function or ED responsive to oral medication or VED as the most appropriate graft candidates.[1] When ED or vascular status is uncertain, consider penile Doppler ultrasound before grafting to assess hemodynamics .[24]
- Stable disease phase. The AUA requires symptoms unchanged for at least 3 months; surgical series typically required at least 12 months from onset and 3–6 months of stable curvature
The 2026 BJU Guideline-of-Guidelines reports that grafting is generally reserved for preserved erectile function and prosthesis for refractory ED.[11] The Fifth International Consultation on Sexual Medicine also recommends considering a prosthesis for patients at high risk of postoperative ED .[37] EAU 2026 uses lengthening (incision or excision with grafting) for men with normal erectile function who have inadequate length, severe curvature or complex deformity , warns of de novo ED up to 50% in men without preoperative ED, notes that complete plaque removal may raise venous-leak ED (partial excision may be acceptable with florid calcification), and identifies no superior graft; it states that grafting without a concomitant prosthesis in complex deformity raises complication risk including ED, so primary prosthesis is a limited-evidence alternative.[24]
Patients to counsel against. In the Langbo / Levine series of 251 PEG patients, 22% were initially advised to undergo IPP but elected PEG; these patients had significantly lower postoperative ability to engage in intercourse (51% versus 76%) and a higher rate of eventual IPP conversion (13% versus 4%), reinforcing the importance of the algorithm.[10]
Technique — Plaque Incision vs. Partial Excision
Partial plaque excision with grafting (PEG)
Partial excision for selected plaques. Plaque incision with grafting is a tunical-lengthening approach; partial excision may be used for florid calcification while avoiding the potential erectile-function cost of complete plaque removal.[24]
Steps:
- Degloving or subcoronal incision with full penile mobilization
- Approach-specific exposure. For a dorsal plaque, lift the dorsal neurovascular bundle from the tunica (Lue technique); a lateral plaque may be exposed laterally without full dorsal mobilization. For a ventral plaque, dissect and protect the urethra and corpus spongiosum as needed before tunical incision.[4][12]
- Artificial erection and relaxing incision. After approach-specific exposure, induce a saline artificial erection to identify the point of maximum curvature, then make an H-shaped or Y-shaped relaxing incision through the plaque on the concave side.[4][12]
- Partial excision when selected: excise the area of maximal deformity, including a tethered septal portion when needed, while protecting cavernosal tissue; do not resect tunica beneath the urethra. Florid calcification is one circumstance in which partial excision may be considered.[24][38] For a selected bothersome calcified plaque where preserving the overlying tunica is desired, a tunica-sparing technique has been described: a lateral longitudinal opening slightly larger than the plaque is made, the calcification is separated from the underlying erectile tissue, and the overlying tunica is carefully dissected free from the plaque (about 3–4 mm) with a fresh blade under magnification before the tunical opening is closed with interrupted sutures starting at the corners to avoid trapping the neurovascular bundle. This dissection is slow and technically demanding. This is a separate, graft-free operation rather than a comparative recommendation: the original 12-man series selected >1.5 mm of overlying tunica on ultrasound, used primary tunical closure, and added plication for straightening; graft harvest and inlay in steps 5–6 do not apply.[25][33]
- Graft harvest and sizing. Measure the opened defect under penile stretch and tailor the graft to its shape and material; in the described sutured pericardial PEG technique, the patch is cut 2–3 mm longer than the measured defect, whereas collagen fleece sealing requires at least 5 mm of overlap on each side.[38]
- Graft suturing into the tunical defect with running non-absorbable monofilament suture (Prolene 4-0 or 5-0) or absorbable suture (PDS)
- Repeat saline artificial erection testing after sutured graft inlay to assess straightening and check the closure for leaks before closing Buck's fascia.[39] After self-adherent collagen fleece placement, the sealing technique limits reinflation to about 80% of maximal erection; avoid high-pressure filling that may lift the patch.[37][38]
- Closure of Buck's fascia and redraping
Plaque incision without excision (relaxing incisions + grafting)
Incisions through the plaque without excision: the plaque is divided to allow the concave side to open up, and the resulting defect is grafted. Preferred when the plaque is densely adherent to the neurovascular bundle or when excision would risk NVB injury.[4]
In a retrospective multicenter post-CCH series of 90 men (25 grafting with IPP, 18 grafting alone and 47 Nesbit plication), graft-material details below concern the 43 grafted men, whereas the complication and recurrent-curvature counts concern the full cohort at three months:[4]
- Among the 43 grafted men, the graft was bovine pericardium in 22 (51.2%) and collagen fleece in 21 (48.8%)[4]
- Median postoperative penile length: 13.0 cm (IQR 12.0–15.0)
- At three months, 86/90 (95.6%) men in the mixed-procedure cohort had no complication recorded under the authors' endpoint; all 43 graft recipients nevertheless reported paresthesia of ungraded severity.[4]
- Persistent/recurrent curvature >20° at three months in the mixed-procedure cohort: 4 of 90 (4.4%).[4]
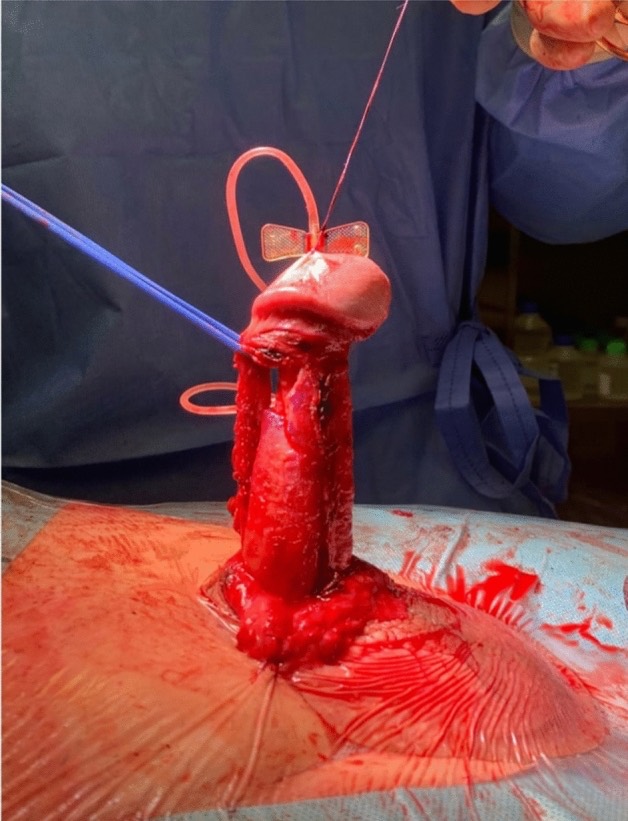
Standard double-Y relaxing incision of the tunica albuginea, opened to straighten the penile shaft completely; the resulting defect is then grafted. From Cocci A, et al. Sci Rep. 2021;11(1):166, Figure 2 (CC BY 4.0).[4]
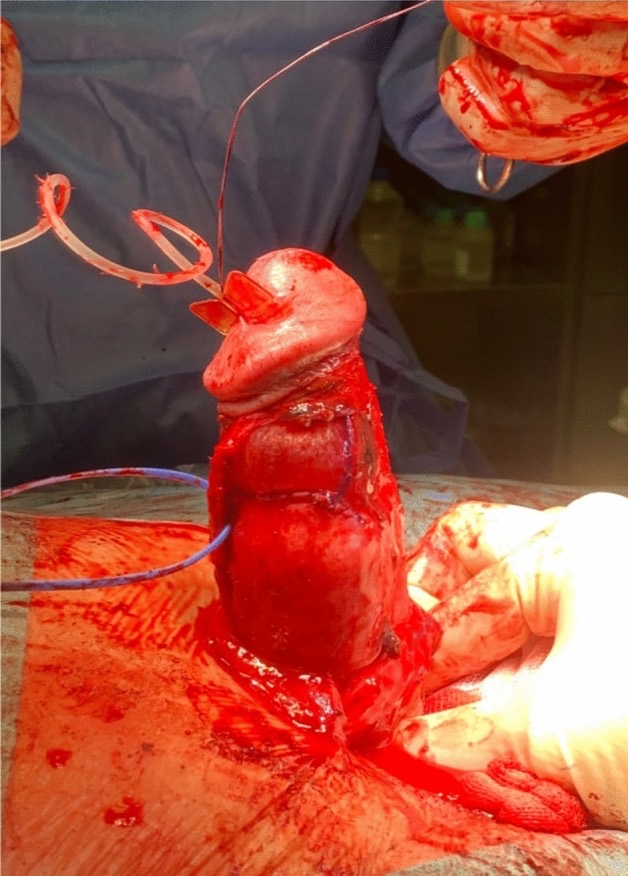
The graft is applied to the tunical defect and fixed to its edges with a running 4-0 polydioxanone (PDS) suture. From Cocci A, et al. Sci Rep. 2021;11(1):166, Figure 3 (CC BY 4.0).[4]
Incision patterns
Several incision configurations have been described:
| Pattern | Description | Notes |
|---|---|---|
| H-incision (Lue 1998)[12] | Two parallel longitudinal incisions connected by a transverse incision through the plaque | Most widely used; rectangular defect; controlled expansion. |
| Double-Y / stellate | Y-shaped incisions at each end of the plaque (or cruciate) | Diamond-shaped defect |
| Single relaxing incision | One transverse incision across the plaque | Simplest; for mild contractures |
| Egydio geometric | One geometrically planned incomplete circumferential double-Y relaxing incision, with grafting | Sansalone 2011 European multicenter series (n=157): mean intraoperative stretched-length gain 2.5 cm (range 1.7–4.1 cm); 19/157 (12%) had mild residual curvature <15° at three months (88% without residual curvature); median follow-up was 20 months[13] |
| Egydio Tunica Expansion Procedure (TEP) | Multiple staggered small cuts on the tunica without graft, used with penile prosthesis implantation | In 416 implant recipients with or without PD, penile gain was 3.3 cm (range 2–6 cm) intraoperatively across the full cohort; curvature was corrected during surgery in the 287 PD cases[14] |
The Hatzichristodoulou "sealing" technique
The TachoSil sealing technique has been described with an equine-collagen patch coated with human fibrinogen and thrombin after partial plaque excision.[5] Penile tunical sealing is outside the current US labeled indication, which covers adjunctive hemostasis on cardiovascular or hepatic tissue; the label contraindicates use in patients with a known anaphylactic or severe systemic reaction to human blood products or horse proteins.[23] Evarrest has a different carrier: oxidized regenerated cellulose and polyglactin 910 fibers, not collagen. Its results and handling instructions should not be substituted for TachoSil data.[23]
Steps:
- Penile degloving; NVB mobilization
- Partial plaque excision on the concave side
- Apply the collagen fleece after moistening it with saline, with the yellow fibrin-coated face against the tunical defect and at least 5 mm overlap on each side; hold the penis on moderate stretch while molding the patch to form a watertight seal.[38]
- Gentle pressure for 3–5 minutes to ensure adherence
- No suture fixation required for the graft
Outcomes (319 of 367 operated patients returned for long-term evaluation; 86.9% follow-up):[5]
- Median operative time: 79.8 minutes (range 50–130)
- Intraoperative complete straightness: 299/319 (93.7%)[5]
- Mean penile length increase: 1.1 ± 0.6 cm (P=.017)
- At median 47.2-month follow-up, 291/319 (91.2%) maintained complete straightness.[5]
- Glans sensation returned to baseline in 300/319 (94%) at long-term evaluation.[5]
- Patient satisfaction: 87.8%; partner satisfaction: 84.3% among 319 long-term participants.[5]
- Erectile function worsened in 50/319 (15.7%), improved in 78/319 (24.5%) and was unchanged in 191/319 (59.8%) at long-term evaluation.[5]
- Eleven treatment-related Clavien-Dindo grade 1 complications were reported
These are outcomes among followed patients in a prospective cohort. A separate four-center retrospective collagen-fleece cohort (n=88) reported postoperative ED in 38.6% and residual curvature in 19.3% at median 31 months.[34]
Graft Materials
Avoid synthetic materials such as polyester (Dacron) and PTFE (Gore-Tex) for penile grafting because of infection, fibrosis, contracture and allergy concerns .[24][37]
Buccal mucosa graft (BMG) — autologous
A 2026 systematic review and meta-analysis of 17 reports (9 full texts and 8 abstracts) found:[6]
| Outcome | Value |
|---|---|
| Success rate | 98.6% |
| Satisfaction | 92.1% |
| De novo ED rate | 1.7% |
| Penile shortening rate | 1.1% |
| IIEF-5 change | +1.69 points |
| Length of affected side | +1.99 cm |
BMG is a thin, flexible autologous graft option with favorable results in selected series, but cheek harvest adds donor-site morbidity. The 2026 review included eight abstract-only reports, direct comparisons have not established superiority over other grafts, and EAU recommends no single graft material.[6][24] For harvest and handling, see buccal mucosa graft — foundations. For BMG harvest and handling, see buccal mucosa graft — foundations.
Hemostatic patches (TachoSil, Evarrest)
- Different carriers: TachoSil uses equine collagen; Evarrest uses oxidized regenerated cellulose plus polyglactin 910.[23]
- Suture-free tunical coverage has been reported.[5]
- Farrell 2019 was a small retrospective IPP-plus-grafting comparison: 18 mixed-patch cases (10 Evarrest, 6 Nu-Knit, 2 TachoSil) versus 15 pericardium cases. Median follow-up was 6.6 months for patches and 34.6 months for pericardium.[7]
- For product labels and handling distinctions, see the fibrin sealant patch hub.
Pericardial grafts and CorMatrix
- Veritas is bovine pericardium, Tutoplast is processed cadaveric (human) pericardium, and CorMatrix is a porcine extracellular-matrix product
- Pericardium has a long track record in PD grafting, with reliable handling and suture retention
- Cadaveric pericardium was associated with satisfaction with erectile function in one retrospective analysis (OR 61.4, 95% CI 7.7–491; a wide interval from a small subgroup)[8]
- In Farrell's 33-patient IPP-plus-grafting comparison, observed curvature and intercourse outcomes showed no clear difference, and mean operative time was longer with pericardium (166 versus 122 minutes); median follow-up differed markedly (34.6 versus 6.6 months), so equivalence was not established.[7]
Porcine small intestinal submucosa (SIS; Cook Biodesign)
- Remodels to host tissue over 6–12 months
- Good handling; acceptable outcomes
- Higher cost than some alternatives
Dermal graft — autologous
- Historical standard (Devine). Devine and Horton (1974) described surgical treatment of Peyronie's disease with an autologous dermal graft placed into the tunical defect[28]
- Meaningful donor-site morbidity (abdominal or inguinal harvest)
- Now less commonly used because of donor-site morbidity and reported veno-occlusive ED; no graft material has proved superior.[24]
Saphenous vein — autologous
- Lown ED rate in some series
- Donor-site consideration (saphenous vein harvest)
- Longer operative time
- Harvest has been described through several small incisions with tunneling between them, rather than one long skin incision, with tributaries ligated and their sites opened as the vein is segmented to reduce leakage; the segments are then joined into a single patch before inlay.[26]
- The deep dorsal vein has also been used as a local autologous graft. In a 1993 series of 44 operated men with Peyronie's disease, 18 underwent plaque incision with a deep dorsal vein graft through a single incision; the authors reported rapid return of shaft suppleness, but the report gave no comparative curvature or erectile-function outcomes.[29]
Tunica vaginalis — autologous
- Adjacent tissue, easily harvested
- Thin and flexible
- Useful in revision settings where other materials have been used
- Ainayev 2022 compared TV and BMG in 20 men per group. Both groups had 90% technical success (residual curvature ≤15°) at 24 months, with no statistically significant between-group erectile-function or length difference.[15]
Comparative graft data
Natsos 2024 systematic review and meta-analysis of grafts in PD surgery without prosthesis:[16]
- BMG. In Natsos et al.'s mostly single-arm reports, BMG series had the highest observed straightening rates and least reported de novo ED; baseline curvature was relatively low.
- TachoSil collagen fleece. Its series retained favorable straightening despite higher baseline curvature.
- Tutoplast (cadaveric pericardium). Higher postoperative ED was observed in the included series.[16][24]
- Most included studies were single-arm with a high risk of bias, and no randomized trial establishes graft superiority
Saphenous vein versus BMG (Danacıoğlu 2021, n=41): no significant differences in IIEF, length, or partner satisfaction; residual curvature 13.1% (SV) versus 11.2% (BMG).[17]
SIS versus collagen fleece (matched-pair analysis, Rosenhammer 2019, n=43 each, median curvature 80°): CF significantly faster (80 versus 104 min, p < 0.001); SIS had significantly more shortening (28% versus 5%, p = 0.007).[18]
Special Scenario: Compound / Biplanar Curvature
For severe compound curvature (primary and secondary plane), PEG alone is often insufficient, and supplemental plication in a second plane is typically required. The Levine group's 240-patient series with 161 compound-curvature patients:[3]
- Average primary curvature: 79° (range 35–140°)
- Average secondary curvature: 36° (range 20–80°)
- After PEG, average residual curvature: 30°, requiring 1–6 additional plication sutures
- At 61-month follow-up:
- Recurrent curvature after PEG plus supplemental plication: 12.4% at average 61-month follow-up.[3]
- Net change in penile length: +0.36 cm
- Decreased penile sensation after PEG plus supplemental plication: 13% at average 61-month follow-up.[3]
- Able to engage in penetrative sex after PEG plus supplemental plication, with or without pharmacotherapy: 79%.[3]
For severe compound deformity selected for PEG, residual curvature in a second plane may require supplemental plication, as in the Levine-group series; counsel about that possibility while choosing the overall operation according to rigidity, length, deformity and patient goals.[3][24]
Post-CCH Failure Surgery
A growing patient population: men who attempted intralesional CCH (Xiaflex) first and either did not achieve sufficient correction or developed complications (corporal rupture). In Cocci's 90-patient mixed-procedure series, 86/90 (95.6%) reported no recorded surgical complication and 4/90 (4.4%) had persistent or recurrent curvature >20° at three months; the authors also reported paresthesia in all 43 graft recipients without grading its severity.[4]
Microscopic Electric Rotary Grinding
A novel technique using fine electric rotary grinding (a modified dental-grade burr or equivalent) to precisely remove fibrotic plaque tissue under microscopic visualization, followed by grafting with tunica vaginalis or bovine pericardium.[9] The authors describe this as a preliminary single-center technique; their 21-patient series had mean follow-up of 12.1 months, and comparative precision, safety and broader adoption remain unestablished.[9]
Outcomes
Straightening
- Successful straightening: 80.0–96.4% among the four PIG studies reporting this outcome in a 12-study review; success definitions differed.[32]
- Modern large series (collagen fleece sealing, Hatzichristodoulou): among 319/367 patients evaluated long term, 93.7% were completely straight intraoperatively and 91.2% at median 47.2-month follow-up[5]
- BMG systematic review: 98.6% success[6]
Length
Grafting aims to limit shortening relative to plication, but durable length gain is uncommon and supplemental plication may still shorten the penis.[24] The 319-patient cohort reported a mean gain of 1.1 ± 0.6 cm.[5]
Erectile function
The main downside is erectile dysfunction. De novo ED was reported in 1.7% in a BMG meta-analysis[6] and 21% in a Levine PEG series[20]. In a different PIG series, 46% had a ≥6-point fall in the IIEF erectile-function domain at six months, a different endpoint from de novo ED[19]; results vary with patient selection, graft material and outcome definition. Mechanism is thought to involve veno-occlusive dysfunction at the graft–native-tunica interface.[1][8]
Mulhall predictors of postoperative ED (Flores / Mulhall 2011, multivariable analysis; n=56): degree of preoperative curvature, Egydio incision technique (larger tunical defects), patient age, and baseline venous leak. Mulhall's group discourages PIG in older men, those with venous leak, and those with profound curvature.[19]
Levine predictors (Taylor / Abern / Levine 2012; n=109): neither preoperative cardiovascular risk factors (HTN, DM, smoking) nor duplex parameters (PSV, EDV, RI) significantly predicted postoperative ED.[20] Rate was 10% TAP, 21% PEG.[20] In a later single-center retrospective PIG cohort, new ED occurred in 47/212 (22.2%) previously potent men and reoperation in 25/293 (8.5%) followed men over median 9.8-month follow-up; cardiovascular disease or diabetes was associated with new ED, without establishing causation or longer-term risk.[41]
Montorsi 2000 (n=50, vein graft, highly selected RigiScan and Doppler-normal cohort): only 6% ED, illustrating the patient-selection range across series.[21]
Comparative head-to-head — Yafi 2018 prospective multi-institutional
CCH versus plication versus PEG (n = 57):[22]
| Outcome | CCH (n=18) | Plication (n=14) | PEG (n=25) | p |
|---|---|---|---|---|
| Mean curvature correction | 23.3° (34.4%) | 72.0° (92.2%) | 71.8° (94.9%) | 0.001 |
| Mean IIEF-5 change | +5.7 | +4.9 | +2.2 | NS |
| Mean SPL change | −0.2 cm | −1.0 cm | +0.9 cm | 0.001 |
In Yafi et al.’s prospective nonrandomized comparison, mean curvature fell by 94.9% after PEG and 92.2% after plication. Mean stretched length changed by +0.9 cm after PEG and −1.0 cm after plication.[22]
Sensation
In a prospective 63-patient PIG series, sensory loss was reported by 21% at one week, 8% at six months and 3% at one year; one patient had extensive persistent loss at two years.[30] In a separate 319-patient partial-excision series, 300 (94%) returned to baseline glans sensation at median 47.2-month follow-up.[5]
Complications
| Complication | Rate |
|---|---|
| Erectile-function outcomes | 1.7% de novo ED in a BMG meta-analysis; 21% postoperative ED after PEG in one series; 46% had a ≥6-point IIEF-EF decline at six months in a separate PIG series.[6][20][19] |
| Decreased sensation | 21% at one week, 8% at six months and 3% at one year in a 63-patient PIG series.[30] |
| Hematoma | 0–4.0% in four reporting PIG studies.[32] |
| Persistent/recurrent curvature | 4.4% at three months across mixed post-CCH procedures; 12.4% at average 61 months after PEG plus supplemental plication.[4][3] |
| Infection | 0–2.7% in five reporting PIG studies.[32] |
| Graft-related (rupture, migration) | Rate not quantified in the reviewed PIG studies.[32] |
| Urethral injury | Levine's PEG technique avoids tunical resection beneath the urethra.[38] |
Interrupted septal sutures placed during graft inlay, in addition to meticulous hemostasis, have been described as reducing subgraft hematoma at one center; no denominator or comparative effect size is reported for this maneuver.[27]
No PIG/PEG-specific VTE recommendation exists in the AUA or EAU guidelines. Apply the general risk framework (age, obesity, prior VTE, malignancy, prolonged operation or immobility) on the VTE Prophylaxis page rather than a procedure-specific rule.
The Langbo Lesson — Patient Selection Matters
A Levine-group analysis examined patients who were counseled toward prosthesis (based on suboptimal erectile rigidity) but elected for PEG instead:[10]
- Lower postoperative ability to engage in intercourse: 51% among men advised to receive IPP but choosing PEG versus 76% among men initially advised to receive PEG.[10]
- Higher rate of eventual penile prosthesis implantation: 7/54 (13%) among men initially advised IPP versus 7/197 (4%) among men initially advised PEG.[10]
PEG should be offered only to patients whose erectile function supports it. In this selected retrospective cohort (median follow-up 12 months), men initially advised to receive a prosthesis who chose PEG reported lower intercourse ability and had more subsequent prosthesis placement than men initially advised to receive PEG.[10]
Counseling
- In a 137-patient PEG cohort, 75.2% had stable or greater measured stretched length, but 46.0% perceived postoperative shortening.[35]
- ED risk is real. De novo ED was 1.7% in a BMG meta-analysis and postoperative ED 21% in one PEG series; a different PIG series found a ≥6-point IIEF-EF decline in 46% at six months. Estimates vary by graft, technique, baseline function and endpoint.[6][20][19]
- Recovery is longer than plication: typically 6–8 weeks before return to sexual activity. Once acute swelling and pain settle, begin a postoperative rehabilitation plan using a long-acting PDE5 inhibitor and/or penile traction (Fifth ICSM Scientific Principle).[37] In Rybak et al.'s retrospective PEG comparison, mean measured length change was +1.48 cm with traction (n=36) versus +0.24 cm without (n=23).[40]
- Complex deformities may require combined PEG and plication. Multi-element operations are expected for compound curvatures
- Patient selection. Patients counseled toward prosthesis who insist on PEG have materially worse outcomes
PIG/PEG vs Plication — Selection and Selected Cohort Outcomes
| Feature | PIG / PEG | Plication (TAP / 16-dot / PSP) |
|---|---|---|
| Mechanism | Lengthens concave side | Shortens convex side |
| Typical selection | Severe or complex deformity when plication would cause unacceptable shortening; the proposed >60° threshold is unvalidated[24] | Uncomplicated curvature with adequate length[24] |
| Penile length effect | In Yafi’s selected PEG group (n=25), mean stretched length changed +0.9 cm | In Yafi’s tunical-plication group (n=14), mean stretched length changed −1.0 cm; whole-cohort median follow-up was 12 months[22] |
| Erectile-function outcomes | 1.7% de novo ED in a BMG meta-analysis; 21% postoperative ED after PEG in Taylor et al.; 46% had a ≥6-point IIEF-EF decline at six months in Flores et al.[6][20][19] | 10% postoperative ED after TAP in Taylor et al.[20] |
| Operative time | Longer (80–165 min) | Shorter (48–80 min) |
| Curvature outcome in separate cohorts | 91.2% completely straight at median 47.2 months after collagen-fleece partial excision.[5] | 93% reported curvature <30° at survey after TAP (mean follow-up 72 months).[31] |
| Complexity | Higher (NVB mobilization, graft handling) | Lower (suture-only) |
| Sensory changes | More common (NVB mobilization) | Less common |
| Best long-term satisfaction series | 87.8% among 319/367 long-term respondents (Hatzichristodoulou, median 47.2 mo)[5] | 82% satisfied or very satisfied (Taylor–Levine TAP, n=61, mean 72 mo)[31] |
See Also
- Peyronie's disease — overview
- Tunica plication
- Prosthesis with adjunctive straightening
- Grafts in GU reconstruction — buccal mucosa
Videos
References
1. Nehra A, Alterowitz R, Culkin DJ, et al. Peyronie's disease: AUA guideline. J Urol. 2015;194(3):745–753. doi:10.1016/j.juro.2015.05.098
2. Levine LA, Lenting EL. A surgical algorithm for the treatment of Peyronie's disease. J Urol. 1997;158(6):2149–2152. doi:10.1016/s0022-5347(01)68184-9
3. Chow AK, Sidelsky SA, Levine LA. Surgical outcomes of plaque excision and grafting and supplemental tunica albuginea plication for treatment of Peyronie's disease with severe compound curvature. J Sex Med. 2018;15(7):1021–1029. doi:10.1016/j.jsxm.2018.04.642
4. Cocci A, Ralph D, Djinovic R, et al. Surgical outcomes after collagenase clostridium histolyticum failure in patients with Peyronie's disease in a multicenter clinical study. Sci Rep. 2021;11(1):166. doi:10.1038/s41598-020-80551-3
5. Hatzichristodoulou G, Fiechtner S, Pyrgidis N, et al. Suture-free sealing of tunical defect with collagen fleece after partial plaque excision in 319 consecutive patients with Peyronie's disease: the sealing technique. J Urol. 2021;206(5):1276–1282. doi:10.1097/JU.0000000000001933
6. Badr H, Bettocchi C, Alsalem A, et al. Surgical treatment of Peyronie's disease by plaque incision and buccal mucosa graft: a systematic review and meta-analysis. Asian J Androl. 2026;28(5):485–492. doi:10.4103/aja202543
7. Farrell MR, Abdelsayed GA, Ziegelmann MJ, Levine LA. A comparison of hemostatic patches versus pericardium allograft for the treatment of complex Peyronie's disease with penile prosthesis and plaque incision. Urology. 2019;129:113–118. doi:10.1016/j.urology.2019.03.008
8. Gamidov S, Shatylko T, Gasanov N, et al. Long-term outcomes of surgery for Peyronie's disease: focus on patient satisfaction. Int J Impot Res. 2021;33(3):332–338. doi:10.1038/s41443-020-0297-6
9. Jin DC, Luo Y, Wang P, et al. Microscopic electric rotary grinding of plaques combined with graft repair in the management of Peyronie's disease. J Vis Exp. 2024;(205). doi:10.3791/66305
10. Langbo WA, Wang V, Bajic P, Levine L. Long-term outcomes after plaque excision grafting for Peyronie's disease and subanalysis of patients who undergo the procedure despite preoperative counseling against it. J Sex Med. 2024;21(2):163–168. doi:10.1093/jsxmed/qdad164
11. Chierigo F, Fallara G, Tozzi M, et al. Guideline of guidelines: Peyronie's disease. BJU Int. 2026;137(5):770–782. doi:10.1111/bju.70201
12. Lue TF, El-Sakka AI. Venous patch graft for Peyronie's disease. Part I: technique. J Urol. 1998;160(6 Pt 1):2047–2049. doi:10.1016/S0022-5347(01)62239-0
13. Sansalone S, Garaffa G, Djinovic R, et al. Long-term results of the surgical treatment of Peyronie's disease with Egydio's technique: a European multicentre study. Asian J Androl. 2011;13(6):842–845. doi:10.1038/aja.2011.42
14. Egydio PH. An innovative strategy for non-grafting penile enlargement: a novel paradigm for tunica expansion procedures. J Sex Med. 2020;17(10):2093–2103. doi:10.1016/j.jsxm.2020.05.010
15. Ainayev Y, Zhanbyrbekuly U, Gaipov A, et al. Comparison of technical success and adverse events of plaque incision and grafting methods in patients with Peyronie's disease: tunica vaginalis versus buccal mucosa. Urology. 2022;170:226–233. doi:10.1016/j.urology.2022.07.063
16. Natsos A, Tatanis V, Kontogiannis S, et al. Grafts in Peyronie's surgery without the use of prostheses: a systematic review and meta-analysis. Asian J Androl. 2024;26(3):250–259. doi:10.4103/aja202358
17. Danacıoğlu YO, Çolakoğlu Y, Yenice MG, et al. Comparison of two different grafts for the surgical treatment of Peyronie's disease. Andrologia. 2021;53(3):e13987. doi:10.1111/and.13987
18. Rosenhammer B, Sayedahmed K, Fritsche HM, et al. Long-term outcome after grafting with small intestinal submucosa and collagen fleece in patients with Peyronie's disease: a matched-pair analysis. Int J Impot Res. 2019;31(4):256–262. doi:10.1038/s41443-018-0071-1
19. Flores S, Choi J, Alex B, Mulhall JP. Erectile dysfunction after plaque incision and grafting: short-term assessment of incidence and predictors. J Sex Med. 2011;8(7):2031–2037. doi:10.1111/j.1743-6109.2011.02299.x
20. Taylor FL, Abern MR, Levine LA. Predicting erectile dysfunction following surgical correction of Peyronie's disease without inflatable penile prosthesis placement: vascular assessment and preoperative risk factors. J Sex Med. 2012;9(1):296–301. doi:10.1111/j.1743-6109.2011.02460.x
21. Montorsi F, Salonia A, Maga T, et al. Evidence-based assessment of long-term results of plaque incision and vein grafting for Peyronie's disease. J Urol. 2000;163(6):1704–1708. doi:10.1097/00005392-200006000-00017
22. Yafi FA, Diao L, DeLay KJ, et al. Multi-institutional prospective analysis of intralesional injection of collagenase clostridium histolyticum, tunical plication, and partial plaque excision and grafting for the management of Peyronie's disease. Urology. 2018;120:138–142. doi:10.1016/j.urology.2018.06.049
23. Current US product labels: TachoSil, revised August 2025 and Evarrest. Carrier composition and product-specific instructions; accessed September 11, 2026.
24. EAU. Guidelines on Sexual and Reproductive Health, Limited Update March 2026, sections 8.2.3.b.2, 8.2.3.b.3 and 8.2.3.b.4.
25. Breyer BN, Reed-Maldonado AB, Lue TF. Procedures for Peyronie Disease. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:973–979.
26. Brant WO, Bella AJ, Lue T. Correction of Peyronie's Disease: Plaque Incision and Venous Grafting. In: Montague DK, Gill IS, Angermeier KW, Ross JH, eds. Textbook of Reconstructive Urologic Surgery. Informa Healthcare; 2008:694–698.
27. Atkinson D, Hellstrom WJG. Peyronie's Disease: Non-Autologous Graft Materials. In: Montague DK, Gill IS, Angermeier KW, Ross JH, eds. Textbook of Reconstructive Urologic Surgery. Informa Healthcare; 2008:699–703.
28. Devine CJ Jr, Horton CE. Surgical treatment of Peyronie's disease with a dermal graft. J Urol. 1974;111(1):44–49. doi:10.1016/S0022-5347(17)59886-9
29. Brock G, Kadioglu A, Lue TF. Peyronie's disease: a modified treatment. Urology. 1993;42(3):300–304. doi:10.1016/0090-4295(93)90619-L
30. Terrier JE, Tal R, Nelson CJ, Mulhall JP. "Penile Sensory Changes After Plaque Incision and Grafting Surgery for Peyronie's Disease." J Sex Med. 2018;15(10):1491-1497. doi:10.1016/j.jsxm.2018.07.020
31. Taylor FL, Levine LA. "Surgical Correction of Peyronie's Disease via Tunica Albuginea Plication or Partial Plaque Excision with Pericardial Graft: Long-Term Follow Up." J Sex Med. 2008;5(9):2221–2228. doi:10.1111/j.1743-6109.2008.00941.x
32. Rice PG, Somani BK, Rees RW. "Twenty Years of Plaque Incision and Grafting for Peyronie's Disease: A Review of Literature." Sex Med. 2019;7(2):115–128. doi:10.1016/j.esxm.2019.01.001
33. Eisenberg ML, Smith JF, Shindel AW, Lue TF. "Tunica-sparing ossified Peyronie's plaque excision." BJU Int. 2011;107(4):622–625. doi:10.1111/j.1464-410X.2010.09546.x
34. Costa Silva A, Cilio S, Ye A, et al. "A nationwide multicentric analysis of lengthening corporoplasty with collagene fleece in Peyronie's disease." Int J Impot Res. 2026;38(3):176–181. doi:10.1038/s41443-025-01036-3
35. Langbo WA, Sturgis MR, Roadman DF, Levine L. "Perception and Reality of Postoperative Penile Length in Men Undergoing Plaque Excision and Grafting for Peyronie's Disease." Int J Impot Res. 2026. doi:10.1038/s41443-026-01352-2
36. Ceballos B, Baumgarten AS, Krug AM, Morey AF. "Extratunical grafting for minimally invasive management of complex Peyronie's disease deformities." J Sex Med. 2024;21(6):579–581. doi:10.1093/jsxmed/qdae049
37. Chung E, Ziegelmann M, Lin HC, et al. "Management of Peyronie's disease: recommendations from the Fifth International Consultation on Sexual Medicine (ICSM 2024)." Sex Med Rev. 2026;14(1):qeaf068. doi:10.1093/sxmrev/qeaf068
38. Hatzichristodoulou G, Tsambarlis P, Kübler H, Levine LA. "Peyronie's graft surgery—tips and tricks from the masters in andrologic surgery." Transl Androl Urol. 2017;6(4):645–656. doi:10.21037/tau.2017.07.17
39. Lue K, Emtage JB, Martinez DR, Yang C, Carrion R. "Excision and patch grafting of a lateral Peyronie's plaque—utilizing a longitudinal 'window' approach." Sex Med. 2015;3(2):86–89. doi:10.1002/sm2.49
40. Rybak J, Papagiannopoulos D, Levine L. "A retrospective comparative study of traction therapy vs. no traction following tunica albuginea plication or partial excision and grafting for Peyronie's disease: measured lengths and patient perceptions." J Sex Med. 2012;9(9):2396–2403. doi:10.1111/j.1743-6109.2012.02849.x
41. Sarna S, Pang KH, Christopher AN, Ralph DJ, Muneer A, Alnajjar HM. "Plaque incision and grafting for peyronie’s disease: 15-year experience and functional outcomes from a high-volume andrology centre." Int J Impot Res. Published online June 1, 2026. doi:10.1038/s41443-026-01296-7