Inflatable Penile Prosthesis with Adjunctive Straightening — Comprehensive Guide
For patients with Peyronie's disease and erectile dysfunction refractory to medical therapy, or with severe deformity and borderline EF, the inflatable penile prosthesis (IPP) addresses both problems simultaneously. The device replaces native erectile function and serves as a rigid internal splint against which the curved penis is straightened. In a retrospective multicenter cohort of 499 men with PD undergoing IPP, 82.4% underwent an adjunctive curvature-correction procedure.[1] Described techniques include manual modeling, scratch, plication, plaque incision or grafting, transcorporeal punch excision, and length restoration.[2][12][16][17]
Indications
- PD and ED refractory to oral medications, VED, and ICI
- Deformity preventing coitus with preserved erectile rigidity. Assess plication or incision/grafting according to penile length and deformity complexity. The AUA permits prosthesis when deformity still prevents coitus despite pharmacotherapy or vacuum therapy ; the EAU recommends prosthesis for ED not responding to pharmacotherapy .[2][23]
- Patient preference. A one-operation approach is considered after stable PD and functional impairment are documented; the EAU recommends surgery only when disease is stable and intercourse is compromised .[2][3][23]
Prosthesis Selection
The AUA recommends an inflatable prosthesis for PD prosthetic surgery , citing, in the panel's experience, fewer adverse events and high satisfaction with reinforced-silicone or Bioflex inflatable devices, and the difficulty of intraoperative modeling with a semi-rigid device.[2] A separate review describes modeling as an initial maneuver for residual curvature after implantation.[4]
- Allows manual modeling for residual curvature after implantation; the EAU says it may be proposed first for curvature >30°.[23] Modeling is more difficult and may be less successful with semirigid devices.[2][3]
- Enables full inflation for intraoperative assessment of residual curvature
- Allows post-operative home modeling in patients with residual curvature
- Some PD studies report similar satisfaction with inflatable and malleable devices.[23]
Within inflatable devices:
- AMS 700 CX. Controlled-expansion cylinders are available with Momentary Squeeze or TENACIO pumps.[29]
- Coloplast Titan OTR / Touch. Comparable outcomes
- AMS 700 LGX. Often avoided in PD because longitudinal expansion can worsen a hinge deformity. Surgeon-dependent; some experienced implanters use LGX in PD without issue. The AMS 700 IFU precaution states that LGX cylinders in Peyronie's disease may not give a satisfactory result.[22]
See penile implants — implant models for the full device database.
Approach
The subcoronal approach is preferred when significant tunical work (grafting) is anticipated at implant, as it provides direct visualization of the entire shaft. Penoscrotal is acceptable for milder deformity requiring only modeling. See penile implants — surgical approaches.
The Adjunctive Ladder
From the Hammad 2025 J Sex Med multicenter study of 499 PD patients undergoing IPP:[1]
| Adjunctive technique | Frequency | Median curvature correction |
|---|---|---|
| IPP alone (no adjunct) | 17.6% | N/A [1] |
| Manual modeling (± scratch technique) | 74.7% | 26° [IQR 20–39.5°] [1] |
| Concurrent tunical plication | 4.8% | 40° [28.8–41.2°] [1] |
| Concurrent grafting | 2.0% | 55° [48.8–73.8°] in the grafting group [1] |
| Combined grafting and modeling | 0.8% | Not reported separately in the abstract [1] |
| Transcorporeal Shaeer's punch | Selected | Avoids degloving / NVB mobilization[12] |
| Length-restoration techniques | Severe shortening or length preservation | Mean postoperative penile length gain 2.5 cm in 43 complex-PD patients (Fernández-Pascual); 3.3 cm intraoperative penile gain in Egydio’s mixed 416-man cohort (287 with PD); and 2.8 cm mean intraoperative increase in distal corporal measurement in 32 mild-PD patients (Razdan).[9][13][14] |
For residual curvature after cylinder placement, implant, inflate, assess, model, reassess, and escalate if needed; scratch and Shaeer punch are endocavernosal maneuvers performed before cylinder placement.[12][16] The Hammad series is retrospective and its adjunct groups differed in baseline curvature. The AUA says clinicians may perform adjunctive modeling, plication, or incision/grafting when significant deformity persists after prosthesis insertion ; its review found no clear correlation between surgical complexity and infection, revision, or satisfaction in the available adverse-event evidence.[2]
An earlier series of 36 men with combined PD and ED defined how often an adjunct is needed when plaque-release incision is the secondary maneuver for residual curvature >10° (grafting only for overt exposure of the prosthesis). Inflation of a three-piece IPP alone corrected the curvature in 61%.[25] All men with preoperative curvature of 30° or less straightened with inflation alone, 86% of men with curvature >45° needed plaque incision, and grafting was required in 5.5%, both with preoperative curvature >60°.[25]
Step 1 — IPP Placement
Standard corporotomy, dilation and cylinder placement precede curvature assessment. In a retrospective single-center comparison, 66 men receiving serial Hegar dilation to ≥14 mm had less residual curvature and fewer adjunctive maneuvers than 218 earlier standard-dilation patients; one modeling-related urethral perforation occurred in each group.[5] Fibrosis disruption is a proposed mechanism.
Reported ECD protocol: After standard Dilamezinsert dilation, the study center added serial Hegar dilation to ≥14 mm before cylinder placement.[5]
Step 2 — Assess Residual Curvature
Device fully inflated; goniometer measurement in multiple planes. The EAU 2026 pathway calls for no further intraoperative correction when residual curvature is <30°; when it is >30°, manual modeling may be proposed before a shortening or lengthening maneuver.[23]
Step 3 — Manual Modeling (Wilson Technique)
Manual modeling, with or without scratch, was the most common adjunct in Hammad's 499-patient retrospective cohort (74.7%).[1] First-line because of its noninvasive nature, long-term efficacy, and low complication risk.[15] Best suited for inflatable devices; modeling is difficult with semi-rigid prostheses.[2] For the full deep dive on Wilson / Lucas / Moncada home-modeling protocols, modeling-force biomechanics, urethral-injury safety data, and modeling versus grafting decision rules, see Manual Modeling.
Mechanism. With the prosthesis fully inflated, forced bending against the point of maximal curvature fractures or weakens the plaque intraoperatively, allowing the penis to straighten over the rigid cylinders.
Wilson original technique:
- Place and fully inflate the cylinders. In the described Wilson technique, protect the pump from bending pressure with rubber-shod clamps on accessible cylinder tubing, and support any open corporotomies to prevent cylinder herniation.[3]
- Sustained glans pressure. Firm continuous pressure on the glans protects the urethra from injury
- Forceful counter-bending in the direction opposite to residual curvature
- 90-second sustained pressure intervals per Lucas optimal-modeling protocol; interval-of-pressure rather than rapid repetitive flexion
- Reassess curvature after each interval
- Repeat 90-second intervals as needed toward <15° residual curvature, stopping if correction plateaus.[26]
Lucas optimal-modeling refinements:
- 90-second interval pressure
- Distal-shaft bending proximal to the glans, with distal-tip and corporotomy protection[3]
- Mean curvature fell from 47.8° before modeling to 10.6° afterward among 40 Lucas-series patients.[26]
Moncada home modeling protocol for residual postoperative curvature: the patient bends the inflated device opposite the curvature daily for 6 months, beginning 4 weeks after implantation. In the published uncontrolled series (76 men with <45° residual curvature), 94.7% reached ≤10° at 6 months.[21]
In Hammad's modeling-with-or-without-scratch group, median intraoperative curvature reduction was 26° (IQR 20–39.5°).[1]
Safety considerations:
- Urethral perforation remains a risk (about 3% in the early modeling series).[3] Protect the distal tips and corporotomies, and bend from the distal shaft proximal to the glans rather than levering on the glans.[3][23]
- Cylinder injury from over-aggressive modeling is rare with modern devices
- If curvature resolves, proceed to closure. If curvature persists > 30° after adequate modeling, escalate to plication or grafting.
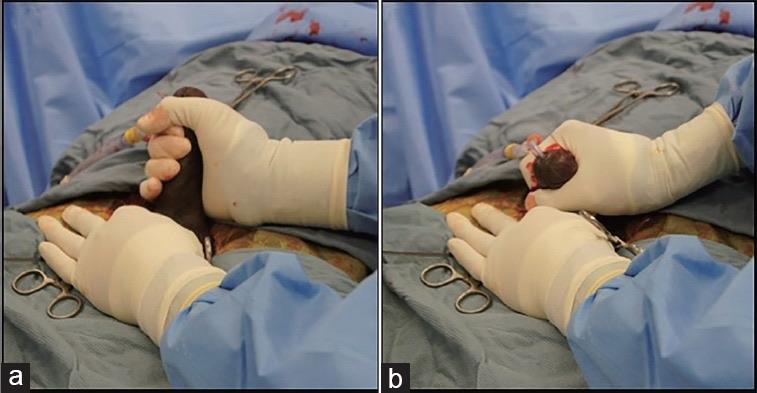
Modified manual modeling for residual curvature after inflatable penile prosthesis placement. (a) The bending hand is placed on the distal shaft, proximal to the glans, to avoid excessive pressure on the cylinder tips and to limit the risk of corporal blowout and urethral injury; the second hand stays on the proximal shaft with the fingers over the corporotomies to prevent device herniation. (b) The penis is bent opposite the curve and held until hand fatigue limits consistent force, usually 30–90 s; an audible pop or a sensation of plaque cracking may occur as collagen fibers are disrupted. From Ziegelmann MJ, et al. Asian J Androl. 2020;22(1):51-59, Figure 3 (CC BY-NC-SA).[3]
Step 3b — The Scratch Technique (Endocavernosal Plaque Disruption)
A variant in which the plaque is disrupted from within the corpus using a sharp instrument (Metzenbaum scissor tip or similar) passed through the corporotomy to score or scratch the inner surface of the tunica at the plaque site before cylinder placement.[16] For the full deep dive on the scratch technique (Bella–Brock lineage, instrument selection, intracavernosal incision patterns by plaque location, Antonini VED protocol detail, and complication profile), see Scratch Technique.
Lineage — the Brock technique
The conceptual ancestor of the modern scratch and punch family is the Bella–Brock minimally invasive intracorporeal plaque incision (Urology 2006, n=23).[19] Brock's group used a triangle-shaped scalpel originally designed for endoscopic carpal tunnel release introduced through a small (approximately 1 cm) corporotomy lateral to the plaque, making multiple intracavernosal incisions that disrupt the inner tunical surface while preserving the outer tunical layer, avoiding grafting in selected discrete plaques and limiting NVB mobilization.[19] In the original 23-patient series with median preoperative curvature 60° (range 30–90°), curvature correction was successful in 21/23 (91%) at a mean 25 months, with same-day or 24-hour discharge.[19] The original Brock technique was offered to patients with intact erectile function (not at IPP) for discrete plaques < 2 cm; the Antonini scratch protocol later adapted the same principle for use during IPP placement with postoperative vacuum therapy.[19][16]
Antonini protocol. IPP with scratch technique and postoperative VED therapy (3 minutes BID):[16]
- Prospective study in 145 patients
- At 24-week follow-up, after a prescribed 12-week VED course, mean residual curvature was 7.7–9.1° by plaque location; VED's separate effect was not measured.[16]
- After scratch, IPP, and modeling when needed, mean curvature was 14.1–21.5° at discharge and 7.7–9.1° at 24 weeks; the separate VED effect was not tested.[16]
- The authors describe the scratch technique, IPP placement, and postoperative vacuum therapy as a combined treatment for PD with concomitant ED.[16]
Technical features. Endocavernosal scratch avoids degloving and neurovascular-bundle mobilization. Antonini et al. reported no neurological impairment in 145 men but did not compare sensory outcomes or operative time with external incision; Wilson modeling was added after implant placement when needed.[16]
Shaeer's punch technique (transcorporeal plaque excision) is a related but more aggressive endocavernosal approach; see Step 4b below.
Step 4 — Concurrent Tunical Plication
Used in approximately 5% of cases.[1][6]
Technique:
- Permanent braided suture placed on the convex side of the penis, tying together the tunica at the point of residual curvature
- Can be placed before or after cylinder deployment:
- Pre-cylinder plication: place sutures before implant insertion but leave them untied during dilation and measurement; adjust and tie them after device inflation to avoid needle injury and premature corporal shortening.[6]
- Post-cylinder plication: assess residual curvature with the device inflated, then deflate fully before suturing; the distal cylinder may be moved proximally or removed from the corpus to avoid needle injury.[6]
Outcomes: Hammad reported a median 40° curvature correction (IQR 28.8–41.2°) in the concurrent-plication group.[1]
Chung / Blecher perspective
Concurrent plication at IPP is a defined technique. Chung and Blecher discuss pre- and post-implant plication for pronounced residual curvature, especially with calcified plaque or severe fibrosis; the sequence depends on the plaque and response to dilation and modeling.[6]
Step 5 — Concurrent Grafting (PICS Technique)
After IPP placement, Hatzichristodoulou described the penile implant in combination with the Sealing technique (PICS) for residual curvature >40°: plaque incision with collagen-fleece coverage of the tunical defect.[8] Grafting alone was used in 2.0% of PD-IPP cases, with combined grafting and modeling in another 0.8%.[1][7]
PICS technique (Falcone, Hatzichristodoulou)
- Complete IPP placement with cylinders in place
- Full device inflation
- In the original PICS technique, deflate the device, deglove the penis through a circumcising incision, open Buck's fascia, and elevate the neurovascular bundle at maximal curvature. Reinflate and incise the plaque while protecting the cylinders.[8]
- Collagen fleece (TachoSil) applied over the tunical defect with gentle pressure (3–5 min)
- No suture fixation required
- Confirm straightening; closure
Outcomes (Falcone multicenter study, 37 complex-PD patients):[7]
- Median preoperative curvature: 75° (IQR 65–77°)
- Median residual curvature after IPP alone: 60° (IQR 50–70°)
- Complete straightness after PICS: 31/37 (84%)[7]
- Residual curvature <20° in remaining cases
- No intraoperative complications; 6/37 (16%) genital hematoma, 3/37 (8%) transient fever, and one acute IPP infection requiring explantation[7]
A graft-free variant covers the tunical incisions with the mobilized neurovascular bundle. Djordjevic and Kojovic (2013) inserted malleable (49) or inflatable (13) prostheses through a ventral approach in 62 men with severe PD and ED, lifted the neurovascular bundle, incised the tunica albuginea at the plaque to correct deformity and gain length, and replaced the wide bundle over all incisions without corporal grafting. At a median 35 months (range 14–82), the penis was completely straight in 59 men (95%); glans numbness decreased or resolved spontaneously within 3 to 6 months.[24]
Outcomes for complex PD with severe shortening
Fernández-Pascual 2019 series of 43 complex-PD patients with severe shortening treated with an inflatable or malleable prosthesis, multiple corporeal incisions, and collagen fleece grafting:[9]
- Mean postsurgical length gain: 2.5 cm (range 1–5 cm)
- Average operative time: 86.7 min (IPP) / 71.6 min (malleable)
- No glans ischemia was recorded among 43 patients at median 21-month follow-up; one IPP infection and one delayed distal corporal erosion were recorded.[9]
- Hematoma or bruising: 23.2% among 43 men receiving IPP or malleable prosthesis with multiple incisions and collagen fleece[9]
- Overall satisfaction: 89.7% of 39 questionnaire respondents would recommend surgery[9]
- Among 39 questionnaire respondents, satisfaction with straightness was 94.9% and with length 82.1%.[9]
Step 4b — Pre-implant Alternative: Shaeer's Punch Technique (Transcorporeal Plaque Excision)
A minimally invasive alternative to external incision or grafting in which plaque is debulked from within the corpora using punch forceps passed through the corporotomy, avoiding degloving and NVB mobilization entirely.[12]
Series (Shaeer 2020, n = 26; mean curvature 58°):[12]
- All 26 punch patients had a straight penis after surgery; the punch step added 5–10 minutes, and one patient developed an infection.[12]
- Compared to 50 minutes for traditional excision and grafting
- Sensitivity was preserved in all 26 punch patients; 7 of 18 retrospective excision/grafting comparators reported glans hypoesthesia.[12]
- No graft material required; defect remains because the rigid IPP cylinder occupies the corpus
Particularly valuable when the plaque is densely adherent to the dorsal NVB and external mobilization carries unacceptable sensory-loss risk.
Step 6 — Length-Restoration Techniques
For patients with severe PD-related shortening in addition to curvature, several concurrent lengthening procedures are paired with IPP:[13][14][17] For the deep dive on sliding or slicing variants (Rolle SST, Egydio TEP geometric-cut algorithm, multiple corporeal incisions versus circumferential approaches, comparative complication data), see Sliding / Slicing Length-Restoration Techniques.
| Technique | Description | Length gain |
|---|---|---|
| Tunica Expansion Procedure (TEP, Egydio) | Multiple staggered, geometric small cuts through the tunica after Buck's-fascia mobilization and NVB dissection; tissue restitution by expansion, not graft substitution. NVB length is the rate-limiting step. Egydio 2020 series of 416 implanted men (287 with PD): mean intraoperative measured penile gain 3.3 cm, ventral glanspexy 92.8%, tunical-constriction relaxing incisions 40.9%.[13] A 2024 systematic review lists postoperative genital hematoma in 83/416 (19.9%) and glans numbness in 16/416 (3.8%) in this mixed cohort (287 with PD; follow-up reported as 12 [6–36] months).[28] Razdan 2024 modified scrotal approach in 32 men with mild PD: mean +2.8 cm distal corporal measurement intraoperatively and +1.6 cm midphallus girth after IPP inflation.[14] | Mean intraoperative penile gain +3.3 cm (Egydio, mixed cohort); mean intraoperative distal corporal measurement increase +2.8 cm (Razdan, mild-PD cohort) |
| Circumferential incision + grafting | Relaxing incisions around full tunical circumference + graft placement | Mean +2.8 cm (range 2.2–4.5 cm) among 20 of 23 men completing follow-up in Sansalone 2012[18] |
| Multiple relaxing corporeal incisions + collagen fleece (Fernández-Pascual) | Multiple small incisions along plaque + TachoSil grafting | Mean +2.5 cm (range 1–5 cm); 35/39 questionnaire respondents (89.7%) would recommend surgery; no glans ischemia observed among 43 treated patients[9] |
| Sliding / modified sliding technique | Original sliding mobilizes the neurovascular bundle and urethra and bridges dorsal and ventral tunical defects with grafts. The modified sliding (MoST) variant covers the defects with Buck's fascia and corporal/spongiosal tissue without graft.[3] | EAU 2026 recommends against the sliding technique because of reported glans necrosis ; newer variants have been described for use by experienced high-volume surgeons after full counseling.[17][23] |
| Ventral phalloplasty + suprapubic lipectomy | Adjunctive procedures to improve perceived length | Cosmetic gain only[17] |
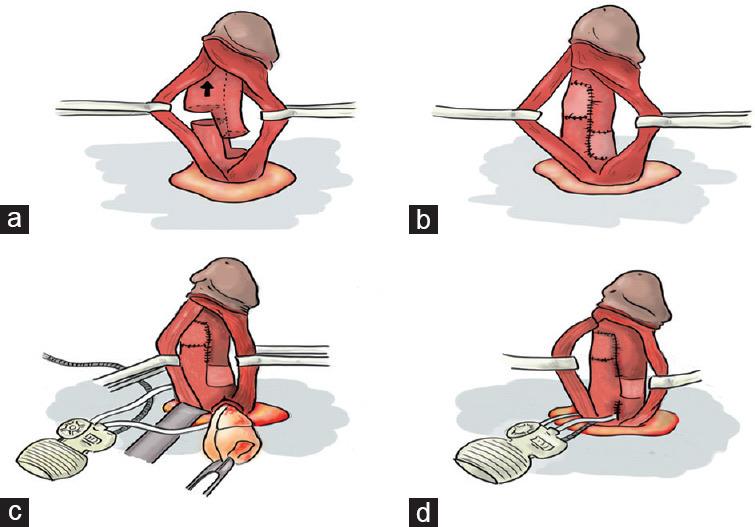
Modified sliding technique with prosthesis placement. (a) Sliding technique: stretching in the direction of the arrow stops when the neurovascular bundle reaches its maximum length. (b) The two tunical defects are covered with two rectangular grafts. (c) Insertion of the prosthesis in the modified sliding technique. (d) The proximal corporotomies are closed using the stay sutures. From Lo Re M, et al. Asian J Androl. 2026;28(1):3-8, Figure 2 (CC BY-NC-SA).[17]
Sansalone 2012 simultaneous-lengthening series (23 men with severe shortening; 20 completed follow-up at a mean of 22 months): IPP with circumferential incision and graft achieved a mean length gain of 2.8 cm (range 2.2–4.5). Glans sensitivity was reduced in 4 of 20, residual dorsal curvature under 15° persisted in 3, and 90% were satisfied.[18]
Step 7 — Postoperative Vacuum Therapy
In Antonini’s prospective, uncontrolled combined protocol, VED was prescribed without a constriction ring for 3 minutes twice daily for 12 weeks starting 2 weeks after discharge. Mean curvature was 14.1–21.5° at discharge after scratch, IPP, and modeling when needed and 7.7–9.1° at the 24-week assessment; the VED contribution was not isolated.[16]
Graft choice for IPP + grafting
Hemostatic patches versus pericardium allograft. Farrell 2019 was a retrospective comparison of 33 patients undergoing IPP placement with plaque incision or grafting. The 18 patch patients received Evarrest (10), Nu-Knit (6), or TachoSil (2); 15 received pericardium. Median follow-up was 6.6 months for patches and 34.6 months for pericardium.[10]
- Operative time: shorter with hemostatic patches (122 versus 166 min, P=.01)
- Residual curvature >20°: 16.7% (3/18 patch) versus 13.3% (2/15 pericardium), not significantly different[10]
- Penetrative intercourse: 94.4% (17/18 mixed-patch) versus 93.3% (14/15 pericardium), comparable[10]
- No complications attributable to graft material
- No IPP herniation through tunical defect in either group
Long-Term Outcomes
Straightening
- Curvature improvement above 80% in all 26 prosthesis studies that reported it in the AUA guideline review, with complete straightening in 85–100% of the seven studies that reported it (Grade C, observational)[2]
- Hammad 2025 reports curvature correction across modeling, plication, and grafting in the contexts where each is appropriate[1]
Satisfaction
Gamidov 2021 mixed-surgery cohort: At median 9.5-year follow-up, 342 men were assessed after several Peyronie procedures; erection satisfaction below uses the 285 sexually active men, while appearance and combined satisfaction use all 342.[11]
- 139/285 sexually active men (48.8%) were completely satisfied with erections; the abstract prints 40.6%, which uses all 342 assessed men as the denominator.
- 57.6% completely satisfied with penile appearance[11]
- Only 29.5% were completely satisfied with both appearance and erectile function[11]
Predictors of satisfaction with EF:[11]
- Preoperative IIEF-EF score (OR 1.67 per point)[11]
- Cadaveric pericardium graft (OR 61.4, 95% CI 7.7–491)[11]
- Saphenous vein graft (OR 8.5)[11]
- Tunica albuginea plication (OR 5.6)[11]
Predictors of satisfaction with appearance:
- Higher curvature severity: lower satisfaction (OR 0.93 per 5°)[11]
- Tunica plication was associated with lower appearance satisfaction (OR 0.12) in the mixed-surgery cohort.[11]
Complications
- IPP infection: one acute infection requiring explantation among 37 PICS patients (2.7%).[7]
- Glans ischemia after lengthening with neurovascular-bundle or urethral mobilization: A dusky or purple glans warrants prompt assessment. Remove the urethral catheter and penile wrap if present, fully deflate a partially inflated device, and expedite prosthesis removal if perfusion does not improve rapidly.[3]
- Mechanical failure: low with modern devices
- Genital hematoma: 6/37 (16%) after PICS; hematoma or bruising: 23.2% among 43 men after multiple incisions and collagen fleece with IPP or malleable prostheses.[7][9]
- Transient fever: 3/37 (8%) after PICS.[7]
- Residual curvature >20°: 3/18 (16.7%) after mixed hemostatic patches versus 2/15 (13.3%) after pericardium in Farrell’s IPP plus plaque-incision cohort.[10]
- The AUA review of observational studies found no clear correlation between adjunct complexity and infection, revision, or patient satisfaction.[2]
EAU 2026 position. The EAU recommends prosthesis implantation, with or without additional straightening (modeling, plication, incision or excision with or without grafting), for men with Peyronie's disease and ED that does not respond to pharmacotherapy . Its stepwise rule differs slightly from the intraoperative thresholds used below: if residual curvature after cylinder placement is under 30°, no further step is needed because the prosthesis acts as a tissue expander over the next six to nine months; if over 30°, manual modeling may be proposed first, although supporting evidence is limited (bending against the curvature for about 90 seconds with the device fully inflated), with a reported urethral perforation risk of about 3%; and if over 30° persists, shortening or lengthening procedures follow. Inflatable and malleable devices give similar satisfaction, satisfaction is lower than in men without Peyronie's disease although depression falls after surgery (19.3% to 10.9%), and the sliding technique is not recommended because of glans necrosis.[23]
Balzano Curvature-Based Algorithm
A useful operative algorithm, published by Balzano in Can J Urol 2022, keys the choice of adjunct to artificial erection findings, curvature magnitude, and curvature direction rather than to a fixed sequential ladder.[20]
| Artificial-erection finding | Curvature direction | Recommended adjunct |
|---|---|---|
| < 30° or isolated hourglass deformity | Any | Scratch technique |
| >30° | Dorsal or dorsolateral | Internal transverse incision via ventral corporotomy [20] |
| >30° | Lateral | Partial ipsilateral Buck's fascia elevation, plaque microperforations, and TachoSil coverage [20] |
| >30° | Ventral | Partial urethral elevation off the corpora, plaque microperforations, and TachoSil coverage [20] |
Balzano described an alternative sequence: assess curvature with an artificial erection, perform location-specific plaque correction, then insert the prosthesis. This retrospective single-center algorithm is not the post-implant adjunctive ladder above.[20] Internal transverse incision via the ventral corporotomy lets the surgeon address a dorsal plaque without separately degloving and mobilizing the dorsal NVB; partial Buck's elevation with microperforations tackles lateral or ventral plaques while leaving the underlying tunical scaffold mostly intact. In Balzano's 32-patient, single-surgeon series, isolated hourglass deformity or curvature <30° was managed with the scratch technique alone.[20]
Intraoperative Decision Algorithm
IPP placed, fully inflated, residual curvature measured
         |
         v
   Residual <15°       →   Close if functionally straight
         |
   Residual 15–30°     →   Observe or consider modeling by function
         |
   Residual >30°       →   Manual modeling (Step 3), then reassess
         |
   Persistent >30°    →   Plication or incision/grafting according to
                            deformity, length and tunical defect
The EAU 2026 pathway proposes modeling above 30°, on limited evidence, before further correction if curvature persists; operative choice remains anatomy dependent.[23]
The decision is sequential and graded: attempt the least-invasive maneuver first and escalate only when needed.
Counseling
- Both problems are addressed in one operation. This is the main appeal
- Manual modeling with or without scratch was used in 74.7% of the 499 PD-IPP cases in Hammad's retrospective cohort. Patients can be counseled that an adjunctive maneuver may be planned.[1]
- Plication or grafting may be added for severe residual curvature and may increase operative time.[1] The AUA guideline found no correlation between adjunct complexity and infection or revision in available adverse-event evidence.[2]
- Length restoration. A 43-patient multiple-incision and collagen-fleece series reported 1–5 cm of length gain. For adjunctive corporal lengthening, the Fifth ICSM cautions that serious complications can occur and advises an extensively experienced penile reconstructive surgeon (Scientific Principle).[9][27]
- Postoperative home modeling or vacuum therapy may be prescribed for residual curvature.
- Discuss appearance and erectile-function expectations separately.[11]
- Irreversibility. As with any IPP, natural erections end
See Also
- Peyronie's disease — overview
- Penile implants — surgical approaches
- Penile implants — implant models
- Scratch technique — endocavernosal plaque disruption (deep dive)
- Manual modeling — Wilson / Lucas / Moncada protocols (deep dive)
- Sliding / slicing length-restoration techniques (deep dive)
- Plaque incision / excision with grafting
- Tunica plication
Videos
References
1. Hammad MAM, Barham DW, Simhan J, et al. A multicenter evaluation of penile curvature correction in men with Peyronie's disease undergoing inflatable penile prosthesis placement. J Sex Med. 2025;22(2):349–355. doi:10.1093/jsxmed/qdae192
2. Nehra A, Alterowitz R, Culkin DJ, et al. Peyronie's disease: AUA guideline. J Urol. 2015;194(3):745–753. doi:10.1016/j.juro.2015.05.098
3. Ziegelmann MJ, Farrell MR, Levine LA. Modern treatment strategies for penile prosthetics in Peyronie's disease: a contemporary clinical review. Asian J Androl. 2020;22(1):51–59. doi:10.4103/aja.aja_81_19
4. Berookhim BM, Karpman E, Carrion R. Adjuvant maneuvers for residual curvature correction during penile prosthesis implantation in men with Peyronie's disease. J Sex Med. 2015;12 Suppl 7:449–454. doi:10.1111/jsm.13001
5. Katlowitz Y, Taniguchi H, Torremade J, Salter CA, Mulhall JP. Extended corporal dilation decreases the need for intraoperative adjuvant maneuvers for residual curvature after inflatable penile implant placement in men with Peyronie's disease. J Sex Med. 2026;23(5):qdag083. doi:10.1093/jsxmed/qdag083
6. Chung E, Blecher G. Perspective: residual penile curvature correction during penile prosthesis implantation by plication in Peyronie's patients. Int J Impot Res. 2023;35(7):643–646. doi:10.1038/s41443-023-00774-6
7. Falcone M, Preto M, Peretti F, et al. The use of collagen fleece to correct residual curvature during inflatable penile prosthesis implantation (PICS technique) in patients with complex Peyronie disease: a multicenter study. J Sex Med. 2023;20(2):229–235. doi:10.1093/jsxmed/qdac003
8. Hatzichristodoulou G. The PICS technique: a novel approach for residual curvature correction during penile prosthesis implantation in patients with severe Peyronie's disease using the collagen fleece TachoSil. J Sex Med. 2018;15(3):416–421. doi:10.1016/j.jsxm.2017.12.012
9. Fernández-Pascual E, Gonzalez-García FJ, Rodríguez-Monsalve M, et al. Surgical technique for complex cases of Peyronie's disease with implantation of penile prosthesis, multiple corporeal incisions, and grafting with collagen fleece. J Sex Med. 2019;16(2):323–332. doi:10.1016/j.jsxm.2018.11.014
10. Farrell MR, Abdelsayed GA, Ziegelmann MJ, Levine LA. A comparison of hemostatic patches versus pericardium allograft for the treatment of complex Peyronie's disease with penile prosthesis and plaque incision. Urology. 2019;129:113–118. doi:10.1016/j.urology.2019.03.008
11. Gamidov S, Shatylko T, Gasanov N, et al. Long-term outcomes of surgery for Peyronie's disease: focus on patient satisfaction. Int J Impot Res. 2021;33(3):332–338. doi:10.1038/s41443-020-0297-6
12. Shaeer O, Soliman Abdelrahman IF, Mansour M, Shaeer K. Shaeer's punch technique: transcorporeal Peyronie's plaque surgery and penile prosthesis implantation. J Sex Med. 2020;17(7):1395–1399. doi:10.1016/j.jsxm.2020.03.018
13. Egydio PH. An innovative strategy for non-grafting penile enlargement: a novel paradigm for tunica expansion procedures. J Sex Med. 2020;17(10):2093–2103. doi:10.1016/j.jsxm.2020.05.010
14. Razdan S, Zisman A, Valenzuela R. Scrotal approach for Tunica Expansion Procedure (TEP) for penile girth and length restoration during penile prosthesis implantation in patients with penile angulation due to Peyronie's disease and erectile dysfunction: technique and outcomes. Int J Impot Res. 2024;36(2):146–150. doi:10.1038/s41443-022-00652-7
15. Conlon WJ, Herzog BJ, Hellstrom WJG. Residual penile curvature correction by modeling during penile prosthesis implantation in Peyronie's disease patients. Int J Impot Res. 2023;35(7):639–642. doi:10.1038/s41443-023-00694-5
16. Antonini G, De Berardinis E, Del Giudice F, et al. Inflatable penile prosthesis placement, scratch technique and postoperative vacuum therapy as a combined approach to definitive treatment of Peyronie's disease. J Urol. 2018;200(3):642–647. doi:10.1016/j.juro.2018.04.060
17. Lo Re M, Alonso Isa M, Garcia Rojo E, et al. Advancements in penile lengthening techniques concurrent with penile prosthesis placement: a narrative review. Asian J Androl. 2026;28(1):3-8. doi:10.4103/aja202512
18. Sansalone S, Garaffa G, Djinovic R, et al. Simultaneous penile lengthening and penile prosthesis implantation in patients with Peyronie's disease, refractory erectile dysfunction, and severe penile shortening. J Sex Med. 2012;9(1):316–321. doi:10.1111/j.1743-6109.2011.02509.x
19. Bella AJ, Beasley KA, Obied A, Brock GB. Minimally invasive intracorporeal incision of Peyronie's plaque: initial experiences with a new technique. Urology. 2006;68(4):852–7. doi:10.1016/j.urology.2006.05.006
20. Balzano FL, Mian AH, Abramowitz DJ, et al. Novel Peyronie's algorithm at the time of penile implant. Can J Urol. 2022;29(4):11255-11261. PMID 35969730. (open-access PDF)
21. Moncada I, Krishnappa P, Ascencios J, Lopez I, Martinez-Salamanca JI. Home modeling after penile prosthesis implantation in the management of residual curvature in Peyronie's disease. Int J Impot Res. 2021;33(6):616–619. doi:10.1038/s41443-020-0325-6
22. Boston Scientific. AMS 700 Inflatable Penile Prosthesis with TENACIO Pump: Instructions for Use. 51558342-01A (US English). Precautions: LGX cylinders in Peyronie's disease.
23. EAU. Guidelines on Sexual and Reproductive Health, Limited Update March 2026, section 8.2.3.b.3 (penile prosthesis in Peyronie's disease).
24. Djordjevic ML, Kojovic V. "Penile Prosthesis Implantation and Tunica Albuginea Incision Without Grafting in the Treatment of Peyronie's Disease with Erectile Dysfunction." Asian J Androl. 2013;15(3):391-394. doi:10.1038/aja.2012.149
25. Mulhall J, Ahmed A, Anderson M. "Penile Prosthetic Surgery for Peyronie's Disease: Defining the Need for Intraoperative Adjuvant Maneuvers." J Sex Med. 2004;1(3):318-321. doi:10.1111/j.1743-6109.04046.x
26. Lucas JW, Gross MS, Barlotta RM, et al. "Optimal Modeling: an Updated Method for Safely and Effectively Eliminating Curvature During Penile Prosthesis Implantation." Urology. 2020;146:133-139. doi:10.1016/j.urology.2020.08.055
27. Chung E, Ziegelmann M, Lin HC, et al. "Management of Peyronie's disease: recommendations from the Fifth International Consultation on Sexual Medicine (ICSM 2024)." Sex Med Rev. 2026;14(1):qeaf068. doi:10.1093/sxmrev/qeaf068
28. Falcone M, Preto M, Morgado AR, et al. "Risk and benefits of penile length preservation techniques during penile prosthesis implantation: a systematic review by the young academic urologists sexual and reproductive health working group." Ther Adv Urol. 2024;16:17562872231215177. doi:10.1177/17562872231215177
29. Boston Scientific. "AMS 700 Inflatable Penile Prosthesis." Product catalog. Accessed October 8, 2026. Product specifications.