Feminizing Gender-Affirming Surgery
Feminizing genital gender-affirming surgery (GAS) comprises bilateral orchiectomy, vulvoplasty (zero or shallow depth), full-depth vaginoplasty (penile inversion, peritoneal flap or intestinal) and the component procedures within them (clitoroplasty, urethroplasty, labiaplasty). Breast or chest, facial feminization and voice surgery are covered in the Feminizing Procedures clinical-conditions article. Eligibility and perioperative hormone management follow WPATH SOC v8 (2022), the Endocrine Society 2017 clinical practice guideline (Hembree) and ACOG 2021.[1][2][6]
The sources are mainly retrospective series and reviews. They are the van der Sluis 2023 and Morrison 2023 reviews, Hehemann and Walsh 2019 on orchiectomy as a bridge to vaginoplasty, and Stelmar 2023 on offering shallow-depth vaginoplasty as a standard option (35 of 110 patients, 32%, chose it over full-depth).[7][8][9][10] Opsomer 2021 reports the 15-year Ghent series of 384 penile inversion vaginoplasties: 97.2% reported being able to engage in penetrative intercourse, 1.6% had rectal perforation and 37.1% had late revision.[11] Fakin 2021 is a retrospective single-centre comparison of single-stage and two-stage inversion vaginoplasty, in which depth was constant with the single-stage technique and fell by more than 30% in the first year with the two-stage technique.[13] Peritoneal flap series include Castanon 2022, Jacoby 2019 and Ratanalert 2026.[4][5][14] Lee 2025 is a prospective lower urinary tract cohort in which symptom scores and uroflowmetry did not worsen at 12 months after robotic peritoneal flap vaginoplasty.[15] Shamamian 2025 analyzes predictors of dilation difficulty, and De Rosa 2024 is a systematic review of vaginal stenosis.[17][18] Blasdel 2024 is a narrative review of surgeon-reported versus patient-reported urinary complications, and AFFIRM (Huber 2021) is a validated patient-reported instrument.[16][19]
Decision Framework
Eligibility and Readiness
Per WPATH SOC v8 and the Endocrine Society 2017 Clinical Practice Guideline:[1][6]
- Persistent, well-documented gender incongruence
- A single assessment opinion from a professional competent in transgender health when documentation is required (SOC v8 statement 5.5; SOC v7 called for two independent referrals for genital surgery, which could be sent in one jointly signed letter).[1][49]
- Age of majority for gonadectomy: the Endocrine Society 2017 guideline suggests delaying gonadectomy until then (recommendation 5.5), whereas SOC v8 statement 13.7 allows surgical interventions in eligible adolescents after multidisciplinary assessment[6][1]
- For eligible adults, SOC v8 suggests considering gonadectomy after tolerance of at least 6 months of hormone therapy, unless hormone replacement or gonadal suppression is not clinically indicated or the procedure is inconsistent with the patient's goals (statement 13.5).[1] For adult genital procedures, it suggests stability on the current regimen, which may include at least 6 months or longer if needed for the surgical result (13.6), unless hormones are not desired or are contraindicated. For eligible adolescents, SOC v8 statement 6.12.g specifies at least 12 months of hormone therapy before orchiectomy or vaginoplasty unless hormone therapy is not desired or is medically contraindicated.[1] The Endocrine Society 2017 guideline advised at least 1 year of consistent hormone therapy before genital surgery unless hormones were not desired or were medically contraindicated; SOC v7 listed 12 continuous months of hormone therapy unless hormones were not clinically indicated.[1][6][49]
- Capacity to consent to the irreversibility of gonadectomy and to the lifelong dilation commitment required after full-depth vaginoplasty
- Before gonadectomy, discuss fertility loss and sperm cryopreservation, and refer patients interested in preservation to a fertility specialist.[1]
Goal-Directed GU Pathway Selection
| Patient Priority | Standalone Orchiectomy | Vulvoplasty (Zero/Shallow-Depth) | Full-Depth Vaginoplasty |
|---|---|---|---|
| Remove testicular testosterone production / reduce antiandrogens[8] | ✓ | ✓ (included) | ✓ (included) |
| Feminine vulvar appearance only | ✗ | ✓ | ✓ |
| Receptive vaginal penetration | ✗ | ✗ | ✓ |
| Erogenous neoclitoral sensation | ✗ | ✓ | ✓ |
| Tissue and aftercare burden | Gonadectomy without canal construction | Vulvar reconstruction without a canal | Canal construction with ongoing dilation |
| No lifelong dilation commitment | ✓ | ✓ | ✗ (required) |
| Bridge to or option for future vaginoplasty | ✓ (preserve scrotal skin) | Possible, but secondary canal creation is more complex and may require peritoneal flaps plus extragenital skin grafts because genital donor tissue has been used.[47] | n/a |
Anchors: Saltman 2023 (NSQIP; 246 gender-affirming and 997 cisgender nononcologic orchiectomies; complication rate 3.7% for gender-affirming orchiectomy vs 4.4% for torsion, p = 0.6, and 5.9% for testicular pain, p = 0.2); Stelmar 2023 (single institution; 35 of 110 chose shallow-depth over full-depth; of 29 survey respondents, 86% would choose it again; 27% had complications needing further surgery, 82% of complications related to urinary spraying); van der Sluis 2020 (17 women over 30 years; 59% had no wish for receptive penetration; all 12 who reported satisfaction were satisfied); Hehemann and Walsh 2019 (orchiectomy as a bridge; preserve scrotal skin if future vaginoplasty is contemplated).[7][8][9][20][21]
Vaginoplasty Technique Selection
| Clinical Scenario | Approach and evidence | Alternative(s) | Avoid |
|---|---|---|---|
| Default candidate; adequate penile + scrotal skin (uncircumcised or sufficient tissue); standard depth (~14 cm) acceptable | Penile inversion vaginoplasty (PIV) is the most established technique and is called the gold standard in several of the cited series. A full-thickness skin graft to lengthen the canal was needed in 85.7% of 384 Ghent cases (Opsomer 2021).[11] Single-stage PIV had fewer complications in a retrospective comparison (Fakin 2021: wound dehiscence 4.8% vs 33.9%; one revision 6.4% vs one or more reoperations 56.5%; depth constant during the first postoperative year)[13] | Robotic peritoneal-augmented PIV (Jacoby 2019: +5 cm depth beyond skin-graft length in 41 combined PIV/peritoneal-flap cases at mean 114-day follow-up)[4] | PIV alone when donor tissue is clearly insufficient |
| Insufficient penile / scrotal skin (radical circumcision, puberty-blocker exposure, lichen sclerosus, scrotal hypoplasia) | Robotic or laparoscopic peritoneal-flap vaginoplasty can augment inverted penile skin when distal skin remains (Jacoby 2019; Castanon 2022). Full-length peritoneal lining has been described in a 10-patient series with 3-month follow-up (Ratanalert 2026). Plan distal canal and vulvar coverage against the actual genital-skin deficit.[4][5][14] A retrospective robotic peritoneal-flap series identified intra-abdominal complications requiring readmission or reoperation in 6/274 patients (2.2%), including two incarcerated internal hernias requiring laparoscopic reduction.[42] Castanon 2022 (n = 52): depth 14.7 ± 0.5 cm at 6 months, about 96% self-reported satisfaction, complications in 7 patients (13.5%), none of those complications needing further surgery.[14] Lee 2025 (n = 43): no worsening of lower urinary tract function at 12 months[15] | Augmentation of PIV with peritoneal flap (Jacoby) | Intestinal vaginoplasty as first-line in standard candidates (higher complication burden, mucus, rare neoplasia signal) |
| Failed primary vaginoplasty with refractory stenosis | Intestinal (sigmoid) vaginoplasty is an option after refractory stenosis following PIV. In a retrospective comparison of 45 such revisions, short-term complication rates were comparable for intestinal-segment and peritoneal-flap revision, while recurrent vaginal stenosis was reported more often after peritoneal-flap revision.[35] De Rosa reported 0.20% versus 5.70% vaginal stenosis for intestinal versus PIV procedures in a review limited to primary surgery.[18] | Robotic peritoneal-flap revision | Sigmoid as first-line in standard candidates (laparotomy/laparoscopy + bowel anastomosis; diversion-colitis-like inflammation; mucus burden) |
| Canal not desired | Vulvoplasty (zero- or shallow-depth) (Stelmar 2023; van der Sluis 2020[21]): high satisfaction, 86% of 29 survey respondents (of 35 patients) would choose it again, and 27% had complications needing further surgery, mostly urinary spraying (82% of complications)[9] | Standalone bilateral orchiectomy if external feminization is also deferred | Coercive canal creation; full-depth vaginoplasty when patient priorities don't include penetrative function |
| Active smoker; insufficient electrolysis | Defer vaginoplasty while actively smoking or before scrotal/perineal hair removal for the planned canal lining is complete; arrange preoperative smoking cessation and continue abstinence while the graft heals. In general-surgery trials, cessation for at least 4 weeks had greater benefit than shorter cessation.[40] Smoking impairs fibroblast proliferation and collagen deposition even after inflammatory-cell function begins to recover.[29] | Standalone orchiectomy as bridge | Vaginoplasty without preoperative electrolysis (intravaginal hair growth); resuming smoking before the skin graft has fully healed |
| Prior pelvic radiation | Vulvoplasty may be considered; a 2026 surgeon Delphi consensus classifies prior pelvic radiotherapy as a relative contraindication to full-depth vaginoplasty. Evaluate any canal-construction plan at an experienced center.[38] | Standalone orchiectomy | Sigmoid vaginoplasty in heavily irradiated bed without colorectal-surgery review |
| Prior radical prostatectomy | Some authors recommend vulvoplasty in this setting, reasoning that dissecting a full-depth vaginal canal may injure the external urinary sphincter and cause incontinence.[33] | Full-depth vaginoplasty with sphincter-sparing canal dissection at an experienced center | — |
Peritoneal vs Penile-Inversion vs Intestinal Sub-Comparison
| Feature | Penile Inversion (PIV) | Peritoneal Pull-Through (Robotic) | Sigmoid (Intestinal) |
|---|---|---|---|
| Depth measure | 14 cm intraoperative target in the Ghent series, not a measured mean (Opsomer 2021) | Jacoby reported 5 cm added beyond skin-graft length in 41 primary penile-inversion/peritoneal-flap cases (mean follow-up 114 days); Castanon reported mean depth 14.7 ± 0.5 cm at 6 months in 52 cases combining inverted penile skin with peritoneal flaps[4][11][14] | Mean 13.9 ± 2.0 cm at mean 6-month follow-up in 12 primary sigmoid cases (Salgado 2018)[39] |
| Fluid production | Penile/scrotal skin is not intrinsically secretory; incorporated urethral tissue or retained glands may produce some fluid | Peritoneum can secrete fluid, but volume and functional lubrication after transfer are unquantified | Bowel mucosa produces continuous mucus that may require hygiene management; no lining has proven arousal-responsive lubrication comparable to a natal vagina[36] |
| Donor-tissue requirement | Penile + scrotal skin (graft needed in 85.7% in the Ghent series)[11] | Peritoneal flaps augment canal lining, but the cited series also use inverted penile skin for the distal canal and genital skin for vulvar construction[4][14] | 12–15 cm sigmoid bowel segment in Salgado's primary series[39] |
| Microsurgery / robotics | None | Robotic platform (Da Vinci Xi or SP) or laparoscopic | Laparoscopic or open + bowel anastomosis |
| Dilation requirement | Lifelong, frequent | Lifelong, frequent; in Shamamian's mixed-technique vaginoplasty cohort, primary peritoneal graft was associated with dilation difficulty (OR 3.20)[17] | Ongoing dilation through the introitus and bowel-to-introitus anastomosis remains necessary; De Rosa reported 4.7% introital stenosis after primary intestinal vaginoplasty[18] |
| Vaginal-stenosis rate (De Rosa 2024 SR) | 5.70% (introital stenosis 3.13%) | Not reported separately | 0.20% (introital stenosis 4.7%)[18] |
| Rectoneovaginal fistula | Rectoneovaginal fistula 3/330 (0.9%) after primary PIV (Gaither; median follow-up 3 months)[28]; rectal perforation 6/384 (1.6%) in Ghent PIV[11] | Limited data | Anastomotic leak risk distinct from RVF |
| LUT function (Lee 2025) | n/a | No worsening at 12 mo (AUASI and UDI-6 declined, below the minimum important difference; uroflowmetry unchanged) | Limited prospective LUT data |
| Revision and follow-up | Ghent PIV: 37.1% late revision.[11] | Robotic peritoneal-flap cohort: 61/500 (12%) elective revisions; 425/500 (85%) followed at least 1 year. This is a different revision endpoint from the Ghent series, and longer follow-up remains limited.[46] | Limited long-term data |
| Ideal candidate | Standard candidate with adequate donor tissue | Insufficient donor tissue; revision; depth augmentation | Revision after refractory stenosis |
Component-Procedure Decisions Within Vaginoplasty
Clitoroplasty
| Anatomy | Recommended Technique | Notes |
|---|---|---|
| Uncircumcised, or circumcised with > 2 cm inner preputial skin and at least 8 cm of shaft skin proximal to the scar | Preputial-skin clitoroplasty with dorsal neurovascular pedicle glans-penis flap | Fascelli 2024 anatomy-guided framework[26]; the authors prefer it for greater coronal tissue volume and esthetics. Separately, Sigurjónsson 2017 reported orgasm in 86% of 22 assessed patients after glans-based neoclitoroplasty[22] |
| Circumcised or limited preputial skin | Urethral-flap clitoroplasty with dorsal NVB pedicle | Fascelli 2024; uses more corpus spongiosum, and the urethra forms the clitoral hood |
| Concern for neoclitoral viability | Protect the dorsal neurovascular pedicle during clitoroplasty | Neoclitoral necrosis occurred in 3/62 two-stage patients versus 0/63 single-stage patients in one retrospective center comparison (Fakin 2021).[13] |
Sigurjónsson 2017 measured tactile and vibratory sensitivity in 22 patients at a mean of 37 months and reported erogenous neoclitoral sensation; 86% of these 22 assessed patients experienced orgasm.[22]
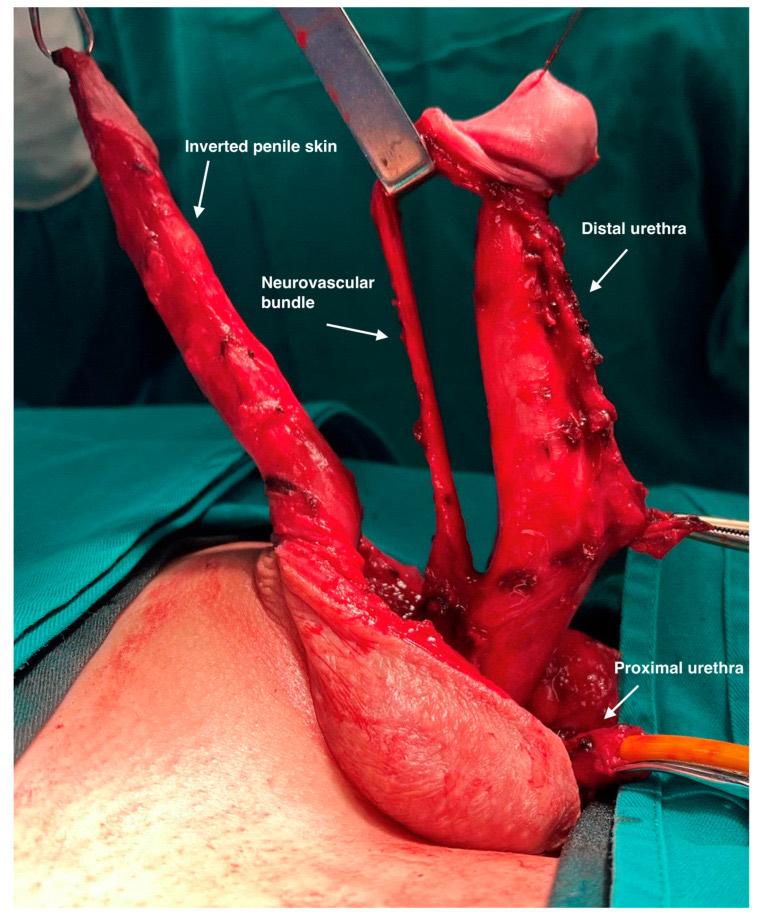
Penile disassembly during feminizing gender-affirming surgery. The penile skin is degloved and inverted, the dorsal neurovascular bundle is lifted from the corpora cavernosa with partial dissection of the dorsal glans, and the urethra is divided ventrally (catheterized proximal urethra at lower right). In this live-donor feasibility study the distal urethra was left attached to the corpora. From Pusica S, et al. Life (Basel). 2023;13(11):2212, Figure 3 (CC BY 4.0).[34]
Urethroplasty (Urethral Shortening + Repositioning)
The neomeatus is moved to a feminine position and the urethra is shortened. In the Blasdel 2024 narrative review, urinary complication rates in cohorts outside the operating surgeon's own reports were higher than surgeon-reported rates:[16][23]
| Outcome | Surgeon-Reported | Patient-Reported / Other Cohorts |
|---|---|---|
| Meatal stenosis | 5–16.3% (mean incidence across systematic reviews)[16] | Not well characterised (4–40% across individual series, Nassiri 2020)[23] |
| Misdirected urinary stream | 9.5–33% | 33–55% (AFFIRM: 68.9% reported misdirected stream)[19] |
| Voiding dysfunction | 5.6–33%[16] | 47–66%[16] |
| Urinary incontinence | 4–19.3%[16] | 23–33%[16] |
Urethroplasty aims for a downward-directed stream, with adequate urethral shortening to avoid post-void dribbling and a feminine meatal position. Counsel about misdirected urinary stream after urethroplasty. In the cross-sectional AFFIRM validation cohort, 68.9% reported this symptom.[16][19]
Labiaplasty
Labia majora are constructed from scrotal skin (or labia minora from preputial or urethral tissue) as the final step of vulvar reconstruction. Labial construction is usually performed with primary vaginoplasty or vulvoplasty; secondary labiaplasty can address residual aesthetic concerns.[12][24][48]
Preoperative Preparation
| Intervention | Detail |
|---|---|
| Scrotal / perineal electrolysis or laser hair removal | Used before PIV, beginning 6 to 12 months before surgery, to prevent intravaginal hair growth |
| Smoking cessation | Offer cessation support and document abstinence; general-surgery trials found greater benefit with at least 4 weeks of cessation than with shorter periods.[40] |
| BMI optimization | BMI was not independently associated with complications in Gaither 2018 n = 330[28] |
| Pelvic-floor physical therapy | A narrative review discusses PFPT before and after gender-affirming surgery.[27] In the FLOWER randomized trial of vaginoplasty, PFPT at 3 and 6 weeks after surgery showed no between-group differences in dilation ease, pain with dilation, vaginal length, or pelvic-floor symptoms at 12 weeks (20 PFPT, 17 controls assessed).[41] |
| Dilation counseling | Patients are counseled on the lifelong commitment. Early postoperative dilation averaged 6.6 days/week, 2.4 times/day and about 38 min/session in 17 patients (Gomez 2026 longitudinal patient-reported outcomes) |
| Estradiol and VTE planning | SOC v8 suggests surgeon and prescriber collaborate (statement 12.18). It reports no higher VTE rate when hormones were continued and stresses continued sex-steroid therapy after gonadectomy; hold decisions are individualized by VTE risk.[1] A 2026 surgeon Delphi consensus recommended perioperative enoxaparin prophylaxis but found no consensus on hormone interruption or restart timing.[38] As one center protocol, Smith, Yuan, and Garcia describe holding injectable estrogen for 2 weeks or oral estrogen for 5 days before feminizing surgery, with resumption 3 weeks after surgery.[30] |
| Self-care feasibility for full-depth vaginoplasty | Counseling covers whether the patient can sustain the dilation and douching expected after surgery, including mobility or dexterity limitations, cognitive or mental-health conditions, access to supplies, a private setting, and distance, cost or transport to experienced complication care; barriers are addressed with support planning, and shallow-depth vulvoplasty is offered when it better matches the patient's goals[31] |
Postoperative Dilation Protocol
Dilation maintains neovaginal patency after penile inversion vaginoplasty.[25]
- Observed dilation across follow-up: Gomez 2026 surveyed 27 patients at 1, 3, 6, 9 and 12 months; 17 completed every time point. Reported means were 6.6 days/week, 2.4 times/day and 38.3 min/session.[25]
- Early difficulty: all 17 patients who completed every survey time point reported at least one dilation challenge (tightness 71%, bleeding 71%, pain 65%), and prevalence declined significantly after 6 months.[25]
- Predictors of dilation difficulty (Shamamian 2025, retrospective, n = 614): unemployment OR 2.74, HIV OR 2.59, psychiatric diagnosis besides gender dysphoria OR 1.61 and primary peritoneal graft OR 3.20 (p = 0.019 for the peritoneal-graft association).[17]
- Stenosis. Difficulty with dilation can lead to partial or complete closure of the neovaginal canal.[17] Structured PFPT referral is appropriate for patients with persistent pain or difficulty.
Long-Term Urologic Surveillance
| Concern | Recommendation |
|---|---|
| Voiding dysfunction (common, underrecognized) | In the AFFIRM questionnaire-validation cohort of 102 postoperative women, reported symptoms included misdirected stream 68.9%, nocturia 51.3% and urinary frequency 29.7%; trigger urology referral when symptomatic[19] |
| Prostate screening | Prostate is left in situ during vaginoplasty and sits anterior to the neovagina. After full-depth vaginoplasty, consider a neovaginal prostate examination when indicated; after zero-depth vulvoplasty or orchiectomy alone, use an anatomy-appropriate route. Discuss prostate cancer screening by organ inventory, age, risk factors and symptoms. Estrogen therapy lowers PSA, and no validated PSA threshold exists for this population.[3][45] |
| Vaginal hygiene | Review the operating team's tissue-specific cleaning instructions and examine persistent odor or discharge before treatment. Published douching regimens vary widely in start time, frequency and solution, with no evidence-based standard; Jackson and colleagues describe soap or dilute vinegar/povidone-iodine and a 5-day empiric vaginal metronidazole course as one approach.[3][37] |
| Neovaginal bleeding | After bowel-lined vaginoplasty, evaluate new bleeding for mucosal lesions, including inflammatory bowel disease or neoplasia; biopsy suspicious lesions.[3] |
| STI screening | Standard guidelines apply; counseling adapted to neovaginal tissue type and sexual practices |
| Periodic exam | Annual or biennial pelvic examination to monitor for stenosis, granulation tissue, intravaginal hair regrowth, and prolapse |
| Urethral red flags | New urinary retention, a persistently weak stream, or bothersome misdirected urination after vaginoplasty warrants urologic assessment; meatal stenosis and voiding dysfunction are reported complications.[16] |
| Future radical prostatectomy | Laparoscopic and robotic radical prostatectomy after penile-inversion vaginoplasty have been described in case reports.[43][44] A 2021 chapter projected, on anatomical grounds, that the neovagina between the prostate and rectum may complicate posterior dissection and that a shortened, scarred or altered urethra and external sphincter could affect continence and vesicourethral-anastomotic healing. It considered retropubic robotic access anatomically feasible because the prostate and space of Retzius remain in their usual positions.[32] |
Treatment Database
| Procedure | Domain | Best for / indication |
|---|---|---|
| Bilateral Simple Orchiectomy | Gonadectomy | Stand-alone gonadectomy or bridge to vaginoplasty — preserve scrotal skin if future canal planned. |
| Vulvoplasty — Zero-Depth / Shallow-Depth | Vulvoplasty | Patients not seeking penetrative-vaginal function or wishing to avoid lifelong dilation. |
| Penile Inversion Vaginoplasty (PIV) | Vaginoplasty | Gold-standard full-depth vaginoplasty when penile/scrotal skin is adequate. |
| Skin Graft Vaginoplasty (FTSG / STSG) | Vaginoplasty | Adjunct to PIV when penile skin is insufficient for full canal depth. |
| Peritoneal Pull-Through Vaginoplasty (Robotic / Laparoscopic) | Vaginoplasty | Penoscrotal hypoplasia from puberty suppression or scrotal-skin insufficiency; depth augmentation. |
| Intestinal Vaginoplasty (Sigmoid / Ileum / Right Colon) | Vaginoplasty | Revision after failed primary PIV; provides a bowel-lined full-depth canal. |
| Penile Disassembly (Penectomy / Tissue Redistribution) | Component Procedures | Orchestrating step of feminizing vaginoplasty / vulvoplasty; tissue redistribution for neoclitoris. |
| Clitoroplasty — Preputial-Skin Flap (dorsal NVB pedicle) | Component Procedures | Sensate-neoclitoris construction with a preputial-skin flap and dorsal neurovascular pedicle when genital skin is sufficient. |
| Urethroplasty — Urethral Shortening + Feminizing Repositioning | Component Procedures | Standard urethral shortening and feminizing repositioning during vaginoplasty / vulvoplasty. |
| Labiaplasty | Component Procedures | Labia majora and minora creation concurrent with vaginoplasty / vulvoplasty; cosmetic revision. |
| Neovaginal Stenosis Management — Stepwise | Revision / Salvage | Post-vaginoplasty canal stenosis; stepwise dilation, scar lysis, then revision options. |
| Vaginoplasty Revision — Robotic Peritoneal-Flap Augmentation | Revision / Salvage | Refractory canal stenosis or depth loss after primary PIV. |
| Sigmoid Revision Vaginoplasty | Revision / Salvage | Complete canal obliteration, failed prior revision, or fistula with stenosis. |
| Rectoneovaginal Fistula Repair | Revision / Salvage | Rectoneovaginal fistula after vaginoplasty; stepwise closure with interposition flap salvage. |
| Meatal-Stenosis Revision | Revision / Salvage | Neomeatal stenosis after feminizing urethroplasty; stepwise dilation through BMG urethroplasty. |
| Granulation-Tissue Debridement | Revision / Salvage | Persistent post-vaginoplasty granulation tissue; stepwise topical to surgical management. |
See Also
- GAS Overview (Special Populations)
- Feminizing Procedures (Special Populations)
- Revision & Salvage GAS
- Pharmacology — Gender-Affirming Hormone Therapy
- Foundations — Peritoneal Flap
Podcasts
Videos
References
1. Coleman E, Radix AE, Bouman WP, et al. Standards of Care for the Health of Transgender and Gender Diverse People, Version 8 (WPATH SOC v8). Int J Transgend Health. 2022;23(Suppl 1):S1–S259. doi:10.1080/26895269.2022.2100644
2. American College of Obstetricians and Gynecologists. Health care for transgender and gender diverse individuals. Committee Opinion No. 823. 2021. (Cronin B, Stockdale CK, eds.)
3. Jackson Q, Yedlinsky NT, Gray M. Lifelong care of patients after gender-affirming surgery. Am Fam Physician. 2024;109(6):560–565. PMID 38905554
4. Jacoby A, Maliha S, Granieri MA, et al. Robotic Davydov peritoneal flap vaginoplasty for augmentation of vaginal depth in feminizing vaginoplasty. J Urol. 2019;201(6):1171–1176. doi:10.1097/JU.0000000000000107
5. Ratanalert W, Pobpan P. Full-length peritoneal flap vaginoplasty: a feasible approach for hairless neovaginal reconstruction in gender-affirming surgery. Plast Reconstr Surg. 2026;157(3):566–569. doi:10.1097/PRS.0000000000012265
6. Hembree WC, Cohen-Kettenis PT, Gooren L, et al. Endocrine treatment of gender-dysphoric / gender-incongruent persons: an Endocrine Society clinical practice guideline. J Clin Endocrinol Metab. 2017;102(11):3869–3903. doi:10.1210/jc.2017-01658
7. van der Sluis WB, Schäfer T, Nijhuis THJ, Bouman MB. Genital gender-affirming surgery for transgender women. Best Pract Res Clin Obstet Gynaecol. 2023;86:102297. doi:10.1016/j.bpobgyn.2022.102297
8. Hehemann MC, Walsh TJ. Orchiectomy as bridge or alternative to vaginoplasty. Urol Clin North Am. 2019;46(4):505–510. doi:10.1016/j.ucl.2019.07.005
9. Stelmar J, Smith SM, Lee G, Zaliznyak M, Garcia MM. Shallow-depth vaginoplasty: preoperative goals, postoperative satisfaction, and why shallow-depth vaginoplasty should be offered as a standard feminizing genital gender-affirming surgery option. J Sex Med. 2023;20(11):1333–1343. doi:10.1093/jsxmed/qdad111
10. Morrison SD, Claes K, Morris MP, et al. Principles and outcomes of gender-affirming vaginoplasty. Nat Rev Urol. 2023;20(5):308–322. doi:10.1038/s41585-022-00705-y
11. Opsomer D, Vyncke T, Mertens D, et al. Fifteen-year experience with the Ghent technique of penile inversion vaginoplasty. Plast Reconstr Surg. 2021;148(3):416e–424e. doi:10.1097/PRS.0000000000008300
12. Massie JP, Morrison SD, Van Maasdam J, Satterwhite T. Predictors of patient satisfaction and postoperative complications in penile inversion vaginoplasty. Plast Reconstr Surg. 2018;141(6):911e–921e. doi:10.1097/PRS.0000000000004427
13. Fakin RM, Giovanoli P. A single-center study comparison of two different male-to-female penile-skin inversion vaginoplasty techniques and their 3.5-year outcomes. J Sex Med. 2021;18(2):391–399. doi:10.1016/j.jsxm.2020.09.014
14. Castanon CDG, Matic S, Bizic M, et al. Laparoscopy-assisted peritoneal pull-through vaginoplasty in transgender women. Urology. 2022;166:301–302. doi:10.1016/j.urology.2022.05.001
15. Lee J, Oh C, Brucker B, Bluebond-Langner R, Zhao LC. Impact of gender-affirming vaginoplasty on lower urinary tract function: a single-center prospective cohort study. Neurourol Urodyn. 2025;44(2):311–318. doi:10.1002/nau.25649
16. Blasdel G, Dy GW, Nikolavsky D, et al. Urinary reconstruction in genital gender-affirming surgery: checking our surgical complication blind spots. Plast Reconstr Surg. 2024;153(4):792e–803e. doi:10.1097/PRS.0000000000010813
17. Shamamian PE, Chen D, Wang A, et al. Predictors of dilation difficulty in gender-affirming vaginoplasty. J Plast Reconstr Aesthet Surg. 2025;101:178–186. doi:10.1016/j.bjps.2024.11.042
18. De Rosa P, Kent M, Regan M, Purohit RS. Vaginal stenosis after gender-affirming vaginoplasty: a systematic review. Urology. 2024;186:69–74. doi:10.1016/j.urology.2024.02.005
19. Huber S, Ferrando C, Safer JD, et al. Development and validation of urological and appearance domains of the post-affirming-surgery form and function individual reporting measure (AFFIRM) for transwomen following genital surgery. J Urol. 2021;206(6):1445–1453. doi:10.1097/JU.0000000000002141
20. Saltman AJ, Dorante MI, Jonczyk MM, et al. Outcomes of orchiectomy for gender-affirming surgery: a National Surgical Quality Improvement Program study. Urology. 2023;180:98–104. doi:10.1016/j.urology.2023.07.003
21. van der Sluis WB, Steensma TD, Timmermans FW, et al. Gender-confirming vulvoplasty in transgender women in the Netherlands: incidence, motivation analysis, and surgical outcomes. J Sex Med. 2020;17(8):1566–1573. doi:10.1016/j.jsxm.2020.04.007
22. Sigurjónsson H, Möllermark C, Rinder J, Farnebo F, Lundgren TK. Long-term sensitivity and patient-reported functionality of the neoclitoris after gender reassignment surgery. J Sex Med. 2017;14(2):269–273. doi:10.1016/j.jsxm.2016.12.003
23. Nassiri N, Maas M, Basin M, Cacciamani GE, Doumanian LR. Urethral complications after gender-reassignment surgery: a systematic review. Int J Impot Res. 2020;33(8):793–800. doi:10.1038/s41443-020-0304-y
24. Sabbagh P, Richard C, Bourillon A, et al. Penile inversion vulvo-vaginoplasty with scrotal graft for trans women: surgical technique and results of initial experience. J Sex Med. 2025;22(1):156–164. doi:10.1093/jsxmed/qdae135
25. Gomez DA, Ley M, Hu AC, et al. Longitudinal patient-reported outcomes of vaginal dilation after penile inversion vaginoplasty. J Sex Med. 2026;23(4):qdag068. doi:10.1093/jsxmed/qdag068
26. Fascelli M, Peters BR, Dy GW, Dugi DD. Gender-affirming clitoroplasty and construction of the clitoro-urethral complex: an anatomy-guided selection of two techniques. Urology. 2024;183:e320–e322. doi:10.1016/j.urology.2023.10.009
27. Motiwala ZY, Misra S, Desai A, et al. Postoperative urogynecologic complications after gender-affirming surgery: a narrative review. Int Urogynecol J. 2026;37(4):805–822. doi:10.1007/s00192-025-06405-6
28. Gaither TW, Awad MA, Osterberg EC, et al. Postoperative complications following primary penile inversion vaginoplasty among 330 male-to-female transgender patients. J Urol. 2018;199(3):760–765. doi:10.1016/j.juro.2017.10.013
29. Sørensen LT. Wound healing and infection in surgery: the pathophysiological impact of smoking, smoking cessation, and nicotine replacement therapy: a systematic review. Ann Surg. 2012;255(6):1069–1079. doi:10.1097/SLA.0b013e31824f632d
30. Smith SM, Yuan N, Garcia MM. Feminizing Genital Gender-Affirming Surgery. In: Garcia M, ed. Genital Gender Affirming Surgery: An Illustrated Guide and Video Atlas. Springer; 2024:69–80.
31. Garcia MM. Decision-Making in Masculinizing Surgery and Feminizing Surgery. In: Nikolavsky D, Blakely SA, eds. Urological Care for the Transgender Patient: A Comprehensive Guide. Springer; 2021:7–21. doi:10.1007/978-3-030-18533-6_2
32. Scott K, Bratslavsky G, Ferry E. Care of Transgender Patients: Oncological Concerns. In: Nikolavsky D, Blakely SA, eds. Urological Care for the Transgender Patient: A Comprehensive Guide. Springer; 2021:194–201.
33. Mishra K, Bluebond-Langner R, Zhao LC. Male-to-Female Gender-Affirming Surgery: Vaginoplasty. In: Partin AW, Dmochowski RR, Kavoussi LR, Peters CA, eds. Campbell-Walsh-Wein Urology. 13th ed. Elsevier; 2025:2664–2676.
34. Pusica S, Stojanovic B, Bencic M, Bizic M, Atanasijevic T, Djordjevic ML. Penile microdissection: a live donor feasibility study in feminizing gender-affirming surgery. Life (Basel). 2023;13(11):2212. doi:10.3390/life13112212
35. Lava CX, Berger LE, Li KR, et al. "A comparative analysis of peritoneal flap and intestinal vaginoplasty for management of vaginal stenosis." J Plast Reconstr Aesthet Surg. 2024;98:55-63. doi:10.1016/j.bjps.2024.08.047
36. O'Dwyer C, Kumar S, Wassersug RJ, et al. "Vaginal self-lubrication following peritoneal, penile inversion, and colonic gender-affirming vaginoplasty: a physiologic, anatomic, and histologic review." Sex Med Rev. 2023;11(3):212-223. doi:10.1093/sxmrev/qead015
37. Zhou SY, Cripps C. "A scoping review of douching practices following gender-affirming vaginoplasty: toward standardized guidelines." Sex Med Rev. 2026. doi:10.1093/sxmrev/qeag011
38. Pezzoli M, Lo Re M, Pizziconi V, et al. "International Delphi consensus on feminising genital surgery in assigned-male-at-birth individuals." BJU Int. 2026. doi:10.1111/bju.70196
39. Salgado CJ, Nugent A, Kuhn J, Janette M, Bahna H. "Primary Sigmoid Vaginoplasty in Transwomen: Technique and Outcomes." Biomed Res Int. 2018;2018:4907208. doi:10.1155/2018/4907208
40. Mills E, Eyawo O, Lockhart I, Kelly S, Wu P, Ebbert JO. "Smoking cessation reduces postoperative complications: a systematic review and meta-analysis." Am J Med. 2011;124(2):144–154.e8. doi:10.1016/j.amjmed.2010.09.013
41. Ferrando CA, Mishra K, Grimstad FW, Weigand NW, Pikula C. "A randomized trial comparing perioperative pelvic floor physical therapy to current standard of care in transgender women undergoing vaginoplasty for gender affirmation: the FLOWER Trial." Int Urogynecol J. 2023;34(12):2985–2993. doi:10.1007/s00192-023-05623-0
42. Robinson IS, Blasdel G, Bluebond-Langner R, Zhao LC. "The management of intra-abdominal complications following peritoneal flap vaginoplasty." Urology. 2022;164:278–285. doi:10.1016/j.urology.2022.01.036
43. Kumar S, Tyldesley S, Poon CI, Saunders JTW, Hoag CC. "Case – laparoscopic radical prostatectomy in a transgender woman after gender-affirming vaginoplasty." Can Urol Assoc J. 2024;18(3):E98–E103. doi:10.5489/cuaj.8387
44. Blasdel G, Borah L, Navarrete R, Howland R, Kuzon WM Jr, Montgomery JS. "Prostatectomy after gender-affirming vaginoplasty for a transgender woman with prostate cancer." Urol Case Rep. 2024;56:102819. doi:10.1016/j.eucr.2024.102819
45. Hall R, Ball R, Bancroft E, Eeles R, Berner AM. "Systematic review of PSA reference intervals in the gender diverse population with prostates." BJU Int. 2025;136(4):568–577. doi:10.1111/bju.16825
46. Blasdel G, Hemal K, Dubach-Reinhold C, et al. "Gender-affirming vaginoplasty using robotic peritoneal flap method: long-term outcomes of 500 cases." Ann Surg. 2026;283(6):1068–1074. doi:10.1097/SLA.0000000000006621
47. Chao BW, Keiner C, Demzik A, Pariser JJ. "Technical considerations for neovaginal canal creation during primary and revision gender-affirming vaginoplasty." Plast Aesthet Res. 2025;12:29. doi:10.20517/2347-9264.2025.18
48. Ferchichi F, Morel-Journel N, Carnicelli D, et al. "Analysis of surgical complications and risk factors in genital feminization surgery: a retrospective cohort study of 407 transgender women." Sex Med. 2025;13(3):qfaf045. doi:10.1093/sexmed/qfaf045
49. Coleman E, Bockting W, Botzer M, et al. "Standards of Care for the Health of Transsexual, Transgender, and Gender-Nonconforming People, Version 7." Int J Transgend. 2012;13(4):165–232. doi:10.1080/15532739.2011.700873