Modified Belgrade Metoidioplasty With Urethral Lengthening
Modified Belgrade metoidioplasty releases the hormonally enlarged clitoris and extends the urethra to the neophallus tip using a combined buccal mucosa graft (BMG), anterior vaginal-wall flap, and labia minora flap. Scrotoplasty and testicular implants may be staged in the modified pathway.[1] The operation accepts a higher urethral-complication burden for the functional goal of standing micturition, which high-volume series report in most patients.[1][2][3]
For the no-UL alternative, see Simple Metoidioplasty; for the broader cohort-level decision framework, see Masculinizing Gender-Affirming Surgery.
Indications
The modified Belgrade pathway is best suited for patients who want standing micturition, accept the limits of metoidioplasty phallic size, and prefer a sensate native-tissue neophallus over phalloplasty.[1][4][12]
| Patient Priority | Fit for Modified Belgrade Metoidioplasty |
|---|---|
| Standing micturition | Strong fit; this is the main reason to add UL |
| Preserved erogenous sensation | Strong fit; native clitoral neurovascular supply is preserved |
| Avoiding phalloplasty donor-site morbidity | Strong fit |
| Penetrative intercourse | Poor fit; mean neophallus length is limited and erectile prosthesis placement is not the endpoint |
| Lowest morbidity pathway | Poor fit; no-UL metoidioplasty has much lower urethral risk |
| Future phalloplasty flexibility | Good fit; later phalloplasty remains feasible |
Contraindications and Caution Zones
Urethral lengthening drives the morbidity. In a retrospective cohort of 74 metoidioplasty patients (36 with additional urethral lengthening), Waterschoot et al. found additional urethral lengthening to be an independent predictor of all urethral complications, strictures and fistulas.[5]
| Scenario | Counseling Point |
|---|---|
| Active smoking | Counsel cessation before elective UL and discuss fistula risk; in a 74-patient retrospective metoidioplasty cohort, smoking was associated with any fistula (OR 6.54) and permanent fistula (OR 3.76).[5] |
| Standing micturition is not a priority | Prefer simple metoidioplasty or phalloplasty without UL |
| Limited labia minora / vaginal-wall tissue | May compromise flap-based urethral reconstruction; consider modified staging or alternate graft strategy |
| Retained vaginal canal planned | Counsel carefully; proximal fistula repair outcomes are worse when colpectomy is not performed before or during repair[6] |
| Penetrative intercourse is the primary goal | Phalloplasty plus delayed erectile prosthesis is usually more goal-concordant |
Historical Context
Djordjevic and colleagues reported the Belgrade experience in 2009 as a single-stage operation combining clitoral release, urethral lengthening, vaginectomy, scrotoplasty, and testicular implantation.[2] The urethral innovation was combining a BMG dorsal plate with vascularized genital flaps rather than relying on labial skin alone.[7]
The "modified Belgrade" label usually refers to center-specific adaptations of that concept. Lin-Brande et al. described a stepwise approach that preserves the Belgrade urethroplasty principle while modifying flap design, waterproofing, and scrotoplasty sequencing for their practice.[1]
Preoperative Planning
Preoperative planning should separate the decision to perform metoidioplasty from the decision to add UL. The first is a phallic-construction choice; the second is a voiding-function choice with its own risk profile.
| Planning Domain | Practical Point |
|---|---|
| Hormone history | Lin-Brande required at least 1 year of testosterone therapy to maximize clitoral growth before metoidioplasty[1][4] |
| Standing-voiding goal | Confirm that standing micturition is important enough to justify UL morbidity, distinguish voiding through a trouser fly from standing with clothing lowered, and assess presurgical clitoral length and mons adiposity. In a surgeon Delphi, 9/11 respondents agreed that fewer than 20% of patients with 2–4 cm presurgical length would void through a fly.[19] |
| Tobacco / nicotine | Stop preoperatively; risk counseling should be explicit because fistula is the dominant complication |
| Cardiometabolic factors | Review BMI, diabetes, and cardiovascular disease during preoperative risk assessment. Higher BMI was associated with complications and secondary procedures in a Norwegian retrospective metoidioplasty series.[17] A 2026 surgeon Delphi identified BMI, diabetes, and cardiovascular disease as relevant risk factors for masculinizing genital surgery.[21] |
| Vaginectomy | Decide whether to perform concurrent vaginectomy / colpectomy; vaginal remnants and proximal fistulas are recurrent management problems[3][6] |
| Buccal harvest | Counsel on oral pain, numbness, cheek tightness, and diet changes |
| Testicular implants | May be simultaneous in high-volume one-stage protocols or delayed 4-6 months depending on center practice |
Technique
The modified Belgrade operation builds the neourethra in two planes: BMG forms the dorsal urethral plate on the corporal bodies, and vascularized vaginal / labia minora tissue forms the ventral tube and waterproofing layers.[1][7]
| Step | Technical Goal |
|---|---|
| Clitoral degloving and release | Deglove the clitoris circumferentially; divide superficial suspensory and dorsal clitoral tethering to maximize ventral extension |
| Urethral-plate division | Divide the short native urethral plate tethering the meatus to the ventral glans; this creates the gap that UL must bridge |
| BMG harvest | Harvest buccal mucosa from the inner cheek and prepare it as the dorsal plate graft |
| Dorsal plate construction | Quilt BMG to the ventral corporal surface from the native urethral orifice toward the glans |
| Proximal fixed urethra | Raise anterior vaginal-wall flap to bridge the native meatus to the metoidioplasty shaft base |
| Ventral pendulous urethra | Use labia minora flap to complete the ventral neourethral tube over a catheter |
| Waterproofing | Cover suture lines with vascularized labia minora subcutaneous tissue; de-epithelialized contralateral labial tissue can overlap the urethra and shaft |
| Scrotoplasty | Rotate labia majora flaps anteriorly / superiorly; use center-specific scrotoplasty design and implant timing |
| Vaginectomy / colpectomy | Perform concurrently when indicated, especially when UL is being built and proximal fistula risk is a concern |
The reconstructive principle mirrors complex hypospadias and urethroplasty: a grafted plate plus vascularized local tissue is used in place of a long tube made only from marginal skin.
Alternative ventral flap: dorsal clitoral skin. Instead of the labia minora flap, longitudinal dorsal clitoral skin can be transposed to the ventral surface through a buttonhole maneuver and joined to the BMG margins with two lateral running sutures to form the penile neourethra, with the distal urethral plate and extensively mobilized glans wings used for the glanular urethra and terminal meatus. This is the technique compared with the BMG-plus-labia-minora-flap approach in the Djordjevic / Bizic 2013 series below.[9]
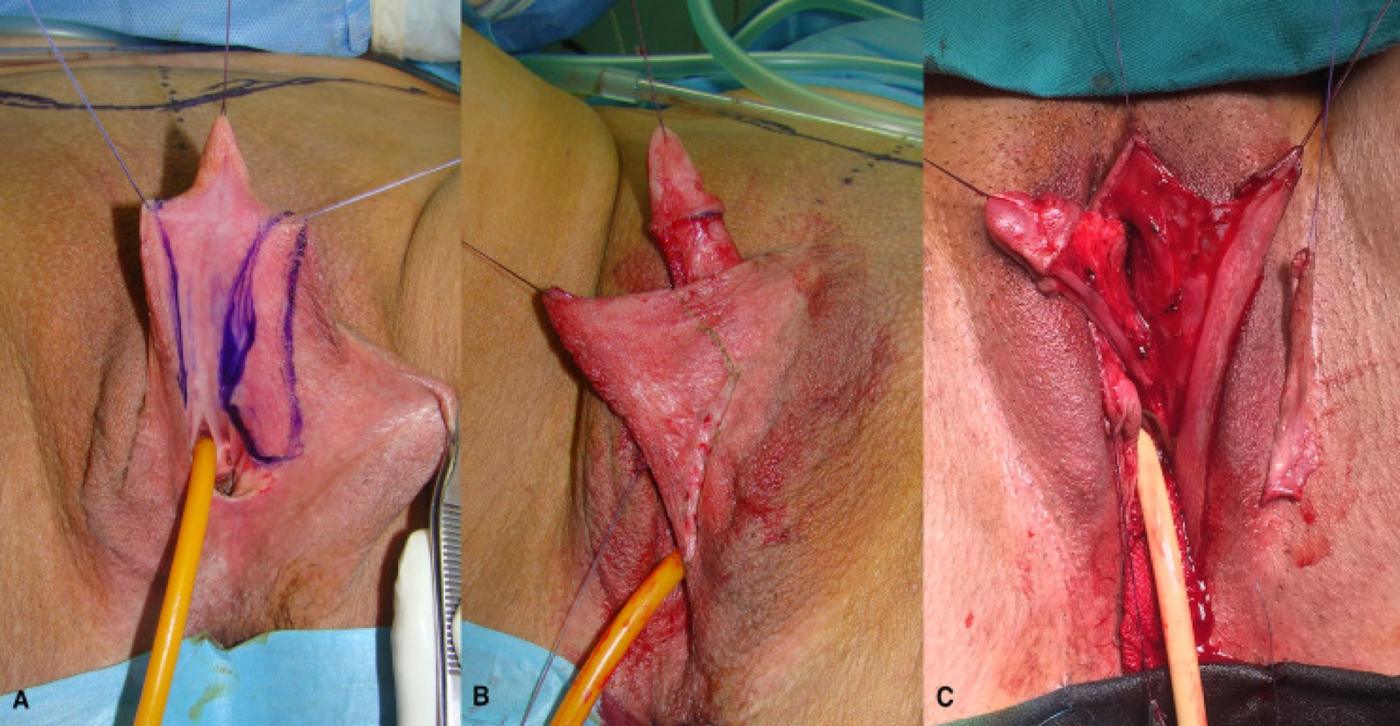
Labia minora tissue for urethral lengthening. (A) Markings of the urethral plate and the inner surface of the labia minora planned for urethral reconstruction. (B) Outer layer of the labia minora planned for skin graft harvest. (C) Labia minora flap and skin graft raised for urethral lengthening. In selected patients the Belgrade group uses this hairless labia minora skin graft in place of buccal mucosa for the dorsal plate. From Bordas N, et al. Front Endocrinol (Lausanne). 2021;12:760284, Figure 2 (CC BY).
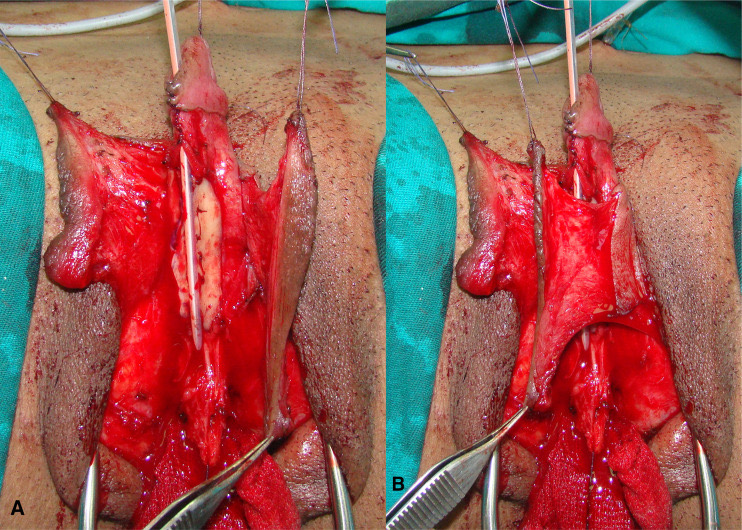
Two-plane urethral lengthening. (A) Buccal mucosa graft used as the urethral substitute (dorsal plate). (B) A left labial flap with an abundant vascular pedicle forms the anterior part of the neourethra. From Bordas N, et al. Front Endocrinol (Lausanne). 2021;12:760284, Figure 7 (CC BY).[3]
Belgrade Versus Ring Flap Metoidioplasty
Ring flap metoidioplasty is a different UL strategy that uses anteriorly based labia minora / vestibular flaps and avoids buccal harvest. It also preserves pedicle blood supply by not dividing the suspensory ligament in the same way.[8] In a retrospective ring-flap series, 11 of 69 metoidioplasty patients (16%) developed a fistula, 4 (6%) developed a stricture, and 8 (12%) required surgical urethral repair.[18]
| Feature | Modified Belgrade | Ring Flap |
|---|---|---|
| Dorsal urethral plate | Buccal mucosa graft | No BMG; labia minora / vestibular flap tissue |
| Ventral urethra | Anterior vaginal-wall flap + labia minora flap | Bilateral anteriorly based labia minora and vestibular flaps |
| Oral donor-site morbidity | Yes | No |
| Suspensory-ligament division | Typically performed | Not performed in the described ring-flap approach |
| Staging | Often one-stage | Labial-fold revision and implants may be staged |
| Main advantage | Stable BMG dorsal plate | Avoids buccal harvest and preserves flap blood supply |
| Main tradeoff | Oral morbidity and graft dependence | Pedicle and flap-design constraints |
Postoperative Care
One described postoperative pathway after metoidioplasty with urethral lengthening uses suprapubic drainage and a 10–12 Fr neourethral stent, with saline irrigation through the stent to keep the buccal graft moist during the first 72 hours, broad-spectrum antibiotics and an anticholinergic while the catheter remains, stent removal at 10 days followed by daily 5 mL saline irrigation, voiding beginning at 3 weeks, and suprapubic-tube removal the following day, alongside at least 6 months of vacuum-pump use with a PDE5 inhibitor to prevent retraction.[16]
Outcomes
High-volume Belgrade series report short hospital stays, mean neophallus length around 5.6 cm, preserved erogenous sensation, and standing micturition in most patients.[2][3][13] Lin-Brande et al. reported a median operative time of 408 minutes in 21 patients undergoing their modified approach.[1]
| Series / Technique | N | Key Outcomes |
|---|---|---|
| Djordjevic 2009 single-stage Belgrade | 82 | Standing voiding in all patients at median follow-up of 32 months; mean neophallic length 5.7 cm; preserved sensation; 2 strictures and 7 fistulas required minor revision[2] |
| Djordjevic 2009 BMG + labia minora flap | 38 | Standing voiding in all 38 at median follow-up of 22 months; 2 fistulas and 1 urethral erosion from a testicular implant required revision[7] |
| Djordjevic / Bizic 2013 comparison | 207/298 operated patients (69.5%) who agreed to participate and attended regular follow-up | BMG + labia minora flap (n = 158) versus BMG + dorsal clitoral skin flap (n = 49): standing voiding 93% versus 87.8% and fistula 5.7% versus 14.3% (p < 0.05); non-randomized[9] |
| Bordas / Djordjevic 2021 (five urethroplasty variants) | 813 | Mean follow-up 94 months (range 16–180); mean neophallus 5.6 cm measured 3–6 months postoperatively; urethral fistula 8.9%; stricture 1.7%; vaginal remnant 9.6%; testicular implant rejection 2% across the mixed cohort[3] |
| Lin-Brande 2021 modified Belgrade | 21 | Median operative time 408 minutes, EBL 400 mL, LOS 3 days; complications in 10 (48%), 7 of them Clavien I-II; 2 (9.5%) required revision urethroplasty; no fistulae at a median follow-up of 5.5 months[1] |
| Waterschoot 2021 metoidioplasty cohort (predominantly preputial-island AUL, not BMG Belgrade) | 74 (36 with AUL) | Median follow-up 44 months; any urethral complication in 42/74 (56.8%) across the full cohort. AUL predicted all urethral complications (OR 15.5), stricture (OR 24.5), fistula (OR 6.07), and permanent fistula (OR 3.83)[5] |
| Veerman 2020 UL functional cohort | 63 (8 metoidioplasty, 55 phalloplasty) | Mean follow-up 23 months; strictures in 5 of 8 and fistulas in 4 of 8 metoidioplasty patients; 73% of the whole cohort needed revision; 70% voided from the tip of the phallus after treatment[14] |
The four Belgrade reports in this table have overlapping enrollment periods.[2][3][7][9] Standing micturition is the defining functional endpoint. In a Norwegian retrospective series of modified Hage metoidioplasty, all 84 patients underwent urethral lengthening with only partial vaginal-lining removal. Stricture occurred in 19/84 (22.6%) and fistula in 11/84 (13.1%); the technique and retained vaginal canal limit direct comparison with modified Belgrade reconstruction.[17] The high-volume Belgrade series reported standing voiding in most patients.[3] In a separate Norwegian cohort, 41 of 84 patients (48.8%) required at least one secondary procedure, including urethral, testicular-implant, and cosmetic procedures; discuss the possibility of further surgery during counseling without treating this as a modified-Belgrade-specific rate.[17]
Complications
Urethral Fistula
Fistula is usually the dominant complication after metoidioplasty with UL. De Rooij et al. reported that fistula repair outcomes depend on fistula size and location: small pendulous-urethral fistulas had higher recurrence-free rates than large proximal-anastomotic fistulas. In the proximal subgroup, repair succeeded in 7/11 patients (64%) with colpectomy before or during repair versus 2/13 (15%) without it (p = 0.03); the overall comparison was 22/33 (67%) versus 15/31 (48%) and was not statistically significant (p = 0.14).[6] The bulbar neourethra-to-native-urethra anastomosis has been identified as a particular weak point because of the higher pressure of the urinary stream at that level; joining the clitoral bulbs over the neourethra and adding vascularized surrounding tissue at this junction has been described as a fistula-prevention maneuver, though comparative evidence that it lowers fistula rates has not been reported.[16]
| Fistula Scenario | Management Principle |
|---|---|
| Small pendulous fistula | Delay until tissue inflammation settles; multilayer closure with vascularized interposition |
| Large proximal fistula | Evaluate retained vaginal cavity / remnant; consider colpectomy before or during repair |
| Persistent or recurrent fistula | Reconstruct as a failed-UL urethroplasty problem rather than repeating simple skin closure |
| Active infection / wound breakdown | Drain, divert, and delay definitive repair |
Urethral Stricture
Endoscopic dilation or DVIU performs poorly for many post-UL strictures. In de Rooij 2022, the 3-year recurrence-free rate for strictures was 43% after endoscopic treatment and 82% after open treatment.[6] In a review of urethroplasty after gender-affirming urethral lengthening, 76% of patients had undergone phalloplasty and 24% metoidioplasty.[15] Staged repair had reported recurrence of 0–25%, particularly for long pendulous strictures; recurrence approached 50% in some one-stage series, especially without augmentation, and failures were also reported with buccal mucosa grafts.[15]
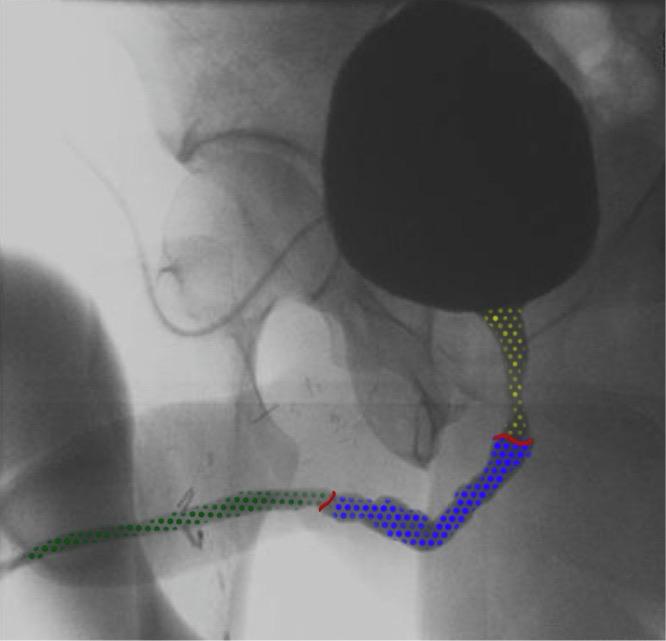
Urethral anatomy after urethral lengthening. Green dots mark the pars pendulans urethra, blue dots the pars fixa urethra and yellow dots the native urethra; red lines mark the proximal and distal urethral anastomoses. From Neuville P, et al. Int J Impot Res. 2026;38(4):302-310, Fig. 2 (CC BY).[15]
| Stricture Scenario | Preferred Direction |
|---|---|
| Short isolated anastomotic stricture | Excision and primary anastomosis may be appropriate in selected cases |
| Long pendulous / phallic stricture | Staged urethroplasty had the lowest recurrence range (0-25%) in the systematic review[15] |
| Recurrent after dilation / DVIU | Assess location, length, and healing interval. The 2026 EAU guideline strongly recommends avoiding incision or urethroplasty within six months after neophalloplasty and avoiding more than two endoscopic incisions except for palliation; it weakly recommends staged urethroplasty when a neophallic-urethral stricture needs open repair.[20] |
| Associated fistula / vaginal remnant | Treat the entire failed-UL unit |
Non-Urethral Complications
Other complications include wound separation, vaginal remnant, testicular implant rejection or displacement, oral donor-site morbidity, and dissatisfaction with phallic size for penetrative function.[3][10]
Emerging Modifications
Nakamura et al. described vaginal-mucosal graft metoidioplasty, using mucosa harvested during vaginectomy to replace buccal mucosa for urethral reconstruction. The attraction is that the graft source is already being removed, which avoids oral morbidity. In seven combined hysterectomy, oophorectomy, vaginal-closure and metoidioplasty operations, median blood loss was 1,610 mL; the authors attributed this to vaginal-flap elevation and circumferential graft harvest. At a median five-month follow-up, one fistula required closure and one mild stricture remained under observation. This remains an emerging alternative to BMG-based reconstruction.[11]
Operative Pearls
- Preserve vascularized labia minora tissue for both ventral urethral construction and waterproofing.
- Do not over-tubularize tight tissue over a large catheter; ischemia and tension are fistula invitations.
- If a vaginal remnant is present, look for it before repairing proximal fistula.
- Counsel on standing voiding separately from stream quality; spraying and dribbling may persist even when the patient can void standing.
- Keep phalloplasty conversion feasible by minimizing avoidable donor-site and perineal scarring.
References
1. Lin-Brande M, Clennon E, Sajadi KP, et al. Metoidioplasty with urethral lengthening: a stepwise approach. Urology. 2021;147:319-322. doi:10.1016/j.urology.2020.09.013
2. Djordjevic ML, Stanojevic D, Bizic M, et al. Metoidioplasty as a single stage sex reassignment surgery in female transsexuals: Belgrade experience. J Sex Med. 2009;6(5):1306-1313. doi:10.1111/j.1743-6109.2008.01065.x
3. Bordas N, Stojanovic B, Bizic M, Szanto A, Djordjevic ML. Metoidioplasty: surgical options and outcomes in 813 cases. Front Endocrinol. 2021;12:760284. doi:10.3389/fendo.2021.760284
4. Kocjancic E, Acar O, Talamini S, Schechter L. Masculinizing genital gender-affirming surgery: metoidioplasty and urethral lengthening. Int J Impot Res. 2022;34(2):120-127. doi:10.1038/s41443-020-0259-z
5. Waterschoot M, Hoebeke P, Verla W, et al. Urethral complications after metoidioplasty for genital gender affirming surgery. J Sex Med. 2021;18(7):1271-1279. doi:10.1016/j.jsxm.2020.06.023
6. de Rooij FPW, Falcone M, Waterschoot M, et al. Surgical outcomes after treatment of urethral complications following metoidioplasty in transgender men. J Sex Med. 2022;19(2):377-384. doi:10.1016/j.jsxm.2021.12.006
7. Djordjevic ML, Bizic M, Stanojevic D, et al. Urethral lengthening in metoidioplasty (female-to-male sex reassignment surgery) by combined buccal mucosa graft and labia minora flap. Urology. 2009;74(2):349-353. doi:10.1016/j.urology.2009.02.036
8. Demzik A, Snyder L, Hayon S, Chen M, Figler BD. Ring flap metoidioplasty. Urology. 2021;158:243. doi:10.1016/j.urology.2021.09.014
9. Djordjevic ML, Bizic MR. Comparison of two different methods for urethral lengthening in female to male (metoidioplasty) surgery. J Sex Med. 2013;10(5):1431-1438. doi:10.1111/jsm.12108
10. de Rooij FPW, van de Grift TC, Veerman H, et al. Patient-reported outcomes after genital gender-affirming surgery with versus without urethral lengthening in transgender men. J Sex Med. 2021;18(5):974-981. doi:10.1016/j.jsxm.2021.03.002
11. Nakamura K, Sakurai T, Sakamoto A, Watanabe K, Ogawa R. Vaginal-mucosal graft metoidioplasty: a novel surgical technique for urethral reconstruction in transmasculine surgery. J Sex Med. 2025;22(7):1275-1279. doi:10.1093/jsxmed/qdaf125
12. Bizic M, Stojanovic B, Bencic M, Bordas N, Djordjevic M. Overview on metoidioplasty: variants of the technique. Int J Impot Res. 2021;33(7):762-770. doi:10.1038/s41443-020-00346-y
13. Stojanovic B, Djordjevic ML. Updates on metoidioplasty. Neurourol Urodyn. 2023;42(5):956-962. doi:10.1002/nau.25102
14. Veerman H, de Rooij FPW, Al-Tamimi M, et al. Functional outcomes and urological complications after genital gender-affirming surgery with urethral lengthening in transgender men. J Urol. 2020;204(1):104-109. doi:10.1097/JU.0000000000000795
15. Neuville P, Madec FX, Vetterlein MW, et al. Systematic review of the outcomes of urethroplasty following urethral lengthening in transgender men. Int J Impot Res. 2026;38(4):302-310. doi:10.1038/s41443-025-01132-4
16. Stojanovic B, Bizic M, Djordjevic M. Surgical Anatomy — Metoidioplasty. In: Nikolavsky D, Blakely SA, eds. Urological Care for the Transgender Patient: A Comprehensive Guide. Springer; 2021:115–126.
17. Sundhagen HP, Wæhre A, Tønseth KA. "Metoidioplasty in Norway: A 13-year Experience from a National Center." Plast Reconstr Surg Glob Open. 2024;12(11):e6307. doi:10.1097/GOX.0000000000006307
18. Sun HH, Gupta S, Chen ML. "Urethral outcomes of the labia minora ring flap for metoidioplasty and phalloplasty." Urology. 2024;188:156-161. doi:10.1016/j.urology.2024.03.028
19. Blasdel G, Chen ML, Berli J, et al. "Outcomes Following Metoidioplasty and Phalloplasty Gender Affirming Surgery With Urethral Lengthening: A Modified Delphi Consensus Study." Urology. 2025;206:196-203. doi:10.1016/j.urology.2025.07.071
20. European Association of Urology. "EAU Guidelines on Urethral Strictures: Disease Management in Transgender Patients." 2026. Guideline.
21. Lo Re M, Pezzoli M, Cocci A, et al. "Urological issues in masculinising genital surgery: a Delphi consensus study." BJU Int. 2026 Aug 20. Epub ahead of print. doi:10.1111/bju.70428