Simple Metoidioplasty Without Urethral Lengthening
Simple metoidioplasty creates a sensate neophallus from the hormonally enlarged clitoris without extending the urethra into the phallus.[9] Without urethral lengthening (UL), reliable standing micturition is generally not achieved, although Morrison's extended no-UL technique may permit an anterior-directed stream while standing in some patients.[12] In a mixed no-UL series, urologic complications occurred in 8/68 (12%); a retrospective metoidioplasty series associated UL with more urethral complications.[1][2]
This is the atlas page for the no-UL metoidioplasty pathway. For the broader cohort-level decision framework, see Masculinizing Gender-Affirming Surgery; for the clinical overview of masculinizing procedures, see Masculinizing Procedures.
Indications
Simple metoidioplasty is best suited for patients who prioritize erogenous sensation, lower morbidity, and preservation of future phalloplasty options over standing micturition or penetrative rigidity.[1][3]
| Patient Priority | Fit for Simple Metoidioplasty |
|---|---|
| Preserved erogenous sensation | Good fit; native clitoral neurovascular supply is preserved |
| Lower urethral morbidity | Good fit; UL is omitted |
| Standing micturition | Poor fit; native meatus remains proximal / perineal |
| Penetrative intercourse | Usually a poor fit. In a 2026 review of 23 metoidioplasty papers spanning surgical techniques, 10 of the 11 studies assessing penetrative capacity reported that 0–24% of respondents could penetrate; one study reported 70%. No-UL-specific estimates remain uncertain.[13] |
| Future flexibility | Good fit; subsequent phalloplasty remains feasible |
| Desire to avoid staged urethral reconstruction | Good fit |
The choice follows the patient's goals.
Contraindications and Caution Zones
Counseling should align the planned procedure with the patient's goals, including whether standing micturition requires urethral lengthening. Patients who strongly prioritize standing micturition need a UL pathway, with counseling about the associated fistula and stricture risk.[2][4]
| Scenario | Counseling Point |
|---|---|
| Standing micturition is a primary goal | Simple metoidioplasty does not move the meatus to the neophallus tip |
| Penetrative intercourse is a primary goal | Phalloplasty plus delayed erectile prosthesis is the more goal-concordant pathway |
| Limited clitoral hypertrophy after testosterone | Neophallus length is limited by clitoral growth; in a 16-patient mixed-technique series (7 simple releases, 9 with UL), preoperative stretched clitoral length correlated with exposed length measured immediately after surgery. Testosterone duration beyond at least one year was not significantly correlated with length, and healed dimensions were not measured.[14] |
| Active smoking | Counsel cessation, especially if staged UL is being considered later; in one retrospective series, smoking predicted fistula formation after metoidioplasty (OR 6.54)[2] |
| Retained vaginal canal | Continue anatomy-based pelvic and STI screening. After receptive vaginal sex following metoidioplasty without vaginectomy, use clinician- or patient-collected vaginal swabs for STI testing; when the cervix is retained, urine specimens are inadequate to detect cervical infection. Counsel on postvoid dribbling, infections, and pelvic symptoms.[5] |
Preoperative Planning
Preoperative work covers goals, clitoral growth on testosterone, fertility plans, and timing of adjacent procedures. Discuss fertility preservation before hysterectomy or BSO, and contraception when pregnancy is possible; testosterone is not contraception.[7] WPATH SOC8 sets the readiness criteria for genital gender-affirming surgery. ACOG and the American Family Physician review emphasize ongoing anatomy-based preventive care after surgery.[6][7][5]
| Planning Domain | Practical Point |
|---|---|
| Hormone history | Record testosterone use and clitoral response. Lin-Brande's 33-patient institutional series required at least one year of testosterone; SOC8 Statement 13.6 suggests stability on the current regimen, which may include six months or longer if needed for the desired result, unless hormones are not desired or are contraindicated.[9][6] |
| Voiding goal | Confirm that voiding from the native proximal meatus is acceptable |
| Adjunct procedures | Vaginectomy, scrotoplasty, hysterectomy / BSO, mons reduction, and testicular implants may be staged or combined depending on anatomy and center practice |
| Future phalloplasty | Document that no-UL metoidioplasty does not preclude later phalloplasty; it can be a first-stage endpoint or a final operation[3] |
| Tobacco / nicotine | Stop before genital reconstruction[2] |
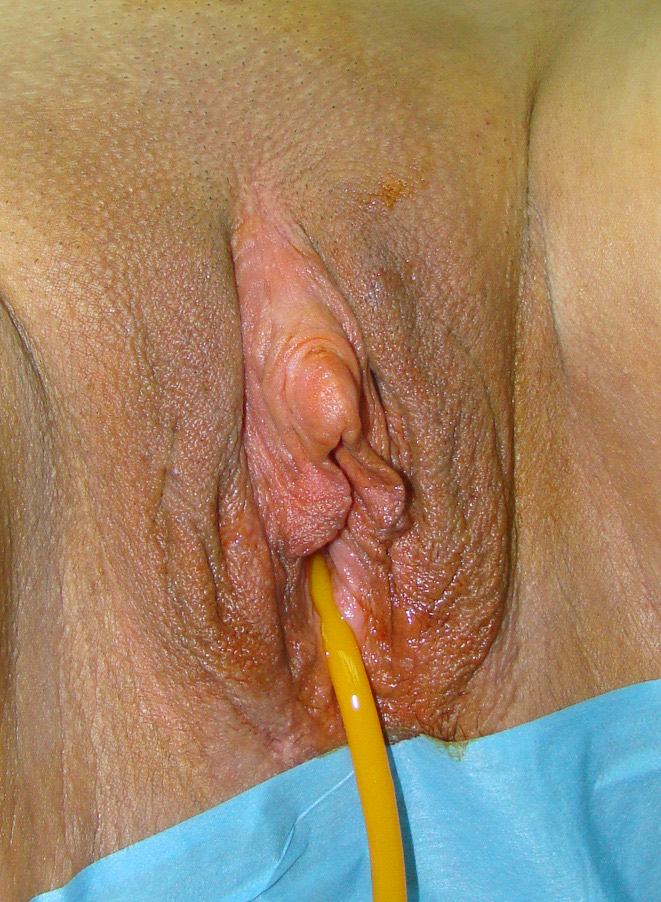
Preoperative appearance after topical testosterone, showing the hypertrophied clitoris that metoidioplasty releases and straightens. The catheter marks the native urethral meatus, which stays in place when the urethra is not lengthened. From Bordas N, et al. Front Endocrinol (Lausanne). 2021;12:760284, Figure 1 (CC BY).[3]
Technique
Simple metoidioplasty releases and straightens the hormonally enlarged clitoris and covers the shaft with local genital skin without constructing a phallic urethra.[4][8][9] Meatal management varies: Morrison's extended no-UL technique with scrotoplasty slightly mobilizes the native urethra and creates a perineal urethrostomy.[12]
| Step | Technical Goal |
|---|---|
| Exposure and marking | Mark clitoral hood, labia minora flaps, labia majora scrotoplasty flaps if planned, and any mons / vaginectomy incisions |
| Clitoral degloving | Deglove the clitoris to expose tethering structures and maximize shaft mobility |
| Suspensory-ligament release | Divide superficial suspensory attachments to improve apparent length and projection |
| Ventral chordee correction | Release ventral tethering to straighten the neophallus without compromising neurovascular supply |
| Shaft skin coverage | Use labia minora / local genital flaps to cover the ventral and lateral shaft |
| Native urethra preserved | Do not construct a pars fixa or phallic urethra; the native meatus may remain proximal, or be mobilized behind the scrotum for a perineal urethrostomy in an extended no-UL technique.[12] |
| Adjunct reconstruction | Perform scrotoplasty, vaginectomy, hysterectomy / BSO, or mons work if included in the stage |
Because the urethra is not lengthened, the operation avoids the pars fixa and phallic urethral anastomoses that account for most fistula and stricture morbidity in metoidioplasty with UL.
Outcomes
Pigot et al. reported 68 patients after genital gender-affirming surgery without UL: 35 had metoidioplasty and 33 had phalloplasty. At a median 24 months (range 6–129), 9/68 (13%) had surgical complications and 8/68 (12%) had urologic complications. The published aggregate does not provide simple-metoidioplasty-specific rates for these endpoints.[1]
| Outcome | Mixed no-UL cohort result (35 metoidioplasty; 33 phalloplasty) |
|---|---|
| Cohort size | 68 patients |
| Median follow-up | 24 months |
| Surgical complications | 9/68 (13%) |
| Urologic complications | 8/68 (12%) |
| Storage symptoms | No significant postoperative change |
| Voiding symptoms | No significant postoperative change |
| Urinary-symptom quality of life | Median score in the "pleased" range |
Urinary-function measures came from subsets of the 68-patient cohort: 44/68 completed uroflowmetry/IPSS assessments and 13/68 completed frequency-voiding charts; available denominators varied by measure and time point.[1]
In the Pigot cohort, urinary morbidity was low, and standing voiding was not the endpoint. The patient-reported questionnaire was self-constructed and not validated. Among 40 respondents (71% of the 56 approached), 80% reported increased self-esteem, 80% would undergo surgery again, and 70% would recommend the operation to others.[1]
| Satisfaction Domain | Result |
|---|---|
| Sexual functioning satisfactory / very satisfactory | 45% |
| Voiding satisfactory / very satisfactory | 53% |
| Penis appearance satisfactory / very satisfactory | 63% |
| Neoscrotum appearance satisfactory / very satisfactory | 65% |
| Increased self-esteem | 80% |
| Would undergo surgery again | 80% |
| Would recommend to others | 70% |
No-UL Versus UL Metoidioplasty
UL changes the reconstructive target from a sensate released clitoris to a voiding neophallus, and it carries the urethral risk. In a retrospective series of 74 metoidioplasties, additional urethral lengthening (48.6% of patients) was an independent risk factor for urethral complications, with odds ratios of 15.5 for any urethral complication, 24.5 for stricture, and 6.07 for fistula. Urethral complications of any kind occurred in 56.8% overall.[2]
| Domain | Without UL | With UL |
|---|---|---|
| Voiding endpoint | Native proximal / perineal meatus | Neomeatus at or near neophallus tip |
| Standing micturition | Generally not possible | Usually the goal and often achievable |
| Urethral complication exposure | Low | Substantially higher |
| Stricture risk | Avoids new pars fixa / phallic urethra | Driven by reconstructed urethral segments |
| Reoperation burden | Lower | Higher |
| Sensation | Preserves native clitoral sensation | Also preserves clitoral sensation, but with added urethral reconstruction |
In a cross-sectional survey of 102 transgender men (74 phalloplasty, 28 metoidioplasty), de Rooij et al. found a lower mean number of reported complications without UL (1 versus 2.7) and reoperations (0.4 versus 1.6), with no significant difference in patient-reported satisfaction. UL was performed in 51/74 phalloplasty patients and 5/28 metoidioplasty patients. Satisfaction with neophallus appearance and voiding were positive predictors of overall satisfaction.[10]
Postoperative Care and Follow-Up
Early care includes wound care and edema control. Catheter and drain plans depend on the no-UL technique and any adjunct procedures; a Foley catheter is used in Morrison's extended no-UL approach.[12] Patients are monitored for hematoma, wound separation, urinary retention, postvoid dribbling, infection and pelvic pain. Because no neourethra is constructed, evaluation of urinary symptoms should consider the native urethra, any urogenital or perineal opening, a retained vaginal cavity, pelvic-floor dysfunction, and prior lower-tract disease.[5] In Pigot's mixed no-UL cohort, skin-lined opening stenosis occurred in 8/68 (12%) and could obstruct voiding; no urethral fistula or stricture occurred.[1]
SOC8 Statement 13.9 suggests lifelong urologic follow-up after metoidioplasty.[6] Patients who retain vaginal anatomy also need anatomy-based preventive care, including STI screening when indicated.[5] Patients who later request standing micturition or penetrative function can discuss staged UL or phalloplasty.[5] A Belgrade one-stage metoidioplasty series that included urethral reconstruction reported that 12.5% of 938 patients later requested phalloplasty.[11]
Operative Pearls
- The operation is defined by its endpoint: sensate phallic release without urethral reconstruction.
- Confirm preoperatively that the patient understands voiding will remain proximal / perineal.
- Preserve the clitoral neurovascular bundle; sensation is the main functional advantage.
- Chordee correction can improve projection. Counsel on likely size using the patient's preoperative anatomy and planned release; Bordas's one-stage cohort with urethroplasty reported mean neophallus length 5.6 cm (range 4.8–10.2 cm), measured 3–6 months after surgery.[3]
- Keep future phalloplasty feasible by minimizing avoidable scarring in flap-planning territories.
- If scrotoplasty is performed, counsel separately on implant timing and staged prosthesis risk.
References
1. Pigot GLS, Al-Tamimi M, Nieuwenhuijzen JA, et al. Genital gender-affirming surgery without urethral lengthening in transgender men-a clinical follow-up study on the surgical and urological outcomes and patient satisfaction. J Sex Med. 2020;17(12):2478-2487. doi:10.1016/j.jsxm.2020.08.004
2. Waterschoot M, Hoebeke P, Verla W, et al. Urethral complications after metoidioplasty for genital gender affirming surgery. J Sex Med. 2021;18(7):1271-1279. doi:10.1016/j.jsxm.2020.06.023
3. Bordas N, Stojanovic B, Bizic M, Szanto A, Djordjevic ML. Metoidioplasty: surgical options and outcomes in 813 cases. Front Endocrinol. 2021;12:760284. doi:10.3389/fendo.2021.760284
4. Kocjancic E, Acar O, Talamini S, Schechter L. Masculinizing genital gender-affirming surgery: metoidioplasty and urethral lengthening. Int J Impot Res. 2022;34(2):120-127. doi:10.1038/s41443-020-0259-z
5. Jackson Q, Yedlinsky NT, Gray M. Lifelong care of patients after gender-affirming surgery. Am Fam Physician. 2024;109(6):560-565. PMID 38905554
6. Coleman E, Radix AE, Bouman WP, et al. Standards of care for the health of transgender and gender diverse people, version 8. Int J Transgend Health. 2022;23(Suppl 1):S1-S259. doi:10.1080/26895269.2022.2100644
7. American College of Obstetricians and Gynecologists. Health care for transgender and gender diverse individuals: ACOG Committee Opinion, Number 823. Obstet Gynecol. 2021;137(3):e75-e88. doi:10.1097/AOG.0000000000004294
8. Berli JU, Knudson G, Fraser L, et al. What surgeons need to know about gender confirmation surgery when providing care for transgender individuals: a review. JAMA Surg. 2017;152(4):394-400. doi:10.1001/jamasurg.2016.5549
9. Lin-Brande M, Clennon E, Sajadi KP, et al. Metoidioplasty with urethral lengthening: a stepwise approach. Urology. 2021;147:319-322. doi:10.1016/j.urology.2020.09.013
10. de Rooij FPW, van de Grift TC, Veerman H, et al. Patient-reported outcomes after genital gender-affirming surgery with versus without urethral lengthening in transgender men. J Sex Med. 2021;18(5):974-981. doi:10.1016/j.jsxm.2021.03.002
11. Stojanovic B, Djordjevic ML. Updates on metoidioplasty. Neurourol Urodyn. 2023;42(5):956-962. doi:10.1002/nau.25102
12. Morrison SD, Morris MP, Mokken SE, Buncamper ME, Özer M. "Technical refinements to extended metoidioplasty without urethral lengthening: surgical technique." Plast Reconstr Surg Glob Open. 2022;10(2):e4101. doi:10.1097/GOX.0000000000004101
13. Goldstein B, Uloko M, Okamuro K, et al. "Sexual health outcomes following gender affirming metoidioplasty: a systematic review." Sex Med Rev. 2026;14(1):qeaf060. doi:10.1093/sxmrev/qeaf060
14. Glick H, Tang M, Daignault-Newton S, Hadj-Moussa M. "Assessment of neophallus length following metoidioplasty." Transl Androl Urol. 2023;12(9):1390-1396. doi:10.21037/tau-23-155