Female Cosmetic Genital Surgery (FGCS)
Female genital cosmetic surgery (FGCS) is the elective, aesthetic end of female genital surgery. It includes labiaplasty, clitoral hoodoplasty, labia majora augmentation, monsplasty, surgical vaginoplasty or energy-based devices, hymenoplasty, and regenerative and fat-grafting techniques. Reconstructive operations for trauma, oncologic resection, lichen sclerosus, FGM/C, or congenital anomaly live at 04e Genital Reconstruction; gender-affirming pathway surgery lives at 04k Gender-Affirming Surgery.
Society positions and evidence-quality caveat. The ACOG 2020 Committee Opinion states that procedures to alter sexual appearance or function, other than those done for clinical indications, are not medically indicated, pose substantial risk, and have not had their safety and effectiveness established. The FIGO 2025 Statement holds that it is ethically inappropriate for obstetrician-gynecologists to recommend, perform or refer patients for cosmetic genital procedures in women without structural or functional abnormalities.[1][4] The FDA 2018 safety communication warned against energy-based devices for "vaginal rejuvenation" and cosmetic indications; no such device is FDA-cleared for these uses.[2] Assess psychological concerns during consultation; assess for body dysmorphic disorder (BDD) when indicated, and refer patients with suspected psychological concerns for mental-health evaluation before considering surgery.[1]
Decision Framework
Professional societies advise caution about these procedures (see the box above). The outcome literature reports high satisfaction, but it consists mainly of retrospective series and meta-analyses of them.
- Labiaplasty meta-analyses. Pooled satisfaction was 99% (95% CI 97–99%) in Escandón 2022 (46 studies, 3,804 patients)[5] and 94% (95% CI 93–95%) in Géczi 2024 (53 studies)[6]. Pooled dehiscence was 5.9% in Géczi 2024.[5][6] A 2025 review of nine labiaplasty studies with follow-up of at least one year (748 patients) reported revision in 42/748 (5.6%) and asymmetry in 45/748 (6.0%); these are descriptive counts from heterogeneous reports.[34]
- Symptoms. In a prospective series of 62 patients (82% trim, 18% wedge), the mean number of symptoms fell from 6.5 of 11 to 0.23, and 93.5% were symptom-free at a mean of 13.3 months (Sorice-Virk 2020).[7]
- Psychological outcomes. In a prospective controlled study (29 labiaplasty patients, 22 controls), genital appearance dissatisfaction fell, but general psychological well-being did not change. Higher preoperative psychological distress was associated with lower satisfaction (p = 0.001) (Sharp 2016).[8]
- Mixed genital procedures. A retrospective multicenter study of 258 women (341 procedures, including vaginoplasty and perineoplasty) reported 91.6% satisfaction at 6–42 months (Goodman 2010).[9]
- Clitoral hood. In a series of 789 patients treated by a zone-based classification, satisfaction at six months was 95.7%, complications 4.3% and revision 1.9% (Liu 2022).[10]
- Vaginal laxity. Pereira 2024 found sexual-function improvement in observational studies but not its included randomized trials.[11] A 2026 review found short-term, low-certainty improvement in study-defined laxity response and a modest FSFI gain with radiofrequency versus sham; its only direct comparison favored pelvic floor muscle training over radiofrequency at six months. The review authors advise pelvic floor muscle training first; durable device benefit and efficacy for GSM remain unestablished.[27]
Mandatory Pre-Procedural Assessment
| Assessment | Action |
|---|---|
| Counseling on normal anatomic variation | Begin with reassurance that vulvar size, shape, and color vary widely and change with puberty, aging, childbirth, and menopause.[1] For patients younger than 18 years, consider labiaplasty only for significant congenital malformation or persistent symptoms directly attributable to labial anatomy.[28] |
| Distinguish functional vs purely cosmetic indication | Document specific symptoms (chafing, tugging, pain with exercise / intercourse, hygiene). In a retrospective series of 414 women, 52.4% reported functional impairment, 20.3% aesthetic concerns and 27.3% both.[12] In Sorice-Virk 2020 (n = 62), patients averaged 6.5 of 11 symptoms preoperatively.[7] |
| BDD screening | Assess for BDD when indicated; refer patients with suspected psychological concerns for mental-health evaluation before considering surgery.[1] BDDQ-AS was validated for screening in aesthetic rhinoplasty; BDD-YBOCS assesses severity of current BDD.[24][25] BDD affects about 2.5% of US adults.[3] A systematic review estimated higher prevalence in general cosmetic-surgery settings than in community adults.[26] |
| Psychological-distress assessment | Higher preoperative distress was associated with lower postoperative satisfaction (Sharp 2016, n = 29, p = 0.001).[8] |
| Vaginal laxity / tightening assessment | Before vaginoplasty or perineoplasty, obtain obstetric and pelvic-floor history and evaluate for prolapse, obstructed defecation, and urinary or anal incontinence; refer symptomatic pelvic-floor disease for specialist assessment.[35] |
| Informed consent | For surgery without a clinical indication, explain ACOG's position that safety and effectiveness are unestablished and FIGO's position that it is ethically inappropriate for obstetrician-gynecologists to recommend, perform, or refer for cosmetic genital surgery without structural or functional abnormality. Discuss potential complications (pain, bleeding, infection, scarring, adhesions, altered sensation, dyspareunia, reoperation) and the lack of high-quality effectiveness data for most procedures.[1][4] Explore partner expectations or pressure and confirm that the patient's goals are voluntary.[36] |
Identify the Clinical Goal
| Patient Concern | Primary Procedure Category | Evidence Level |
|---|---|---|
| Labia minora protrusion (functional ± aesthetic) | Labiaplasty (trim, wedge or de-epithelialization) | Low overall (mainly observational series); a randomized 48-patient trim-versus-wedge trial detected no statistically significant between-technique difference in genital self-image or BDD symptom scores, or association between complications and technique, at six months.[1][5][6][37] |
| Clitoral-hood redundancy | Clitoral hoodoplasty (usually combined with labiaplasty) | Low (Level IV classification-based case series; comparative validation lacking)[10] |
| Labia majora atrophy / deflation | Fat grafting or HA filler (see Labia Majora Augmentation) | Fat: case series; HA: one single-center randomized trial versus no intervention in women aged 40–65 with hypotrophy (n = 76; six-month outcomes); evidence preliminary.[31] In the US, labia-majora HA filler use is outside FDA-approved dermal-filler sites; disclose unknown site-specific risks and the general risk of intravascular injection and tissue necrosis.[33] |
| Labia majora excess (post-massive weight loss) | Labia majora reduction (excision) | Very Low (case reports) |
| Mons pubis ptosis / excess | Monsplasty (liposuction, excision, or dermal-fascial suspension according to the deformity)[38] | Very Low (case series) |
| Vulvovaginal atrophy (GSM) | Offer the option of local low-dose vaginal estrogen for GSM-related dryness, discomfort/irritation, or dyspareunia .[29] Microfat and nanofat grafting have been described in a small GSM series.[23] Vaginal laser devices have insufficient evidence for routine GSM use (see Vaginal Laser Therapy).[4][17][29] | Vaginal estrogen: Grade C; fat grafting: uncontrolled series; laser: evidence does not support routine use |
| Hymen restoration | Hymenoplasty | Very Low (retrospective series) |
| G-spot enhancement | No established enhancement procedure; explain the absent efficacy evidence and ACOG and FIGO positions.[1][4] | Virtually none; safety and effectiveness not established |
Technique Selection by Procedure Category
Labiaplasty: Trim vs Wedge vs De-Epithelialization
| Factor | Trim Resection | Wedge Resection | De-Epithelialization |
|---|---|---|---|
| Best for | Irregular / darkened edge; diffuse protrusion[13] | Central protrusion; preserve natural edge / color transition | Mild hypertrophy; preserve volume |
| Pooled satisfaction (Géczi 2024) | 96% (edge resection) | 96% | 97% (5 studies; 95% CI 85–99%)[6] |
| Pooled dehiscence | Not among the highest | 3% (Escandón 2022) to 8% (Géczi 2024)[5][6] | Not among the highest |
| Nicotine or cocaine use | Favored[13] | Not favored[13] | Not addressed in the algorithm |
| Edge appearance | Scar along free margin | Preserves natural edge | Preserves natural edge |
| Surgeon experience needed | Precise marking and frenular preservation[13] | Flap design and vascular preservation[13] | Not comparatively established |
| Decision rule | Zahedi 2023 algorithm: the patient wants the darkened or irregular edge removed[13] | Zahedi 2023 algorithm: the patient wants the natural edge and color transition preserved[13] | Mild hypertrophy with a wish to preserve volume (not part of the Zahedi algorithm) |
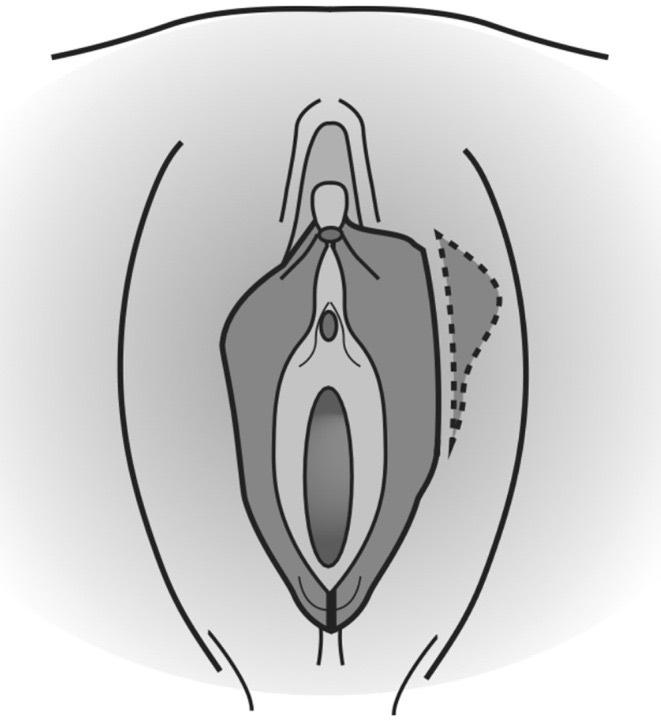
Edge (trim) resection labiaplasty: a linear vertical incision on the labium minus removes the excess tissue along an excision line that follows the curve of the labium (dashed line). From Buzzaccarini G, et al. Int J Gynaecol Obstet. 2025;170(1):49–58, Figure 2 (CC BY 4.0).[22]
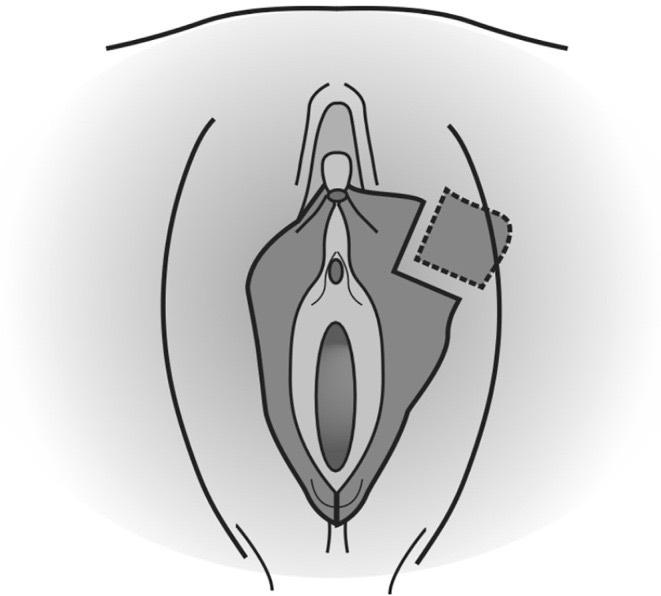
Wedge resection labiaplasty: after the limits of resection are drawn (dashed outline), the edges are cut with a scalpel and then approximated, reducing the labium while keeping its natural edge. From Buzzaccarini G, et al. Int J Gynaecol Obstet. 2025;170(1):49–58, Figure 3 (CC BY 4.0).[22]
Energy-Based Devices for GSM / "Rejuvenation"
Energy-based devices (fractional CO₂, Er:YAG, RF ± PEMF) are not FDA-cleared for cosmetic vaginal "rejuvenation" or for GSM (FDA 2018 Safety Communication).[2] In the double-blind, sham-controlled Li 2021 JAMA RCT (85 postmenopausal women), fractional CO₂ laser did not significantly improve vaginal symptoms at 12 months.[17] Uncontrolled series report benefit, and the discrepancy may reflect a placebo effect. A systematic review of vaginal-laxity treatments found improved sexual function in observational studies but not in randomized trials.[11] FIGO 2025 states that research data are insufficient to support the safety and effectiveness of laser devices for GSM or cosmetic purposes.[4] ESSM 2020 likewise found that the clinical effect of laser devices on vaginal symptoms was not clearly established.[30] For GSM, the 2025 AUA/SUFU/AUGS guideline recommends counseling that evidence does not support CO₂ laser, Er:YAG laser, or radiofrequency for dryness, discomfort or irritation, dysuria, dyspareunia, quality of life, bothersome symptoms, or treatment satisfaction .[29] It permits consideration of CO₂ laser for dryness, discomfort or irritation, dysuria, or dyspareunia in patients who are not candidates for, or prefer alternatives to, FDA-approved treatments, with shared decision-making and disclosure that use outside clinical trials is experimental .[29] A 2020 single-institution model used a $2,733 patient price for three CO₂ sessions; confirm current local pricing and payer coverage for counseling.[40] For full cross-indication evidence (GSM / SUI / lichen sclerosus / vaginal laxity / breast-cancer survivors) see the canonical Vaginal Laser Therapy page.
Combined Procedures
Multiple procedures are frequently performed simultaneously to achieve a harmonious result. For combined procedures, counsel about the operative and anesthetic exposure and the potential complications of each planned component.[14][15]
- Labiaplasty and clitoral hoodoplasty. This is the most common combination. Concomitant hoodoplasty is done to avoid residual hood redundancy after isolated labiaplasty (Liu 2022; Eserdağ 2021 inverted-Y; Xia 2021 three-step composite).[10][16][19]
- Labiaplasty and labia majora augmentation. This addresses the labia majora–to–minora ratio and allows more conservative labial reduction. In Hersant 2018 (n = 21), one patient had a small edge separation and 81% were satisfied or very satisfied.[18]
- "Genital beautification" packages. Cihantimur 2013 combined labia minora reduction, labia majora fat augmentation, laser brightening, mons liposuction, and optional vaginal tightening (n = 124; wound dehiscence in 8.1%).[14] Cihantimur 2021 studied labia majora augmentation and vaginal tightening with 360 fat transfer (n = 97).[15] Toplu 2021 studied labia minora reduction with optional mons and labia majora fat injection and CO₂ laser (n = 37).[21]
Special Decision Branch — Clitoral Hoodoplasty
Frequently performed concurrently with labiaplasty. The Liu 2022 Aesthet Plast Surg classification divides the hood into a central zone (C) and a lateral zone (L) and defines five types (standard, central hypertrophy, lateral hypertrophy, composite hypertrophy, special). It guides technique selection.[10]
| Anatomy | Technique | Outcome |
|---|---|---|
| Vertical and / or horizontal central redundancy | Inverted-Y plasty with concomitant curvilinear labiaplasty (Eserdağ 2021 n = 63)[16] | 96.9% aesthetic satisfaction with the combined operation at 2 mo |
| Horizontal redundancy | Bilateral triangular skin resection | Per Liu classification |
| Vertical redundancy | Inverted horizontal V-shaped resection | Per Liu classification |
| Composite (lateral hood + labia minora) | Three-step excision (Xia 2021 n = 136)[19] or two-part excision (Duan 2026 n = 68)[20] | Xia: mixed-age cohort (9–55 years), 95.5% satisfaction at 3 mo, complications 4.4%, revision 3.7%. Duan: adult cohort, complications 7.4%, revision 1.5%, GAS scores improved |
| Liu 2022 classification-based (any anatomy) | Tailored technique per zone[10] | 95.7% satisfaction at 6 mo; complications 4.3%; revision 1.9% (n = 789) |
Safety note. Identify and protect the clitoral body and dorsal nerve during hoodoplasty; injury may impair clitoral sensation and sexual response.[39]
Postoperative Management
- Activity restriction. Match restrictions to the procedure and healing: an expert technical review describes avoiding tampons or intercourse for 4 weeks after trim labiaplasty or clitoral hood reduction, up to 6 weeks after wedge labiaplasty, and 6–8 weeks after perineoplasty or vaginoplasty; high-impact exercise after monsplasty or majoraplasty is delayed for 6 weeks.[35]
- Wound care: sitz baths, topical antibiotic ointment, loose-fitting clothing.
- Ice application: first 48–72 hours to reduce edema.
- Follow-up cadence: 1 week (wound check), 6 weeks (clearance for activity), 3–6 months (final outcome assessment).
- PRO assessment: FSFI at baseline and 6 months postoperatively; FGSIS or GAS at baseline and 6 months.
- Maintenance counseling: HA filler will resorb over time (see Labia Majora Augmentation); whether repeat energy-based sessions are needed or effective for GSM or vaginal laxity remains undetermined.[32]
Complication Management
| Complication | Incidence | Management |
|---|---|---|
| Wound dehiscence | Escandón: 3% with wedge and 5% with laser; Géczi: 8.4% with wedge and 13.3% with Z-plasty (one study)[5][6] | Conservative; secondary closure if needed |
| Asymmetry | 6.3% in Qiang’s 414-patient labiaplasty series[12] | Observation (may improve with edema resolution); revision if persistent |
| Hematoma | 0.5–8% (highest pooled incidence with W-shape resection)[5] | Observation if small; drainage if expanding |
| Infection | 3.0% pooled after labiaplasty (95% CI 1.9–4.7%; 35 studies)[6] | Antibiotics; wound care |
| Flap necrosis (wedge) | Very rare (3 cases in a meta-analysis of 3,804 patients)[5] | Debridement; secondary healing or revision |
| Altered sensation | Possible complication; incidence and persistence are not established[1] | Assess distribution, severity, and course |
| Over-resection | Frequency not established[13] | Prevent with conservative marking; reconstruction may be possible if sufficient tissue remains, but correction is not always possible[13] |
| Patient dissatisfaction | 8.9% after labiaplasty with or without hood reduction (Qiang); 1.6% dissatisfied with aesthetic result after mixed genital beautification (Cihantimur)[12][14] | Reassess the specific concern and any complication; assess for BDD when indicated, and refer suspected psychological concerns for mental-health evaluation before considering revision.[1] |
Treatment Database
| Procedure | Domain | Best for / indication |
|---|---|---|
| Trim Labiaplasty | Labiaplasty | Irregular or darkened labial edge; diffuse protrusion; trim is favored over wedge if surgery proceeds in a nicotine or cocaine user[13] |
| Wedge Labiaplasty | Labiaplasty | Central labial protrusion with desire to preserve natural edge / color transition |
| De-Epithelialization Labiaplasty | Labiaplasty | Mild hypertrophy with desire to preserve volume; dehiscence was not among the highest pooled rates[5][6] |
| Laser-Assisted Labiaplasty | Labiaplasty | Satisfaction and overall complication rates were not significantly different from scalpel in an observational meta-analysis; laser cohorts had lower pooled bleeding, swelling, and hematoma rates, with limited comparative evidence.[6] |
| Combined Wedge-Edge Resection | Labiaplasty | Mixed central protrusion + irregular edge requiring both edge cleanup and central reduction |
| Inverted-Y Plasty Clitoral Hoodoplasty | Clitoral Hoodoplasty | Vertical and/or horizontal central hood redundancy (Eserdağ technique) |
| Bilateral Triangular / Inverted-V Resection (Liu) | Clitoral Hoodoplasty | Hood reduction tailored to Liu 2022 zone classification (horizontal vs vertical redundancy) |
| Three-Step / Two-Part Composite Excision | Clitoral Hoodoplasty | Composite lateral hood + labia minora redundancy in a single excision |
| Labia Majora Augmentation (Autologous Fat Grafting) | Labia Majora | Labia majora atrophy or deflation; restores volume and balances minora-to-majora ratio |
| Labia Majora Reduction (Majoraplasty) | Labia Majora | Labia majora excess (often after massive weight loss) |
| Monsplasty | Mons Pubis | Mons pubis ptosis or excess; typically combined with abdominoplasty or post-MWL |
| Fat Grafting to Mons Pubis | Mons Pubis | Mons pubis deflation; volume restoration without skin excision |
| Vaginal Laser Therapy (Fractional CO₂ / Er:YAG / RF) | Energy-Based Devices | GSM and "vaginal rejuvenation" uses are not FDA-cleared[2]; a sham-controlled fractional CO₂ trial in postmenopausal women found no significant vaginal-symptom improvement at 12 months[17] |
| Hymenoplasty | Hymenoplasty / G-Spot | Hymen restoration for cultural, religious, or personal reasons |
| G-Spot Amplification | Hymenoplasty / G-Spot | HA injection for purported "G-spot" enhancement; safety/efficacy not established |
| Microfat + Nanofat Grafting | Regenerative | Microfat to labia majora and nanofat to vagina have been described for vulvovaginal atrophy/GSM in an uncontrolled 50-patient series; comparative or restorative efficacy is unestablished[23] |
See Also
- Male Cosmetic Genital Surgery
- Genital Reconstruction Atlas (non-cosmetic)
- Gender-Affirming Surgery
- Prolapse Repair — Posterior Colporrhaphy
- Foundations — V-Y Advancement Flap
References
1. Committee on Gynecologic Practice, American College of Obstetricians and Gynecologists. Elective female genital cosmetic surgery: ACOG Committee Opinion No. 795. Obstet Gynecol. 2020;135(1):e36–e42. doi:10.1097/AOG.0000000000003616
2. US Food and Drug Administration. Statement on efforts to safeguard women's health from deceptive health claims and significant risks related to devices marketed for use in medical procedures for "vaginal rejuvenation". FDA Safety Communication. 2018.
3. Mansfield AK. Genital manifestations of body dysmorphic disorder in men: a review. Fertil Steril. 2020;113(1):16–20. doi:10.1016/j.fertnstert.2019.11.028
4. Capito L, Antsaklis A, Gupte S. FIGO Statement: cosmetic genital surgery. Int J Gynaecol Obstet. 2025;170(1):11–14. doi:10.1002/ijgo.70203
5. Escandón JM, Duarte-Bateman D, Bustos VP, et al. Maximizing safety and optimizing outcomes of labiaplasty: a systematic review and meta-analysis. Plast Reconstr Surg. 2022;150(4):776e–788e. doi:10.1097/PRS.0000000000009552
6. Géczi AM, Varga T, Vajna R, et al. Comprehensive assessment of labiaplasty techniques and tools, satisfaction rates, and risk factors: a systematic review and meta-analysis. Aesthet Surg J. 2024;44(11):NP798–NP808. doi:10.1093/asj/sjae143
7. Sorice-Virk S, Li AY, Canales FL, Furnas HJ. Comparison of patient symptomatology before and after labiaplasty. Plast Reconstr Surg. 2020;146(3):526–536. doi:10.1097/PRS.0000000000007081
8. Sharp G, Tiggemann M, Mattiske J. Psychological outcomes of labiaplasty: a prospective study. Plast Reconstr Surg. 2016;138(6):1202–1209. doi:10.1097/PRS.0000000000002751
9. Goodman MP, Placik OJ, Benson RH, et al. A large multicenter outcome study of female genital plastic surgery. J Sex Med. 2010;7(4 Pt 1):1565–1577. doi:10.1111/j.1743-6109.2009.01573.x
10. Liu M, Li Q, Li S, et al. Preliminary exploration of a new clitoral-hood classification system and treatment strategy. Aesthet Plast Surg. 2022;46(6):3080–3093. doi:10.1007/s00266-022-02874-y
11. Pereira GMV, Cartwright R, Juliato CRT, et al. Treatment of women with vaginal laxity: systematic review with meta-analysis. J Sex Med. 2024;21(5):430–442. doi:10.1093/jsxmed/qdae028
12. Qiang S, Li FY, Zhou Y, et al. Long-term follow-up in labiaplasty in 414 women: a single-center experience in China. Ann Plast Surg. 2022;89(4):353–357. doi:10.1097/SAP.0000000000003264
13. Zahedi S, Bhat D, Pedreira R, Canales FL, Furnas HJ. Algorithm for trim and wedge labiaplasties. Aesthet Surg J. 2023;43(6):685–692. doi:10.1093/asj/sjad033
14. Cihantimur B, Herold C. Genital beautification: a concept that offers more than reduction of the labia minora. Aesthet Plast Surg. 2013;37(6):1128–1133. doi:10.1007/s00266-013-0211-4
15. Cihantimur B, Aglamis O, Ozsular Y. 360 genital fat transfer. Aesthet Plast Surg. 2021;45(6):2996–3002. doi:10.1007/s00266-021-02488-w
16. Eserdağ S, Anğın AD. Surgical technique and outcomes of inverted-Y plasty procedure in clitoral-hoodoplasty operations. J Minim Invasive Gynecol. 2021;28(9):1595–1602. doi:10.1016/j.jmig.2021.01.015
17. Li FG, Maheux-Lacroix S, Deans R, et al. Effect of fractional carbon dioxide laser vs sham treatment on symptom severity in women with postmenopausal vaginal symptoms: a randomized clinical trial. JAMA. 2021;326(14):1381–1389. doi:10.1001/jama.2021.14892
18. Hersant B, Jabbour S, Noel W, et al. Labia majora augmentation combined with minimal labia minora resection: a safe and global approach to the external female genitalia. Ann Plast Surg. 2018;80(4):323–327. doi:10.1097/SAP.0000000000001435
19. Xia Z, Liu CY, Yu N, et al. Three-step excision: an easy way for composite labia minora and lateral clitoral hood reduction. Plast Reconstr Surg. 2021;148(6):928e–935e. doi:10.1097/PRS.0000000000008589
20. Duan L, Li Z, Zhang H, Zhang B. Composite labia minora and clitoral hood reduction: an optional surgical method. Aesthet Plast Surg. 2026;50(8):3035–3042. doi:10.1007/s00266-025-05075-5
21. Toplu G, Altinel D. Genital beautification and rejuvenation with combined use of surgical and non-surgical methods. Aesthet Plast Surg. 2021;45(2):758–768. doi:10.1007/s00266-020-01980-z
22. Buzzaccarini G, Degliuomini RS, De Rosa L, Villa S, Messina S, Siesto G, et al. A road map through the multi-faceted world of female genital cosmetic surgical techniques. Int J Gynaecol Obstet. 2025;170(1):49–58. doi:10.1002/ijgo.16169
23. Menkes S, SidAhmed-Mezi M, Meningaud JP, Benadiba L, Magalon G, Hersant B. "Microfat and nanofat grafting in genital rejuvenation." Aesthet Surg J. 2021;41(9):1060–1067. doi:10.1093/asj/sjaa118
24. Lekakis G, Picavet VA, Gabriëls L, Grietens J, Hellings PW. "Body dysmorphic disorder in aesthetic rhinoplasty: Validating a new screening tool." Laryngoscope. 2016;126(8):1739–1745. doi:10.1002/lary.25963
25. Snorrason I, Jaroszewski AC, Greenberg JL, et al. "Yale-Brown Obsessive-Compulsive Scale modified for body dysmorphic disorder: Factor structure and construct validity of subfactors." J Obsessive Compuls Relat Disord. 2024;42:100881. doi:10.1016/j.jocrd.2024.100881
26. Veale D, Gledhill LJ, Christodoulou P, Hodsoll J. "Body dysmorphic disorder in different settings: A systematic review and estimated weighted prevalence." Body Image. 2016;18:168–186. doi:10.1016/j.bodyim.2016.07.003
27. Randombage PJS, Hettipathirana PS, Akurugodagama M. "Comparative effectiveness of conservative and surgical interventions for vaginal laxity: a systematic review and pairwise meta-analysis." Int Urogynecol J. 2026. doi:10.1007/s00192-026-06833-y
28. Committee on Adolescent Health Care, American College of Obstetricians and Gynecologists. "Breast and labial surgery in adolescents: Committee Opinion No. 686." Obstet Gynecol. 2017;129(1):e17–e19. doi:10.1097/AOG.0000000000001862
29. Kaufman MR, Ackerman LA, Amin KA, et al. "The AUA/SUFU/AUGS guideline on genitourinary syndrome of menopause." J Urol. 2025;214(3):242–250. doi:10.1097/JU.0000000000004589
30. Romero-Otero J, Lauterbach R, Aversa A, et al. "Laser-based devices for female genitourinary indications: position statements from the European Society for Sexual Medicine (ESSM)." J Sex Med. 2020;17(5):841–848. doi:10.1016/j.jsxm.2020.02.013
31. Fasola E, Dridi D, Degliuomini RS, et al. "Performance and safety of hyaluronic acid-based gynaecological filler for labia majora augmentation: a randomised controlled study." Life (Basel). 2026;16(7):1141. doi:10.3390/life16071141
32. Juhász MLW, Korta DZ, Mesinkovska NA. "Vaginal rejuvenation: a retrospective review of lasers and radiofrequency devices." Dermatol Surg. 2021;47(4):489–494. doi:10.1097/DSS.0000000000002845
33. US Food and Drug Administration. "Dermal Fillers (Soft Tissue Fillers)." FDA. https://www.fda.gov/medical-devices/aesthetic-cosmetic-devices/dermal-fillers-soft-tissue-fillers (accessed October 8, 2026).
34. McGrattan M, Majeed A, Hanna SA. "Long-term Functional and Aesthetic Outcomes of Labiaplasty: A Review of the Literature." Aesthet Surg J. 2025;45(2):180–185. doi:10.1093/asj/sjae211
35. Furnas HJ, Canales FL, Pedreira RA, et al. "The Safe Practice of Female Genital Plastic Surgery." Plast Reconstr Surg Glob Open. 2021;9(7):e3660. doi:10.1097/GOX.0000000000003660
36. Alavi-Arjas F, Nahidi F, Simbar M, et al. "The role of sexual partner in women’s seeking for labiaplasty: a systematic review and meta-analysis." J Sex Med. 2024;21(10):844–852. doi:10.1093/jsxmed/qdae091
37. Minikowski GC, Veiga DF, Felix GAA, Pedroso JCM, Ferreira LM, Sabino Neto M. "Genital self-image and body dysmorphic symptoms in patients undergoing central wedge or linear labiaplasty: a clinical trial." Plast Reconstr Surg. 2025;155(1):53e–65e. doi:10.1097/PRS.0000000000011534
38. El-Khatib HA. "Mons pubis ptosis: classification and strategy for treatment." Aesthet Plast Surg. 2011;35(1):24–30. doi:10.1007/s00266-010-9552-4
39. Tappy E, Corton M. "Surgical anatomy of the clitoris and surrounding vulvar structures." Am J Obstet Gynecol. 2023;229(4):460–462. doi:10.1016/j.ajog.2023.07.004
40. Wallace SL, St Martin B, Lee K, Sokol ER. "A cost-effectiveness analysis of vaginal carbon dioxide laser therapy compared with standard medical therapies for genitourinary syndrome of menopause-associated dyspareunia." Am J Obstet Gynecol. 2020;223(6):890.e1–890.e12. doi:10.1016/j.ajog.2020.06.032