Hyaluronic Acid Filler — Penile Girth Augmentation
Hyaluronic acid (HA) filler injection is a minimally invasive office-based procedure for penile girth enhancement. It is the most commonly described injectable filler for this indication, and a narrative review reports that it is better tolerated than other augmentation methods.[1][4] Its main advantage is reversibility with hyaluronidase. Published penile HA series describe different injection approaches.[5][6] Penile HA use in the United States is outside FDA-approved indications.[23] The 2026 EAU guideline weakly recommends HA for girth enhancement, whereas the 2026 BAUS/AGUS consensus recommends against absorbable injectable fillers because of low-quality supporting evidence.[19][22] For positioning versus other male cosmetic options see Cosmetic Genital Surgery — Male.
Society positioning. The SMSNA 2024 position statement states that limited data suggest a cosmetic benefit of temporary HA and PLA fillers for girth, with an acceptable safety profile, and urges IRB-approved safety and efficacy studies.[18] The cited trial enrolled 74 men with small penis syndrome; injection-site adverse events occurred in 2/39 (5.1%) assigned HA and 5/35 (14.3%) assigned PLA by 24 weeks.[3] The SMSNA statement strongly recommends against permanent fillers such as paraffin and silicone and requires that penile dysmorphic disorder be ruled out before any invasive enhancement.[18] Reviews describe the evidence as low quality and the procedures as investigational.[2] The 2026 Fifth International Consultation on Sexual Medicine considers biodegradable fillers such as HA relatively safe but expects additional procedures over time ; it recommends against silicone, paraffin and oil-based fillers .[20] HA fillers are FDA-approved for facial soft-tissue augmentation; penile use is off-label.[23]
HA injection into the glans, for cosmetic glans enlargement or premature ejaculation, uses a different plane and volume and is covered on Glans Augmentation with Hyaluronic Acid.
Patient population and indications
Small penis syndrome (SPS) describes distress about penile size despite dimensions often being in the normal range; it is distinct from true micropenis (stretched penile length < 2.5 SD below mean).[3] Assess separately for penile dysmorphic disorder (PDD), which the SMSNA says must be ruled out before invasive treatment.[18] The 2026 EAU guideline recommends against HA filler in men with PDD .[19] Most men seeking penile augmentation have penile dimensions within the normal range.[4] See Small Penis Syndrome / PDD for the full clinical context.
Pre-treatment considerations:
-
Baseline assessment. Record stretched penile length and shaft girth , and use a validated questionnaire to screen for BDD in men with normal penile dimensions . Refer patients with suspected BDD for mental health counseling .[19]
-
Psychosexual counseling first. Many patients can be reassured without treatment.[5]
-
Psychosocial improvement does not correlate with penile-size change.[6]
-
Patients should understand the temporary nature of HA fillers and the need for repeat treatments.[7]
Mechanism and material properties
HA is a naturally occurring glycosaminoglycan in the extracellular matrix. When injected as a cross-linked gel, it produces volume augmentation through hydrophilic expansion; each molecule binds up to 1,000× its weight in water. Advantages over other injectable materials[4][8][9]:
- Biocompatibility. Naturally occurring substance with minimal immunogenicity.
- Reversibility. Dissolved with hyaluronidase if complications or undesired results.
- Predictable degradation. Gradually resorbed over months, allowing controlled retreatment.
Injection technique
No universally standardized protocol exists. Common elements[10][1][11]:
- Products: Restylane Sub-Q (Q-med), Macrolane VRF 30, and various high-viscosity, large-particle HA gels for deep-tissue augmentation.
- Volume: mean 20–40 mL across studies.[1]
- Plane: between Dartos fascia and Buck's fascia along the shaft, avoiding the dorsal neurovascular bundle and corpora cavernosa.[11][5]
- Anesthesia: local penile block or topical anesthetic; ambulatory / office setting.[12]
Described techniques
| Technique | Approach | Key feature |
|---|---|---|
| "Back & Forth" (Kwak 2011) | 21 G cannula, fascial layer; manual roller homogenization | Uniform shaft distribution[11] |
| Emicircumferential (Sito 2013) | Semicircular pattern (ventral or dorsal) rather than circumferential | Intended to reduce vascular-compromise risk; in a retrospective chart review, no complications in the HA arm vs 8 granulomas and 1 fat necrosis with lipofilling[7] |
| Combined shaft and glans injection (Boiko 2024) | 10 mL shaft HA via two 22 G cannula entry points; 4 mL glans HA via multiple injections | Single-center, 3-month case series[6] |
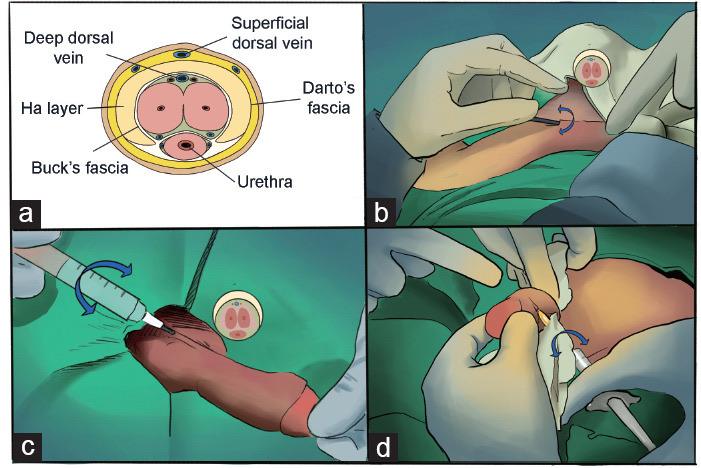
Penile augmentation with hyaluronic acid (HA) injection. (a) Cross-sectional view showing the HA layer in relation to Dartos fascia, Buck fascia, the superficial and deep dorsal veins and the urethra. (b) Full dilation of the subcutaneous space of the penile shaft with an 18-gauge cannula introduced through incisions at the penile root. (c) HA injection by the fanning technique. (d) Supplementary HA injection. From Zhang CL, et al. Asian J Androl. 2022;24(6):601-606, Figure 1 (CC BY-NC-SA).[5]
Efficacy
| Study | n | Volume | Follow-up | Flaccid girth gain | Erect girth gain | Satisfaction |
|---|---|---|---|---|---|---|
| Kwak 2011 J Sex Med[11] | 50 enrolled; 41 at 18 mo | 20.6 mL | 18 mo | +3.93 cm at 1 mo / +3.78 cm at 18 mo | NR | 3.34 / 4 patient; 3.38 / 4 partner at 18 mo |
| Yang 2019 RCT J Sex Med[9] | 36 assigned HA; 31/72 dropped out across both arms | NR | 48 wk | +1.70 cm | NR | maintained ≤ 48 wk |
| Yang 2020 24-wk RCT J Sex Med[3] | 39 (HA) | NR | 24 wk | +2.1 cm | NR | VAS appearance +1.8; sex life +1.0 |
| Yang 2020 18-mo RCT J Clin Med[13] | 33 (HA); 46/67 followed at 18 mo across both arms | NR | 18 mo | significant (p < 0.001) | NR | sustained |
| Zhang 2022 Asian J Androl[5] | 38 | 21.5 mL | 12 mo | +3.41 cm at 1 mo / +2.44 at 12 mo | +1.32 / +0.80 cm | IMGI +46.2; IIEF +7.6 |
| Quan 2021 Asian J Androl[10] | 230 | NR | 6 mo | +2.66 cm at 1 mo / +1.80 at 6 mo | NR | not formally assessed |
| Boiko 2024 (shaft plus glans HA) Aesthet Surg J[6] | 132/148 completers | 14 mL total (10 mL shaft; 4 mL glans) | 3 mo | +1.7 cm midshaft / +1.5 cm glans | NR | sexual relationship satisfaction +17.9; confidence +12.2 |
| Sito 2013 (HA and lipofilling combined; retrospective)[7] | 83 combined (56 HA; 27 lipofilling) | NR | 1-y assessment; mean follow-up 24 mo | +3.2–4.5 cm resting circumference across both methods | Not measured; patients reported decrement during erection | 72/83 (87%) "very satisfied" across both methods |
Key efficacy patterns
- Girth gain is greatest at 1 month and attenuates over 6–18 months, which is attributed to HA resorption. It remains statistically significant at all measured time points.[10][9][13]
- Flaccid girth gains exceed erect girth gains; at 12 months, erect girth gain was only +0.80 cm versus +2.44 cm flaccid.[5]
- Flaccid length increases modestly (+1.65–2.55 cm in Zhang 2022), possibly from added volume pushing penile skin forward. Length is not a primary effect.[5][7]
- Erectile function. IIEF rose by 7.6 (p < 0.01) at 1 month in the uncontrolled Zhang 2022 series.[5]
- Psychological benefits (improved genital self-image, reduced inadequacy beliefs, improved confidence) remained steady in follow-up even as physical gains attenuated.[5][3]
HA vs polylactic acid (PLA) fillers
Multicenter randomized comparisons include the Yang trials[3][9][13] and a separate Ahn trial. In Ahn, 64 men (32 per arm) completed 24-week follow-up, with no significant between-group difference in girth gain or satisfaction.[24] The Yang trials found:
- At 4 weeks, HA produced significantly greater girth than PLA (p < 0.001 in the 2019 trial). At 24 weeks in the 2020 trial the difference was 0.5 cm (p = 0.031).
- At 48 weeks the HA-PLA difference was no longer significant (p = 0.075). At 18 months, both groups maintained significant gains and the change in girth did not differ between groups.
- HA has a faster onset and is reversible with hyaluronidase.
- PLA is a slower-onset, collagen-stimulating filler that hyaluronidase does not dissolve. In the 18-month trial, mean girth gain declined by 43.6% from month 1 with HA versus 22.1% with PLA (p = 0.015), although between-group girth gains at month 18 did not differ significantly.[13]
HA vs other penile augmentation methods
| Method | Girth gain | Duration | Reversible | Complications | Key limitation |
|---|---|---|---|---|---|
| HA filler | +1.5–3.9 cm | 6–18 mo (temporary) | Yes (hyaluronidase) | 4.3–9.1% in selected cited studies[10][13]; pooled estimate 9.0% (95% CI 5.1–13.9%) across studies[21] | Repeat treatments; attenuation |
| Lipofilling (autologous fat) | 3.2–4.5 cm was reported across HA and fat in Sito 2013, not separately for fat[7] | unpredictable resorption | No | Granuloma, fat necrosis (8 granulomas and 1 fat necrosis in Sito 2013) | Unpredictable resorption; donor-site morbidity |
| Surgical grafts (dermal / AlloDerm) | significant | Permanent | No | Skin necrosis, infection, reoperation reported across surgical-treatment studies; 8/15 (53.3%) studies reported at least one of these events, a figure not specific to grafts[2] | Negative impact on penile length; higher morbidity |
| Silicone implants (Penuma) | significant | Permanent | Surgical removal | Infection, erosion, seroma, necrosis; removal up to 10%[4] | Risk of severe deformity |
A narrative review concluded that HA filler injections are better tolerated than other penile-augmentation methods, although follow-up periods are short. In retrospective series, surgical grafts improved girth and satisfaction but reduced penile length. Silicone implants carried risks of infection, erosion, seroma and necrosis, with removal in up to 10%.[4]
Safety and complications
Series and randomized trials of HA penile augmentation report low complication rates.[5][3][9][10][6] In Boiko's single-center series of 132 completers, there were 12 incidents (9%) of gel migration or nodule formation and 2 incidents (1.5%) of transient pain by 3 months.[6]
- In the Quan series, 10/230 (4.3%) men had bleeding, nodules, or infection over 6 months; edema was reported separately in 21/230 (9.1%), all of whom had redundant prepuce.[10] Injection-related adverse events occurred in 2/39 (5.1%) men receiving HA in the 24-week Yang trial and 3/33 (9.1%) in the 18-month trial.[3][13]
Reported complications[10][4][8]:
- Subcutaneous bleeding or bruising. Most common; self-limiting.
- Subcutaneous nodules. Palpable lumps from uneven distribution or focal HA accumulation.
- Penile edema. Transient; more common with redundant prepuce.
- Gel migration. Displacement from injection site; associated with redundant prepuce.
- Infection. In Quan's series, 2/230 (0.9%) men developed infection; both underwent incision and drainage of purulence and HA followed by 3–5 days of intravenous antibiotics.[10]
- Contour irregularities or asymmetry. Corrected with hyaluronidase or additional filler.[12][8]
- No systemic or local allergic reactions occurred in the Quan 2021 series.[10]
- No serious adverse events were reported in the randomized HA-versus-PLA trials.[3][9][13]
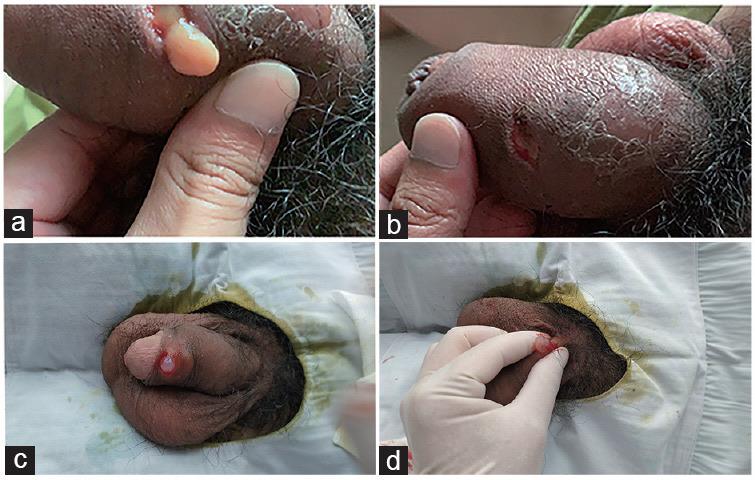
Management of infection and nodules after penile HA augmentation. (a) Purulent fluid and HA gel discharged after incision of the infected penile skin. (b) Appearance 3 days after debridement. (c) Incision over a subcutaneous nodule in the penile skin. (d) Removal of the subcutaneous nodule. From Quan Y, et al. Asian J Androl. 2021;23(4):392-395, Figure 4 (CC BY-NC-SA).[10]
Distinguish HA from unapproved oil-based injectables. HA fillers must be differentiated from unapproved oil-based substances (silicone oil, paraffin, mineral oil, Vaseline) injected in non-medical settings; see Non-Autologous Injectables for the full per-substance breakdown. These cause sclerosing lipogranuloma ("paraffinoma" or "siliconoma") requiring complex tissue excision and skin transplantation. Prior oil-based injections can cause tissue injury requiring excision.[4] After excision, HA correction of residual contour deformity has been described in a five-patient retrospective series.[12]
Reversibility with hyaluronidase
Reversibility is the main advantage of HA over other injectable materials.[8][14]
- Moon 2026 Int J Impot Res case series. In four patients with residual HA after penile girth enhancement, hyaluronidase was used to correct asymmetries, manage adverse effects and prepare the site for reinjection.[8]
- Hyaluronidase is FDA-approved as an adjuvant in subcutaneous fluid administration, to increase dispersion and absorption of other injected drugs, and in subcutaneous urography. Filler dissolution is off-label.[15]
- Alam 2018 JAMA Dermatol RCT. In 9 women with filler nodules in the inner arm, hyaluronidase resolved nodules better than saline, higher doses (9 U vs 1.5 U per 0.1 mL) resolved them faster, and the dose effect was more notable for Restylane-L.[14]
- Dermatologic reviews describe hyaluronidase as generally safe; hypersensitivity to the enzyme itself is possible.[16][17]
Durability and retreatment
HA filler augmentation is inherently temporary, both a limitation and a safety feature.
- Peak girth gains at 1 month.
- Gradual attenuation occurs over 6–18 months, attributed to enzymatic degradation and mechanical forces.
- At 12 months, flaccid girth gains retain approximately 70–75% of 1-month peak (e.g., +3.41 to +2.44 cm).[5]
- At 18 months, significant augmentation persists in RCT data (p < 0.001); 46/67 participants across both arms were followed to that visit, and missing outcomes were carried forward.[13]
- One Restylane Sub-Q series reported maintenance at 18 months with minimal attenuation (from 11.41 to 11.26 cm).[11]
- Repeat treatments are necessary to maintain results, with cumulative cost.[7]
- Variability in durability reflects HA-product cross-linking density, injection volume, plane, and individual patient metabolism.
Correction of secondary deformities
HA fillers have also been used to correct secondary contour deformities of the penis after prior augmentation procedures (e.g., after excision of non-absorbable substances). In the Yordanov 2021 retrospective series of 5 patients (mean 3.32 mL HA), the filler corrected residual irregularities, including in fibrosis from prior surgeries. Satisfaction was high with no complications at 9 months.[12]
Limitations of current evidence
- No standardized injection protocol. Volumes, products, techniques, and planes vary across studies.[10][1]
- Overall low quality of evidence. The vast majority of studies (89.7%) are not RCTs.[2]
- Short follow-up periods. Prospective HA filler studies have short follow-up, and long-term data are limited.[4]
- High dropout rates. Up to 43.1% in some RCTs.[9]
- Publication bias. Adverse events likely under-reported.[2]
- Lack of standardized outcome measures. Different studies use different satisfaction and girth-measurement instruments.
- No head-to-head RCTs versus surgical girth enhancement.
Where HA filler fits
- Temporary HA filler has been studied in randomized trials for cosmetic girth enhancement in men with SPS.[3] Psychosexual counseling and reassurance come first; the 2026 EAU guideline strongly recommends against HA in men with PDD.[19]
- HA is reversible with hyaluronidase, and reported complication rates are low.
- Repeat treatments are required to maintain results; counsel patients on cumulative cost and the temporal pattern of attenuation.
- HA is not a length-enhancement intervention; for length see Penile Traction Therapy.
- Surgical approaches. Penuma silicone sleeves and dermal grafts can require revision or removal; retrospective graft series report penile shortening. The 2026 EAU guideline strongly recommends against both for penile girth enhancement because it considers them experimental.[4][19]
- A multidisciplinary approach is advised: psychological assessment, realistic expectations, and informed consent about the temporary effect and complications.[4]
See Also
Cosmetic Genital Surgery — Male · Glans Augmentation with Hyaluronic Acid · Small Penis Syndrome / PDD · Penile Traction Therapy · Vacuum Erection Device · Penile Implants
References
1. Salloum A, Bazzi N, Haber R. Nonsurgical methods for penile augmentation: a systematic review. Dermatol Surg. 2021;47(3):e81-e85. doi:10.1097/DSS.0000000000002816
2. Manfredi C, Romero Otero J, Djinovic R. Penile girth enhancement procedures for aesthetic purposes. Int J Impot Res. 2022;34(4):337-342. doi:10.1038/s41443-021-00459-y
3. Yang DY, Jeong HC, Ahn ST, et al. A comparison between hyaluronic acid and polylactic acid filler injections for temporary penile augmentation in patients with small penis syndrome: a multicenter, patient/evaluator-blind, comparative, randomized trial. J Sex Med. 2020;17(1):133-141. doi:10.1016/j.jsxm.2019.10.006
4. Ramazan M, Øbro LF, Wiborg MH, et al. Complications of penile augmentation: a narrative review of injectables, implants, and surgical grafts. Int J Impot Res. 2026;38(3):238-246. doi:10.1038/s41443-025-01190-8
5. Zhang CL, Quan Y, Li H, et al. Penile augmentation with injectable hyaluronic acid gel: an alternative choice for small penis syndrome. Asian J Androl. 2022;24(6):601-606. doi:10.4103/aja20223
6. Boiko MI, Notsek MS, Boiko OM. The efficacy of injection penile girth enhancement as an option for small penis syndrome management. Aesthet Surg J. 2023;44(1):84-91. doi:10.1093/asj/sjad152
7. Sito G, Marlino S, Santorelli A. Use of Macrolane VRF 30 in emicircumferential penis enlargement. Aesthet Surg J. 2013;33(2):258-264. doi:10.1177/1090820X12472337
8. Moon DG, Cho SB, Ahn ST. Managing residual volumes in penile girth enhancement with hyaluronic acid fillers: a case series and literature review. Int J Impot Res. 2026;38(8):575-579. doi:10.1038/s41443-025-01182-8
9. Yang DY, Ko K, Lee SH, Lee WK. A comparison of the efficacy and safety between hyaluronic acid and polylactic acid filler injection in penile augmentation: a multicenter, patient/evaluator-blinded, randomized trial. J Sex Med. 2019;16(4):577-585. doi:10.1016/j.jsxm.2019.01.310
10. Quan Y, Gao ZR, Dai X, et al. Complications and management of penile augmentation with hyaluronic acid injection. Asian J Androl. 2021;23(4):392-395. doi:10.4103/aja.aja_78_20
11. Kwak TI, Oh M, Kim JJ, Moon DG. The effects of penile girth enhancement using injectable hyaluronic acid gel, a filler. J Sex Med. 2011;8(12):3407-3413. doi:10.1111/j.1743-6109.2010.01748.x
12. Yordanov YP. Nonsurgical correction of secondary contour deformities of the penile girth. Aesthet Surg J. 2021;41(8):944-949. doi:10.1093/asj/sjab089
13. Yang DY, Jeong HC, Ko K, et al. Comparison of clinical outcomes between hyaluronic and polylactic acid filler injections for penile augmentation in men reporting a small penis: a multicenter, patient-blinded/evaluator-blinded, non-inferiority, randomized comparative trial with 18 months of follow-up. J Clin Med. 2020;9(4):E1024. doi:10.3390/jcm9041024
14. Alam M, Hughart R, Geisler A, et al. Effectiveness of low doses of hyaluronidase to remove hyaluronic acid filler nodules: a randomized clinical trial. JAMA Dermatol. 2018;154(7):765-772. doi:10.1001/jamadermatol.2018.0515
15. HYLENEX recombinant (hyaluronidase human injection) prescribing information, section 1, Indications and Usage. Halozyme/Antares Pharma. DailyMed set ID 3023cc56-ed4b-4e87-b3a1-81b20943f658.
16. Landau M. Hyaluronidase caveats in treating filler complications. Dermatol Surg. 2015;41 Suppl 1:S347-S353. doi:10.1097/DSS.0000000000000555
17. Sharma DSC, Lahiri MA. Use of hyaluronidase in plastic surgery: a review. J Plast Reconstr Aesthet Surg. 2021;74(7):1610-1614. doi:10.1016/j.bjps.2021.03.125
18. Trost L, Khera M, Köhler T, et al. Cosmetic penile enhancement procedures: an SMSNA position statement. J Sex Med. 2024;21(6):573-578. doi:10.1093/jsxmed/qdae045
19. European Association of Urology. "Penile Size Abnormalities and Dysmorphophobia." EAU Guidelines on Sexual and Reproductive Health. 2026. https://uroweb.org/guidelines/sexual-and-reproductive-health/chapter/penile-size-abnormalities-and-dysmorphophobia
20. Chung E, Jenkins L, Moon DG, et al. "Penile augmentation and cosmetic surgery: recommendations from the Fifth International Consultation on Sexual Medicine (ICSM 2024)." Sex Med Rev. 2026;14(1):qeaf067. doi:10.1093/sxmrev/qeaf067
21. Fonseca TDF, Querobino SM. "Penile augmentation procedures: a systematic review and meta-analysis of techniques, materials, and safety outcomes." Sex Health. 2026;23(4):SH26112. doi:10.1071/SH26112
22. Mubarak M, Kalejaiye O, Kumar V, et al. "British Association of Urological Surgeons (BAUS) consensus document on male genital augmentation and enhancement procedures." J Clin Urol. 2026;19(2):149-166. doi:10.1177/20514158251391054
23. U.S. Food and Drug Administration. "Dermal Fillers (Soft Tissue Fillers)." FDA Medical Devices. FDA guidance (accessed October 8, 2026).
24. Ahn ST, Shim JS, Bae WJ, Kim SW, Kim JJ, Moon DG. "Efficacy and safety of penile girth enhancement using hyaluronic acid filler and the clinical impact on ejaculation: a multi-center, patient/evaluator-blinded, randomized active-controlled trial." World J Mens Health. 2022;40(2):299-307. doi:10.5534/wjmh.210007