Labia Majora Augmentation (Autologous Fat Grafting)
Autologous fat grafting (lipofilling) is the most commonly reported technique for labia majora augmentation, the restoration of volume to atrophic, deflated, or hypoplastic labia majora using the patient's own adipose tissue. The Jabbour 2017 Aesthet Surg J systematic review of 9 studies (level 4 evidence) included 4 fat-grafting articles with 183 patients. More recent series add microfat, nanofat and stromal vascular fraction (SVF)-enriched preparations.[1][2][3] For positioning versus other female cosmetic options see Cosmetic Genital Surgery — Female.
Society positioning. ACOG Committee Opinion No. 795 (2020) states that procedures to alter sexual appearance or function, other than those done for clinical indications, are not medically indicated, pose substantial risk, and have no established safety or effectiveness.[4] It advises assessment for body dysmorphic disorder (BDD) when indicated, with psychiatric referral before surgery if psychological concerns are suspected. The FIGO 2025 statement considers it ethically inappropriate for obstetrician-gynecologists to recommend, perform, or refer patients for elective cosmetic genital surgery in women without structural or functional abnormalities; it distinguishes reconstruction for congenital anomalies or injury.[15] No randomized trials compare fat grafting with other augmentation methods for the labia majora, and only 2 of the 9 studies in the Jabbour review were prospective.[1]
Indications
- Age-related volume loss or atrophy. Postmenopausal deflated, wrinkled labia majora.[2][1]
- Genitourinary syndrome of menopause (GSM). Vulvovaginal atrophy with dryness and dyspareunia. For these symptoms, the 2025 AUA/SUFU/AUGS guideline recommends offering local low-dose vaginal estrogen and vaginal moisturizers or lubricants .[20] In an uncontrolled series of 50 women, labial microfat was combined with vaginal nanofat; its independent effect on GSM symptoms is undetermined.[2]
- Correcting the labia minora-to-majora ratio. Augmenting the majora masks conservatively reduced minora, which limits the labia minora resection needed (Hersant 2018 combined approach).[5]
- Post-surgical or oncologic reconstruction. After ablative surgery (e.g., for Bowen's disease) where flap reconstruction has not restored volume or relieved mucosal-exposure symptoms (Vogt 2011, single case report).[6]
- Gender-affirming surgery. Labial fat grafting after penile inversion vaginoplasty for flattened labia majora (the most common indication, 83% of grafted patients in Patel 2021). Patients requiring fat grafting were more likely to have had introital stenosis (33% versus 6%, p = 0.007) and prolonged granulation tissue > 6 weeks (83% versus 32%, p = 0.01).[7]
- Aesthetic dissatisfaction. Congenital hypoplasia or weight-loss-related deflation.[1][8]
Surgical technique
Fat harvest
- Donor sites. Abdomen, inner thighs, flanks, mons pubis. When the mons is also reduced, the harvested fat can serve as graft material (Cihantimur 2021 "360" technique).[3]
- Standard tumescent technique with small-bore liposuction cannulas.
Fat processing
| Method | Description | Use |
|---|---|---|
| Standard centrifugation | Harvested fat is centrifuged into oil, aqueous fraction and purified fat. Most common method.[1] | Volumetric augmentation |
| Microfat | Standard processed fat | Labia majora volume[2] |
| Nanofat | Mechanically emulsified and filtered fat preparation | Vaginal application has been described with concurrent labial microfat; its independent clinical effect is undetermined[2] |
| MAFT (micro-autologous fat transplantation) | Lai et al. used 1/120 mL parcels for vaginal submucosal injection; the labial parcel setting was not specified | Small-parcel delivery described; comparative labial graft survival was not measured[9] |
| SVF-enriched fat | ADSCs + SVF concentrate (Cihantimur 360) | Higher regenerative-cell load[3] |
Injection technique
- Blunt-tipped cannulas through small stab incisions.
- In El Danaf's combined body-contouring series, a blunt 2-mm cannula placed fat in thread-like rows, mainly in the medial labial tissue; symmetry was checked after injection.[17]
- Inject small aliquots per pass and avoid large boluses, which risk central necrosis.
Reported volumes per session
| Series | Technique | Volume per session |
|---|---|---|
| Jabbour 2017 SR[1] | Various fat grafting | Study mean total injected volumes: 18–120 mL per session |
| Menkes 2021[2] | Microfat + nanofat | Not separately specified |
| Lai 2023 (MAFT)[9] | Micro-autologous fat transplantation | Mean 20.8 mL vulva/mons among 14 labial recipients; mean 21.9 mL vagina among all 20 |
| Cihantimur 2021 (360)[3] | SVF-enriched fat | Not specified per site |
| Hersant 2018[5] | Standard fat grafting (combined with conservative labiaplasty) | Not specified |
Outcomes
| Series | n | Population | Satisfaction / endpoint | Follow-up |
|---|---|---|---|---|
| Cihantimur 2021 (360)[3] | 97 | Aesthetic (with vaginal tightening) | FGSIS 17.7 → 20.9 (6 mo, p < 0.001) → 22.2 (12 mo, p = 0.013) | 12 mo |
| Menkes 2021 (microfat / nanofat)[2] | 50 | GSM (mean age 53) | VHI + FSD significantly improved; 80% normalized at 6 mo; stable at 18 mo | 18 mo |
| Hersant 2018 (fat + conservative labiaplasty)[5] | 21 | Aesthetic | 81% satisfied / very satisfied; one minor wound separation (4.7%) | Not specified |
| Lai 2023 (MAFT)[9] | 20; 14 received labial grafts | Vaginal grafting in all 20; five also had labiaplasty | Reported questionnaire score 43.8 to 68.6 (p < 0.001); this score cannot be attributed specifically to labial grafting and is not interpretable as a standard FSFI total (maximum 36)[9][18] | 6 mo |
| Cihantimur 2013 (genital beautification)[8] | 124 | Combined procedures | 95.2% happy; 3.2% very happy | 12 mo |
| Patel 2021 (post-PIV)[7] | 6 (of 182 PIV patients) | Gender-affirming | Described by the authors as safe and effective; retrospective single-surgeon review | Not specified |
| Toplu 2021 (combined surgical / non-surgical)[10] | 37 | Aesthetic | 33/37 satisfied / very satisfied with postoperative appearance (89.2% by calculation; article reports an inconsistent 94.5%) | 12 mo |
Functional and histologic benefits
Fat grafting has also been associated with histologic and functional changes in small series.
- Lai 2023 MAFT. In a retrospective series, 20 women underwent vaginal fat grafting via the MAFT gun; 14 also received labial grafts. The authors reported improved lubrication and dyspareunia at six months. Vaginal tissue from one additional patient, sampled during vaginoplasty three months after grafting, showed greater collagen deposition, vascularity, and estrogen-receptor expression and less protein gene product 9.5 (a nerve-fiber marker) in grafted than adjacent nongrafted tissue.[9]
- Menkes 2021. In 50 women with GSM, microfat and nanofat grafting was followed by improvement, particularly in dryness and dyspareunia, with results stable through 18 months.[2]
Complications
No major or life-threatening complications were reported in the studies included in the Jabbour review.[1] Minor complications:
- Ecchymosis of labia majora and clitoral hood (transient; resolved by POD 7).[3]
- Tenderness in the pubic area was transient in the Cihantimur series.[3] Lai's 20-patient vaginal grafting series (14 also received labial grafts) reported mild palpable nodulation in one patient who had vaginal and labial grafting plus labiaplasty; the nodule's site was not specified.[9]
- Pain at vaginal entrance points (transient).[3]
- No infection, edema, lipoma, or granuloma formation was reported through postoperative month 3 in the Cihantimur 2021 combined labial-augmentation and vaginal-tightening series (n = 97).[3]
- The Hersant 2018 combined-technique series (n = 21) reported no flap necrosis, infection, pain, or sexual dysfunction; one small wound separation (4.7%) resolved spontaneously.[5]
- Wound dehiscence occurred in 8.1% of the Cihantimur 2013 genital-beautification series, which included concurrent labiaplasty.[8]
Fat-graft retention and durability
Labial volume retention has not been measured by MRI or ultrasound in a published series. Available signals:
- Menkes reported sustained VHI and Female Sexual Distress results through 18 months after combined labial microfat and vaginal nanofat treatment.[2]
- Cihantimur reported higher FGSIS scores at 6 and 12 months after combined labial augmentation and vaginal tightening.[3]
- In a 7-week mouse model, human fat grafts retained 56.5% of volume (Kim 2020); retention in human labia is unknown.[11]
- Repeat sessions were not reported in the earlier labial fat-grafting series above. In a 2026 retrospective series of 26 labial fat grafts performed during body contouring, two patients underwent repeat grafting after more than half the grafted volume was judged to have resorbed; 15 of 26 graft recipients had follow-up of at least two months.[17] Counsel about resorption and possible repeat grafting.[17]
Comparison with alternative augmentation methods
| Method | Material | Per-session volume | Duration | Advantages | Limits |
|---|---|---|---|---|---|
| Autologous fat grafting | Patient's own fat | Study mean total injected volumes 18–120 mL per session[1] | Labial volume retention was not quantified in the cited follow-up series[2][3] | Autologous; natural feel; no synthetic filler | Donor site; variable retention; possible overcorrection or repeat grafting |
| Hyaluronic acid (HA) | Product-specific: 19 or 21 mg/mL in the 2016 series; 25 mg/mL as reported in the 2026 trial[12][16] | 2–6 mL/session in older reviewed series; mean initial 0.5 mL/side in the 2026 trial[1][16] | Temporary; appearance assessed at 12 mo in the 2016 series[12] | Office procedure; no donor; hyaluronidase can dissolve HA | Repeat injections may be needed (26/40 at one month in the 2026 trial); cost; vascular occlusion with tissue necrosis was reported after multisite vulvovaginal HA injection[16][19] |
| Calcium hydroxyapatite (CaHA) | CaHA filler | Small volumes | Improvement assessed at 90 days; longer-term labial duration was not established[13] | Biostimulatory filler; office procedure | In a ten-person randomized comparison with HA, both groups improved at 90 days, but superiority of either filler was not established[13] |
| Dermal fat graft | Autologous dermal-fat block | Surgical block | Stable result reported in a single case[14] | Stable volume reported | Surgical harvest; donor-site scar |
A 2026 single-center randomized study of 76 women aged 40–65 with labia majora hypotrophy compared a cross-linked HA filler (n = 40) with no intervention (n = 36); participants and investigators were unblinded, and allocation concealment was not implemented.[16] At six months, FSFI was 29.3 ± 3.4 in the HA group versus 19.6 ± 8.5 in untreated controls (p < 0.0001), and GAIS ratings favored HA (p < 0.0001); the Motakef labial-proportion category did not change significantly in either group. No serious adverse events occurred in this 76-patient study with six-month follow-up.[16] A 2025 prospective, manufacturer-funded, uncontrolled nine-center HA series treated 72 women; 65/67 rated their appearance improved at 12 weeks, and improvement persisted among available respondents at 52 weeks. Touch-ups occurred in 36/72 at four weeks and treatment-related adverse events in 11/72, including injection-site pain, induration, and inflammation lasting 130, 93, and 64 days, respectively, in three patients; the study did not measure retained volume or compare HA with fat.[21] Fat grafting has not been compared with fillers in a randomized trial.
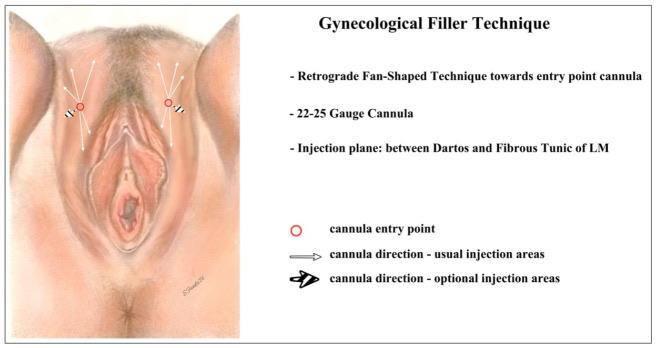
Minimum effective dose (MED) technique for hyaluronic acid augmentation of the labia majora, used in the 2026 randomized study: one cannula entry point on each side, retrograde fan-shaped injection toward the entry point with a 22–25 gauge cannula, and an injection plane between the dartos and the fibrous tunic of the labia majora; arrows mark the usual and optional injection areas. Original drawing by E. Fasola. From Fasola E, et al. Life (Basel). 2026;16(7):1141, Figure 2 (CC BY).[16]
Combined approaches
- Fat grafting and conservative labiaplasty (Hersant 2018). Augmenting the majora masks the minora, which allows a more conservative labia minora reduction (n = 21; no comparison group).[5]
- 360 Vaginal Beautification (Cihantimur 2021). Labia majora fat grafting and vaginal tightening using SVF-enriched fat.[3]
- "Genital beautification" concept (Cihantimur 2013). Labia minora reduction, labia majora fat augmentation, labial brightening by laser, and mons-pubis liposuction, with or without vaginal tightening (95.2% "happy" at 1 yr).[8]
- Surgical and non-surgical (Toplu 2021). Labiaplasty with fat injection to the mons / labia majora as indicated and fractional CO₂ laser; 33/37 were satisfied or very satisfied with postoperative appearance at 1 year (89.2% by calculation; article reports an inconsistent 94.5%).[10]
- Microfat and nanofat (Menkes 2021). In women with GSM, microfat was placed in the labia majora for volume and nanofat in the vagina; this uncontrolled series did not isolate either component's clinical effect or measure tissue regeneration.[2]
Special population — gender-affirming surgery
In Patel's retrospective single-surgeon series, 6/182 patients received labial fat grafting after penile inversion vaginoplasty, always during another revision; flattened labia majora was the indication in five of six. The authors described grafting as safe and effective in this setting, but outcomes of isolated labial grafting were not measured. Grafted patients were more likely to have had introital stenosis (33% versus 6%, p = 0.007) and granulation tissue persisting > 6 weeks (83% versus 32%, p = 0.01) after initial vaginoplasty; the authors suggested these features may predict grafting need and proposed scarring and contracture as a possible explanation.[7]
Limitations
- ACOG 2020: the lack of high-quality data limits conclusions about the effectiveness of genital cosmetic procedures, including labia majora augmentation.[4]
- No randomized trials compare fat grafting with other augmentation methods.[1]
- Only 2 of 9 studies in the Jabbour review were prospective.[1]
- No standardized approach or consensus guideline exists for labia majora augmentation.[1]
- Volumetric retention has not been measured by MRI or ultrasound in a published series.
- Patients should be counseled about possible repeat sessions and the unpredictability of fat-graft survival.
- ACOG advises BDD assessment when indicated before surgery.[4]
Postoperative management
- Activity restriction. Set activity limits according to recipient-site healing and any concurrent procedure. With concurrent labiaplasty, a published postoperative protocol avoids tampons and intercourse for four weeks after trim and up to six weeks after wedge; high-impact exercise is delayed to six weeks.[22] Protect the donor site per general lipofilling protocol.
- Wound care. Ice 48–72 h; loose-fitting clothing.
- Compression / pressure at the donor site; avoid pressure on the recipient site so as not to compress the graft.
- Follow-up. 1 week (donor and recipient sites), 6 weeks, 6 months, 12 months, with FGSIS / FSFI / VHI / FSD as relevant to indication.
- Counseling on durability. Fat resorption can occur, and a second session may be needed for the desired volume.
See Also
- Female Cosmetic Genital Surgery (umbrella)
- Trim (Edge / Linear) Resection Labiaplasty
- Central Wedge Resection Labiaplasty
- Foundations — V-Y Advancement Flap
References
1. Jabbour S, Kechichian E, Hersant B, et al. Labia majora augmentation: a systematic review of the literature. Aesthet Surg J. 2017;37(10):1157–1164. doi:10.1093/asj/sjx056
2. Menkes S, SidAhmed-Mezi M, Meningaud JP, et al. Microfat and nanofat grafting in genital rejuvenation. Aesthet Surg J. 2021;41(9):1060–1067. doi:10.1093/asj/sjaa118
3. Cihantimur B, Aglamis O, Ozsular Y. 360 genital fat transfer. Aesthet Plast Surg. 2021;45(6):2996–3002. doi:10.1007/s00266-021-02488-w
4. Committee on Gynecologic Practice, American College of Obstetricians and Gynecologists. Elective female genital cosmetic surgery: ACOG Committee Opinion No. 795. Obstet Gynecol. 2020;135(1):e36–e42. doi:10.1097/AOG.0000000000003616
5. Hersant B, Jabbour S, Noel W, et al. Labia majora augmentation combined with minimal labia minora resection: a safe and global approach to the external female genitalia. Ann Plast Surg. 2018;80(4):323–327. doi:10.1097/SAP.0000000000001435
6. Vogt PM, Herold C, Rennekampff HO. Autologous fat transplantation for labia majora reconstruction. Aesthet Plast Surg. 2011;35(5):913–915. doi:10.1007/s00266-011-9664-5
7. Patel V, Morrison SD, Gujural D, Satterwhite T. Labial fat grafting after penile inversion vaginoplasty. Aesthet Surg J. 2021;41(3):NP55–NP64. doi:10.1093/asj/sjaa431
8. Cihantimur B, Herold C. Genital beautification: a concept that offers more than reduction of the labia minora. Aesthet Plast Surg. 2013;37(6):1128–1133. doi:10.1007/s00266-013-0211-4
9. Lai YW, Wu SH, Chou PR, et al. Autologous fat grafting in female genital area improves sexual function by increasing collagenesis, angiogenesis, and estrogen receptors. Aesthet Surg J. 2023;43(8):872–884. doi:10.1093/asj/sjad040
10. Toplu G, Altinel D. Genital beautification and rejuvenation with combined use of surgical and non-surgical methods. Aesthet Plast Surg. 2021;45(2):758–768. doi:10.1007/s00266-020-01980-z
11. Kim JH, Kim SE, Kim YJ, Kim YW, Cheon YW. Comparison of volume retention and biocompatibility of acellular dermal matrix/hyaluronic acid filler to autologous fat grafts in a mouse model. Aesthet Plast Surg. 2020;44(3):986–992. doi:10.1007/s00266-020-01680-8
12. Fasola E, Gazzola R. Labia majora augmentation with hyaluronic acid filler: technique and results. Aesthet Surg J. 2016;36(10):1155–1163. doi:10.1093/asj/sjw083
13. Vilela CL, de Lima Faria GE, Boggio RF. Treatment of atrophy of the labia majora: calcium hydroxyapatite or hyaluronic acid? Aesthet Plast Surg. 2024;48(3):472–477. doi:10.1007/s00266-023-03617-3
14. Salgado CJ, Tang JC, Desrosiers AE. Use of dermal fat graft for augmentation of the labia majora. J Plast Reconstr Aesthet Surg. 2012;65(2):267–270. doi:10.1016/j.bjps.2011.07.010
15. Capito L, Antsaklis A, Gupte S; FIGO Committee on Ethical Aspects of Human Reproduction and Women's Health. FIGO statement: cosmetic genital surgery. Int J Gynaecol Obstet. 2025;170(1):11–14. doi:10.1002/ijgo.70203
16. Fasola E, Dridi D, Degliuomini RS, et al. Performance and safety of hyaluronic acid-based gynaecological filler for labia majora augmentation: a randomised controlled study. Life (Basel). 2026;16(7):1141. doi:10.3390/life16071141
17. El Danaf AA. "Labia majora lipofilling during body contouring: complications." Aesthetic Plast Surg. 2026;50(15):6141–6149. doi:10.1007/s00266-026-05920-1
18. Baser RE, Li Y, Carter J. "Psychometric validation of the Female Sexual Function Index (FSFI) in cancer survivors." Cancer. 2012;118(18):4606–4618. doi:10.1002/cncr.26739
19. Lin P, Zhou G, Li G, et al. "Superselective internal pudendal artery thrombolytic therapy combined with concentrated growth factor for hyaluronic acid embolization after vulvovaginal rejuvenation: a case report and review of literature." Aesthetic Plast Surg. 2026;50(7):2814–2822. doi:10.1007/s00266-025-05184-1
20. Kaufman MR, Ackerman AL, Amin KA, et al. "The AUA/SUFU/AUGS Guideline on Genitourinary Syndrome of Menopause." J Urol. 2025;214(3):242–250. doi:10.1097/JU.0000000000004589. Full guideline
21. Boucher F, Eychenne C, Gurriet B, et al. "Evaluation of the Efficacy and Safety of Hyaluronic Acid Injection for Volume Restoration of the Labia Majora: ESOLANE study." Int Urogynecol J. 2025;36(6):1243–1253. doi:10.1007/s00192-025-06094-1
22. Furnas HJ, Canales FL, Pedreira RA, Comer C, Lin SJ, Banwell PE. "The Safe Practice of Female Genital Plastic Surgery." Plast Reconstr Surg Glob Open. 2021;9(7):e3660. doi:10.1097/GOX.0000000000003660