Polylactic Acid Filler — Penile Girth Augmentation
Polylactic acid (PLA) filler is a biostimulatory injectable used for penile girth enhancement. Unlike hyaluronic acid (HA), which gives immediate volume, PLA is proposed to induce endogenous neocollagenesis, producing a more gradual augmentation that may last longer.[1][2] It is the second most studied injectable filler for penile augmentation after HA, with the most rigorous comparative data from a series of multicenter RCTs.[3][4][5] For positioning versus other male cosmetic options see Cosmetic Genital Surgery — Male.
Society positioning. The SMSNA 2024 expert-opinion statement describes limited evidence of possible cosmetic benefit with temporary HA and PLA fillers, urges IRB-approved safety and efficacy analyses when they are offered, and strongly recommends against permanent filler materials.[23] It also states that body dysmorphic disorder must be ruled out before invasive treatments.[23] For adults without structural or functional penile abnormalities, the 2026 BAUS consensus recommends against absorbable fillers because high-quality supporting evidence is absent.[32] The 2026 EAU guideline weakly recommends soft-tissue fillers for penile girth enhancement in selected men but strongly recommends against their use in men with penile dysmorphic disorder.[33] Sculptra (PLA filler) is FDA-approved for HIV-associated facial lipoatrophy and certain facial wrinkles; penile use is off-label.[27][28]
Mechanism — biostimulatory vs volumetric
PLA is a synthetic, biocompatible, biodegradable polymer that functions as a biostimulatory scaffold rather than a conventional space-filling filler.[2][6]
Dermal cell, human 3D skin-model and aged-animal skin studies suggest the following responses to PLA formulations.[7][6][8][2]
- Subclinical foreign body response. PLA microparticles elicit a controlled inflammatory tissue response with M2 macrophage polarization.
- Fibroblast activation. Macrophage-mediated upregulation of TGF-β1, TGF-β2, IL-1β, and CXCL6 activates resident fibroblasts.
- Neocollagenesis. Stimulated fibroblasts produce type I and type III collagen, creating new volume through autologous tissue rather than exogenous material.
- Gradual degradation. PLA microparticles metabolized to CO₂ and H₂O via the Krebs cycle and expelled through the respiratory system; the newly formed collagen persists.
This mechanism explains the distinct temporal profile: gradual onset of augmentation but potentially longer-lasting results, since the volume is composed of the patient's own collagen rather than an exogenous gel that undergoes enzymatic degradation.[2]
FDA approval and regulatory status
Sculptra (poly-L-lactic acid) was FDA-approved in 2004 for HIV-associated facial lipoatrophy and in 2009 for cosmetic correction of nasolabial-fold contour deficiencies and other facial wrinkles in immunocompetent patients.[9][10][11][27][28] The 18-month penile RCT used PowerFill, a different PLA formulation; penile use has no US FDA indication.[5] In facial applications, therapeutic effects last approximately 2 years.[10][12]
Clinical evidence
The penile-PLA evidence includes a 23-man prospective series and four multicenter, patient- and evaluator-blinded HA-versus-PLA RCTs, three led by Yang and one by Ahn.[1][25]
Yang 2017 — foundational PLA monotherapy
23 healthy men, mean injected volume 20 mL.[1]
- Proximal, mid- and distal-shaft circumference increased by mean +2.2, +2.7, +2.7 cm at 3 months (each p < 0.001).[1]
- Among 21 of 23 men assessed at 18 months, mean girth remained above baseline; the 3-to-18-month difference was not statistically significant (p > 0.05).[1]
- VAS satisfaction rose from 51.6 at baseline to 64.8 at 3 months and 74.3 at 6 months (each p < 0.05).
- Six mild, transient adverse events occurred in 5 subjects; no serious adverse events were reported.
Head-to-head RCTs vs HA
| Trial | n | Follow-up | PLA girth gain | HA girth gain | Between-group | Satisfaction | AE rate (PLA vs HA) |
|---|---|---|---|---|---|---|---|
| Yang 2019 J Sex Med 48-wk RCT[3] | 72 enrolled (41 remained) | 48 wk | +13.49 mm (p < 0.001) | +16.95 mm (p < 0.001) | HA > PLA at 4 wk (p < 0.001); NS at 48 wk (p = 0.075) | comparable (p > 0.05) | 8.3% vs 2.8% |
| Yang 2020 J Sex Med 24-wk RCT[4] | 74 | 24 wk | +1.6 cm (p < 0.001) | +2.1 cm (p < 0.001) | HA > PLA (0.5 cm, p = 0.031) | appearance: between-group p = 0.950; sexual life: between-group p = 0.287 | 14.3% vs 5.1% (p = 0.245) |
| Yang 2020 J Clin Med 18-mo RCT[5] | 67 injected (46 assessed at 18 mo) | 18 mo | significant (p < 0.001) | significant (p < 0.001) | NS during entire study period | between-group appearance p = 0.114 and sexual-performance p = 0.154 at 18 mo; appearance p = 0.028 at 3 mo | 5.9% vs 9.1% |
| Ahn 2022 World J Mens Health 24-wk RCT[34] | 74 randomized (64 completed) | 24 wk | +20.23 ± 8.73 mm | +22.74 ± 12.60 mm | No significant between-group girth difference | Sexual-life satisfaction differed at 12 wk (p = 0.0143), not 24 wk (p = 0.3608) | 9.4% (3/32) vs 6.3% (2/32) |
Key comparative findings
- Early augmentation: HA > PLA at 4 weeks (p < 0.001); HA's volumetric effect is immediate while PLA's collagen-stimulating mechanism is gradual.[3]
- Convergence over time: the difference narrowed and was no longer significant at 48 weeks (p = 0.075). Resorption of HA and gradual collagen stimulation by PLA are the proposed explanations; neither was measured.[3]
- At 18 months: both fillers maintained augmentation above baseline in one RCT, with no statistically significant between-group girth difference.[5] A 2023 meta-analysis of four small trials (283 participants) found greater pooled girth gain with HA; pain and inflammation rates did not differ significantly.[25]
- Satisfaction. The 24-week RCT found no between-group difference in changes from baseline in appearance or sexual-life satisfaction, or in Beliefs about Penis Size Scale scores, at 24 weeks.[4] In the 18-month RCT, the change from baseline in appearance satisfaction differed between groups at 3 months (p = 0.028), but not at 18 months (p = 0.114); PLA appearance satisfaction declined from 6 to 18 months (p = 0.039), with 46/67 assessed at 18 months.[5] A four-trial meta-analysis found greater sexual satisfaction with HA at 12 weeks (p = 0.0004).[25]
- Psychological benefits: both fillers significantly reduced BPSS scores (5.3–7.8 points, p < 0.05).[4]
Durability — comparative evidence through 18 months
Durability is the proposed distinction between PLA and HA, and the penile data do not yet confirm it beyond 18 months:
- PLA: a 23-man prospective series (21 assessed at 18 months) and a separate 67-man RCT (46 assessed at 18 months) followed penile girth through 18 months.[1][5] In the RCT, mean gain declined by 0.51 cm (22.1%) from its 1-month peak; this within-group change was not statistically significant (p = 0.123), and 46/67 participants completed 18-month follow-up.[5]
- HA: flaccid girth gain peaked at 1 month and progressively attenuated, retaining approximately 70–75% of that peak gain at 12 months among 38 completers.[13]
By the proposed biostimulatory mechanism, newly formed collagen persists after the PLA microparticles degrade. Facial-application data report PLLA effects lasting up to 2 years or longer.[12][14] Whether this same durability extends beyond 18 months in penile tissue is unknown; no longer-term penile-augmentation data exist.
Safety
Adverse-event rates after penile PLA injection were similar to HA in the randomized trials.[4][5][3][1]
- PLA injection-related AE rates were 5.9–14.3% across four RCTs with 24-week to 18-month follow-up; reported events were mild, but two PLA recipients in one 24-week trial still had AEs at trial end.[3][4][5][25]
- No serious adverse events were reported in the randomized trials through 18 months; a later three-case penile PLA-based-filler report described delayed granulomas, with surgical excision in 2/3 patients.[5][24]
- No statistically significant difference in AE rates versus HA (p = 0.245).[4]
Reported AEs in penile PLA injection
- Injection-site discomfort / pain.
- Transient edema.
- Subcutaneous nodules may be palpable without being visible; contour deformity has also been observed. A 2025 nonrandomized, single-surgeon cohort reported nodules or penile deformities at 24 weeks in 7/134 PLA recipients (5.2%), 2/125 HA recipients (1.6%), and 3/42 PMMA recipients (7.2%); the three-group comparison was not significant (p = 0.107).[35]
- Bruising.
Considerations from facial-PLA literature (potentially applicable)
- Papules and nodules. Most commonly discussed PLA-specific complication. In facial applications, arise several weeks after injection, generally palpable but non-visible, typically resolve spontaneously. Result from suboptimal product reconstitution or placement; minimized by improved technique.[15]
- True inflammatory granulomas. A 2014 review quoted 0.01–0.1% for true inflammatory granulomas after injectable PLLA.[15] The review describes these reactions as potentially systemic; they may appear months to years after injection and may persist or grow.[15] Treatment: intralesional steroids and antimetabolites (5-fluorouracil).[15][16]
- Late-onset immune-mediated reactions. Alijotas-Reig 2009 case series of 10 non-HIV patients: mean latency 19.2 months (range 6–60) to onset of delayed adverse effects (tender inflammatory nodules, facial edema). After a mean 50.2 months of follow-up (range 38–78): 5/10 in remission, 4/10 with recurrent episodes, and 1/10 lost to follow-up.[16]
- Wortsman 2025 international ultrasound study. Among 240 selected patients with ultrasound-confirmed filler granulomas, 18.8% had received PLLA (versus 50.4% HA).[17]
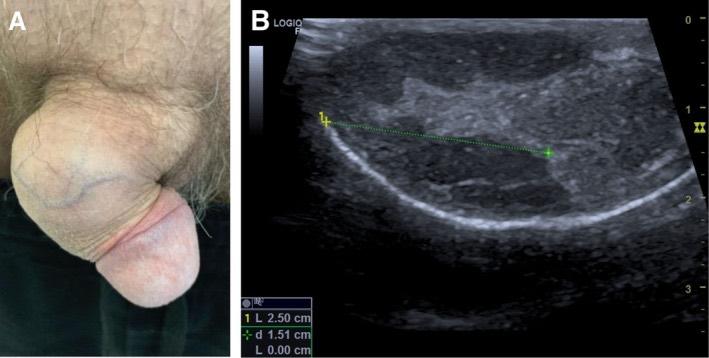
Foreign-body granuloma after polylactic acid filler injection for penile girth enhancement: (A) dorsolateral subcutaneous granuloma in the middle third of the penile shaft; (B) ultrasound image of the lesion. From Boiko M, et al. Clin Case Rep. 2025;13(8):e70811, Figure 1 (CC BY 4.0).[24]
Non-reversibility: distinction from HA. Unlike HA (which can be dissolved with hyaluronidase), PLA cannot be enzymatically reversed.[15] If nodules, asymmetry, or overcorrection occur, management options are limited to observation, intralesional corticosteroids, 5-fluorouracil, or surgical excision.[15][18] Non-reversibility makes precise injection technique and patient selection more important for PLA than for HA.[2] Final result is not fully apparent until weeks to months after injection.[2]
Injection technique
The specific PLA injection technique for penile augmentation is less well-described than for HA. General principles from the RCTs and facial-application literature[4][3][1]:
- Volume: mean approximately 20 mL.[1]
- Plane: In the 18-month PowerFill RCT, filler was placed between the dartos and Buck's fascia by fanning from penile-base entry sites.[5]
- Reconstitution. PowerFill is supplied as a powder; the 18-month penile RCT reconstituted it with 7 mL of saline immediately before injection.[5] Facial Sculptra sources discuss higher-volume dilution and hydration before injection for that formulation.[19][20]
- Post-injection care: the cited 2014 facial PLLA consensus recommends massaging the injected area for a few minutes after treatment and leaves continued self-massage to physician discretion.[9] A separate 2023 facial PLLA consensus describes optional “5-5-5” self-massage (5 minutes, 5 times daily, for 5 days).[26] The 18-month penile RCT instructed gentle shaft massage, an elastic support bandage for one day, and abstinence from intercourse for one month.[5]
- Treatment sessions: facial PLA is often administered over 2–4 sessions spaced 4–6 weeks apart to allow gradual collagen buildup and avoid overcorrection. The penile-augmentation studies used a single injection session.[9][19][1]
PLA vs HA — comparative summary
| Feature | PLA | HA |
|---|---|---|
| Mechanism | Biostimulatory (neocollagenesis) | Volumetric (space-filling) |
| Onset | Gradual (weeks to months) | Immediate |
| Peak girth gain | +1.3–2.7 cm | +1.7–3.4 cm |
| Early augmentation (4 wk) | Less than HA (p < 0.001) | Greater than PLA |
| Girth gain at 48 weeks and 18 months | No statistically significant difference from HA in separate trials; superior durability was not established[3][5] | No statistically significant difference from PLA in those trials[3][5] |
| Durability | No significant 3-to-18-mo girth difference in a 23-man PLA series; in an RCT, mean gain declined 22.1% from 1 to 18 mo (p = 0.123; 46/67 assessed at 18 mo)[1][5] | Among 38 HA completers, 12-mo flaccid girth gain was 2.44/3.41 cm (~72%) of the 1-mo gain[13] |
| Reversibility | Not reversible | Reversible with hyaluronidase |
| Injection-related AE rate across three RCTs (24 wk–18 mo) | 5.9–14.3% (reported events mild)[3][4][5] | 2.8–9.1% (reported events mild)[3][4][5] |
| Nodule / granuloma risk | Delayed penile granulomas have been reported; comparative risk is uncertain[24] | Comparative risk versus PLA is uncertain |
| Satisfaction | Comparable to HA | Comparable to PLA |
| FDA-approved indication | HIV-associated facial lipoatrophy and certain facial wrinkles (penile use off-label)[29][30] | Varies by HA product; includes specified facial uses (penile use off-label)[31] |
Limitations of current evidence
- Single research group. Nearly all penile-PLA data come from Yang et al., limiting generalizability.[3][4][5][1]
- High dropout rates. Up to 43.1% in the 48-week RCT.[3]
- No data beyond 18 months for penile augmentation; the theoretical advantage of longer durability remains unproven in this specific application.[5]
- No standardized penile injection protocol. Reconstitution volumes, dilution ratios, and injection techniques are not standardized for penile use.[21]
- Nodule or granuloma risk in penile tissue is unknown. Penile tissue has unique biomechanical properties (repeated stretching, compression, friction) that may affect PLA microparticle behavior differently than facial tissue.
- Non-reversibility limits the safety margin compared to HA, particularly in an off-label application without established guidelines.
- Overall low quality of evidence. Manfredi 2022 narrative review noted 89.7% of penile-girth-enhancement studies are not RCTs.[22]
Where PLA fits — clinical decision-making
Patient selection. Exclude penile dysmorphic disorder before invasive augmentation; the 18-month PLA trial also excluded men with body dysmorphic disorder.[23][5] In eligible men, PLA may be considered when they:
- Understand that comparative durability remains uncertain: in one RCT, the loss of peak girth gain from 1 to 18 months was 22.1% with PLA versus 43.6% with HA (p = 0.015), but the change in mean flaccid girth from baseline did not differ significantly between groups at 18 months and retreatment was not studied.[5]
- Accept the gradual onset of augmentation (weeks to months rather than immediate).
- Understand and accept non-reversibility.
HA may be chosen when patients:
- Desire immediate visible results.
- Value the safety net of reversibility with hyaluronidase.
- Are undergoing penile augmentation for the first time and wish to "trial" the effect before committing to a non-reversible option.
In the 18-month randomized trial, both fillers increased girth and satisfaction; the between-group girth difference at 18 months was not statistically significant, adverse events were mild, and no serious adverse events were reported.[5] A separate randomized trial followed men for 24 weeks.[4]
See Also
HA Filler — Penile Girth Augmentation · Cosmetic Genital Surgery — Male · Small Penis Syndrome / PDD · Penile Traction Therapy · Vacuum Erection Device
References
1. Yang DY, Ko K, Lee SH, et al. Efficacy and safety of a newly developed polylactic acid microsphere as an injectable bulking agent for penile augmentation: 18-months follow-up. Int J Impot Res. 2017;29(4):136-141. doi:10.1038/ijir.2017.10
2. Vleggaar D, Fitzgerald R, Lorenc ZP. Composition and mechanism of action of poly-L-lactic acid in soft tissue augmentation. J Drugs Dermatol. 2014;13(4 Suppl):s29-31. PMID 24719074
3. Yang DY, Ko K, Lee SH, Lee WK. A comparison of the efficacy and safety between hyaluronic acid and polylactic acid filler injection in penile augmentation: a multicenter, patient/evaluator-blinded, randomized trial. J Sex Med. 2019;16(4):577-585. doi:10.1016/j.jsxm.2019.01.310
4. Yang DY, Jeong HC, Ahn ST, et al. A comparison between hyaluronic acid and polylactic acid filler injections for temporary penile augmentation in patients with small penis syndrome: a multicenter, patient/evaluator-blind, comparative, randomized trial. J Sex Med. 2020;17(1):133-141. doi:10.1016/j.jsxm.2019.10.006
5. Yang DY, Jeong HC, Ko K, et al. Comparison of clinical outcomes between hyaluronic and polylactic acid filler injections for penile augmentation in men reporting a small penis: a multicenter, patient-blinded/evaluator-blinded, non-inferiority, randomized comparative trial with 18 months of follow-up. J Clin Med. 2020;9(4):1024. doi:10.3390/jcm9041024
6. Haykal D, Haddad A, Cartier H, Avelar L. Poly-L-lactic acid in aesthetic dermatology: a decade beyond volume restoration toward regenerative biostimulation. Aesthet Surg J. 2025;sjaf121. doi:10.1093/asj/sjaf121
7. Oh S, Seo SB, Kim G, et al. Poly-D,L-lactic acid filler increases extracellular matrix by modulating macrophages and adipose-derived stem cells in aged animal skin. Antioxidants (Basel). 2023;12(6):1204. doi:10.3390/antiox12061204
8. Huth S, Huth L, Marquardt Y, et al. Molecular insights into the effects of PLLA-SCA on gene expression and collagen synthesis in human 3D skin models containing macrophages. J Drugs Dermatol. 2024;23(4):285-288. doi:10.36849/JDD.7791
9. Vleggaar D, Fitzgerald R, Lorenc ZP, et al. Consensus recommendations on the use of injectable poly-L-lactic acid for facial and nonfacial volumization. J Drugs Dermatol. 2014;13(4 Suppl):s44-51. PMID 24719078
10. Jabbar A, Arruda S, Sadick N. Off face usage of poly-L-lactic acid for body rejuvenation. J Drugs Dermatol. 2017;16(5):489-494. PMID 28628686
11. Simamora P, Chern W. Poly-L-lactic acid: an overview. J Drugs Dermatol. 2006;5(5):436-440. PMID 16703779
12. Butterwick K, Lowe NJ. Injectable poly-L-lactic acid for cosmetic enhancement: learning from the European experience. J Am Acad Dermatol. 2009;61(2):281-293. doi:10.1016/j.jaad.2008.11.881
13. Zhang CL, Quan Y, Li H, et al. Penile augmentation with injectable hyaluronic acid gel: an alternative choice for small penis syndrome. Asian J Androl. 2022;24(6):601-606. doi:10.4103/aja20223
14. Brandt FS, Cazzaniga A, Baumann L, et al. Investigator global evaluations of efficacy of injectable poly-L-lactic acid versus human collagen in the correction of nasolabial fold wrinkles. Aesthet Surg J. 2011;31(5):521-528. doi:10.1177/1090820X11411161
15. Vleggaar D, Fitzgerald R, Lorenc ZP. Understanding, avoiding, and treating potential adverse events following the use of injectable poly-L-lactic acid for facial and nonfacial volumization. J Drugs Dermatol. 2014;13(4 Suppl):s35-9. PMID 24719076
16. Alijotas-Reig J, Garcia-Gimenez V, Vilardell-Tarres M. Late-onset immune-mediated adverse effects after poly-L-lactic acid injection in non-HIV patients: clinical findings and long-term follow-up. Dermatology. 2009;219(4):303-308. doi:10.1159/000243804
17. Wortsman X, Valderrama Y, Ortiz-Orellana G, et al. International multicentric study on ultrasound characteristics, layer location, and corporal distribution of granulomas after cosmetic fillers injections. J Ultrasound Med. 2025;44(8):1447-1455. doi:10.1002/jum.16700
18. O'Daniel G. Management of late-onset, recurrent facial nodular reaction after poly-L-lactic (PLLA) injections. J Drugs Dermatol. 2017;16(12):1297-1299. PMID 29240867
19. Lam SM, Azizzadeh B, Graivier M. Injectable poly-L-lactic acid (Sculptra): technical considerations in soft-tissue contouring. Plast Reconstr Surg. 2006;118(3 Suppl):55S-63S. doi:10.1097/01.prs.0000234612.20611.5a
20. Bartus C, William Hanke C, Daro-Kaftan E. A decade of experience with injectable poly-L-lactic acid: a focus on safety. Dermatol Surg. 2013;39(5):698-705. doi:10.1111/dsu.12128
21. Salloum A, Bazzi N, Haber R. Nonsurgical methods for penile augmentation: a systematic review. Dermatol Surg. 2021;47(3):e81-e85. doi:10.1097/DSS.0000000000002816
22. Manfredi C, Romero Otero J, Djinovic R. Penile girth enhancement procedures for aesthetic purposes. Int J Impot Res. 2022;34(4):337-342. doi:10.1038/s41443-021-00459-y
23. Trost L, Khera M, Köhler T, et al. Cosmetic penile enhancement procedures: an SMSNA position statement. J Sex Med. 2024;21(6):573–578. doi:10.1093/jsxmed/qdae045
24. Boiko M, Boiko O, Pasyechnikov S, Notsek M. Foreign body granuloma after polylactic acid filler injection for penile girth enhancement: three cases report. Clin Case Rep. 2025;13(8):e70811. doi:10.1002/ccr3.70811
25. Kusumaputra A, Setiawan MR, Soebadi MA, Wirjopranoto S. "Efficacy and complications of hyaluronic acid and polylactic acid for penile augmentation: a systematic review and meta-analysis." Ann Med Surg (Lond). 2023;85(9):4531-4538. doi:10.1097/MS9.0000000000001094
26. Avelar L, Ong A, Ong D, et al. "Consensus recommendations on the use of injectable poly-l-lactic acid in Asian patients." J Cosmet Dermatol. 2023;22(12):3223-3231. doi:10.1111/jocd.15969
27. U.S. Food and Drug Administration. "Sculptra: PMA P030050." 2004. FDA approval
28. U.S. Food and Drug Administration. "Sculptra Aesthetic: PMA supplement P030050/S002." 2009. FDA approval
29. U.S. Food and Drug Administration. "Sculptra: PMA P030050." 2004. FDA approval
30. U.S. Food and Drug Administration. "Sculptra Aesthetic: PMA supplement P030050/S002." 2009. FDA approval
31. U.S. Food and Drug Administration. "Dermal Fillers (Soft Tissue Fillers)." FDA guidance
32. Mubarak M, Kalejaiye O, Kumar V, et al. "British Association of Urological Surgeons (BAUS) consensus document on male genital augmentation and enhancement procedures." J Clin Urol. 2026;19(2):149-166. doi:10.1177/20514158251391054
33. European Association of Urology. "Penile Size Abnormalities and Dysmorphophobia." EAU Guidelines on Sexual and Reproductive Health. 2026. Guideline
34. Ahn ST, Shim JS, Bae WJ, Kim SW, Kim JJ, Moon DG. "Efficacy and safety of penile girth enhancement using hyaluronic acid filler and the clinical impact on ejaculation: a multi-center, patient/evaluator-blinded, randomized active-controlled trial." World J Mens Health. 2022;40(2):299-307. doi:10.5534/wjmh.210007
35. Kim DW, Jeong HC, Ko K, et al. "Which dermal filler is better for penile augmentation for aesthetic purposes? A prospective, single-surgeon study based on real-world experience." World J Mens Health. 2025;43(2):428-436. doi:10.5534/wjmh.240105