Reduction Scrotoplasty (Scrotal Lift / Tuck)
Reduction scrotoplasty is a surgical procedure that removes excess scrotal skin to reduce scrotal laxity, improve genital cosmesis, and, when penoscrotal webbing is corrected concurrently, enhance the perceived penile length by exposing the ventral penile shaft. The aesthetic application is poorly addressed in the international literature. A systematic review of aesthetic scrotoplasty identified only 11 eligible articles, most of them case reports or technique descriptions.[1][2]
For the broader male cosmetic-genital-surgery decision framework see the Male Cosmetic Genital Surgery atlas page. For reconstructive scrotoplasty (Fournier's, lymphedema, oncologic resection, hidradenitis suppurativa, buried penis) see Scrotal Reconstruction.
I. Definition and Terminology
The term "scrotoplasty" encompasses a broad range of procedures with inconsistent nomenclature.[1][2]
- Reduction scrotoplasty / scrotal reduction. Excision of excess scrotal skin to reduce scrotal size and laxity.
- Scrotal lift / scrotal tuck. Colloquial terms for aesthetic reduction scrotoplasty.
- Scrotopexy. Fixation of the scrotum in a more superior position, sometimes combined with skin excision.
- Ventral phalloplasty. Correction of penoscrotal webbing at the ventral penile-scrotal junction; often performed concurrently with or as part of a scrotoplasty.
- Scrotectomy. Partial or total excision of scrotal skin, typically used in pathological contexts (lymphedema, malignancy, Fournier's gangrene) rather than cosmetic surgery.
The distinction between aesthetic scrotoplasty (cosmetic) and reconstructive scrotoplasty (pathological) is important. Indications, techniques, and evidence base differ substantially.[2]
II. Indications
A. Aesthetic / cosmetic indications[1][2][3]
- Scrotal laxity / scrotomegaly. An enlarged, pendulous scrotal sac that hangs > 1–2 cm below the tip of the penis, causing discomfort or dissatisfaction. Poorly defined entity with no standardized diagnostic criteria.[1]
- Penoscrotal webbing (scrotal web). A web of scrotal skin extending onto the ventral penile shaft, creating a "tethered" appearance that shortens visible penile length and can interfere with condom use and sexual function.[1][4][5]
- Age-related scrotal ptosis. Progressive loss of scrotal-skin elasticity with aging, analogous to facial-skin laxity.
- Genital rejuvenation. Increasingly sought as part of comprehensive male aesthetic genital surgery, often combined with penile augmentation or suprapubic lipectomy.[3]
- Adolescent genital dissatisfaction. In a selected cohort of 98 adolescents undergoing genital surgery, webbed penis (41/98) and penile curvature (39/98) were most common; concealed penis occurred in 11/98. Genital self-evaluation improved at three months after surgery.[4]
B. Functional / medical indications[1][2]
- Discomfort while wearing loose clothing, walking, exercising, or during intercourse from excessive scrotal skin.
- Recurrent scrotal dermatitis or intertrigo from skin-on-skin contact.
- Hygiene difficulties related to redundant scrotal tissue.
C. Combined with penile prosthesis implantation[5][6][7][8]
Scrotoplasty, including penoscrotal-web release, has been described during penile-prosthesis implantation. Miranda-Sousa's web-release cohort included 39 inflatable and four semirigid implants.[5][6] Reported aims include:
- Correct penoscrotal webbing that obscures the ventral penile shaft.
- Improve the patient's perception of penile length. In Miranda-Sousa's 2007 series, 84% of 43 patients who underwent ventral phalloplasty (penoscrotal-web release) at the time of implant surgery reported some increase in penile length. In a comparison group of 37 implant patients without web release, 84% complained of shortening.[5]
- Optimize the cosmetic result of the prosthesis by creating a more defined penoscrotal junction.
D. Reconstructive indications (out of scope for this page)[2][9][10][11]
- Fournier's gangrene: post-debridement scrotal reconstruction.
- Scrotal lymphedema (filarial or idiopathic).
- Post-oncologic resection (scrotal malignancy).
- Hidradenitis suppurativa.
- Buried / concealed penis repair.
- Trauma.
For these indications see Scrotal Reconstruction.
III. Relevant Scrotal Anatomy
Understanding scrotal anatomy is necessary for safe reduction scrotoplasty.[2][9]
- Scrotal skin. Thin, rugated, highly elastic, richly vascularized. A review of genital hidradenitis reconstruction describes primary closure after resection of up to 50% of the scrotum.[9]
- Dartos fascia. Smooth muscle and connective tissue beneath scrotal skin; dartos contraction wrinkles the skin. The dartos reflex is distinct from the cremasteric reflex, which contracts the cremaster muscle.[28]
- Scrotal septum (median raphe). Divides the scrotum into two compartments; division of the septum is a useful maneuver for mobilizing tissue during closure of large defects.[9]
- Tunica vaginalis. Serous membrane surrounding each testis; serves as a graft bed for split-thickness skin grafts when needed.[9]
- Spermatic cord. Vas deferens, testicular artery, pampiniform plexus, and cremasteric muscle; must be preserved.
- Gubernaculum. Division allows superior mobilization of the testes.[9]
- Blood supply. External pudendal arteries (from femoral) and scrotal branches of the internal pudendal artery provide a dual blood supply, contributing to wound healing and low infection rates.
- Innervation. Anterior scrotal nerves (ilioinguinal, genitofemoral) and posterior scrotal nerves (perineal branch of pudendal).
IV. Surgical Techniques
A. Thomas & Navia algorithm (2021)
A published management algorithm for aesthetic scrotoplasty.[1] A two-component approach based on the specific anatomical problem:
1. For excessive scrotal skin (scrotomegaly / laxity).
- Vertical midline scrotal-skin resection. Elliptical or fusiform excision of redundant skin along the median raphe.
- Thomas and Navia determine the excision amount by a pinch test with the patient standing and the penis flaccid; the >1–2-cm measurement is their proposed description of low-hanging scrotum.[1]
- Closure in layers (dartos fascia and skin) along the midline raphe, concealing the scar in the natural raphe line.
Stepwise operative protocol (vertical midline resection):[1][2][9][23][24][25]
- Positioning and anesthesia. Supine. Thomas and Navia used general or spinal anesthesia for their combined reduction and Z-plasty case.[1] Local anesthesia has been described for other scrotal-content operations by Sharlip and for mixed penile/scrotal procedures by Bal: 97/105 Bal respondents (92.4%) would choose it again.[23][24] Issa used equal parts 1% lidocaine with epinephrine 1:100,000 and 0.25% bupivacaine for bilateral orchiectomy.[25]
- Marking. With the scrotum dependent, identify the median raphe; grasp redundant midline skin and mark an elliptical / fusiform excision centered on the area of maximal redundancy. Thomas and Navia set the amount of scrotal skin and dartos excision with a standing, flaccid-penis pinch test.[1] For concurrent web release, Alter described assessing ventral penile-skin excision with a pharmacologically induced erection to avoid over-resection.[1]
- Incision. Full-thickness vertical midline incision through skin and dartos along the marked ellipse; remain superficial to the scrotal septum and tunica vaginalis.
- Hemostasis. Meticulous electrocautery. The dartos network is highly vascular (paired inferior external pudendal and perineal territories are widely inter-anastomosed).[2]
- Extent of dissection. Thomas and Navia excised marked skin and dartos, then restored the median raphe. Their aesthetic technique did not include septal division, dartos mobilization off the tunica vaginalis, gubernacular division, or spermatic-cord mobilization with orchidopexy; these maneuvers are discussed under Scrotal Reconstruction for diseased or extensive defects.[1][9]
- Closure. In Thomas and Navia's combined reduction and Z-plasty case, the dartos and skin were closed in separate planes with 4-0 absorbable poliglecaprone; the dartos was sutured at the scrotal septum to restore the median raphe.[1]
- Dressing. Compressive supportive garment; remove at 5–7 days. Same-day discharge with early ambulation.
Primary closure after resection of up to about 50% of the scrotum has been described in reconstruction for hidradenitis defects, attributed to native elasticity and the redundant dartos vascular network.[9][29]
2. For penoscrotal webbing.
- Z-plasty at the penoscrotal junction. Designed to break up the linear web, redistribute tissue, and create a more defined angle between penile shaft and scrotum. Thomas and Navia marked 2-cm arms at 60°, adjusted arm length to the extent of the ventral web, and transposed the flaps.[1]
- The Z-plasty lengthens the ventral penile skin while shortening the web, "unmasking" the ventral penile shaft.
3. Combined approach.
- When both scrotomegaly and penoscrotal webbing coexist, both components are performed simultaneously.
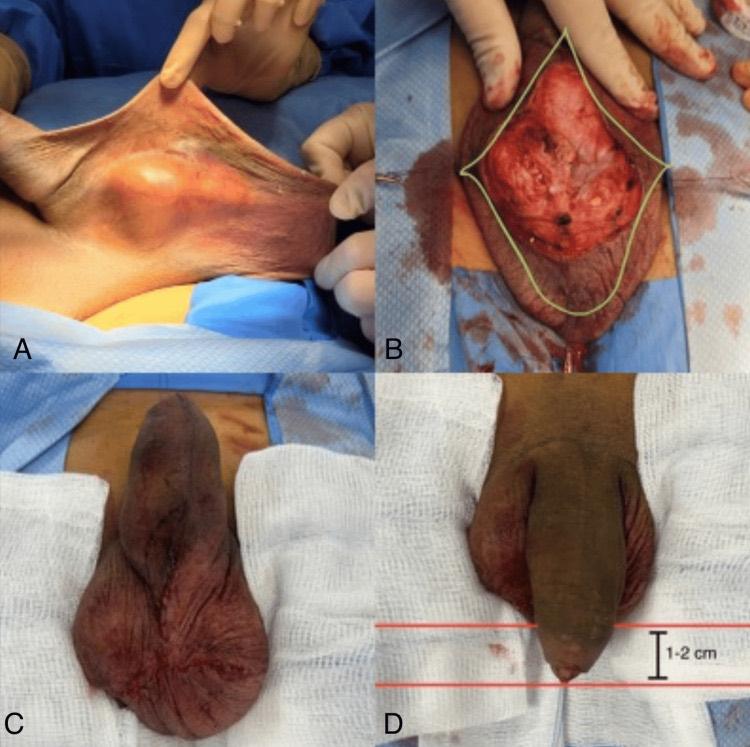
Alternate combined technique (not the Thomas–Navia vertical resection and Z-plasty): Nazario-Perez and colleagues used a modified transverse check-mark incision while preserving dartos. (A) Preoperative laxity and webbing; (B) incision markings; (C, D) immediate postoperative contour, with the glans about 1–2 cm below the inferior scrotal border. From Nazario-Perez MZ, et al. Cureus. 2025;17(2):e79786, Figure 2 (CC BY).[27]
B. Ventral phalloplasty (penoscrotal-web release)[5][7][8]
The most commonly described technique in the context of penile-prosthesis surgery.
- V-Y advancement plasty or Z-plasty at the penoscrotal junction.
- In V-Y plasty, a V-shaped incision at the penoscrotal junction advances the flap distally and closes in a Y configuration, lowering the scrotal insertion point and exposing more ventral shaft. Avoid excess closure tension, which can constrict the penis and cause wound breakdown. For adult-acquired buried penis, the 2026 ICSM consultation advises counseling that these aesthetic procedures may improve apparent flaccid length without increasing girth or erect length .[30]
- A simple transverse elliptical excision of the web with vertical closure is an alternative.
- Adds approximately 12 minutes to operative time when combined with IPP insertion.[5]
C. V-I penoscrotal reconfiguration (Bagnara 2024)[12]
A newer technique specifically for congenital webbed penis.
- V-shaped incision at the penoscrotal junction; the flap is advanced and closed in a linear (I) configuration.
- In a retrospective pediatric series of 21 patients with follow-up assessments scheduled through 12 months, no postoperative complications or repeat operations were reported. Parents gave a satisfaction score of 4 in 17/21 cases (81%).[12]
D. Other described techniques[2][13][14]
- Longitudinal incision with Z-plasty at the penoscrotal junction. Used for concealed-penis correction; the Z-plasty opens the degloving dead cavity for drainage.[13]
- Combined dorsal + ventral phalloplasty. Used with suspensory-ligament release and penile prosthesis for maximal length perception.[15]
- Tissue expansion followed by V-Y scrotoplasty. Two-stage technique for scrotal reconstruction after extensive skin loss; tissue expanders generate additional scrotal skin before definitive scrotoplasty.[16]
V. Scrotoplasty Combined With Penile Prosthesis — Outcomes and Complications
A 2023 NSQIP analysis identified 234 standalone scrotoplasty-coded operations in cisgender and transgender patients, but did not identify an isolated aesthetic-reduction subgroup or report the exact operative approach.[32] The IPP-associated series below comprised 103 operations.[6]
Gupta 2019 (n = 103) — IPP-associated scrotoplasty wound outcomes[6]
| Outcome | Result |
|---|---|
| Total wound dehiscence | 14.6% (15/103) |
| Mild dehiscence (conservative management) | 8.7% (9/103) |
| Moderate dehiscence (clinic suture reinforcement) | 4.9% (5/103) |
| Major dehiscence (washout and exchange to malleable prosthesis) | 1.0% (1/103) |
| Diabetes as risk factor for dehiscence | OR 6.1 (95% CI 1.5–25.0, p = 0.013) |
| V-Y plasty technique as risk factor for dehiscence | OR 4.9 (95% CI 1.2–8.6, p = 0.003) |
| Age, Peyronie's, HTN, smoking, device manufacturer | Not associated with dehiscence |
Findings.
- Diabetes was the strongest risk factor for wound dehiscence (OR 6.1). Diabetic patients should be counseled about the increased complication risk when scrotoplasty is performed concurrently with IPP.[6]
- Scrotoplasty technique, reported as V-Y plasty, was associated with higher odds of dehiscence (OR 4.9).[6]
- Earlier reports describe improved satisfaction with IPP after scrotoplasty. This retrospective single-surgeon series reported wound outcomes.[6]
Miranda-Sousa 2007 (n = 43, ventral phalloplasty)[5]
- 98% (42/43) reported good overall satisfaction at 3 months by questionnaire.[5]
- 84% (36/43) reported some increase in perceived penile length, compared with 84% (31/37) of the group without web release who complained of shortening.[5]
- Complications: wound hematoma 4.7% (2/43) and focal superficial wound dehiscence 7.0% (3/43).[5]
Abdelwahab 2025 RCT (n = 61)[15]
- Randomized comparison of malleable penile prosthesis placement with suspensory-ligament release, Z-plasty, and dorsal and ventral phalloplasty (Group A, n = 31) versus malleable penile prosthesis placement alone (Group B, n = 30).[15]
- Mean functional and visible penile lengths were significantly greater in Group A (p < 0.001), assessed at 3 months. The same group reported a 61-patient randomized trial of similar design in 2022 (El Gharably), and the two reports may share patients.
VI. Complications of Reduction Scrotoplasty
General risk profile (NSQIP, Rezaee 2022 — n = 12,917 benign scrotal operations)[26]
Across 12,917 elective benign scrotal operations of mixed types, 4.1% had a 30-day composite event (postoperative complication, unplanned procedure, or death). Adjusted associations with the composite endpoint were:[26]
| Risk factor | Adjusted OR (95% CI) |
|---|---|
| Malnourishment | 4.1 (1.2–14.5) |
| Decreased functional status | 3.8 (2.0–7.1) |
| Bleeding disorders | 3.4 (2.2–5.4) |
| COPD | 1.8 (1.2–2.6) |
| Age ≥ 40 | 1.6 (1.2–2.0) |
| Smoking | 1.4 (1.2–1.8) |
| Diabetes | 1.3 (1.1–1.7) |
| Increased BMI (per unit) | 1.1 (1.1–1.1) |
Procedure-specific complications[1][2][5][6]
- Wound dehiscence. The most common complication (14.6% when combined with IPP); higher with V-Y plasty and in diabetic patients.[6]
- Hematoma. Hematoma occurred in 4.7% (2/43) in Miranda-Sousa's series.[5] The scrotal skin is highly vascular, and meticulous hemostasis is necessary.
- Seroma. Fluid accumulation in the dead space created by skin excision.
- Infection. Monitor for surgical-site infection; a procedure-specific rate for isolated aesthetic reduction scrotoplasty has not been established.[2]
- Scrotal asymmetry. Uneven skin excision can produce cosmetically unsatisfactory asymmetry.
- Altered scrotal sensation. Damage to anterior or posterior scrotal nerves during skin excision.
- Over-resection. Excessive skin removal results in a tight, uncomfortable scrotum with restricted testicular mobility, pain with sitting, and difficulty with testicular self-examination.[9]
- Scar visibility. Midline raphe scars are generally well-concealed; penoscrotal-junction scars may be more visible.
- Recurrence of laxity. Scrotal skin continues to age and lose elasticity; long-term recurrence of ptosis is possible.
VII. Non-Surgical Alternatives — Energy-Based Devices
Radiofrequency (RF) and other energy-based devices have been used for skin tightening in various body areas; their application to scrotal-skin tightening has been explored anecdotally.[17][18][19]
- Monopolar and bipolar RF devices were reported in a systematic review to produce measurable improvement in skin laxity of the face and body, attributed to thermal stimulation of collagen contraction and neocollagenesis.[18][17]
- Fractional RF microneedling (e.g., Morpheus8) combined with bipolar RF has been described for skin tightening in various body areas.[18]
- No published clinical studies specifically evaluating RF or laser devices for scrotal-skin tightening were identified.
- Theoretical concerns include the proximity of the testes to the treatment area and the potential for thermal injury to spermatic-cord structures, spermatogenesis, and scrotal skin (which is thinner than most body sites).
- A systematic review of energy-based skin tightening concluded that clinically evident skin tightening "remains poorly measured and documented" even in well-studied body areas.[19]
VIII. Scrotoplasty in Specific Clinical Contexts
A. Buried / concealed-penis repair[10][20]
Scrotoplasty may be selected during adult-acquired buried-penis repair according to scrotal anatomy; a 10-institution retrospective cohort reported its use in 51 cases among 101 patients.[31]
- Combined with escutcheonectomy (suprapubic-fat-pad removal) and penile split-thickness skin grafting.
- Fuller 2017 series (n = 12, mean BMI 45.4): all remained unburied at intermediate-term follow-up (mean 8 months) after escutcheonectomy, scrotoplasty, and penile split-thickness grafting; mean graft take was 91.7%.[10]
- Wound dehiscence was reported after combined buried-penis repair, scrotoplasty, and panniculectomy in a seven-case series.[20]
For the operative deep-dive see Suprapubic Lipectomy and Buried Penis Repair (04e).
B. Scrotal lymphedema[11]
- Singh 2011 filarial-lymphedema series (n = 48; 34 with penoscrotal involvement): the 34 patients with penoscrotal disease underwent scrotoplasty after excision of diseased scrotal skin and soft tissue, sparing the testes and cords; all 48 patients in the mixed penile/penoscrotal reconstruction cohort reported a satisfactory cosmetic appearance at median 48-month follow-up.[11]
- All patients resumed sexual activity and reported improved ambulation.[11]
C. Hidradenitis suppurativa[9]
- Up to 50% of the scrotum can be resected and closed primarily when active disease does not make primary closure inappropriate.[29]
- Helpful maneuvers: division of the scrotal septum, mobilization of dartos fascia, division of the gubernaculum, and orchidopexy to secure testes superiorly.[9]
D. Gender-affirming surgery[21]
- Miller 2021 retrospective series of transgender scrotoplasty using labia majora rotational advancement flaps (n = 147; 133 with single-stage phalloplasty; mean follow-up 12.5 months): distal flap necrosis 4.1% (6/147) and large (> 1 cm) perineoscrotal junction dehiscence 4.7% (7/147); hematomas at either the scrotal or perineal site totaled 3.4% (5/147: 2 scrotal, 3 perineal), and all five required operative intervention.[21]
IX. Practical Considerations
Patient selection
- Assess scrotal laxity and penoscrotal webbing and discuss patient expectations. For planned skin excision, use a standing, flaccid-penis pinch assessment; examine the scrotum and testes for other pathology and distinguish buried or trapped penis from isolated scrotal laxity.[1]
- No standardized grading system exists for scrotal laxity. Thomas & Navia propose that a scrotum hanging > 1–2 cm below the penile tip constitutes a "bothersome scrotum."[1]
- Psychological screening. For cosmetic penile augmentation, the SMSNA 2024 expert-opinion statement advises ruling out penile dysmorphic disorder before invasive treatment with a symptom scale or questionnaire and professional psychological assessment.[22]
- Diabetes. Diabetes was associated with wound dehiscence (OR 6.1) when scrotoplasty accompanied IPP.[6]
Operative considerations
- Thomas and Navia describe general or spinal anesthesia for their combined aesthetic reduction and Z-plasty technique.[1][23] Local anesthesia alone has been reported for other penile and scrotal procedures.[1][23]
- Conservative skin excision is recommended. It is better to under-resect than over-resect; excessive removal leads to a tight, uncomfortable scrotum with restricted testicular mobility.[9]
- Meticulous hemostasis is necessary given rich vascularity.
- Thomas and Navia closed the dartos and skin in separate layers to restore the median raphe.[1]
- V-Y plasty was associated with higher dehiscence risk (OR 4.9) in one retrospective series and is used judiciously.[6]
Postoperative care
- Scrotal support (supportive underwear or jockstrap) for 2–4 weeks.
- In published combined-technique cases, sexual activity resumed at 14 days in one patient and at 4–6 weeks in another.[27][1]
- Wound monitoring, particularly in diabetic patients.
- Ice application to minimize edema.
CPT coding
- 55175. Scrotoplasty, simple (straightforward vertical midline skin resection).
- 55180. Scrotoplasty, complicated (septum division, dartos mobilization, orchidopexy, concurrent Z-plasty, or other adjunctive maneuvers).[1][2]
X. Evidence Summary and Limitations
| Feature | Current evidence |
|---|---|
| Level of evidence | Level IV (case reports, technique descriptions, single-surgeon series) |
| Systematic reviews | 2 — Thomas & Navia 2021; Schifano 2022 — both note scarcity of data |
| Largest cited IPP-associated scrotoplasty outcome series | Gupta 2019 (n = 103, scrotoplasty + IPP)[6] |
| RCTs | None identified for isolated cosmetic reduction scrotoplasty; the 61-patient Abdelwahab 2025 trial tested a multicomponent lengthening operation with penile prosthesis implantation at 3 months[15] |
| Standardized outcome measures | None validated for aesthetic scrotoplasty |
| Diagnostic criteria | No consensus; Thomas & Navia propose > 1–2 cm below penile tip |
| Nomenclature | No consensus; multiple overlapping terms |
| Long-term follow-up | Limited; no studies with > 2-year follow-up for aesthetic scrotoplasty |
XI. Clinical Summary
Reduction scrotoplasty is described by Schifano 2022, reviewing scarce evidence, as "easy, safe, and effective" for improving genital cosmesis. It can be performed in isolation or combined with penile-prosthesis implantation, suspensory-ligament release, or other genital aesthetic procedures.[2] The Thomas & Navia 2021 algorithm recommends vertical midline scrotal-skin resection for scrotomegaly and Z-plasty at the penoscrotal junction for webbing correction.[1] In a mixed penile-implant cohort (39 inflatable and four semirigid), 36/43 men reported greater perceived penile length at three months after ventral phalloplasty; 31/37 men without web release complained of shortening.[5] In one retrospective single-surgeon series of 103 IPP-associated scrotoplasties, wound dehiscence occurred in 15/103 (14.6%); diabetes (OR 6.1) and V-Y plasty (OR 4.9) were associated with dehiscence.[6] The evidence base remains limited, dominated by case reports and technique descriptions, and no standardized diagnostic criteria, grading systems, or validated outcome measures exist for aesthetic scrotoplasty.[1][2] Non-surgical alternatives (energy-based devices) lack any published clinical evidence specifically for scrotal-skin tightening and carry theoretical safety concerns regarding the proximity of the testes to the treatment area.[19]
See Also
- Male Cosmetic Genital Surgery (atlas)
- Scrotal Reconstruction (full reconstructive toolkit)
- Buried Penis Repair (04e)
- Suprapubic Lipectomy
- Suspensory Ligament Division
- Penuma & Himplant
- Inflatable Penile Prosthesis (foundations)
- Foundations — Z-Plasty
- Foundations — V-Y Advancement
- Small Penis Syndrome / PDD (clinical conditions)
References
1. Thomas C, Navia A. Aesthetic scrotoplasty: systematic review and a proposed treatment algorithm for the management of bothersome scrotum in adults. Aesthet Plast Surg. 2021;45(2):769–776. doi:10.1007/s00266-020-01998-3
2. Schifano N, Castiglione F, Cakir OO, Montorsi F, Garaffa G. Reconstructive surgery of the scrotum: a systematic review. Int J Impot Res. 2022;34(4):359–368. doi:10.1038/s41443-021-00468-x
3. Zaccaro C, Subirà D, López-Diez I, et al. History and future perspectives of male aesthetic genital surgery. Int J Impot Res. 2022;34(4):327–331. doi:10.1038/s41443-022-00580-6
4. Zampieri N, Dando I, Camoglio FS. Adolescent male genitalia dissatisfaction: a surgical perspective. Asian J Androl. 2022;24(2):176–179. doi:10.4103/aja.aja_60_21
5. Miranda-Sousa A, Keating M, Moreira S, Baker M, Carrion R. Concomitant ventral phalloplasty during penile-implant surgery: a novel procedure that optimizes patient satisfaction and their perception of phallic length after penile-implant surgery. J Sex Med. 2007;4(5):1494–1499. doi:10.1111/j.1743-6109.2007.00551.x
6. Gupta NK, Sulaver R, Welliver C, et al. Scrotoplasty at time of penile implant is at high risk for dehiscence in diabetics. J Sex Med. 2019;16(4):602–608. doi:10.1016/j.jsxm.2019.02.001
7. Whelan P, Levine LA. Additional procedures performed at time of penile-prosthesis implantation: a review of current literature. Int J Impot Res. 2020;32(1):89–98. doi:10.1038/s41443-019-0118-y
8. Lo Re M, Alonso Isa M, Garcia Rojo E, et al. Advancements in penile-lengthening techniques concurrent with penile-prosthesis placement: a narrative review. Asian J Androl. 2025. doi:10.4103/aja202512
9. Hamad J, McCormick BJ, Sayed CJ, et al. Multidisciplinary update on genital hidradenitis suppurativa: a review. JAMA Surg. 2020;155(10):970–977. doi:10.1001/jamasurg.2020.2611
10. Fuller TW, Theisen K, Rusilko P. Surgical management of adult acquired buried penis: escutcheonectomy, scrotectomy, and penile split-thickness skin graft. Urology. 2017;108:237–238. doi:10.1016/j.urology.2017.05.053
11. Singh V, Sinha RJ, Sankhwar SN, Kumar V. Reconstructive surgery for penoscrotal filarial lymphedema: a decade of experience and follow-up. Urology. 2011;77(5):1228–1231. doi:10.1016/j.urology.2010.10.026
12. Bagnara V, Donà A, Berrettini A, et al. The "V-I penoscrotal reconfiguration": a simple technique for the surgical treatment of congenital webbed penis. Int J Urol. 2024;31(8):886–890. doi:10.1111/iju.15476
13. Xu JG, Lv C, Wang YC, Zhu J, Xue CY. Management of concealed penis with modified penoplasty. Urology. 2015;85(3):698–702. doi:10.1016/j.urology.2014.06.044
14. Chen YB, Ding XF, Luo C, et al. A new plastic surgical technique for adult congenital webbed penis. J Zhejiang Univ Sci B. 2012;13(9):757–760. doi:10.1631/jzus.B1200117
15. Abdelwahab M, AbdelKader A, Abdelrassoul M, et al. Maximizing postoperative satisfaction in penile-prosthesis surgery: the predictive power of preoperative length and its role in tailoring enhancement procedures. J Sex Med. 2025. doi:10.1093/jsxmed/qdaf169
16. Rapp DE, Cohn AB, Gottlieb LJ, Lyon MB, Bales GT. Use of tissue expansion for scrotal-sac reconstruction after scrotal-skin loss. Urology. 2005;65(6):1216–1218. doi:10.1016/j.urology.2005.02.006
17. Smith DM. The role of energy-based devices in male body contouring. Clin Plast Surg. 2022;49(2):329–337. doi:10.1016/j.cps.2022.01.001
18. Rohrich RJ, Schultz KP, Chamata ES, Bellamy JL, Alleyne B. Minimally invasive approach to skin tightening of the face and body: systematic review of monopolar and bipolar radiofrequency devices. Plast Reconstr Surg. 2022;150(4):771–780. doi:10.1097/PRS.0000000000009535
19. Atiyeh B, Greige G, Hajjar M, Rabay C, Emsieh S. Clinical relevance of skin tightening with minimally invasive subdermal energy-based (EB) technologies. Aesthet Plast Surg. 2025. doi:10.1007/s00266-025-05022-4
20. Corder B, Googe B, Velazquez A, Sullivan J, Arnold P. Surgical management of acquired buried penis and scrotal lymphedema: a retrospective review. J Plast Reconstr Aesthet Surg. 2023;85:18–23. doi:10.1016/j.bjps.2023.06.021
21. Miller TJ, Lin WC, Safa B, Watt AJ, Chen ML. Transgender scrotoplasty and perineal reconstruction with labia majora flaps: technique and outcomes from 147 consecutive cases. Ann Plast Surg. 2021;87(3):324–330. doi:10.1097/SAP.0000000000002602
22. Trost L, Khera M, Köhler T, et al. Cosmetic penile-enhancement procedures: an SMSNA position statement. J Sex Med. 2024;21(6):573–578. doi:10.1093/jsxmed/qdae045
23. Bal DS, Chung D, Urichuk M, et al. Utilizing local anesthesia only for penile and scrotal urologic surgery: a prospective study on patient tolerability and surgical outcomes for a sedation-free option. Urology. 2024;194:7–13. doi:10.1016/j.urology.2024.08.051
24. Sharlip ID. Surgery of scrotal contents. Urol Clin North Am. 1987;14(1):145–148. doi:10.1016/s0094-0143(21)00827-2
25. Issa MM, Hsiao K, Bassel YS, et al. Spermatic-cord anesthesia block for scrotal procedures in outpatient clinic setting. J Urol. 2004;172(6 Pt 1):2358–2361. doi:10.1097/01.ju.0000144544.43148.10
26. Rezaee ME, Swanton AR, Gross MS. Current findings regarding perioperative complications in benign scrotal surgery. Urology. 2022;169:23–28. doi:10.1016/j.urology.2022.06.043
27. Nazario-Perez MZ, Rodríguez-Fernández LF, Cintron-Cartagena KO, Castillo J. Reduction scrotoplasty with concomitant ventral phalloplasty: rethinking the approach to a common urological condition. Cureus. 2025;17(2):e79786. doi:10.7759/cureus.79786
28. Yilmaz U, Yang CC, Berger RE. "Dartos reflex: a sympathetically mediated scrotal reflex." Muscle Nerve. 2006;33(3):363–368. doi:10.1002/mus.20476
29. Pozo C, Ralph DJ, Lee WG. "Management of penoscrotal hidradenitis: a narrative review." Int J Impot Res. 2025. doi:10.1038/s41443-025-01189-1
30. Chung E, Jenkins L, Moon DG, et al. "Penile augmentation and cosmetic surgery: recommendations from the Fifth International Consultation on Sexual Medicine (ICSM 2024)." Sex Med Rev. 2026;14(1):qeaf067. doi:10.1093/sxmrev/qeaf067
31. Schlaepfer CH, Flynn KJ, Alsikafi NF, et al. "Clinical validation of an adult-acquired buried penis classification system based on standardized evaluation of the penis, abdomen, and scrotum." Urology. 2023;180:249–256. doi:10.1016/j.urology.2023.04.048
32. Saxena N, Jolly D, Wu CA, Boskey ER, Ganor O. "Comparing scrotoplasty complication rates in transgender and cisgender men: An ACS NSQIP study." JPRAS Open. 2023;36:55–61. doi:10.1016/j.jpra.2023.03.003