Suprapubic Lipectomy / Liposuction
Suprapubic lipectomy / liposuction is a spectrum of procedures, from minimally invasive liposuction to open surgical fat-pad excision (lipectomy) and escutcheonectomy, that reduce the suprapubic fat pad to increase apparent (visible) penile length without altering true corporeal length. Used in two distinct contexts: cosmetic or aesthetic penile enhancement in men with excess mons-pubis fat, and reconstructive surgery for adult-acquired buried penis (AABP). Increasingly performed as an adjunct to penile prosthesis implantation and suspensory ligament division.[1][2][3][4]
For positioning versus other male cosmetic options see Cosmetic Genital Surgery — Male. For the AABP clinical condition and reconstructive atlas see Buried Penis and Buried Penis Repair.
Mechanism and rationale
The suprapubic, prepubic or infrapubic fat pad overlies the pubic symphysis and, when excessive, conceals the base of the penile shaft, reducing visible exophytic length. Corporeal length is normal; the penis is buried beneath prepubic fat. Reducing this fat pad reveals the hidden portion of the shaft, increasing skin-to-tip measurement without changing the underlying corpora cavernosa.[1][5]
Suprapubic fat reduction differs from suspensory ligament division, which exteriorizes intracorporeal shaft.[6]
Clinical indications
Cosmetic / aesthetic enhancement
- Men with suprapubic adiposity and normal corporeal length who perceive their penis as short due to the concealing fat pad.
- Assess small-penis anxiety and PDD separately from suprapubic concealment. In men with a normal-sized penis who complain of shortness, the EAU strongly recommends asking about BDD/PDD and referring suspected BDD for mental-health counselling.[29]
- BMI may be normal, overweight, or mildly obese.
- Liposuction may be standalone or combined with SLD and/or girth enhancement.[1][2][6]
Adult-acquired buried penis (AABP) reconstruction
- Men with AABP from suprapubic fat, redundant skin, scarring or diseased tissue; morbid obesity is common in selected high-complexity cohorts but is not required. Staniorski’s high-complexity cohort had median BMI 43 kg/m², whereas Plamadeala’s mixed-severity cohort had median BMI 30 kg/m².[7][8][9]
- Associated with urinary dysfunction, sexual dysfunction, recurrent infections, lichen sclerosus, severely impaired QoL.[10][11]
- AABP repair may require escutcheonectomy, panniculectomy, scrotoplasty and/or STSG according to penile, abdominal and scrotal tissue findings; none is universal.[7][12][13][16]
Procedures and techniques
A. Suprapubic liposuction (minimally invasive)
The least invasive approach[1]:
- Tumescent liposuction of the infrapubic / suprapubic fat pad through 1–2 small stab incisions.
- Cannula directed in a fan-shaped pattern to debulk fat overlying the pubic symphysis and penile base.
- Local anesthesia with tumescent solution, or general / regional anesthesia.
- Volume aspirated: mean 430 ± 90 mL in one combined series.[14]
- Ghanem 2017 Aesthet Plast Surg: in 10 men treated with standalone liposuction (level IV evidence), flaccid and stretched penile length increased at 3 mo (p < 0.001), with minor or no complications.[1]
- Best suited for simple buried penis with isolated excess mons-pubis fat. Must be differentiated from complex cases requiring multicomponent reconstruction.[1]
B. Open suprapubic lipectomy (fat-pad excision)
A more aggressive approach with direct surgical excision[3][15][4]:
- Transverse or elliptical incision in the suprapubic crease, extending laterally toward the ASIS.
- Fat pad dissected free from anterior abdominal fascia using sharp dissection and electrocautery.
- Areolar tissue preserved above fascia to prevent seroma formation.
- Flap inset and closure. In Loh-Doyle’s combined lipectomy/IPP technique, inspect the external-pudendal-based flaps for vascularity, approximate skin from lateral to medial and anchor the flap superiorly to the lower abdominal fold. Close in multiple layers with drain placement as described for open lipectomy.[3][15]
| Series | n | Setting | Outcome |
|---|---|---|---|
| Baumgarten 2019 J Sex Med[15] | 8 (BMI 36.6) | SPL + IPP simultaneous | Authors report excellent cosmetic and functional outcomes; 1 prosthetic infection after inadvertent drain removal |
| Shaeer 2018 J Sex Med[4] | 22 | Simultaneous SPL + penile prosthesis through same abdominal-crease incision | Mean patient-rated length satisfaction rose from 2.55 ± 0.67 to 4.77 ± 0.43 on a 5-point scale (p < 0.0001) |
| Loh-Doyle 2023 Urology[3] | 9 | Concurrent SPL + 3-piece IPP | Improved dorsal phallic length; 1 infection requiring device exchange |
C. Escutcheonectomy
Excision of the escutcheon (hair-bearing suprapubic skin and underlying fat pad), a more extensive procedure typically reserved for AABP reconstruction.[12][13][16]
- Entire escutcheon excised en bloc, exposing the penile base. During dissection to the aponeurosis, protect the spermatic cords and reestablish the penopubic angle with anchoring sutures to limit recurrent burial.[34]
- Preserve sufficient healthy shaft skin; when it is deficient or diseased, reconstruct with STSG harvested from the thigh or suitable excised escutcheon tissue.[12][13][16]
- Fuller 2017 Urology[12] n = 12 (mean BMI 45.4): all remained unburied at mean 8-month follow-up; longer-term recurrence was not assessed. STSG take was 80–100% (mean 91.7%); OR time 312 ± 59 min, LOS 5.3 ± 1.1 d, and EBL 304 ± 133 mL.
- Strother 2018 J Sex Med described harvesting STSG from suitable excised escutcheon tissue to avoid a separate donor-site wound.[13]
- Schlaepfer 2023 PAS classification validation (n=101): escutcheonectomy was the most common component procedure, recorded in 59 patients.[16]
D. Panniculectomy
Excision of the overhanging abdominal pannus, reserved for the most severe AABP cases where the pannus itself contributes to penile burial[17][7]:
- Performed in 7% of AABP repairs (PAS validation study).[16]
- Corresponds to Stage 5 in the Pariser-Santucci classification.[7]
- Barrow 2024 SR and NSQIP analysis. Patients receiving panniculectomy had more wound complications before adjustment; the adjusted difference in 30-day complications was not statistically significant (p > 0.05). BMI remained a significant predictor.[17]
AABP classification systems
Jun–Gallegos–Santucci stages (2018)[7]
| Stage | Findings |
|---|---|
| 1 | Phimotic band only |
| 2 | Diseased penile skin requiring excision + STSG |
| 3 | Requires scrotal excision |
| 4 | Requires escutcheonectomy |
| 5 | Requires panniculectomy |
Jun and Santucci's 73-patient series: 37/73 (51%) had stage 4–5 disease, and 44/73 (60%) had a complication within 30 days. Overall, 62/73 (85%) had either no complication or only Clavien I–II complications; 5/36 (14%) stage 1–3 patients had complications.[7]
PAS classification (validated 2023)[16]
Classifies AABP by P (penile skin and escutcheon), A (abdominal pannus), and S (scrotal skin). Interrater reliability was κ = 0.95. Subtypes strongly associated with specific surgical techniques. Most common: P2c (27%), A0 (41%), S0 (71%).[16]
Efficacy
| Study | n | Procedure | Population | Length gain | Satisfaction | Complications |
|---|---|---|---|---|---|---|
| Ghanem 2017[1] | 10 | Liposuction (standalone) | Infrapubic adiposity | Significant (p < 0.001) | Reported (Likert) | Minor or none |
| Shaeer 2018[4] | 22 | SPL + penile prosthesis | ED + concealed penis | Preoperative erect length not measured | Patient length-satisfaction rating 2.55 → 4.77/5; partner 4.41/5 | No infections / extrusions |
| Baumgarten 2019[15] | 8 | SPL + IPP | ED + suprapubic fat | Improved dorsal length | Authors report excellent outcomes | 1 infection (12.5%) |
| Loh-Doyle 2023[3] | 9 | SPL + 3-piece IPP | ED + lipodystrophy | Improved dorsal length | Good | 1 infection (11%) |
| El Gharably 2022 RCT[18] | 31 (SLR + PL arm) | SLR + pubic lipectomy + Z-plasty + PPI | ED | +2.5 cm visible length at 3 mo (IQR 1–3.5) | EDITS 95.4 vs 85.2 (p < 0.001) | Edema 77.4%, instability 9.7% |
| Wang 2025[19] | 42 (28 with liposuction) | Diamond penoplasty ± liposuction | AABP (mean BMI 35.6) | Whole-cohort mean flaccid gain 3.61 cm (1.94 to 5.55) | 4.02/5 | Dehiscence 3/42, infection 2/42; liposuction-related ecchymosis 3/28 and skin sclerosis 2/28; mean follow-up 6.7 mo |
| Zhang 2019[14] | 15 | SLD + liposuction + ADM | Small-sized or buried penis (BMI 28.9) | +2.4 cm at 3 mo | No patient dissatisfied | Edema, ecchymosis, poor healing |
| Fuller 2017[12] | 12 | Escutcheonectomy + scrotoplasty + STSG | AABP (mean BMI 45.4) | 12/12 unburied at mean 8-month follow-up | NR | STSG take 91.7% |
| Plamadeala 2026 multicentre[9] | 204 | Various AABP repairs | AABP | Median +3.0 cm stretched length (IQR 2.0–6.0) | 59/68 questionnaire respondents satisfied (86.8%) | 55/204 (27.0%) had complications; 26/204 (12.7%) recurred; median follow-up 18 mo |
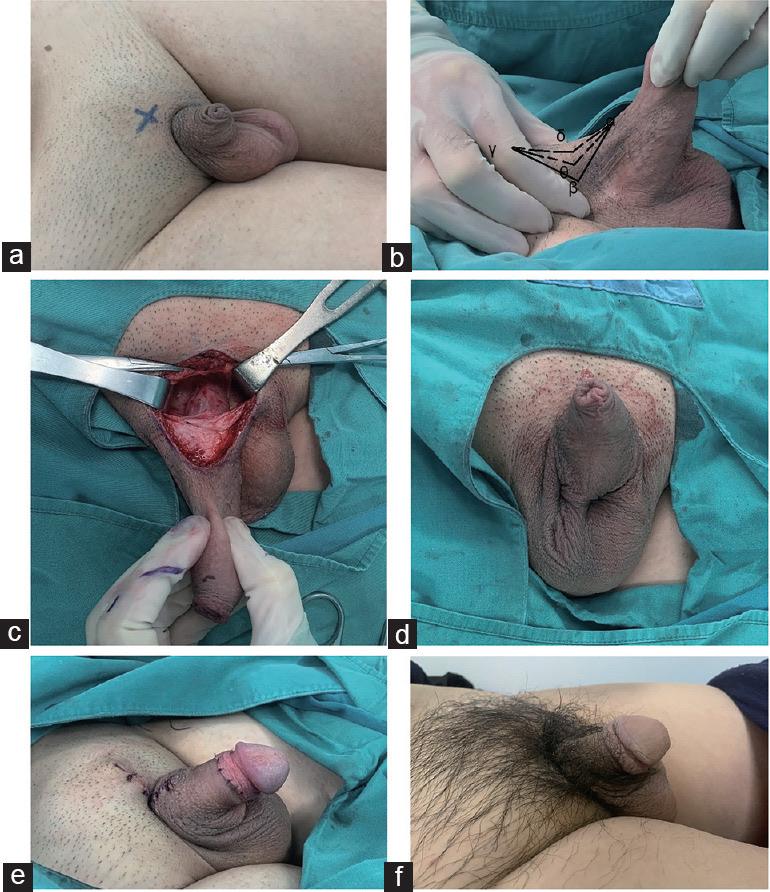
Diamond-shaped penoplasty for adult-acquired buried penis (AABP), the technique in the Wang 2025 row above. (a) Preoperative appearance of the penis. (b) Diamond-shaped incision at the penopubic junction: points α, β, γ and δ are the corners of the diamond, α is the original penopubic angle and θ, the joint between β and δ, becomes the new penopubic angle. (c) Penile degloving through this incision to release abnormal dartos attachments to Buck fascia. (d) Establishment of the penoscrotal angle. (e) Appearance at the end of the procedure. (f) Appearance 3 months after surgery. From Wang J, et al. Asian J Androl. 2025;27(1):72-75, Figure 1 (CC BY-NC-SA).[19]
Non-invasive alternative — cryolipolysis
For the full per-device deep-dive (mechanism, FDA off-label-suprapubic positioning, treatment protocol, paradoxical-adipose-hyperplasia counseling, contraindications, full evidence base) see the canonical page: Cryolipolysis (Suprapubic).
- Mechanism: controlled cooling induces apoptosis of adipocytes; gradual fat reduction over weeks to months.[20][21]
- Azab 2021 Andrologia. In an uncontrolled 46-man series, mean apparent stretched penile length was 12.1 cm before session 1 and 12.88 cm before session 3.[22]
- Mineroff 2023 review: its PubMed search found no suprapubic studies of cryolipolysis, injection lipolysis, radiofrequency or ultrasound; the search did not capture Azab’s 2021 suprapubic cryolipolysis series described above.[22][23]
- General cryolipolysis outcomes: Ingargiola’s 2015 review of 19 studies reported 14.7–28.5% fat reduction by caliper at treated body sites.[20] Ravindran’s 2025 meta-analysis (30 studies, 3,158 participants) reported 80.4% satisfaction, numbness 49.5%, erythema 44.5%, edema 30.5%, and pain 28.8%.[21]
Combined with penile prosthesis implantation
Concurrent suprapubic lipectomy is used to address the common complaint of perceived penile shortening after prosthesis placement.[3][15][4][18][24]
Rationale: many men with ED are overweight or obese with prominent suprapubic fat pads. After prosthesis implantation, the perceived length loss is compounded by the fat pad, leading to dissatisfaction. Concurrent SPL addresses both issues in a single session.[4]
El Gharably 2022 J Sex Med RCT (n = 61) comparing SLR plus pubic lipectomy via Z-plasty during malleable PPI with conventional penoscrotal PPI[18]:
- Median pre-to-post change in visible length at 3 months was 2.5 cm (IQR 1–3.5) in the combined-procedure group versus 0 cm (IQR −1 to 0) in controls (p < 0.001).[18]
- IIEF satisfaction-domain scores and EDITS were higher in the SLR plus lipectomy group (EDITS 95.4 vs 85.2, p < 0.001); length was assessed at 3 months and satisfaction up to 1 year.
- Operative time was longer (170 vs 97.5 min). In the 31-man combined SLR, pubic-lipectomy, Z-plasty and malleable-prosthesis arm, edema occurred in 77.4%, instability in 9.7% and glans numbness in 9.7%.[18]
Krishnappa 2025 Int J Impot Res is a narrative review of length-preservation maneuvers during IPP placement; it lists suprapubic lipectomy among the intraoperative options.[24]
Complications
Complication profiles differ substantially between minimally invasive liposuction and open lipectomy / escutcheonectomy.
Suprapubic liposuction (standalone)
- In a standalone 10-man infrapubic liposuction series with measurements through three months, the authors characterized complications as minor or absent.[1]
- General liposuction major complication rate: 0.7% alone (hematoma 0.15%, pulmonary 0.1%, infection 0.1%, VTE 0.06%); independent risk factors include combined procedures (RR 4.81), age, BMI, hospital setting.[25]
Open suprapubic lipectomy
- Seroma. Seroma is a common complication of body-contouring resection. In a retrospective series of 222 massive-weight-loss body-contouring patients, seroma risk rose 9% for each additional pound of skin excised.[26] Areolar-tissue preservation above fascia and drain placement are used to reduce it.[3]
- Wound dehiscence. In an institutional abdominal lipectomy series (n = 362), wound disruption increased with BMI, from 2.6% in normal-weight patients to 56.3% in class III obesity.[27]
- Hematoma. Associated with increased AABP recurrence (p < 0.05).[9]
- Infection. Wang reported wound infection in 2/42 (4.8%) after diamond penoplasty (28 also had liposuction); Staniorski reported infection in 30% of 103 high-complexity escutcheonectomy-and-graft repairs.[19][8]
Escutcheonectomy / panniculectomy for AABP
- Across heterogeneous AABP repair series, overall complications occurred in 44/73 (60%) within 30 days in Jun’s mixed-stage cohort, 50% of Staniorski’s escutcheonectomy-plus-graft cohort, and 55/204 (27.0%) in Plamadeala’s mixed-procedure cohort; most were Clavien I–II.[7][8][9]
- Wound dehiscence 31% (Staniorski 2023 single-center n = 103).[8]
- Infection 30%.[8]
- Recurrence 12.7%; recurrence-free survival 91.5% at 12 mo, 83.7% at 24 mo.[9]
- Frailty (mFI ≥ 2) strongest predictor of complications (OR 6.41, 95% CI 1.77–23.22, p = 0.005).[8]
- High-complexity procedures (Pariser ≥ III) had higher complication rates (32.6% versus 13.3%, p = 0.005); crude recurrence was 10.4% versus 18.3% (p = 0.165), while the adjusted recurrence hazard was lower (aHR 0.35, p = 0.018).[9]
Functional and QoL outcomes after AABP repair
Small retrospective series report improved urinary and sexual scores after AABP repair despite frequent complications. IPSS, IIEF-15 and quality-of-life figures come from 16/28 Falcone questionnaire respondents; hygiene, urination and willingness to repeat surgery come from 12/14 eligible Voznesensky questionnaire respondents.[10][11][9]
| Outcome | Improvement |
|---|---|
| IPSS | 8 → 2 (p = 0.03) |
| IIEF-15 | 37 → 68 (p = 0.001) |
| Hygiene | 100% improved among all 12 questionnaire respondents (12/14 eligible responded)[11] |
| Urination | 91% improved among 12 questionnaire respondents (12/14 eligible responded)[11] |
| QoL | Falcone: 93.8% positive impact in a 28-patient mixed AABP cohort[10]; Voznesensky: 92% would choose surgery again among 12 questionnaire respondents (12/14 eligible responded)[11] |
| SPL gain (Plamadeala 2026) | +3.0 cm |
| Satisfaction (Plamadeala) | 59/68 questionnaire respondents (86.8%)[9] |
Comparative summary of suprapubic-fat-reduction approaches
| Approach | Invasiveness | Setting | Length gain | Durability | Complication rate | Best candidates |
|---|---|---|---|---|---|---|
| Cryolipolysis | Non-invasive | Office | ~0.78 cm apparent stretched length from before session 1 to before session 3 in one uncontrolled suprapubic series[22] | Not reported | Numbness and erythema in studies at other body sites[21]; paradoxical adipose hyperplasia (pooled 0.22%, 95% CI 0.10–0.47%, low certainty, across body sites); suprapubic-specific risk unknown[32] | Mild suprapubic adiposity; CoolSculpting Elite does not list suprapubic fat as an indicated site and its manual prohibits use on genitalia or inguinal creases.[36] |
| Suprapubic liposuction | Minimally invasive | Ambulatory / OR | Significant (p < 0.001)[1] | 3-mo follow-up (Ghanem) | Minor or none (Ghanem) | Simple buried penis, moderate fat |
| Open suprapubic lipectomy | Surgical | OR | Combined SLR, lipectomy, Z-plasty and malleable PPI gained median 2.5 cm visible length at 3 mo[18] | Lipectomy-only durability not reported | Seroma, dehiscence, infection | Significant fat pad ± concurrent prosthesis |
| Escutcheonectomy | Major surgical | OR; selected combined AABP repairs, largely including escutcheonectomy, had 10/16 same-day discharges[35] | Mixed AABP repairs had median +3.0 cm stretched length[9] | Mixed AABP repairs were 83.7% recurrence-free at 24 mo[9] | 27% overall complications in 204 mixed repairs, and 60% within 30 days in a separate 73-person mixed repair series[9][7] | AABP Stage 4 |
| Panniculectomy | Major surgical | OR (inpatient) | Variable | Not reported | Adjusted 30-day complication difference versus BPR alone not statistically significant (p > 0.05)[17] | AABP Stage 5 with overhanging pannus |
Key clinical considerations
- Weight stability. The EAU 2026 guideline strongly recommends initiating lifestyle and risk-factor changes, particularly weight loss, before AABP surgery to minimize complications and optimize outcomes.[29] Weight regain after fat reduction may lead to recurrence of buried penis or loss of cosmetic benefit. Stable weight is a goal after surgery.[1][5]
- Simple versus complex buried penis. Before choosing liposuction alone, examine the patient standing and supine, compress the fat pad to assess the glans, meatus and viable shaft skin, inspect scrotal skin, and assess voiding symptoms. Suspected meatal or urethral stricture warrants evaluation because it may change the operative plan.[33] Liposuction alone is described for isolated suprapubic fat with examinable, viable penile skin. Diseased skin, lichen sclerosus, scrotal lymphedema or contributory pannus may require multicomponent reconstruction. If the shaft cannot be exposed for examination, counsel about diagnostic uncertainty and plan assessment for occult skin disease.[1][7][30] In a retrospective cohort of 203 patients who underwent buried-penis repair with penile-skin removal, pathology found lichen sclerosus in 35/123 nonexhumable cases (28.4%) versus 11/80 exhumable cases (13.8%), and penile cancer in 8/123 (6.5%) versus 2/80 (2.5%); the cancer difference was not statistically significant.[30]
- Adjunct to other procedures. Most commonly performed combined with SLD for cosmetic lengthening, or with penile prosthesis implantation to maximize visible length.[2][4][18][24]
- Risk stratification. Higher BMI is associated with complications in some retrospective cohorts, while frailty predicted complications in Staniorski’s high-complexity series and surgical complexity predicted them in Plamadeala’s multicentre series. Assess BMI alongside frailty, tissue disease and planned extent of repair. Mansour and colleagues suggest staged body-contouring procedures may suit higher-BMI patients.[17][8][9][27]
- Guidelines. In its section on congenital intrinsic penile shortness, the EAU 2026 guideline weakly recommends suprapubic lipoplasty, liposuction or lipectomy as lengthening options and strongly recommends extensive complication counseling; its procedure text specifies increased penile shaft exposure.[29] For AABP, it strongly recommends surgery in high-volume centers.[29] For adult acquired buried penis, the ICSM 2026 consultation groups suprapubic fat reduction with other aesthetic procedures and states as Expert Opinion that they may improve the appearance of flaccid penile length, but not girth or erect penile length; it describes penile neurovascular and regional nerve-injury risks during dissection.[31] The SMSNA 2024 expert-opinion statements do not address suprapubic fat reduction specifically.[28]
See Also
Cosmetic Genital Surgery — Male · Suspensory Ligament Division · HA Filler — Penile Girth · PLA Filler — Penile Girth · Buried Penis (clinical condition) · Buried Penis Repair (atlas) · Small Penis Syndrome / PDD
References
1. Ghanem H, ElKhaiat YI, Motawi AT, AbdelRahman IF. Infrapubic liposuction for penile length augmentation in patients with infrapubic adiposities. Aesthetic Plast Surg. 2017;41(2):441-447. doi:10.1007/s00266-017-0786-2
2. Spyropoulos E, Christoforidis C, Borousas D, et al. Augmentation phalloplasty surgery for penile dysmorphophobia in young adults. Eur Urol. 2005;48(1):121-127. doi:10.1016/j.eururo.2005.02.021
3. Loh-Doyle JC, Markarian E, Burg M, Boyd S. Suprapubic lipectomy and placement of a three-piece inflatable penile prosthesis. Urology. 2023;181:e204. doi:10.1016/j.urology.2023.07.029
4. Shaeer O, Shaeer K, AbdelRahman IF. Simultaneous suprapubic lipectomy and penile prosthesis implantation. J Sex Med. 2018;15(12):1818-1823. doi:10.1016/j.jsxm.2018.10.012
5. Mirastschijski U. Classification and treatment of the adult buried penis. Ann Plast Surg. 2018;80(6):653-659. doi:10.1097/SAP.0000000000001410
6. García Gómez B, Alonso Isa M, García Rojo E, Fiorillo A, Romero Otero J. Penile length augmentation surgical and non-surgical approaches for aesthetical purposes. Int J Impot Res. 2022;34(4):332-336. doi:10.1038/s41443-021-00488-7
7. Jun MS, Gallegos MA, Santucci RA. Contemporary management of adult-acquired buried penis. BJU Int. 2018;122(4):713-715. doi:10.1111/bju.14230
8. Staniorski CJ, Myrga JM, Vasan RV, Klein RD, Rusilko PJ. Surgical outcomes and prediction of complications following high-complexity buried penis reconstruction. J Urol. 2023;210(5):782-790. doi:10.1097/JU.0000000000003669
9. Plamadeala N, Lee WGD, Ruffo A, et al. Outcomes of adult acquired buried penis (AABP) reconstruction: a multicentre cohort study. Int J Impot Res. 2026;38(4):354-362. doi:10.1038/s41443-026-01269-w
10. Falcone M, Preto M, Timpano M, et al. The outcomes of surgical management options for adult acquired buried penis. Int J Impot Res. 2023;35(8):712-719. doi:10.1038/s41443-022-00642-9
11. Voznesensky MA, Lawrence WT, Keith JN, Erickson BA. Patient-reported social, psychological, and urologic outcomes after adult buried penis repair. Urology. 2017;103:240-244. doi:10.1016/j.urology.2016.12.043
12. Fuller TW, Theisen K, Rusilko P. Surgical management of adult acquired buried penis: escutcheonectomy, scrotectomy, and penile split-thickness skin graft. Urology. 2017;108:237-238. doi:10.1016/j.urology.2017.05.053
13. Strother MC, Skokan AJ, Sterling ME, Butler PD, Kovell RC. Adult buried penis repair with escutcheonectomy and split-thickness skin grafting. J Sex Med. 2018;15(8):1198-1204. doi:10.1016/j.jsxm.2018.05.009
14. Zhang X, Huang Z, Xiao Y, et al. Suspensory ligament release combined with acellular dermal matrix filler in infrapubic space: a new method for penile length augmentation. Andrologia. 2019;51(9):e13351. doi:10.1111/and.13351
15. Baumgarten AS, Beilan JA, Shah BB, et al. Suprapubic fat pad excision with simultaneous placement of inflatable penile prosthesis. J Sex Med. 2019;16(2):333-337. doi:10.1016/j.jsxm.2018.12.005
16. Schlaepfer CH, Flynn KJ, Alsikafi NF, et al. Clinical validation of an adult-acquired buried penis classification system based on standardized evaluation of the penis, abdomen, and scrotum. Urology. 2023;180:249-256. doi:10.1016/j.urology.2023.04.048
17. Barrow B, Laspro M, Brydges HT, et al. Technical considerations and outcomes for panniculectomy in the setting of buried penis patients: a systematic review and database analysis. Ann Plast Surg. 2024;93(3):355-360. doi:10.1097/SAP.0000000000004025
18. Aboul Fotouh El Gharably M, Ghoneima W, Lotfi MA, et al. The efficacy of suspensory ligament release and pubic lipectomy via penopubic Z plasty during penile prosthesis implantation in improving sexual satisfaction: a prospective randomized controlled trial. J Sex Med. 2022;19(5):852-863. doi:10.1016/j.jsxm.2022.02.024
19. Wang J, Ni J, Xu Y, et al. "A diamond-shaped" penoplasty technique with or without concurrent suprapubic liposuction for adult-acquired buried penis: clinical outcomes and patient satisfaction rates. Asian J Androl. 2025;27(1):72-75. doi:10.4103/aja202476
20. Ingargiola MJ, Motakef S, Chung MT, Vasconez HC, Sasaki GH. Cryolipolysis for fat reduction and body contouring: safety and efficacy of current treatment paradigms. Plast Reconstr Surg. 2015;135(6):1581-1590. doi:10.1097/PRS.0000000000001236
21. Ravindran R, Pizzol D, Rahmati M, et al. Cryolipolysis and associated health outcomes, adverse events, and satisfaction: a systematic review and meta-analysis. Obes Rev. 2025;26(8):e13925. doi:10.1111/obr.13925
22. Azab SS, Hamed HA, Elseginy A, Elzawahry HM, Ismail NN. Increase apparent penile length by cryolipolysis in the reduction of male suprapubic fat. Andrologia. 2021;53(3):e13963. doi:10.1111/and.13963
23. Mineroff J, Nguyen JK, Jagdeo J. Potential treatment modalities for suprapubic adiposity and pubic contouring. Arch Dermatol Res. 2023;315(6):1615-1619. doi:10.1007/s00403-023-02555-z
24. Krishnappa P, Matippa P, Fraile-Poblador A, Lledo-Garcia E, Moncada I. Penile length preservation in penile prosthesis placement: tips & tricks. Int J Impot Res. 2025. doi:10.1038/s41443-025-01123-5
25. Kaoutzanis C, Gupta V, Winocour J, et al. Cosmetic liposuction: preoperative risk factors, major complication rates, and safety of combined procedures. Aesthet Surg J. 2017;37(6):680-694. doi:10.1093/asj/sjw243
26. Shermak MA, Rotellini-Coltvet LA, Chang D. Seroma development following body contouring surgery for massive weight loss: patient risk factors and treatment strategies. Plast Reconstr Surg. 2008;122(1):280-288. doi:10.1097/PRS.0b013e31817742a9
27. Mansour A, Steele A, Terrasse W, et al. Incidence of complications associated with lipectomy techniques and patient body mass index: an institutional and national analysis using the Tracking Operations and Outcomes for Plastic Surgeons. Ann Plast Surg. 2023;90(6S Suppl 5):S526-S532. doi:10.1097/SAP.0000000000003532
28. Trost L, Khera M, Köhler T, et al. Cosmetic penile enhancement procedures: an SMSNA position statement. J Sex Med. 2024;21(6):573-578. doi:10.1093/jsxmed/qdae045
29. European Association of Urology. "Penile size abnormalities and dysmorphophobia." EAU Guidelines on Sexual and Reproductive Health. Limited update March 2026, section 9.3.2. Guideline.
30. Quinn A, Holum P, Daly W, Klein R, Rusilko P. "Pathologic differences in adult acquired buried penis patients by exhumable status." Urology. 2026;215:137–140. doi:10.1016/j.urology.2026.05.007
31. Chung E, Jenkins L, Moon DG, et al. "Penile augmentation and cosmetic surgery: recommendations from the Fifth International Consultation on Sexual Medicine (ICSM 2024)." Sex Med Rev. 2026;14(1):qeaf067. doi:10.1093/sxmrev/qeaf067
32. Mah AE, Razeghi P, Li C, Datta S, Tao BK, Ahmad J. "Incidence of Paradoxical Adipose Hyperplasia After Cryolipolysis: A Systematic Review and Meta-Analysis." Aesthet Surg J Open Forum. 2025;7:ojaf142. doi:10.1093/asjof/ojaf142
33. Ho TS, Gelman J. "Evaluation and management of adult acquired buried penis." Transl Androl Urol. 2018;7(4):618–627. doi:10.21037/tau.2018.05.06
34. D’Anna M, Peri Cusí L, Alcaraz Asensio A, Torremadé Barreda J. "Top ten surgical tricks–surgical management of adult acquired buried penis." Int J Impot Res. 2026. doi:10.1038/s41443-026-01293-w
35. Erpelding SG, Hopkins M, Dugan A, Liau JY, Gupta S. "Outpatient surgical management for acquired buried penis." Urology. 2019;123:247–251. doi:10.1016/j.urology.2018.10.002
36. ZELTIQ Aesthetics, Inc. "CoolSculpting Elite System User Manual." AbbVie; 2025. Document CS-UM-CM3-02-EN-M. User manual.