Suspensory Ligament Division (SLD)
Suspensory ligament division (SLD) is a long-standing surgical technique for penile lengthening. It releases the ligamentous attachments anchoring the penile root to the pubic symphysis, allowing the intracorporeal (hidden) portion of the penis to advance anteriorly. Clinical series report gains measured in different ways: Li et al. found +1.3 cm in flaccid stretched length, whereas Karimian et al. reported +2.6 cm in unstretched flaccid length.[2][1] Li et al. reported 35% satisfaction overall and 27% in the PDD subgroup; Karimian et al. reported improved MGSIS scores without a satisfaction percentage; Vyas et al. found 50–100% satisfaction across heterogeneous augmentation procedures and described them as investigational.[1][2][3] For positioning versus other male cosmetic options see Cosmetic Genital Surgery — Male.
SMSNA 2024 position statement. The statement is expert opinion. It holds that, in experienced hands, SLD may increase flaccid penile length, and that it should be considered only after a comprehensive discussion of complications including erectile dysfunction, sensory changes and penile instability. It also holds that body dysmorphic disorder must be ruled out before invasive treatment, using a validated questionnaire or scale plus professional psychological or psychiatric assessment.[4]
Anatomy of the penile suspensory ligamentous system
A cadaveric study of 49 specimens identified three distinct ligaments[5][6][7]:
- Fundiform ligament. The most superficial; arises from Scarpa's fascia (superficial bundles) and the linea alba (deep median bundles); inserts into superficial penile fascia and continues to the scrotal septum. Loose, fibro-fatty tissue not adherent to the tunica albuginea.[5][7]
- Suspensory ligament proper. Deeper, dense fibrous connective tissue arising from the pubic symphysis and inserting into Buck's fascia of the corpora cavernosa. Two lateral circumferential bundles and one median bundle circumscribing the deep dorsal vein. Primary target of SLD.[5][6]
- Arcuate (pubic) ligament. The deepest component; arises from the body of the pubis and pubic symphysis and inserts into Buck's fascia, with lateral attachments to the inferior pubic rami.[5][7]
The suspensory ligament maintains the base of the penis in front of the pubis and is a major support point during erection, stabilizing the upward erection angle during coitus.[6][8]
Mechanism of penile lengthening
SLD exteriorizes more of the existing intracorporeal shaft that normally resides behind the pubic symphysis, by releasing the tethering effect of the suspensory ligament.[9][10]
Ramos 2024 cadaveric morphometric study (16 specimens): complete ligamentolysis produced uniform length increase averaging +26.4 mm (SD 14.8; range 4–60 mm).[9]
In 16 cadavers, shorter pre-ligamentolysis length correlated with greater absolute gain (r = −0.601, p = 0.014). Age, ligament width, pubic-arch depth, and ethnicity showed no significant correlations with gain.[9]
Surgical techniques
1. Classic infrapubic approach with V-Y plasty
The most commonly described technique[11][12][13]:
- Penopubic incision with an inverted V-shaped skin flap.
- Division of the suspensory ligament down to the pubic symphysis, with attention to the external pudendal vessels near the fundiform base and the dorsal neurovascular bundle beneath the median suspensory blade.[22] Chen et al. describe a partial-release alternative in an anatomical model that preserves deep support fibers.[7]
- V-Y skin advancement to cover the newly exposed shaft and prevent retraction.
- Optional silicone spacer or fat flap in the dead space between the corpora and pubis.
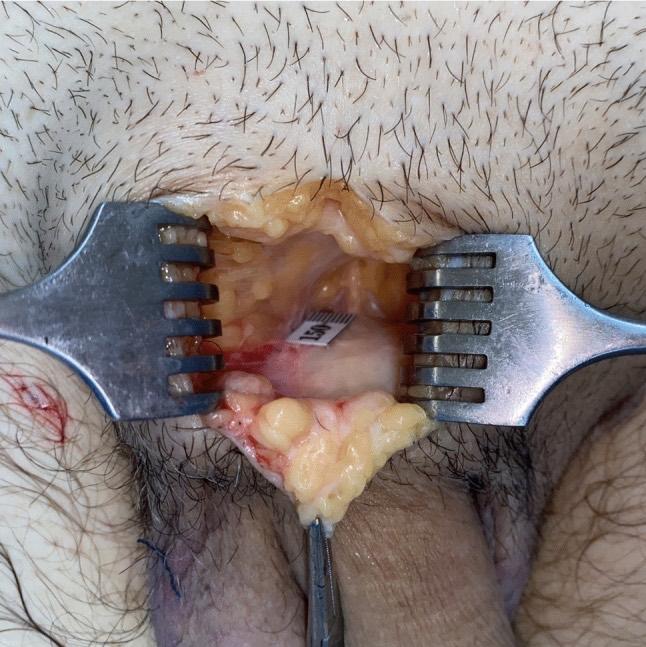
Suspensory ligament of the penis exposed in a cadaveric specimen after dissection of the abdominal subcutaneous tissue and its membranous layer, with a measuring tape placed beside the anterior border of the ligament. From Ramos M, et al. Aesthetic Plast Surg. 2024;48(8):1635–1643, Fig. 6 (CC BY 4.0).[9]
Deskoulidi & Caminer 2023: refined V-Y with distally based fat flaps advanced into the dead space and fat injections for simultaneous girth enhancement. In a report of 75 patients drawing on 15 years of experience, the authors reported +2–4 cm flaccid length gain, described complications as minimal, and noted that 3/75 (4%) returned for revision of fat injections at 6–12 months.[11] SMSNA separately advises against graft-and-flap penile augmentation outside a research protocol until further outcome data are available.[4]
Drawbacks of V-Y plasty: hypertrophic scarring 51% in one comparative study, plus visible "hump" at the penile base and potential for retraction.[14]
2. V-Y half-skin half-fat advancement flap with T-closure (Shaeer technique)
Designed to address the drawbacks of standard V-Y plasty[12]:
- The caudal half of the V-flap is deskinned, creating a rectangular fat flap.
- Suture the caudal ligament flap to Buck's fascia, then fill the penopubic gap with the deskinned fat flap and secure its deep surface and inferior edge to the pubis.[12]
- T-shaped closure to avoid pulling the penis back.
- Stay suture from glans to thigh maintains the penis in a stretched position postoperatively.
- In the reported case, gained length was maintained at six months, with no basal hump and a faint scar.[12]
3. Circumcision (subcoronal) ligamentolysis
Avoids the penopubic incision entirely.[14]
- Ligamentolysis through a subcoronal circumcision incision; penile skin degloved to access the suspensory ligament.
- No V-Y plasty required.
Mertziotis 2013 (n = 82; V-Y in the first 35 men, then subcoronal ligamentolysis in the next 47; sequential, not randomized): the authors described 79/82 men as having penile dysmorphophobia and three as having true micropenis.[14] A validated BDD diagnostic assessment was not reported; 79/82 also received free dermal-fat girth grafting, and stretching plus extender use were prescribed in both groups.[14]
| Outcome | V-Y plasty | Circumcision approach | p |
|---|---|---|---|
| Length / girth gain | similar | similar | — |
| OR time | 151 min | 125 min | 0.005 |
| Retraction | 11% | 6% | 0.453 |
| Hypertrophic scar | 51% | No major wound complications recorded | — |
| Satisfaction-score change at 12 mo | +2.54 | +4.02 | 0.007 (between-group change) |
| SEAR (Self-Esteem and Relationship) score change at 12 mo | +6.37 | +15.38 | < 0.001 (between-group change) |
4. Trans-scrotal approach (Karimian 2026)
Karimian et al. label 14 of 21 men as having BDD, five as having micropenis and two as having hypospadias. The SMSNA cosmetic-procedure statements concern men without penile dysmorphic disorder and call for that condition to be ruled out before invasive treatment.[1][4]
- Flaccid penile length +2.6 ± 1.66 cm (p < 0.05).
- Stretched penile length +2.4 ± 0.57 cm (p < 0.05).
- MGSIS improved significantly; IIEF-5 did not change. No major complications were reported.
5. Combined with adjuncts to prevent reattachment
- Acellular dermal matrix (ADM). Zhang 2019 treated 15 men with a small-sized or buried penis (mean BMI 28.9) with SLD, ADM filler and suprapubic liposuction; tip-to-skin length increased by 4.3 cm on the table and by 2.4 cm at 3 mo (p < 0.05).[15]
- Distally based fat flaps. Deskoulidi 2023.[11]
- Silicone spacer. Li 2006 series.[2]
Efficacy
| Study | n | Technique | Reported length change (measurement) | Erect Δ | Satisfaction | Follow-up |
|---|---|---|---|---|---|---|
| Li 2006 Eur Urol[2] | 42 | SLD ± silicone spacer | Mean +1.3 ± 0.9 cm stretched (range −1 to +3 cm) | NR | 35% overall; 27% in PDD | 6–78 mo |
| Deskoulidi-Caminer 2023 PRS[11] | 75 | SLD + V-Y + fat flaps | +2–4 cm | NR | improved sexual self-esteem | NR in accessible abstract (15 yr denotes surgeon experience) |
| Karimian 2026 Aesthetic Plast Surg[1] | 21 | Trans-scrotal SLD | +2.6 ± 1.66 cm flaccid; +2.4 ± 0.57 cm SPL | NR | MGSIS improved significantly | not specified |
| Mertziotis 2013 Asian J Androl[14] | 82 | V-Y (35) vs subcoronal (47) | similar | NR | greater satisfaction-score improvement with subcoronal approach (p = 0.007) | 12 mo |
| Zhang 2019 Andrologia[15] | 15 | SLD + ADM + liposuction | +2.4 ± 0.8 cm at 3 mo | NR | No patient reported dissatisfaction with appearance or function | 3 mo |
| Panfilov 2006 Aesthet Plast Surg[13] | 88 (31 with SLD) | Fat transfer; 31 also had SLD | +1.5–4.8 cm (mean 2.42) across the mixed cohort | NR | NR | not specified |
| Ramos 2024 cadaveric[9] | 16 | Complete ligamentolysis | +26.4 mm avg (range 4–60) | N/A | N/A | N/A |
Key efficacy patterns
- Vyas 2020 systematic review. Across 16 poor-quality studies of 1,192 men who received aesthetic augmentation phalloplasty, length gain ranged from 8% to 83% in the flaccid state and 12% to 53% in the erect state.[3] The ligament may contribute less to erect length because the corpora are already fully distended.
- Loss of on-table gain. In Zhang's 15 men, the 3-month gain (2.4 cm) was about 56% of the on-table gain (4.3 cm); scar contracture and retraction are the proposed explanations.[15]
- Spacers and fillers. In Li's series, a silicone spacer between pubis and penis was associated with a better stretched-length outcome (p < 0.05).[2] Rossi's uncontrolled SLD-plus-silicone-spacer series (245 men) reported mean gains of 2.5 cm flaccid and 1.9 cm stretched length.[21] Visits were scheduled through 48 months, but the paper does not give length means or denominators at each visit; it recorded wound infection in 6/245, pain lasting >2 months in 8/245, and one spacer removal 13 years after surgery following major weight loss.[21] Postoperative erect-length change and penile instability were not reported.[21][4] Spacers, fillers and fat flaps are intended to prevent ligament reattachment.[15]
SLD in combined operations
Aboul Fotouh 2022 J Sex Med prospective RCT (n = 61) comparing SLD plus pubic lipectomy via Z-plasty during malleable penile prosthesis implantation with conventional penoscrotal placement[16]:
- SLD group: +1.5 cm functional penile length (IQR 0–2) and +2.5 cm visible length (IQR 1–3.5) versus 0 cm in controls (p < 0.001), assessed at 3 months.
- IIEF satisfaction-domain scores and EDITS were higher in the SLD group (EDITS 95.4 vs 85.2, p < 0.001); satisfaction was assessed up to 1 year.
- Operative time was longer (170 vs 97.5 min). Complications in the combined SLD, pubic-lipectomy, Z-plasty and malleable-prosthesis group were penile edema (77.4%), instability (9.7%) and glans numbness (9.7%).[16]
Hardrock Sandwich Technique (HST)
Sertkaya 2025 Int J Impot Res retrospective series (n = 456, at least 1 year of follow-up), a composite of bovine pericardial graft, autologous plasma gel "sandwich", SLD, and placement of a half-testicular prosthesis at the divided ligament (see the dedicated HST page for the full evidence base)[17][27]:
- On postoperative day 1 after the combined procedure, mean girth increased 43.1% (+4.51 cm) and mean length increased 20.8% (+2.17 cm).[17]
- At one year, 83.4% reported improved satisfaction, 71.1% improved self-confidence, and 75.3% improved self-esteem.[17]
- Complications: seroma 6.1%, wound dehiscence 2.3%, infection 2.7%, hematoma 1.4%, skin necrosis 0.2%; no erectile dysfunction or ejaculation issues were reported in this cohort.[17]
Complications
SLD has a complication profile that non-surgical approaches lack.[18][3][16]
Reported complications
The Wessells figures below describe 12 men referred with complications after procedures elsewhere; all had SLD and 10 also had fat injection.[18]
- Penile retraction or loss of gained length. In Mertziotis’ sequential comparison at 12 months, retraction occurred in 4/35 men (11%) after V-Y plasty and 3/47 (6%) after subcoronal ligamentolysis; the authors discuss reattachment to the pubis as a mechanism.[14]
- Erection instability. Loss of support or a changed erection angle is a recognized risk after ligament division.[8][4] In a randomized trial combining SLD with pubic lipectomy, Z-plasty and malleable prosthesis placement, 9.7% of the intervention group had instability; this is a combined-procedure rate.[16]
- Altered erection angle. Downward or horizontal pointing rather than upward, can impair function.[12]
- Poor cosmetic appearance. Irregular fat nodules (58%), skin deformity or scarring (33%), scrotalization (33%) in the Wessells 1996 referral series.[18]
- Scrotalization. Scrotal skin advances onto the penile shaft, creating an unsightly appearance and shortening visible penis.[18]
- Wound complications. 50% in the Wessells 1996 series.[18]
- Sexual dysfunction. 33% in the same series.[18]
- Hypertrophic scarring. 51% with V-Y plasty (Mertziotis 2013).[14]
- Glans numbness. In the prosthesis RCT, 3/31 men (9.7%) in the combined SLD, pubic lipectomy, Z-plasty and malleable-implant arm had glans numbness.[16]
- De novo erectile dysfunction. A review of suspensory ligament repair for venogenic erectile dysfunction reports it in 3–5%; that is a different operation and population and is not a rate for cosmetic SLD.[8]
- Penile edema. In the prosthesis RCT, 24/31 men (77.4%) in the combined SLD, pubic lipectomy, Z-plasty and malleable-implant arm had postoperative edema.[16]
- Reoperation. Necessary in 50% of patients in the Wessells 1996 referral complication series.[18]
Pooled complication rate
Vyas 2020 systematic review: the pooled complication rate across all augmentation procedures was 14.6%, highest for combined length and girth procedures.[3]
Satisfaction — the central challenge
Patient satisfaction after SLD is highly variable and often disappointing, particularly in PDD patients.[2][18][3]
| Source | Satisfaction |
|---|---|
| Li 2006 overall (n=42) | 35%[2] |
| Li 2006 PDD subgroup | 27%[2] |
| Wessells 1996 referral complication series (n=12) | Satisfaction not reported; 1/12 (8%) reported subjective length increase[18] |
| Rossi 2022 SLD + silicone spacer (n=245; congenital or acquired short penis) | 200/245 (81.6%) completely satisfied (selection / reporting bias likely); mixed indications limit comparison with cosmetic/PDD cohorts.[21] |
| Vyas 2020 SR | 50–100% (inconsistent methodology)[3] |
The disconnect between objective length gains and subjective satisfaction is recurring. Li et al. concluded SLD "may increase penile length but usually not to a degree that satisfies the patient" and that men with PDD "should be encouraged to seek psychological help primarily, with surgery reserved as the last resort."[2]
Postoperative protocols to prevent retraction
Scar contracture and retraction erode length gains. Postoperative protocols aim to prevent them.
- Penile traction therapy (PTT). Mertziotis et al. began stretching in postoperative week two and prescribed an extender from about week six for several months, without isolating the extender's benefit.[14] Shaeer used a glans-to-thigh stay suture,[12] and Panfilov described postoperative bandaging after fat transfer with or without SLD.[13] See Penile Traction Therapy.
- Stay sutures. Temporary glans-to-thigh sutures during early postoperative period.[12]
- Spacer placement. Silicone spacer, ADM, or fat flap in the infrapubic dead space to physically prevent reattachment.[2][15][11]
SLD vs non-surgical penile lengthening
| Feature | SLD | Penile Traction Therapy | VED |
|---|---|---|---|
| Flaccid or stretched-flaccid length gain (different measurements) | +2.6 cm in one 21-man trans-scrotal SLD series; Li reported +1.3 cm in stretched-flaccid length[1][2] | <2 cm flaccid gain in a review restricted to men without penile abnormalities[28] | +0.3 cm mean stretched length at six months in 37 men with baseline stretched length <10 cm; not statistically significant[25] |
| Erect length gain | Not established for isolated SLD; 12–53% was reported across mixed augmentation procedures[3] | +0.5–1.5 cm | Not demonstrated |
| Onset | Immediate (surgical) | Gradual (3–6 mo) | N/A |
| Permanence | Long-term durability uncertain; retraction can reduce the gain[14] | Longer-term durability after stopping is uncertain[24] | Durability unestablished; no significant length gain at six months[25] |
| Invasiveness | Surgical (general / regional) | Non-invasive | Non-invasive |
| Complication rate | SLD-specific rate not established; 14.6% pooled across mixed augmentation operations[3] | Minimal (transient discomfort) | In one 37-man six-month vacuum study, hematoma in 1 and glans numbness in 1, both resolved spontaneously[25] |
| Satisfaction | 35% overall; 27% in PDD (Li, n = 42)[2]; 81.6% completely satisfied after SLD plus spacer (Rossi, n = 245)[21] | — | 30% after 6 months of vacuum treatment (Aghamir, n = 37)[25] |
| Effect on erection | May impair (erectile dysfunction, penile instability, altered angle)[4][12] | Among 54 men with penile-size concerns who chose an extender after counseling, 9/13 with mild baseline erectile dysfunction reported normal erectile function at nine months[29] | Erectile-function outcomes were not reported in the cited elongation study[25] |
| Reversibility | Irreversible | Reversible (stop use) | Reversible |
Limitations of evidence
- No RCTs comparing SLD to sham surgery or non-surgical alternatives for cosmetic penile lengthening.[3]
- Low-quality evidence.[19] In a review of 16 aesthetic augmentation studies involving 1,192 men, Vyas et al. reported poor patient-selection and outcome-reporting methods; 16% of men underwent length-only procedures.[3]
- Inconsistent outcome reporting. Different measurement techniques, time points, satisfaction instruments.[3]
- Publication bias. Complications likely under-reported; the Wessells 1996 referral series remains one of the few studies specifically documenting them.[18]
- Limited long-term data. Vyas et al. reported follow-up ranging from 6 to 48 mo across 16 studies of mixed aesthetic augmentation procedures and judged outcome reporting poor.[3]
- No standardized surgical technique. Approaches vary widely.[3][10]
- Patient-selection criteria are not standardized. Proportion of PDD versus true micropenis versus other indications varies across studies.[20]
Where SLD fits
Clinical SLD series report length gains using different measurements: Li et al. found +1.3 cm in stretched-flaccid length and Karimian et al. found +2.6 cm in flaccid length; adjunctive series report larger gains.[2][1][11][13] It carries risks of erection instability, retraction, poor cosmetic outcomes and low satisfaction in penile dysmorphic disorder. The 2026 EAU guideline weakly recommends suspensory ligament release for congenital intrinsic penile shortness and strongly recommends discussing possible complications; its management algorithm also lists SLR for men with normal penile size when body dysmorphic disorder is not suspected after psychosexual assessment.[23] The SMSNA 2024 statement calls for a discussion of these complications and for exclusion of body dysmorphic disorder before invasive treatment.[2][18][3][8][4][20] The 2026 ICSM consensus recommends counseling about the high likelihood of additional procedures for suboptimal cosmesis or functional complications.[24] For cosmetic penile augmentation in adults without structural or functional penile abnormalities, BAUS/AGUS 2026 strongly recommends comprehensive medical, surgical and psychosexual assessment with focused examination and validated psychometric measures, with psychological referral when the assessment indicates it; it recommends against surgical techniques, including suspensory-ligament release, because high-quality supporting evidence is lacking.[26]
See Also
Cosmetic Genital Surgery — Male · Small Penis Syndrome / PDD · Penile Traction Therapy · HA Filler — Penile Girth · PLA Filler — Penile Girth
References
1. Karimian B, Shamshirgaran A, Farsani RM, Mohammadi A, Aghamir SMK. Trans-scrotal suspensory ligament release: a novel technique for penile length augmentation. Aesthetic Plast Surg. 2026;50(3):1431-1438. doi:10.1007/s00266-025-05053-x
2. Li CY, Kayes O, Kell PD, et al. Penile suspensory ligament division for penile augmentation: indications and results. Eur Urol. 2006;49(4):729-733. doi:10.1016/j.eururo.2006.01.020
3. Vyas KS, Abu-Ghname A, Banuelos J, Morrison SD, Manrique O. Aesthetic augmentation phalloplasty: a systematic review of techniques and outcomes. Plast Reconstr Surg. 2020;146(5):995-1006. doi:10.1097/PRS.0000000000007249
4. Trost L, Khera M, Köhler T, et al. Cosmetic penile enhancement procedures: an SMSNA position statement. J Sex Med. 2024;21(6):573-578. doi:10.1093/jsxmed/qdae045
5. Mariani UM, Fayman M, Nkomozepi P, Ihunwo AO, Mazengenya P. Topographic and structural anatomy of the suspensory ligament of the penis: implications for phalloplasty. Aesthet Surg J. 2024;44(5):516-526. doi:10.1093/asj/sjad376
6. Hoznek A, Rahmouni A, Abbou C, Delmas V, Colombel M. The suspensory ligament of the penis: an anatomic and radiologic description. Surg Radiol Anat. 1998;20(6):413-417. doi:10.1007/BF01653133
7. Chen X, Wu Y, Tao L, et al. Visualization of penile suspensory ligamentous system based on visible human data sets. Med Sci Monit. 2017;23:2436-2444. doi:10.12659/msm.901926
8. Liu W, Calopedos R, Blecher G, Love C. Penile suspensory ligament: anatomy, function, and clinical perspectives of its repair. J Sex Med. 2025;22(1):175-183. doi:10.1093/jsxmed/qdae166
9. Ramos M, Varanda Pereira A, Silva L, Inácio AR, Álvares Furtado I. Morphometric predictors of penile length increase after division of its suspensory ligament. Aesthetic Plast Surg. 2024;48(8):1635-1643. doi:10.1007/s00266-023-03837-7
10. Zaccaro C, Subirà D, López-Diez I, et al. History and future perspectives of male aesthetic genital surgery. Int J Impot Res. 2022;34(4):327-331. doi:10.1038/s41443-022-00580-6
11. Deskoulidi PI, Caminer D. Lengthening phalloplasty with division of the suspensory ligament and distally based fat flaps in penis enlargement operations. Plast Reconstr Surg. 2023;152(3):434e-437e. doi:10.1097/PRS.0000000000010313
12. Shaeer O, Shaeer K, el-Sebaie A. Minimizing the losses in penile lengthening: "V-Y half-skin half-fat advancement flap" and "T-closure" combined with severing the suspensory ligament. J Sex Med. 2006;3(1):155-160. doi:10.1111/j.1743-6109.2005.00105.x
13. Panfilov DE. Augmentative phalloplasty. Aesthetic Plast Surg. 2006;30(2):183-197. doi:10.1007/s00266-004-0153-y
14. Mertziotis N, Kozyrakis D, Bogris E. Is V-Y plasty necessary for penile lengthening? Girth enhancement and increased length solely through circumcision: description of a novel technique. Asian J Androl. 2013;15(6):819-823. doi:10.1038/aja.2013.58
15. Zhang X, Huang Z, Xiao Y, et al. Suspensory ligament release combined with acellular dermal matrix filler in infrapubic space: a new method for penile length augmentation. Andrologia. 2019;51(9):e13351. doi:10.1111/and.13351
16. Aboul Fotouh El Gharably M, Ghoneima W, Lotfi MA, et al. The efficacy of suspensory ligament release and pubic lipectomy via penopubic Z plasty during penile prosthesis implantation in improving sexual satisfaction: a prospective randomized controlled trial. J Sex Med. 2022;19(5):852-863. doi:10.1016/j.jsxm.2022.02.024
17. Sertkaya Z, Albayrak AT, Başağa Y, Sökmen D. A retrospective evaluation of the safety and effectiveness of an innovative penile enlargement approach: the Hardrock Sandwich Technique. Int J Impot Res. 2025. doi:10.1038/s41443-025-01172-w
18. Wessells H, Lue TF, McAninch JW. Complications of penile lengthening and augmentation seen at 1 referral center. J Urol. 1996;155(5):1617-1620. doi:10.1016/s0022-5347(01)66144-5
19. Manfredi C, Romero Otero J, Djinovic R. Penile girth enhancement procedures for aesthetic purposes. Int J Impot Res. 2022;34(4):337-342. doi:10.1038/s41443-021-00459-y
20. Schifano N, Cakir OO, Castiglione F, Montorsi F, Garaffa G. Multidisciplinary approach and management of patients who seek medical advice for penile size concerns: a narrative review. Int J Impot Res. 2022;34(5):434-451. doi:10.1038/s41443-021-00444-5
21. Rossi A, Alei G, Frisenda M, et al. "Penile lenghthening original technique using a pubo-cavernous spacer. Long term results from a series of over 200 patients." Arch Ital Urol Androl. 2022;94(3):339–344. doi:10.4081/aiua.2022.3.339
22. Filipoiu FM, Ion RT, Filipoiu ZF, Tulin AD, Enciu O, Enyedi M. "Suspension of the penis – dissection, anatomical description and highlighting of anatomical risks in sectioning the suspensory ligaments." Basic Clin Androl. 2023;33:26. doi:10.1186/s12610-023-00202-1
23. European Association of Urology. "Penile Size Abnormalities and Dysmorphophobia." EAU Guidelines on Sexual and Reproductive Health. 2026, §9.3.2.b. Guideline
24. Chung E, Jenkins L, Moon DG, et al. "Penile augmentation and cosmetic surgery: recommendations from the Fifth International Consultation on Sexual Medicine (ICSM 2024)." Sex Med Rev. 2026;14(1):qeaf067. doi:10.1093/sxmrev/qeaf067
25. Aghamir SMK, Hosseini R, Alizadeh F. "A vacuum device for penile elongation: fact or fiction?" BJU Int. 2006;97(4):777–778. doi:10.1111/j.1464-410X.2006.05992.x
26. Mubarak M, Kalejaiye O, Kumar V, et al. "British Association of Urological Surgeons (BAUS) consensus document on male genital augmentation and enhancement procedures." J Clin Urol. 2026;19(2):149-166. doi:10.1177/20514158251391054
27. Sertkaya Z, Sökmen D, Albayrak AT, Başağa Y. "A Novel Technique for Elective Penile Enlargement Surgery: The Hardrock Sandwich Technique." J Sex Med. 2025;22(Suppl 2):qdaf077.246. doi:10.1093/jsxmed/qdaf077.246
28. Marra G, Drury A, Tran L, Veale D, Muir GH. "Systematic Review of Surgical and Nonsurgical Interventions in Normal Men Complaining of Small Penis Size." Sex Med Rev. 2020;8(1):158-180. doi:10.1016/j.sxmr.2019.01.004
29. Nowroozi MR, Amini E, Ayati M, Jamshidian H, Radkhah K, Amini S. "Applying extender devices in patients with penile dysmorphophobia: assessment of tolerability, efficacy, and impact on erectile function." J Sex Med. 2015;12(5):1242-1247. doi:10.1111/jsm.12870