Prostate Artery Embolization (PAE)
Prostate artery embolization (PAE) is a minimally invasive interventional-radiology procedure that selectively occludes the prostatic arterial supply to induce ischemic necrosis and infarction of the prostatic adenoma. Case series report volume reduction of about 25–40% at 3–12 months. PAE does not remove tissue; the adenoma shrinks through devascularization.[1][2][3]
For positioning versus other BPH MISTs and surgical alternatives, see the BPH & Male LUTS chooser.
The AUA 2026 BPH guideline states that clinicians may offer PAE with particle embolics to patients with LUTS/BPH and prostates of 50 cc or larger .[22] Its trials used particle embolics, and the guideline states that the efficacy and safety of liquid embolics remain unknown. It calls for urologic assessment before PAE to confirm that LUTS are due to BPH , performance by an interventional radiologist specifically trained in PAE , and counseling about radiation exposure .[22] The 2023 Amendment had rated PAE Conditional, Grade C, for clinicians trained in the procedure, and found no substantial evidence to recommend it over more widely available MISTs.[4] EAU 2026 weakly recommends offering PAE to men with moderate-to-severe LUTS who want a minimally invasive option and accept less optimal outcomes than with TURP, and it lists PAE as still under investigation. EAU strongly recommends that PAE be done only in units where urologists work with trained interventional radiologists to select patients and follow them.[23]
Mechanism of action
Selective occlusion of the prostatic arterial supply causes ischemic necrosis and infarction of the adenoma. Prostate volume then falls progressively (25–40% in case series), which is proposed to lower intraurethral pressure and relieve obstruction.[1][2][3]
Preprocedural evaluation
| Component | Detail |
|---|---|
| Clinical | IPSS, QoL, IIEF, uroflowmetry (Qmax), PVR, DRE |
| Laboratory | PSA, urinalysis, BMP, coagulation studies |
| Imaging | CT angiography (CTA) of the pelvis maps the prostatic arterial anatomy, identifies variants, assesses atherosclerotic disease and determines catheterizability. MR angiography is an alternative. Prostate volume by TRUS or MRI.[5][6][7] |
| Exclusion criteria | CTA-demonstrated prostatic arteries not amenable to PAE; active UTI; neurogenic bladder; severe atherosclerotic disease or iliac tortuosity precluding access[4][7]. SIR 2026 lists suspected or known prostate cancer that has not been evaluated or managed among general contraindications; men on active surveillance are not categorically excluded.[24] The Embosphere IFU specifically contraindicates prostate cancer, bladder cancer or stones, chronic renal failure, and obstruction from non-BPH causes such as urethral stricture.[27] |
A 2025 Delphi consensus of 14 international experts (Rostambeigi 2025 JVIR) set recommendations across six procedural domains: preprocedural imaging, antibiotic prophylaxis, arterial access, prostatic artery identification and cannulation, embolization technique, and non-target embolization prevention.[5]
Procedural technique
Access and angiography
- Local anesthesia, usually with conscious sedation. Plan periprocedural antibiotic prophylaxis with the interventional radiologist under the local protocol; SIR 2026 notes that regimens vary and comparative evidence is not definitive.[24]
- Arterial access via femoral (most common) or radial puncture.
- DSA of bilateral internal iliac arteries to map prostatic supply.
- Cone-beam CT (CBCT) helps identify prostatic supply and potential nontarget branches.[2][8][9][6] Selective angiography assesses rectal, penile and bladder anastomoses; protective embolization or an antireflux microcatheter is used for high-flow anastomoses or reflux toward nontarget vessels when indicated.[6]
Prostatic artery anatomy
The prostatic artery most commonly arises from the internal pudendal artery or the inferior vesical artery, with numerous variants. Bilateral catheterization is the goal; unilateral PAE is associated with significantly higher recurrence (42% versus 21%).[3][6] Anatomic considerations:
- Shared origins with superior vesical, obturator, or internal pudendal arteries
- Anastomoses with rectal, penile, and bladder arteries (risk of non-target embolization)
- Accessory prostatic branches and collaterals should be identified during PAE[6][10]
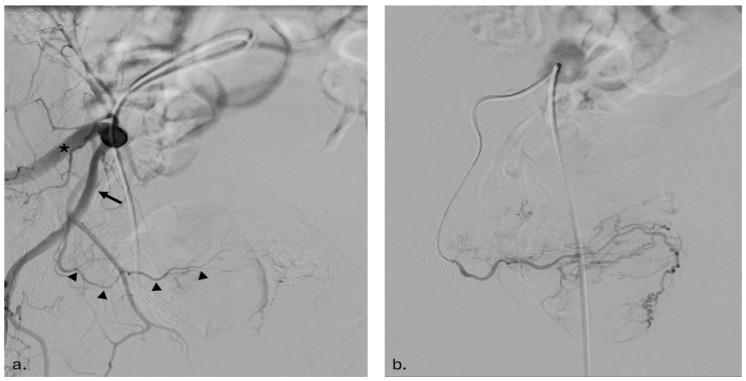
Right internal iliac artery angiography. (a) Selective angiography of the right internal iliac artery in an ipsilateral oblique projection separates the anterior division trunk (arrow), which typically gives rise to the prostatic artery (arrowheads), from the posterior division trunk (asterisk), which gives rise to parietal muscular branches. (b) Super-selective angiography of the ipsilateral prostatic artery through a 1.9 Fr catheter with an injector (10 mL of contrast at 2 mL/s; 600 psi), used to identify anastomoses with non-target vessels such as rectal or penile arteries. From Iossa V, et al. J Clin Med. 2025;14(11):3775, Figure 2 (CC BY).[10]
Embolization
Super-selective microcatheterization positions the catheter tip within or at the ostium of the prostatic artery. SIR 2026 and technical reports describe angiographic stasis as an embolization endpoint,[2][9][11][24] whereas the Embosphere IFU directs stopping before complete prostatic-artery stasis as flow diminishes to reduce retro-migration.[27]
Embolic agents
| Agent | Size | Notes |
|---|---|---|
| Tris-acryl gelatin microspheres (Embosphere) | 300–500 µm | Most widely used in RCTs[2][4] |
| PVA microspheres (Bead Block) | 300–500 µm | Calibrated spherical particles[3] |
| Non-spherical PVA particles | 45–150 or 150–250 µm | Used in some European centers (PROEMBO trial)[7] |
| Smaller microspheres | 100–300 µm | More distal penetration; used in 80% of cases in one large series.[12] In a randomized particle-size trial, 100–300 µm spheres did not improve 18-month clinical success over 300–500 µm spheres and caused more mild adverse events (37/43 vs 19/46).[28][24] |
| NBCA glue (cyanoacrylate) | Liquid | Mixed with ethiodized oil; 100% technical success in 186 patients in a retrospective single-center cohort (Loffroy 2026). Its use for PAE is off label in the United States.[13][24] |
| EVOH (Onyx-type) | Liquid | 88% clinical success at 3 mo in a retrospective single-center series; Prostatic EVOH Penetration Score (PEPS): success in 100% with high and 0% with low scores[14] |
The PErFecTED technique
PErFecTED (Proximal Embolization First, Then Embolize Distal) is a two-step approach described by Carnevale in 2014 to increase prostatic ischemia:[11]
- Step 1 (Proximal): advance the microcatheter past collateral branches and position it within the prostatic artery before its branching; embolize slowly to near stasis. Selective embolization of the urethral group (which supplies the periurethral adenoma) precedes the capsular group after advancing into intraprostatic branches in Step 2.[11]
- Step 2 (Distal). At near stasis, inject contrast to check for newly apparent collateral shunts before advancing the microcatheter into intraprostatic branches. Slowly deliver additional embolic material to achieve distal stasis, avoiding reflux and injection through a wedged catheter. Retract to the arterial origin for the final control angiogram.[11]
The authors, in a technical report without a comparison group, described infarcts in all patients after adding the second step and lower recurrence than with earlier methods.[11]
Emerging adjuncts
- NBCA glue. Loffroy 2026 (retrospective, n = 186): IPSS 20.1 to 10 at 12 mo; volume 118 to 81 mL; no major complications; IIEF-5 unchanged.[13]
- EVOH (Onyx-type). Guerra 2026 (retrospective, n = 73): 88% clinical success at 3 mo; clinical success in all 57 patients with a high PEPS and none of 5 with a low PEPS.[14]
- "Coil-out". Adjunctive coil occlusion of the prostatic artery after particle embolization to prevent recanalization has been described.[5]
The AUA 2026 guideline notes limited prospective evidence for liquid embolics.[22]
Procedural parameters
| Metric | Typical range |
|---|---|
| Procedure time | Mean 71.3 min among 38 sham-to-PAE crossovers in a sham-controlled trial[4][33] and 122.2 min in a PAE–TURP trial[31]; 26.1% lower in 2023 than 2019 in a 551-procedure retrospective single-center series[12] |
| Fluoroscopy time | Mean 19.4 min among 38 sham-to-PAE crossovers in a sham-controlled trial[4][33] and 50.8 min in a PAE–TURP trial[31]; 25.2% lower in 2023 than 2019 in a 551-procedure retrospective single-center series[12] |
| Radiation output / estimated effective dose | One sham-controlled trial reported a dose–area product of 247.9 ± 153.8 Gy·cm².[4] In a 10-center cohort of 1,345 fixed-unit cases, median kerma–area product was 161.8 Gy·cm² (IQR 92.7–253.6) and median estimated effective dose was 17.8 mSv (IQR 10.2–27.9).[30] |
| Bilateral embolization achieved | 80.7% (96/119) in PROEMBO[7]; approximately 85–90% in SIR guidance[24] |
| Technical success | Bilateral embolization about 85–90%, with one study reporting 75% (AUA 2026)[22] |
| Setting | Outpatient in most cases. A temporary Foley may be used for angiographic orientation; place a Foley if acute urinary retention develops after PAE.[11][6] |
Clinical efficacy
| Outcome | Result | Follow-up |
|---|---|---|
| IPSS improvement | −9 points in Alizadeh's 551-procedure retrospective series[12]; mean maximum improvement of 16 points in Carnevale's 317-patient cohort[3]; median 5-point reduction (IQR 2–12) among 68 with 12-month IPSS data of 119 enrolled in PROEMBO[7] | Carnevale: study follow-up 3–96 mo; PROEMBO: 12 mo |
| QoL improvement | −2 to −4 points | 3–96 mo |
| Qmax improvement | +6 mL/s mean maximum improvement in the Carnevale PAE cohort[3] | Study follow-up 3–96 mo (mean 27 mo) |
| Prostate volume reduction | 39% mean maximum in the Carnevale series[3] | Study follow-up 3–96 mo |
| PSA reduction | About 24% on average in the Dias review[6] | Not specified |
| Clinical success (definitions vary) | 88% (64/73) with EVOH: IPSS < 18 with ≥25% decrease and QoL ≤3 with ≥1-point decrease[14] | 3 mo |
| Catheter-free or voiding-trial success (retention patients) | 84% (63/75) of evaluable patients passed voiding trials and remained catheter-free at last follow-up (mean 611 d) in Powell's cohort[16]; 94% (119/126) in Bhatia's retention cohort were catheter-free at 3 mo[15]; 65.8% (48/73) in a prospective multicenter acute-retention cohort were catheter-free by 3 mo and remained so through 24 mo[29] | Powell: mean 611 d; Bhatia: 3 mo; prospective registry: 24 mo |
| BPO medication-free rate | 65.5%[15] | 1 yr |
Sources for the table: AUA 2023 amendment[4]; Cochrane 2022[2]; Carnevale 10-yr[3]; Dias 2021 review[6]; Bhatia 1,075-pt series[15]; Guerra 2026 EVOH[14]; Powell 2021[16]. The ranges mix randomized, retrospective and single-arm data.
In the Bhatia 2025 retrospective single-center series (n = 1,075, mean follow-up 458 d), the LUTS subgroup had a median IPSS of 9 at 48–60 mo versus a median of 23 before PAE across the cohort.[15]
In the Carnevale 2020 single-center series (n = 317; mean follow-up 27 months, range 3–96), the mean maximum IPSS improvement was 16 points, prostate-volume reduction was 39%, and Qmax improvement was 6 mL/s. Early clinical failure was 1.9%; 72/317 men (23%) met the study's treatment-defined LUTS recurrence endpoint after month 3 (34 restarted an alpha-blocker, 26 underwent TURP and 12 repeat PAE), with a median time to recurrence of 72 months among those who recurred.[3]
Voiding versus storage symptoms: PAE improves voiding more than storage. Among LUTS patients with analyzable IPSS component scores (n = 137 overall), mean relative improvement at 1 month was 69% for voiding versus 46% for storage symptoms (p < 0.000001).[16]
Durability and retreatment — the central limitation
Retreatment is the main limitation against surgical alternatives:
- Cochrane 2022. PAE likely increases retreatment versus TURP (RR 3.20, 95% CI 1.41–7.27 at up to 12 months; RR 3.80, 95% CI 1.32–10.93 at 13–24 months from one RCT; moderate certainty).[2]
- Abt 2-yr RCT. 10 PAE patients (21%) required TURP within 2 yr because of unsatisfying outcomes.[17]
- Carnevale single-center series. Symptom recurrence occurred in 72/317 men (23%) during mean 27-month follow-up; median time to recurrence among those who recurred was 72 months. Recurrence was observed in 8/19 after unilateral versus 64/298 after bilateral PAE (42% versus 21%; p = 0.04). Higher baseline PSA was inversely associated with recurrence (HR 0.9 per ng/mL).[3]
- Bhatia 1,075-pt series. 16% of reintervention-eligible patients required a second prostatic intervention up to 60 mo.[15]
- Prospective PROstate registry. Of 478 men treated at 14 centers for LUTS or acute retention, 16 (3.3%) underwent repeat PAE and 32 (6.7%) underwent surgery or another MIST within 24 mo. These are separately reported outcomes from a single-arm cohort with incomplete follow-up.[29]
- A 2025 narrative review estimated retreatment at approximately 1 in 5 at 2 yr and nearly half at 5 yr in long-term randomized follow-up.[18] In the underlying single-center trial, 20/48 (42%) men treated with PAE underwent TURP by five years. Only 18/48 PAE and 38/51 TURP recipients were assessed at 60 months: IPSS improved by 7.8 versus 11.6 points (between-group p = 0.092), Qmax increased by 3.6 versus 9.3 mL/s, and PVR fell by 28 versus 220 mL; the objective measures favored TURP.[25] Conversion and attrition limit interpretation of the five-year symptom comparison.[23][25]
Comparison with TURP
| Parameter | PAE | TURP |
|---|---|---|
| IPSS improvement (12 mo) | −9 to −13 | −12 to −15 |
| Qmax improvement (2 yr) | +3.9 mL/s | +10.2 mL/s |
| PVR reduction (2 yr) | −62 mL | −204 mL[17] |
| Prostate volume reduction (2 yr) | −10.7 mL | −30.2 mL[17] |
| Further surgery at 2 yr | 10/48 (21%) crossed over to TURP; 1/48 (2%) had another procedure[17] | 5/51 (10%) had another procedure[17] |
| Total adverse events | Fewer (43 vs 78, p = 0.005) | More |
| Ejaculatory preservation | Better | Worse |
| Erectile function | Similar | Similar |
| Hospital stay in the Abt trial | Mean 2.2 days (SD 0.6)[31] | Mean 4.2 days (SD 1.7)[31] |
| Anesthesia | Conscious sedation | Spinal / general |
References: AUA 2023 sham + TURP RCT data[4]; Cochrane 2022[2]; Abt 2-yr RCT[17].
In the Abt single-center, open-label RCT (103 randomized; 48 PAE and 51 TURP participants with primary-outcome data), IPSS fell 9.23 points after PAE and 10.77 after TURP at 12 weeks, and noninferiority within the 3-point margin was not shown (95% CI −1.45 to 4.52).[31] At 2 years, TURP was superior for IPSS (difference 2.88, p = 0.047; a protocol-defined secondary endpoint without correction for multiple testing) and Qmax (difference −6.33 mL/s). PAE had fewer adverse events, although the distribution across severity classes was similar.[17]
PAE vs medical therapy — the PARTEM trial
PARTEM (Sapoval 2023, multicenter RCT, n = 90) compared PAE to dutasteride and tamsulosin combination therapy in BPH ≥ 50 mL resistant to alpha-blocker monotherapy:[19]
- IPSS improvement at 9 mo: −10.0 (PAE) versus −5.7 (CT); difference −4.4, p = 0.0008.
- IIEF-15 change: +8.2 (PAE) versus −2.8 (CT).
- No PAE-related serious adverse events or hospitalizations.
- Between months 9 and 24, 5/42 PAE patients underwent prostatic surgery; 18/38 combined-therapy patients underwent an invasive treatment (14 PAE and 4 prostatic surgeries).[19]
P-EASY ADVANCE (2024) separately randomized 39 treatment-naive men with enlarged prostates and obstructed or equivocal urodynamics to PAE or tamsulosin–dutasteride. At first follow-up urodynamics, 12/19 (63%) after PAE versus 4/14 (28%) after medication were unobstructed (p = 0.03), and IPSS, Qmax and quality of life improved more after PAE. The small groups and unequal mean timing of follow-up urodynamics (9.7 versus 7.4 mo) limit generalization to routine first-line use.[32]
Safety and complications
Severe adverse events under the SIR severity classification occurred in 0.65% (7/1,075) in the Bhatia retrospective series.[15] In a separate prospective 14-center registry, 10/478 (2.1%) men experienced a serious adverse event under a different event definition.[29] The Bhatia events were:
- TIA 0.3% (3/1,075)[15]
- Urosepsis 0.2% (2/1,075; treated with IV antibiotics)[15]
- Prostate sloughing requiring TURP 0.2% (2/1,075)[15]
- All resolved without permanent sequelae.[15]
Reported minor adverse events vary across studies.[2] Alizadeh et al. reported 16 minor complications among 551 PAE interventions (2.9%),[12] while Loffroy et al. reported minor adverse events in 35/186 patients (18.8%) after NBCA PAE.[13]
- Postembolization syndrome (pain, dysuria, frequency, low-grade fever) is the most common and resolves within about 1 wk with symptomatic management.[20][22]
- Perineal pain 9.4% (Feng 2017, as summarized by Cochrane 2022)[2]
- Hematuria 9% (Feng 2017, as summarized by Cochrane 2022)[2]
- Acute urinary retention 7% (Feng 2017); up to 28.4% in one included series (Wang 2015), as summarized by Cochrane 2022[2]
- Hematospermia, rectal bleeding, UTI, inguinal hematoma, transient frequency
Non-target embolization of the bladder, rectum, corpus cavernosum or penile arteries is the main technical concern; the AUA 2026 guideline reports it as rare (under 1%).[22] CBCT helps identify and avoid non-target vessels. In the EVOH series, 8 non-target embolizations were identified in 7 of 73 patients (10%); all were asymptomatic.[14]
Sexual function. Series report no significant change in IIEF-5, and ejaculatory disorders were less frequent with PAE than TURP in Cochrane low-certainty evidence.[2][3][12][13] In the open-label PARTEM trial, IIEF-15 rose by 8.2 points with PAE.[19]
SIR multisociety consensus recommendations
The McWilliams 2019 SIR multisociety consensus (with CIRSE, SFR and BSIR, and endorsed by six other societies) issued the positions and grades listed below. SIR published updated PAE practice guidance in 2026 covering patient selection, technique, periprocedural care, outcomes, and safety.[20][24]
- PAE is an acceptable minimally invasive treatment for appropriately selected men with moderate-to-severe LUTS (Level B, strong).
- PAE may be considered for very large prostates > 80 cm³ without an upper size limit (Level C, moderate).
- PAE may be considered for acute or chronic urinary retention with preserved bladder function (Level C, moderate).
- PAE may be considered for patients wishing to preserve erectile and/or ejaculatory function (Level C, weak).
- PAE may be considered for hematuria of prostatic origin (Level D, strong).
- PAE may be considered for patients not surgical candidates due to age, comorbidity, coagulopathy, or inability to stop anticoagulation (Level E, moderate).
Predictors of success
- Larger prostate volume was the strongest predictor in the cited analyses; patients with prostates > 80 cm³ showed more IPSS improvement (14 versus 10.5 points), Qmax improvement and PVR reduction.[20] In a post hoc analysis of 48 PAE-treated trial patients, exploratory ROC thresholds for a 12-week IPSS decrease of at least 8.8 points were total prostate volume ≥ 39 mL and central gland volume ≥ 38 mL.[21]
- Higher central-gland index (central gland / total prostate volume) correlates with greater Qmax improvement (rs = 0.46, p = 0.003).[21]
- Bilateral embolization over unilateral (recurrence 21% versus 42%).[3]
- Higher baseline PSA inversely related to recurrence (HR 0.9 per ng/mL; likely reflects larger adenoma burden).[3]
- Postprocedural pain and PSA / CRP elevation may serve as early outcome predictors (possibly reflecting adequate ischemia).[21]
- Atherosclerotic plaque burden and iliac tortuosity predict technical failure but not clinical outcome.[7]
- In a retrospective, single-center EVOH series of 73 men, PEPS category was associated with three-month clinical success (57/57 high, 7/11 medium, 0/5 low).[14]
Ideal patient profile
- Moderate-to-severe LUTS (IPSS 8–35) with benign prostatic obstruction in a man who wants a minimally invasive option and accepts less optimal outcomes than TURP. The EAU 2026 recommendation is weak and does not require prior medical-therapy failure; SIR 2026 permits selected men to choose PAE before a medication trial.[23][24]
- Larger prostates (50 mL or more; the AUA 2026 guideline notes that trials enrolled prostates of 50 cc or larger)[22]
- Patients prioritizing erectile or ejaculatory function[20]; counsel separately about future fertility because the Embosphere IFU says PAE should not be performed in men who want to father a child while fertility effects remain undetermined.[27]
- High surgical risk (advanced age, comorbidity, anticoagulation)
- Selected patients with BPH-related urinary retention and preserved bladder function seeking catheter independence.[20]
- Patients with prostatic hematuria
- Favorable vascular anatomy on CTA (accessible prostatic arteries; minimal atherosclerosis / tortuosity)
Advantages and limitations
Advantages
- Usually outpatient under local anesthesia with moderate sedation.[23][16]
- No transurethral prostate resection; general anesthesia is used in selected patients.[16]
- Sexual function preservation
- No upper limit on prostate size
- Fewer total adverse events than TURP in one two-year randomized trial (43 vs 78 events), with a similar distribution of event severity.[17]
- SIR 2019 says PAE may be considered for men with moderate-to-severe BPH/LUTS who are not surgical candidates because anticoagulation or antiplatelet therapy cannot be stopped (Level E, moderate).[20]
- Greater IPSS improvement than dutasteride-tamsulosin in alpha-blocker-resistant BPH of 50 mL or more at 9 months (PARTEM)[19]
Limitations
- Cochrane 2022 found higher retreatment after PAE than TURP at up to 24 months. EAU 2026 reports that 42% of men who received PAE underwent TURP within five years in one randomized trial.[23] In separate retrospective cohorts, 90 men (16% of reintervention-eligible patients; mean follow-up 458 days) underwent a second prostatic procedure, with events observed up to 60 months, while 72/317 men (23%; mean follow-up 27 months) had symptom recurrence; these are different endpoints.[2][3][15][23]
- Less objective improvement in Qmax and PVR versus TURP.[17] In the PoPAE randomized trial of prostates >80 cc with confirmed obstruction and preserved detrusor contractility, 70% of 23 PAE recipients remained obstructed at six months, whereas 88% of 25 open-simple-prostatectomy recipients were unobstructed or equivocal; IPSS and PVR reductions were similar.[26]
- Technically demanding; steep learning curve
- Radiation exposure (fluoroscopy); an EAU-cited systematic review of 22 studies estimated a median 0.117% cancer-death risk for a 66-year-old, equivalent to about 5.4 days of life expectancy, with a 20-fold range in exposure between centers[23]
- In PROEMBO, bilateral embolization was not achieved in 23/119 patients: 18/119 underwent unilateral embolization and 5/119 had bilateral failure. Plaque burden and iliac tortuosity were associated with technical failure.[7]
- Limited long-term data (most RCTs ≤ 2 yr)
- Overall evidence certainty remains low to moderate
See Also
- BPH & Male LUTS chooser
- Rezūm (WVTT)
- Simple Prostatectomy: alternative for very large glands without retreatment-rate trade-off
- Prostate Enucleation / HoLEP
References
1. Picel AC, Hsieh TC, Shapiro RM, Vezeridis AM, Isaacson AJ. Prostatic artery embolization for benign prostatic hyperplasia: patient evaluation, anatomy, and technique for successful treatment. Radiographics. 2019;39(5):1526–1548. doi:10.1148/rg.2019180195
2. Jung JH, McCutcheon KA, Borofsky M, et al. Prostatic arterial embolization for the treatment of lower urinary tract symptoms in men with benign prostatic hyperplasia. Cochrane Database Syst Rev. 2022;3:CD012867. doi:10.1002/14651858.CD012867.pub3
3. Carnevale FC, Moreira AM, de Assis AM, et al. Prostatic artery embolization for the treatment of lower urinary tract symptoms due to benign prostatic hyperplasia: 10 years' experience. Radiology. 2020;296(2):444–451. doi:10.1148/radiol.2020191249
4. Sandhu JS, Bixler BR, Dahm P, et al. Management of lower urinary tract symptoms attributed to benign prostatic hyperplasia (BPH): AUA guideline amendment 2023. J Urol. 2024;211(1):11–19. doi:10.1097/JU.0000000000003698
5. Rostambeigi N, Sapoval M, Bilhim T, et al. Standardized technique for prostatic artery embolization: a Delphi consensus study on optimized methods and emerging concepts. J Vasc Interv Radiol. 2025;S1051-0443(25)00726-2. doi:10.1016/j.jvir.2025.10.033
6. Dias US, de Moura MRL, Viana PCC, et al. Prostatic artery embolization: indications, preparation, techniques, imaging evaluation, reporting, and complications. Radiographics. 2021;41(5):1509–1530. doi:10.1148/rg.2021200144
7. Schmidt VF, Grethen J, Pryadko M, et al. Pre- and periprocedural imaging predicts technical but not clinical success of prostatic artery embolization using non-spherical PVA particles — insights from the prospective PROEMBO trial. Acad Radiol. 2025;S1076-6332(25)00922-5. doi:10.1016/j.acra.2025.09.043
8. Franco JV, Jung JH, Imamura M, et al. Minimally invasive treatments for lower urinary tract symptoms in men with benign prostatic hyperplasia: a network meta-analysis. Cochrane Database Syst Rev. 2021;7:CD013656. doi:10.1002/14651858.CD013656.pub2
9. Uflacker AB, Haskal ZJ, Baerlocher MO, et al. Society of Interventional Radiology research reporting standards for prostatic artery embolization. J Vasc Interv Radiol. 2020;31(6):891–898.e1. doi:10.1016/j.jvir.2020.03.003
10. Iossa V, Punzi E, Pandolfo SD, et al. Prostate artery embolization (PAE) in the treatment of benign prostatic hyperplasia: a case series and narrative review. J Clin Med. 2025;14(11):3775. doi:10.3390/jcm14113775
11. Carnevale FC, Moreira AM, Antunes AA. The "PErFecTED technique": proximal embolization first, then embolize distal for benign prostatic hyperplasia. Cardiovasc Intervent Radiol. 2014;37(6):1602–1605. doi:10.1007/s00270-014-0908-z
12. Alizadeh LS, Radek D, Booz C, et al. Prostatic artery embolization: lessons from 551 procedures at a single-center. Acad Radiol. 2024;31(11):4519–4527. doi:10.1016/j.acra.2024.05.039
13. Loffroy R, Quirantes A, Tomassoni MT, et al. One-year outcomes of glue prostate-artery-embolization for symptomatic benign prostatic hyperplasia: a single-center retrospective cohort study. Eur Radiol. 2026;36(3):2317–2328. doi:10.1007/s00330-025-11983-6
14. Guerra X, Denis le Sève L, Pellerin O, et al. Prostatic artery embolization using ethylene vinyl alcohol copolymer (EVOH): efficacy, safety and clinical impact of liquid embolic penetration. Cardiovasc Intervent Radiol. 2026. doi:10.1007/s00270-026-04353-2
15. Bhatia S, Bhatia A, Richardson AJ, et al. Prostatic artery embolization: mid- to long-term outcomes in 1,075 patients. J Vasc Interv Radiol. 2025;36(3):456–466. doi:10.1016/j.jvir.2024.11.002
16. Powell T, Staib L, Liu B, et al. Voiding and storage domain-specific symptom score outcomes after prostate artery embolization for lower urinary tract symptoms and urinary retention. Urology. 2021;156:216–224. doi:10.1016/j.urology.2021.02.046
17. Abt D, Müllhaupt G, Hechelhammer L, et al. Prostatic artery embolisation versus transurethral resection of the prostate for benign prostatic hyperplasia: 2-yr outcomes of a randomised, open-label, single-centre trial. Eur Urol. 2021;80(1):34–42. doi:10.1016/j.eururo.2021.02.008
18. Dinc R. Promising minimally invasive option emerging in the treatment of benign prostatic obstruction: prostatic artery embolization. J Clin Med. 2025;14(24):8631. doi:10.3390/jcm14248631
19. Sapoval M, Thiounn N, Descazeaud A, et al. Prostatic artery embolisation versus medical treatment in patients with benign prostatic hyperplasia (PARTEM): a randomised, multicentre, open-label, phase 3, superiority trial. Lancet Reg Health Eur. 2023;31:100672. doi:10.1016/j.lanepe.2023.100672
20. McWilliams JP, Bilhim TA, Carnevale FC, et al. Society of Interventional Radiology multisociety consensus position statement on prostatic artery embolization for treatment of lower urinary tract symptoms attributed to benign prostatic hyperplasia. J Vasc Interv Radiol. 2019;30(5):627–637.e1. doi:10.1016/j.jvir.2019.02.013
21. Abt D, Müllhaupt G, Mordasini L, et al. Outcome prediction of prostatic artery embolization: post hoc analysis of a randomized, open-label, non-inferiority trial. BJU Int. 2019;124(1):134–144. doi:10.1111/bju.14632
22. Goueli R, Badlani GH, Welliver C, et al. Management of lower urinary tract symptoms attributed to benign prostatic hyperplasia: AUA guideline (2026). Statement 51, prostate artery embolization. American Urological Association; 2026.
23. European Association of Urology. EAU Guidelines on the Management of Non-neurogenic Male LUTS. 2026 (March update). See section 5.3.4.b (recommendations, weak for offering PAE, strong for urologist and interventional-radiologist collaboration).
24. Mouli S, Dolmatch BL, Gunn AJ, et al. "Society of Interventional Radiology (SIR) 2026 Practice Guidance Document for Prostatic Artery Embolization." J Vasc Interv Radiol. 2026 Jun 1:108771. doi:10.1016/j.jvir.2026.108771
25. Müllhaupt G, Hechelhammer L, Graf N, et al. "Prostatic artery embolisation versus transurethral resection of the prostate for benign prostatic obstruction: 5-year outcomes of a randomised, open-label, noninferiority trial." Eur Urol Focus. 2024;10(5):788–795. doi:10.1016/j.euf.2024.03.001
26. Lebani BR, Porto DDS, Silva ABD, et al. "Randomized controlled trial comparing open simple prostatectomy or prostate artery embolization in large prostates: clinical and urodynamic assessment - PoPAE study." Urology. 2024;189:94–100. doi:10.1016/j.urology.2024.04.024
27. Merit Medical. Embosphere Microspheres in a Sterile Vial: Instructions for Use (730060003EN). Manufacturer IFU.
28. Torres D, Costa NV, Pisco J, et al. "Prostatic artery embolization for benign prostatic hyperplasia: prospective randomized trial of 100–300 μm versus 300–500 μm versus 100- to 300-μm + 300- to 500-μm Embospheres." J Vasc Interv Radiol. 2019;30(5):638–644. doi:10.1016/j.jvir.2019.02.014.
29. Sapoval MR, Bhatia S, Déan C, et al. "Two-year outcomes of prostatic artery embolization for symptomatic benign prostatic hyperplasia: an international, multicenter, prospective study." Cardiovasc Intervent Radiol. 2024;47(11):1515–1524. doi:10.1007/s00270-024-03802-0.
30. Ayyagari R, Rahman SZ, Grizzard K, et al. "Multicenter quantification of radiation exposure and associated risks for prostatic artery embolization in 1476 patients." Radiology. 2024;310(3):e231877. doi:10.1148/radiol.231877.
31. Abt D, Hechelhammer L, Müllhaupt G, et al. "Comparison of prostatic artery embolisation (PAE) versus transurethral resection of the prostate (TURP) for benign prostatic hyperplasia: randomised, open label, non-inferiority trial." BMJ. 2018;361:k2338. doi:10.1136/bmj.k2338.
32. Brown N, Kiosoglous A, Castree S, et al. "The 'Prostate Embolisation AS first-line therapY compAred to meDication in treatment naïVe men with prostAte eNlargement, a randomised ControllEd trial' (P-EASY ADVANCE): a randomised controlled trial of prostate embolisation vs medication for BPH." BJU Int. 2024;134(Suppl 2):38–46. doi:10.1111/bju.16479.
33. Pisco JM, et al. "Randomised Clinical Trial of Prostatic Artery Embolisation Versus a Sham Procedure for Benign Prostatic Hyperplasia." Eur Urol. 2020;77(3):354–362. doi:10.1016/j.eururo.2019.11.010