Anatomical Enucleation of the Prostate
Prostate enucleation is the anatomic BPH operation in which the transition-zone adenoma is separated from the compressed peripheral and central-zone "surgical capsule" and removed as a shell-out procedure. HoLEP is the reference technique. The same principle is applied with thulium laser enucleation, thulium fiber laser enucleation, bipolar transurethral enucleation and hybrid platform variants. The AUA 2026 BPH guideline states that clinicians should offer laser enucleation (HoLEP or ThuLEP) as an option for LUTS/BPH and may offer alternative transurethral enucleation techniques .[71] The 2023 AUA amendment described HoLEP and ThuLEP as independent of prostate size, and EAU 2026 strongly recommends HoLEP as an alternative to TURP or open prostatectomy for moderate-to-severe LUTS/BPO. EAU weakly recommends Tm:YAG (ThuLEP, ThuVEP) and bipolar enucleation as alternatives to TURP, and strongly recommends open prostatectomy for glands above 80 mL only when endoscopic enucleation is not available.[1][2][72]
Where Enucleation Fits
| Scenario | Why enucleation fits | Main caution |
|---|---|---|
| Large prostate (>80 mL)[72] | Removes the adenoma endoscopically with open-prostatectomy-level debulking and shorter hospitalization | Learning curve and morcellation logistics |
| Any-size gland with retention | Strong outlet relief and catheter-free outcomes, including very large glands | Chronic retention still needs detrusor-function counseling |
| Anticoagulated / high bleeding risk | Laser enucleation is more hemostatic than classic monopolar TURP and avoids glycine TUR syndrome | Antithrombotic continuation can still increase catheter time, hematuria, and readmission |
| Adenoma histology | Retrieves transition-zone tissue for pathology, unlike vaporization or many MISTs | Sakai et al. advocate risk-adapted imaging and selective biopsy before BPO surgery to identify clinically significant cancer.[37] Incidental prostate cancer needs PSA-density and grade-group-based follow-up. |
| Maximal durability priority | Lower retreatment than many MISTs and durable IPSS / Qmax / PVR gains | Retrograde ejaculation is common with standard techniques |
| Ejaculation-preservation priority | Modified two-lobe, mucosal-sparing, and bladder-neck-sparing variants may help preserve antegrade ejaculation in selected men; a systematic review found limited benefit from hood sparing alone and higher rates with broader preservation of peri-verumontanum tissue, anterior urethral mucosa, and bladder-neck fibers.[79] | — |
Enucleation is a weaker choice when the patient mainly wants office therapy, rapid recovery with minimal catheter time, or ejaculation preservation over durability. In those cases, compare it with Prostatic Urethral Lift, water vapor therapy, iTIND, Aquablation, or Optilume BPH from the BPH & Male LUTS database.
Equipment and Physics
| Item | Standard HoLEP setup | Notes |
|---|---|---|
| Energy source | Ho:YAG laser, 2,140 nm | Water-absorbed; optical penetration is about 0.4 mm, while EAU 2026 describes coagulation and necrosis limited to 3–4 mm; pulsed cutting with hemostasis.[3][4][72] |
| Power range | 20-120 W | Functional outcomes appear similar across low-, medium-, and high-power systems[5][6] |
| Fiber | 550 um or 1000 um | Larger fibers may feel faster / more stable; smaller fibers may improve visibility and deflection depending on bridge and scope |
| Scope | 26-28 Fr continuous-flow resectoscope with laser bridge | Miniaturized 22 Fr MiLEP aims to reduce urethral trauma[7] |
| Tissue retrieval | Mechanical morcellator through nephroscope | The morcellation phase carries the distinctive bladder-injury risk[8][9] |
| Irrigation | Saline | Avoids classic glycine-absorption TUR syndrome |
Representative laser settings
| Phase | Common low / medium setting | Common high-power setting | Practical note |
|---|---|---|---|
| Main enucleation | 1.5-2 J x 20-25 Hz (30-50 W) | 2 J x 40-50 Hz (80-100 W) | Low power can be fully effective; high power may speed large-gland dissection |
| Apical dissection | 1-2 J x 20-30 Hz | Reduced energy / long pulse near sphincter | Prioritize visibility and mucosal preservation over speed |
| Hemostasis | 1 J x 30 Hz or defocused coagulation | Defocused, reduced-energy pulses | Coagulate perforators on the capsular bed rather than painting the whole capsule |
A survey of 22 ESUT/T.R.U.S.T. experts found a preference for long-pulse or pulse-modified Ho:YAG modes during main-gland enucleation, and reported lower median Ho:YAG power at the apex than in the main gland (75 versus 94 W).[10]
Pulse modulation and platform variants
| Platform / mode | Proposed advantage | Evidence signal |
|---|---|---|
| MOSES HoLEP | Vapor-channel pulse sequence; less energy loss in irrigation | RCT and comparative data show shorter hemostasis / operative time in some series, with similar functional outcomes[11][12] |
| Quanta Virtual Basket / Magneto | Pulse modulation for cutting plus coagulation mode | In a nonrandomized 100-versus-100 comparison, HoLEP using these modes had shorter morcellation time (14.6 versus 21.2 minutes), less postoperative gross hematuria, and less clot-induced urinary retention (0% versus 5%) than ThuLEP. The comparison changed both energy source and pulse mode.[13] |
| Thulium laser / thulium fiber enucleation | Continuous or highly adjustable water-absorbed cutting | Same anatomic operation with different energy delivery; outcomes depend heavily on surgeon experience |
| Bipolar enucleation | Uses familiar bipolar TUR equipment and saline | — |
Operative Sequence
The operation has two major phases: enucleation and morcellation.
Core landmarks
- Verumontanum: the distal safety landmark; apical work should stay proximal and respectful of sphincteric mucosa.
- Surgical capsule: white, fibrous, glistening, sometimes cobblestone-textured plane between adenoma and compressed peripheral / central zone.[14]
- Perforating vessels: perpendicular vessels from capsule into adenoma confirm correct depth but require selective hemostasis.
- Anterior apex: the most treacherous area because the plane is less distinct and close to the external sphincter.
- Bladder neck: defines proximal release and median-lobe orientation; bladder-neck preservation trades off against deobstruction in selected ejaculation-sparing strategies.
Classic three-lobe HoLEP
The original Gilling-style operation separates the median and lateral lobes before morcellation:[3][15]
- Create bladder-neck incisions at 5 and 7 o'clock down to capsule.
- Enucleate the median lobe retrograde from apex toward bladder.
- Develop each lateral-lobe plane along the capsule.
- Release the lobes into the bladder.
- Obtain capsular hemostasis.
- Morcellate the free adenoma under direct vision.
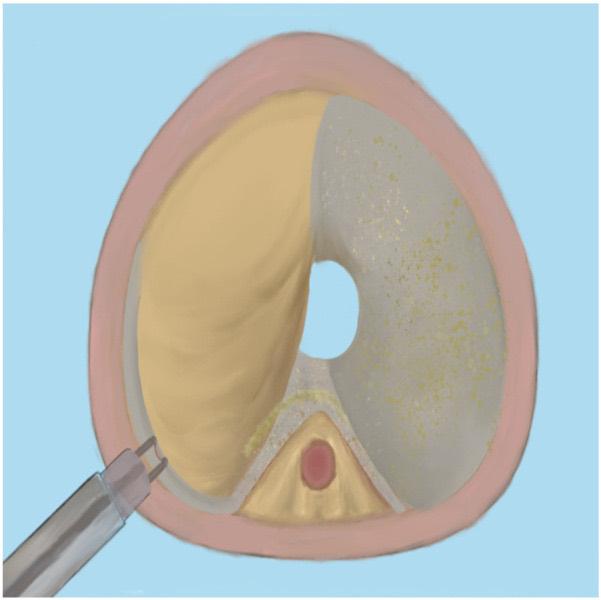
Three-lobe enucleation, schematic endoscopic view: after the median lobe has been enucleated and pushed into the bladder, the right lateral lobe is enucleated along the surgical capsule. From Yi X, et al. Front Surg. 2025;12:1668140, Figure 3 (CC BY 4.0).[73]
En-bloc and early-apical-release approaches
En-bloc HoLEP identifies the capsule once and removes the adenoma as a single horseshoe-shaped unit. Early apical release detaches adenoma from sphincteric mucosa at the beginning rather than at the end of the case. These modifications aim to improve efficiency and continence recovery by avoiding repeated apical re-entry and late traction on sphincteric tissue.[16][17][18]
| Technique | Intended advantage | Caveat |
|---|---|---|
| Three-lobe | Standardized anatomy, widely taught, reliable for varied gland shapes | More incisions and more repeated plane-finding |
| Two-lobe | Faster than three-lobe in some series; may reduce ejaculatory dysfunction when modified | Evidence is smaller and technique-specific |
| En-bloc | In a 123-man RCT of glands >80 mL, en-bloc reduced laser energy and operative time, without a significant difference in complications or three-month SUI; a separate matched retrospective study reported fewer grade ≥II adverse events.[17][82] | Requires comfort with circumferential plane development |
| En-bloc with early apical release | Protects apical mucosa and sphincter by releasing the apex early | Multicenter data are mixed; hematuria / transfusion can increase if hemostasis lags |
| Top-down | Bladder-neck-to-apex dissection may simplify apical orientation for learners | Less universal than three-lobe / en-bloc |
| Urethral mucosal preservation | Improves early continence and may preserve ejaculation in selected patients | Must not leave obstructing adenoma behind |
The ESUT Delphi consensus emphasized early sphincter detachment, apical mucosal preservation between 11 and 1 o'clock, gentle apical disruption, and avoidance of excess energy near the apical mucosa.[18] In a trial randomizing 89 men to veil-sparing and 91 to standard HoLEP, positive one-hour pad tests at one month were reported in 10 and 21 men, respectively (P = .047); the between-group difference was not significant at 12 months.[83]
Morcellation Safety
Morcellation is where a technically successful enucleation can still become dangerous.[8][9]
| Rule | Rationale |
|---|---|
| Keep the bladder distended | Creates distance between morcellator and bladder wall |
| Keep the blade in the center of the bladder | Avoids dome, lateral-wall, and trigonal injury |
| Never activate without tissue in view | Prevents blind suction of bladder mucosa |
| Keep tissue between lens and blade | Maintains a visual backstop |
| Pause for bleeding or poor visibility | Blind morcellation is the mechanism of major injury |
| Consider transabdominal ultrasound guidance when difficult | May help localize blade and tissue in very large glands, poor visibility, or residual chips; a proof-of-concept video describes ultrasound as an adjunct to direct cystoscopic visualization.[9] |
Superficial mucosal injuries can often be catheter-managed; true perforation requires immediate recognition, bladder drainage strategy, and selective operative repair depending on location and depth.
Outcomes
Single-center long-term series report IPSS reductions, Qmax increases, PVR reductions and PSA reductions across small to very large glands, consistent with transition-zone debulking.[19][20][21] EAU 2026 advises a review four to six weeks after catheter removal for symptom response and adverse events, using IPSS/ICIQ-MLUTS, uroflowmetry, PVR, and erectile/ejaculatory assessment; the follow-up recommendation is weak and based on level-4 evidence.[72]
| Outcome domain | Typical direction after HoLEP | Practical interpretation |
|---|---|---|
| IPSS / QoL | Large sustained decrease | Symptom relief is durable beyond the early recovery phase |
| Qmax | Large increase | Objective deobstruction is the main advantage over many MISTs |
| PVR / retention | Large decrease; high catheter-free rates | Counsel chronic retention patients that detrusor underactivity may persist |
| PSA | Fell 66.7% at most recent follow-up in one 1,476-patient HoLEP cohort (median follow-up 9.1 yr)[19] | New PSA baseline should be established after healing |
| Medication use | Usually decreases substantially | Persistent storage symptoms may still need OAB therapy |
| Retreatment | Low, often lower than TURP in database studies | Durability is a major reason to choose enucleation |
Compared with TURP
September 2026 Cochrane review: 52 randomized trials included 6,242 men across surgical comparisons; searches ran through April 8, 2026. For HoLEP versus TURP at ≤ 12 months, symptom and quality-of-life differences were small: IPSS mean difference −0.67 points (95% CI −1.20 to −0.14; 14 trials, 1,666 men), with low-certainty evidence. Major adverse events may be similar. Transfusion was less frequent with HoLEP (RR 0.19, 95% CI 0.09–0.42; 15 trials, 1,755 men; moderate certainty). Retreatment probably differed little (RR 0.45, 95% CI 0.14–1.50; eight trials, 813 men; moderate certainty), and erectile function was similar (three trials, 518 men).[70]
The review found no eligible ejaculatory-function data and insufficient evidence for the very-large-prostate or anticoagulation subgroups. Earlier trials and reviews describe shorter catheterization / hospitalization; operative time, the learning curve, and morcellation remain practical considerations.[22][23][24][70]
Compared with open or robotic simple prostatectomy
For large glands, comparative studies report simple-prostatectomy-level debulking with HoLEP and less blood loss, shorter hospitalization and shorter catheter duration than open surgery. The AUA 2026 guideline states that clinicians should offer simple prostatectomy (open, laparoscopic or robotic) for prostates larger than 80 cc .[71] Robotic simple prostatectomy is an option when the surgeon can preserve antegrade ejaculation in selected patients, when concomitant bladder pathology requires open / robotic access, or when enucleation expertise is not available.[25][26][27]
Energy-source variants — ThuLEP, ThuFLEP, and bipolar enucleation
The EAU ESUT, AUA and contemporary AEEP literature describe enucleation as a technique that does not depend on the energy source; the proposed determinant of outcome is completeness of adenoma removal along the surgical capsule.[42][43] ThuLEP, ThuFLEP and BipolEP apply the same anatomical operation with different energy platforms.
Thulium laser enucleation (ThuLEP)
Thulium lasers operate at 1940–2013 nm near the water-absorption peak. Thulium optical penetration is approximately 0.2 mm versus approximately 0.4 mm for holmium; thulium energy is used for smooth, precise incisions with rapid vaporization and hemostasis. In an ex vivo human-prostate study, coagulation-necrosis depth did not differ significantly between holmium and thulium fiber lasers at the tested settings.[44][45][80]
| Platform | Wavelength | Mode | Power | Notes |
|---|---|---|---|---|
| Tm:YAG continuous-wave | 2013 nm | CW | 100–200 W | Original thulium platform; smooth cutting, excellent hemostasis[45] |
| Thulium fiber laser (TFL / ThuFLEP) | 1940 nm | CW or pulsed | 50–200 W | Compact, portable, lower cost; even shallower penetration[46] |
| Pulsed solid-state Tm:YAG | 2013 nm | Pulsed (high peak power) | 100 W | Newest platform; shorter OR time and less postoperative pain than HoLEP in a multivariable analysis of a non-randomized comparison[47] |
In an ESUT / T.R.U.S.T.-Group expert survey, 73% of experts used Ho:YAG, 50% TFL, 23% continuous-wave Tm:YAG and 14% pulsed Tm:YAG for enucleation.[10]
ThuLEP vs HoLEP — the head-to-head data
| Trial / cohort | n | Key finding |
|---|---|---|
| Bozzini 2021 RCT (multicenter)[48] | 236 | No difference in IPSS, QoL, Qmax, PVR or PSA at 3 and 12 mo. Hemoglobin decrease was 0.45 vs 2.77 g/dL (p = 0.005) with ThuLEP versus HoLEP. HoLEP had more postoperative urinary retention and stress incontinence. |
| Shoma 2023 single-center 3-arm RCT (≥ 80 mL)[42] | 155 randomized; 138 analyzed at 6 mo and 120 at 12 mo | Qmax, IPSS, QoL and PVR did not differ significantly across HoLEP, ThuLEP and B-TUEP at 6 or 12 mo. In the subgroup with prostates > 120 mL, 1-year IPSS improvement favored HoLEP and ThuLEP (p = 0.01). |
| ThuFLEP vs HoLEP (Kosiba 2024 RCT; Filzmayer 2026 follow-up)[76][81] | 150 randomized (74 vs 76); 90 IPSS and 92 QoL respondents at 24 mo | ThuFLEP met the IPSS and QoL noninferiority endpoints at 3 and 24 mo; major complications did not differ significantly at 3 mo. The 24-mo extension used patient-reported outcomes without repeat Qmax, PVR, or PSA. The secondary analyses were exploratory. |
| ThuFLEP single-arm cohort (Petov 2022)[49] | 1,328 | Through 3 yr, IPSS fell from 20.3 to 5.4 and Qmax rose from 7.8 to 21.8 mL/s; SUI 1.2%, stricture 1.1%, BNC 0.9%. |
| Network meta-analysis (Huang 2019 BMJ)[50] | 109 RCTs / 13,676 patients | Enucleation methods gave better Qmax and IPSS than resection and vaporization methods. Top three for Qmax at 12 mo vs monopolar TURP: bipolar enucleation +2.42 mL/s (95% CI 1.11–3.73), diode laser enucleation +1.86 mL/s (CI −0.17 to 3.88) and holmium laser enucleation +1.07 mL/s (CI 0.07–2.08). Short-term transient incontinence was more frequent with enucleation than resection (OR 1.92). |
| EEP vs TURP meta (Vo 2025)[51] | 28 RCTs / 3,085 patients | EEP was associated with better IPSS (at 12 mo), Qmax and PVR, shorter catheterization and stay, and lower rates of transfusion (RR 0.22), stricture (RR 0.55) and reoperation for recurrent BPH (RR 0.32). Heterogeneity was high for several outcomes. |
Ejaculation-sparing ThuLEP (ES-ThuLEP)
In the Guldibi systematic review (mostly holmium studies), the reported retrograde ejaculation rate was 71.3 ± 16.1% with standard laser enucleation techniques.[52] ES-ThuLEP preserves the paracollicular and supracollicular tissue proximal to the verumontanum:
- Bozzini 2021 large cohort (n = 283): ejaculation preserved in 71.7% at 3 mo / 77.4% at 6 mo with no compromise in IPSS or erectile function.[53]
- Trama 2022 prospective (n = 53): 48, 51, and 52 men reported preserved ejaculation at 3, 6, and 12 mo, respectively.[54]
- Perri 2025 ES-ThuLEP using Tm:YAG versus TFL: 81% antegrade preservation in both groups, with significantly higher rates in prostates ≥ 80 mL.[55]
- Guldibi 2023 SR of laser AEEP (15 studies, 1,877 men, only three on thulium fiber): the retrograde-ejaculation rate was 62.1% overall, 71.3% with standard techniques and 27.2% with ejaculation-preserving modifications (p < 0.001).[52]
- A prospective series of 110 men found no significant change in erectile function 3-6 months after ThuLEP.[56] In the Shoji RCT of ThuLEP versus bipolar TURP, described in the AUA 2026 guideline, ED was reported by 17% (7/41) versus 44% (16/36) at 1 yr (RR 0.38).[71]
ThuLEP learning curve
- A single-surgeon study of 60 consecutive patients reported significant improvement in morcellation and enucleation efficiency after about 20 cases.[57]
- A single-surgeon analysis reported a learning curve of about 60 cases with a well-trained mentor present.[58]
- ThuFLEP for laser-EEP-naïve surgeon with limited mentoring: approximately 60 cases, complications low throughout training.[59]
- The Enikeev 2018 RCT (90 patients, three surgeons experienced in TURP) compared HoLEP, ThuFLEP and monopolar enucleation learning curves with structured mentoring. The authors concluded that EEP can be adopted within 30 surgeries and that laser EEP adapts faster than monopolar enucleation.[60]
Bipolar enucleation (BipolEP / B-TUEP / B-TUERP)
Bipolar enucleation uses bipolar electrocautery in saline delivered through a standard resectoscope loop or button electrode, applied to the same anatomical operation. The advantage is that it uses existing bipolar TURP equipment already in most ORs, eliminating the laser-generator capital cost.[61][62] Bipolar resection in saline avoids the TUR-syndrome risk of monopolar resection.
Multiple electrode and generator systems are available: Olympus TURis bipolar loop, Gyrus PK plasma button (large surface for simultaneous vaporization and coagulation), Karl Storz bipolar resectoscope. Power settings depend on the generator and electrode; the cited Gyrus PK button-enucleation technique used 160 W for cutting and 100 W for coagulation in saline.[62]
B-TUEP vs B-TURP — RCTs and meta-analyses
| Trial / cohort | n | Key finding |
|---|---|---|
| Samir 2019 RCT (≥ 80 g)[63] | 240 | B-TUERP (enucleation and resection) versus B-TURP: longer OR time (105 vs 61 min), more resected tissue, less hemoglobin drop (1.5 vs 2 g/dL), and shorter catheter, irrigation and hospital stay. At 24 mo B-TUERP had better IPSS (6 vs 7, p = 0.008), Qmax (24.9 vs 20.1 mL/s, p = 0.034) and PVR (18.6 vs 24.7 mL, p = 0.001). |
| Arcaniolo 2020 ESUT cumulative[64] | meta | b-EEP higher resected tissue, Qmax improvement, lower transfusion than B-TURP. |
| Magistro 2021 matched-pair[24] | TURP / HoLEP / B-TUEP | HoLEP and B-TUEP retrieved more tissue than TURP (71.4% / 70% vs 50%, p < 0.05). |
| Bebi 2021 size-stratified[65] | mixed | No difference in functional outcomes, complications or sexual symptoms by prostate volume; enucleation efficacy was higher in glands > 110 mL. Comorbidity and antiplatelet/anticoagulant use were independently associated with postoperative complications. |
B-TUEP long-term durability
- Filomena 2023 single-center B-TUEP cohort (50 enrolled): Twelve men were excluded during 10-year follow-up. Among those assessed, IPSS improvement persisted, Qmax remained 12 mL/s above baseline at 10 years, erectile function improved early and remained improved through 5 years, and none underwent reoperation for persistent BOO.[66]
- Lombardo 2021 B-TUEP versus LSP, > 80 g, 3-yr (n = 296): both arms showed sustained functional improvement (250 completed 3 yr). The abstract reports 8% LSP reintervention, while the detailed 3-year results report 4% LSP (7 cases); both give 5% B-TUEP, with six cases in the detailed results. Transfusion occurred in 9% of each arm; grade III reinterventions occurred, with no grade IV/V complications.[67]
- Frendl 2021 claims-based real-world (n = 15,982, 7-yr): cumulative failure (reoperation or retention after 30 days) was 15.3% for TURP, 13.9% for PVP and 6.7% for endoscopic enucleation, which made up only 1.5% of the cohort. Enucleation showed a nonsignificant trend toward lower failure versus TURP (HR 0.67, 95% CI 0.36–1.22).[68]
B-TUEP technique — mushroom vs morcellation
A 234-pt B-TUEP comparison found morcellation had shorter OR time (60 versus 80 min, p < 0.001) versus the mushroom technique (resecting enucleated tissue into smaller pieces for evacuation through the resectoscope sheath).[69]
Head-to-head — when to choose which energy source
| Parameter | ThuLEP | BipolEP (B-TUEP) |
|---|---|---|
| Energy source | Thulium laser (1940–2013 nm) | Bipolar electrocautery in saline |
| Equipment cost | High (laser generator + fibers) | Low (standard bipolar resectoscope) |
| Prostate size | Laser EEP is size-independent in AUA guidance[71]; ES-ThuLEP cohort mean 88.8 ± 32.2 mL[54] | B-TUEP studied in 30–80 cc and >80 cc cohorts[66][67]; in one RCT subgroup with prostates >120 mL, 1-year IPSS improvement favored HoLEP and ThuLEP over B-TUEP[42] |
| IPSS reduction | ~ 15 points | ~ 15 points |
| Qmax improvement | ES-ThuLEP: +12.3 mL/s at 12 mo (7.7 to 20.0 mL/s)[54] | B-TUEP: +16 mL/s at 5 yr and +12 mL/s at 10 yr[66] |
| Blood loss (Hb drop) | 0.45 g/dL (Bozzini 2021, versus 2.77 g/dL with HoLEP) | 1.5 g/dL (Samir 2019, versus 2 g/dL with B-TURP) |
| Reported reinterventions (different indications) | ThuLEP: surgery on the prostate for worsening BPH-related urinary outcomes in 10/379 (2.6%) at 5 years and 21/353 (5.9%) at 10 years in one cohort; urethral and bladder-neck reconstruction were excluded from this endpoint.[78] | B-TUEP: 5% underwent surgery for bladder-neck contracture or urethral stricture within 3 years in one cohort[67]; no reoperation for persistent BOO was reported among men assessed at 10 years in another cohort.[66] |
| Ejaculation preservation (standard) | In one ThuLEP series, 58/74 men (78.4%) eligible for assessment of preserved ejaculation reported consistent ejaculation at 3–6 months; 58/110 (52.7%) was the rate among all enrolled men.[56] | Not quantified in the cited B-TUEP cohorts |
| Ejaculation preservation (modified) | 81.0% antegrade ejaculation at 6 mo in one ES-ThuLEP cohort[55]; Trama reported 52 men with preserved ejaculation at 12 mo but labeled this 94.3% despite 52/53 being 98.1%[54] | Limited data |
| Learning curve | 20–60 cases | Steep but leverages TURP skills |
| Tissue for histology | Yes (morcellation) | Yes (morcellation or mushroom) |
In the Shoma three-arm RCT of prostates ≥80 mL, IPSS, Qmax, QoL and PVR did not differ significantly across HoLEP, ThuLEP and B-TUEP at 12 months (120 analyzed).[42] In a separate RCT of prostates ≥80 g, ThuLEP had shorter operative time than bipolar plasma enucleation (90.5 versus 117.22 minutes), while IPSS, Qmax, PVR and IIEF-5 did not differ significantly among 108 men completing 12 months.[84] The Vo meta-analysis compared endoscopic enucleation with TURP; it notes that platform choice reflects institutional resources and surgeon preference, while costs were not analyzed.[51]
Anticoagulation and High-Risk Patients
For patients at high risk of bleeding or on anticoagulant or antiplatelet therapy, the AUA 2026 guideline states that clinicians may offer HoLEP, ThuLEP, PVP or PAE .[71] Laser energy provides cutting and hemostasis in saline irrigation, but antithrombotic therapy still adds logistical burden.[28][29][30] EAU 2026 weakly recommends Tm:YAG laser enucleation for men on anticoagulant or antiplatelet therapy and notes that the evidence for laser enucleation in these men lacks RCTs, comes from prostates under 110 mL and does not separate antiplatelet from anticoagulant therapy.[72]
| Finding | Counseling point |
|---|---|
| AP / AC patients can undergo HoLEP effectively | Functional outcomes are generally preserved |
| Warfarin often behaves worse than DOACs | Expect more bleeding-related logistics in some series |
| Antithrombotics can prolong catheterization | Same-day catheter-free pathways may not apply |
| Continued AP / AC was associated with higher bleeding odds in pooled observational enucleation cohorts | A 2026 review found higher odds of bleeding-related complications (OR 2.91, 95% CI 1.71–4.93) and surgical hemostasis (OR 3.69, 95% CI 1.73–7.84) with ongoing therapy; discuss clot retention, irrigation and delayed bleeding.[75] |
| Major complications are not consistently increased | — |
Anticoagulation decisions should still follow institutional perioperative-anticoagulation pathways, thrombotic risk, and anesthesia planning. See Antithrombotic Therapy and Anticoagulation Reversal for the medication framework.
No AUA- or EAU-stated VTE-prophylaxis recommendation exists specifically for HoLEP/AEEP; apply the general urologic-surgery risk framework (age, obesity, prior VTE, malignancy, prolonged operative time or immobility) on the VTE Prophylaxis page.
Complications
| Complication | Typical range / pattern | Prevention / management |
|---|---|---|
| Transient stress incontinence | Common early; falls sharply by 3-12 months | Apical mucosal preservation, early apical release, pelvic-floor therapy, patience |
| Persistent urinary incontinence / surgery for SUI | The AUA 2026 guideline gives 0.9–3% for persistent urinary incontinence after laser enucleation overall.[71] In a retrospective HoLEP claims cohort, incontinence was coded in 551/11,559 men (4.8%) at 1–2 years, while 13/11,559 (0.1%) received an AUS or sling within 2 years; baseline incontinence was coded in 20.7%.[74] | Assess the incontinence phenotype and stability before considering sling or AUS |
| Urgency / urge incontinence | Often improves, but may persist with detrusor overactivity | Rule out UTI, BNC, stricture, residual obstruction; treat OAB phenotype |
| Bleeding / clot retention | Lower than TURP | Capsular perforator hemostasis, catheter traction / irrigation when needed |
| Bladder neck contracture | 30 cases among 1,476 patients in one HoLEP series (median follow-up 9.1 yr)[19] | Avoid excessive bladder-neck thermal injury; treat with incision / resection if it occurs |
| Urethral stricture | Around 1-3% in series; EAU 2026 cites 2.6% after HoLEP versus 4.4% after monopolar TURP, and stress incontinence of 1.5% in both, in meta-analyses[72] | Minimize instrumentation trauma; consider smaller-scope approaches in selected patients |
| Capsular perforation | Usually catheter-managed if extraperitoneal / limited | Stay in plane; recognize fat, venous sinus, or sudden loss of resistance |
| Morcellation injury | Rare but distinctive | Stop when visibility is poor; maintain bladder distension; ultrasound when difficult |
Transient SUI risk factors
Risk factors reported across series include older age, higher BMI, diabetes, larger adenoma weight, pre-existing incontinence, shorter membranous urethral length, high detrusor voiding pressure, and early surgeon learning curve.[31][32][33]
Sexual Function
Erectile function is usually preserved after HoLEP, although men with strong baseline erections may notice small declines and very large glands may carry higher risk in some cohorts. Ejaculatory function is the predictable trade-off: standard HoLEP commonly causes retrograde ejaculation or markedly reduced ejaculatory volume. The AUA 2026 guideline gives an incidence of 50-75% after laser enucleation, similar to TURP.[34][35][71] EAU 2026 cites meta-analyses that found no difference in mid-term retrograde ejaculation between HoLEP and TURP, modified-template HoLEP preserving ejaculation in up to 77.8% of men, and a retrospective median-lobe-only enucleation series in which antegrade ejaculation was preserved in 28/32 (88%) men who had antegrade ejaculation before surgery, while 8/55 (14.5%) of the full cohort required surgical reintervention for persistent LUTS/BPO by 1 year.[72][77]
| Goal | Enucleation counseling |
|---|---|
| Preserve erections | Reasonable expectation, but assess baseline SHIM and vascular risk |
| Preserve antegrade ejaculation | Standard HoLEP is poor for this goal; consider modified techniques or non-enucleative alternatives |
| Maximize durability | HoLEP / enucleation is often the stronger choice than ejaculation-preserving MISTs |
| Avoid bothersome dry orgasm | Discuss before surgery; many patients are not bothered, but some strongly are |
Incidental Prostate Cancer
Enucleation retrieves a transition-zone specimen, so incidental prostate cancer is not rare. Reported rates vary widely with preoperative PSA / MRI / biopsy intensity, but many detected cancers are Grade Group 1 and suitable for active surveillance.[36][37]
Practical pathway:
- Establish a new PSA nadir after healing.
- Interpret PSA density against residual peripheral-zone volume when imaging is available.
- Use grade group, percent involvement, MRI findings, and life expectancy to choose surveillance versus definitive therapy.
- Radical prostatectomy after HoLEP is feasible, but bladder-neck reconstruction and operative complexity may increase.[38]
Learning Curve
The learning curve is a main barrier to HoLEP adoption, and the AUA 2026 guideline states that the decision to perform it must rest on the clinician's expertise and equipment availability.[71] Basic efficiency may improve after 25-50 cases, but continence, complication control, morcellation comfort, and large-gland speed continue to improve beyond that.[39][40]
Training structure:
- Start with mentored cases and standardized three-lobe or en-bloc-with-apical-release anatomy.
- Avoid first cases with extreme gland size, severe bleeding risk, bladder stones, or distorted post-radiation anatomy.
- Separate metrics: enucleation efficiency, morcellation efficiency, conversion, capsular perforation, SUI at 1 / 3 / 12 months, and readmission.
- Review unedited video, especially apical release and anterior commissure joining.
- Build a plan for morcellation rescue before the first case: spare resectoscope loop, Ellik evacuation, open conversion threshold, and ultrasound availability.
The hardest steps for learners are usually apical dissection and joining anterior / posterior planes.[40][41]
Operative Pearls
- Enucleation is a plane operation.
- The apex decides continence. Slow down near the sphincter, preserve mucosa, and avoid thermal painting.
- Perforators confirm the plane. Coagulate selectively rather than stripping the capsule into a charred surface.
- Morcellation needs its own pause point. Reassess visibility, bladder distension, and chip size before activating the blade.
- A large PVR does not by itself predict failure. Chronic retention may still do well, but detrusor underactivity changes counseling.
- Reset the PSA baseline. A post-HoLEP PSA that fails to fall or rises later deserves evaluation.
- Standard HoLEP is not ejaculation-sparing. Modified techniques may improve rates, but counseling should assume dry or reduced ejaculation.
Podcasts
Videos
References
1. Sandhu JS, Bixler BR, Dahm P, et al. Management of lower urinary tract symptoms attributed to benign prostatic hyperplasia (BPH): AUA guideline amendment 2023. J Urol. 2024;211(1):11-19. doi:10.1097/JU.0000000000003698
2. European Association of Urology. EAU Guidelines on the Management of Non-neurogenic Male Lower Urinary Tract Symptoms. 2026 update. EAU
3. Tan AH, Gilling PJ. Holmium laser prostatectomy: current techniques. Urology. 2002;60(1):152-156. doi:10.1016/S0090-4295(02)01648-5
4. Xu H, Wan X, Gu M, et al. Surgical treatment for benign prostatic hyperplasia: holmium laser enucleation of the prostate (HoLEP). J Vis Exp. 2018;(133):56683. doi:10.3791/56683
5. Chen L, Chen C, Li C, et al. Low-power versus high-power laser for holmium laser enucleation of prostate: systematic review and meta-analysis. World J Urol. 2025;43(1):228. doi:10.1007/s00345-025-05621-5
6. Elshal AM, El-Nahas AR, Ghazy M, et al. Low-power vs high-power holmium laser enucleation of the prostate: critical assessment through randomized trial. Urology. 2018;121:58-65. doi:10.1016/j.urology.2018.07.010
7. Alves BB, Gabrich P, Favorito LA. Prospective results of the minimally invasive laser enucleation of the prostate (MiLEP). Prostate. 2024;84(16):1501-1505. doi:10.1002/pros.24790
8. Rijo E, Misrai V, Aho T, Gomez-Sancha F. Recommendations for safe and efficient morcellation after endoscopic enucleation of the prostate. Urology. 2018;121:197. doi:10.1016/j.urology.2018.06.027
9. Tzou DT, Metzler IS, Tsai C, et al. Ultrasound-guided morcellation during difficult holmium laser enucleation of the prostate. Urology. 2020;135:171-172. doi:10.1016/j.urology.2019.09.027
10. Ortner G, Guven S, Somani BK, et al. Experts' recommendations in laser use for the endoscopic treatment of prostate hypertrophy: a comprehensive guide by ESUT and T.R.U.S.T. World J Urol. 2023;41(11):3277-3285. doi:10.1007/s00345-023-04565-y
11. Kavoussi NL, Nimmagadda N, Robles J, et al. MOSES technology for holmium laser enucleation of the prostate: a prospective double-blind randomized controlled trial. J Urol. 2021;206(1):104-108. doi:10.1097/JU.0000000000001693
12. Nottingham CU, Large T, Agarwal DK, Rivera ME, Krambeck AE. Comparison of newly optimized Moses technology standard holmium:YAG for endoscopic laser enucleation of the prostate. J Endourol. 2021;35(9):1393-1399. doi:10.1089/end.2020.0996
13. Perri D, Besana U, Mazzoleni F, et al. Holmium:YAG laser enucleation of the prostate using the new Cyber Ho generator with Magneto technology. World J Urol. 2025;43(1):161. doi:10.1007/s00345-025-05536-1
14. Oh SJ, Shitara T. Enucleation of the prostate: an anatomical perspective. Andrologia. 2020;52(8):e13744. doi:10.1111/and.13744
15. Fraundorfer MR, Gilling PJ. Holmium:YAG laser enucleation of the prostate combined with mechanical morcellation: preliminary results. Eur Urol. 1998;33(1):69-72. doi:10.1159/000019535
16. Scoffone CM, Cracco CM. The en-bloc no-touch holmium laser enucleation of the prostate (HoLEP) technique. World J Urol. 2016;34(8):1175-1181. doi:10.1007/s00345-015-1741-y
17. Tamalunas A, Schott M, Keller P, et al. Efficacy, efficiency, and safety of en-bloc vs three-lobe enucleation of the prostate. Urology. 2023;175:48-55. doi:10.1016/j.urology.2023.02.014
18. Tunc L, Herrmann T, Guven S, et al. A Delphi consensus to standardize the technique of anatomical endoscopic enucleation of prostate. World J Urol. 2023;41(9):2303-2309. doi:10.1007/s00345-023-04496-8
19. Ibrahim A, Alharbi M, Elhilali MM, Aube M, Carrier S. 18 years of holmium laser enucleation of the prostate: a single center experience. J Urol. 2019;202(4):795-800. doi:10.1097/JU.0000000000000280
20. Krambeck AE, Handa SE, Lingeman JE. Experience with more than 1,000 holmium laser prostate enucleations for benign prostatic hyperplasia. J Urol. 2013;189(1 Suppl):S141-S145. doi:10.1016/j.juro.2012.11.027
21. Elmansy HM, Kotb A, Elhilali MM. Holmium laser enucleation of the prostate: long-term durability of clinical outcomes and complication rates during 10 years of followup. J Urol. 2011;186(5):1972-1976. doi:10.1016/j.juro.2011.06.065
22. Chen F, Chen Y, Zou Y, et al. Comparison of holmium laser enucleation and transurethral resection of prostate in benign prostatic hyperplasia: a systematic review and meta-analysis. J Int Med Res. 2023;51(8):3000605231190763. doi:10.1177/03000605231190763
23. Li S, Zeng XT, Ruan XL, et al. Holmium laser enucleation versus transurethral resection in patients with benign prostate hyperplasia: updated systematic review and meta-analysis. PLoS One. 2014;9(7):e101615. doi:10.1371/journal.pone.0101615
24. Magistro G, Schott M, Keller P, et al. Enucleation vs resection: a matched-pair analysis of TURP, HoLEP and bipolar TUEP in medium-sized prostates. Urology. 2021;154:221-226. doi:10.1016/j.urology.2021.04.004
25. Lee MS, Assmus MA, Ganesh M, et al. Outcomes comparison between HoLEP, open simple prostatectomy, and robotic simple prostatectomy for large gland BPH. Urology. 2023;173:180-186. doi:10.1016/j.urology.2022.12.018
26. Benzouak T, Addar A, Prudencio-Brunello MA, et al. Comparative analysis of HoLEP and robotic-assisted simple prostatectomy in BPH management: systematic review and meta-analysis. J Urol. 2025;213(2):150-161. doi:10.1097/JU.0000000000004297
27. Grosso AA, Amparore D, Di Maida F, et al. Comparison of perioperative and short-term outcomes of en-bloc HoLEP and robot-assisted simple prostatectomy: propensity-score matching analysis. Prostate Cancer Prostatic Dis. 2024;27(3):478-484. doi:10.1038/s41391-023-00743-6
28. Agarwal DK, Large T, Stoughton CL, et al. Real-world experience of HoLEP with patients on anticoagulation therapy. J Endourol. 2021;35(7):1036-1041. doi:10.1089/end.2020.0886
29. Yuk HD, Oh SJ. Perioperative safety and efficacy of HoLEP in patients receiving antithrombotic therapy. Sci Rep. 2020;10(1):5308. doi:10.1038/s41598-020-61940-0
30. Romero-Otero J, Garcia-Gomez B, Garcia-Gonzalez L, et al. Critical analysis of a multicentric experience with HoLEP: outcomes and complications of 10 years of routine practice. BJU Int. 2020;126(1):177-182. doi:10.1111/bju.15028
31. Houssin V, Olivier J, Brenier M, et al. Predictive factors of urinary incontinence after HoLEP: a multicentric evaluation. World J Urol. 2021;39(1):143-148. doi:10.1007/s00345-020-03169-0
32. Cornwell LB, Smith GE, Paonessa JE. Predictors of postoperative urinary incontinence after HoLEP: 12 months follow-up. Urology. 2019;124:213-217. doi:10.1016/j.urology.2018.11.032
33. Lee N, Benzouak T, Nguyen DD, et al. Membranous urethral length as a predictor for urinary incontinence after holmium enucleation of the prostate. World J Urol. 2026;44(1):138. doi:10.1007/s00345-026-06232-4
34. Roper C, Slade A, Caras R, Shelton T, Rivera M. Ejaculatory and erectile function outcomes following HoLEP. Prostate. 2024;84(9):791-796. doi:10.1002/pros.24697
35. Deslandes M, Klein C, Marquette T, et al. Influence of HoLEP on erectile function: results of a multicentric analysis of 235 patients. World J Urol. 2022;40(11):2747-2754. doi:10.1007/s00345-022-04175-0
36. Han JH, Chung DH, Cho MC, et al. Natural history of incidentally diagnosed prostate cancer after HoLEP. PLoS One. 2023;18(2):e0278931. doi:10.1371/journal.pone.0278931
37. Sakai A, Borza T, Antar A, et al. Incidental prostate cancer diagnosis is common after HoLEP. Urology. 2024;183:170-175. doi:10.1016/j.urology.2023.11.014
38. Katsimperis S, Tzelves L, Markopoulos T, et al. Radical prostatectomy following HoLEP: systematic review of perioperative, oncological, and functional outcomes. Cancers (Basel). 2025;17(22):3685. doi:10.3390/cancers17223685
39. Kampantais S, Dimopoulos P, Tasleem A, et al. Assessing the learning curve of HoLEP: a systematic review. Urology. 2018;120:9-22. doi:10.1016/j.urology.2018.06.012
40. Elshal AM, Nabeeh H, Eldemerdash Y, et al. Prospective assessment of the learning curve of HoLEP using a multidimensional approach. J Urol. 2017;197(4):1099-1107. doi:10.1016/j.juro.2016.11.001
41. Chavali JSS, Rivera ME, Lingeman JE. HoLEP learning curve-resident perspective: survey of senior residents from a high-volume tertiary center. J Endourol. 2024;38(9):977-981. doi:10.1089/end.2024.0054
42. Shoma AM, Ghobrial FK, El-Tabey N, El-Hefnawy AS, El-Kappany HA. A randomized trial of holmium laser vs thulium laser vs bipolar enucleation of large prostate glands. BJU Int. 2023;132(6):686-695. doi:10.1111/bju.16174
43. Castellani D, Pirola GM, Pacchetti A, Saredi G, Dellabella M. State of the art of thulium laser enucleation and vapoenucleation of the prostate: a systematic review. Urology. 2020;136:19-34. doi:10.1016/j.urology.2019.10.022
44. Becker B, Netsch C, Bozzini G, et al. Reasons to go for thulium-based anatomical endoscopic enucleation of the prostate. World J Urol. 2021;39(7):2363-2374. doi:10.1007/s00345-021-03704-7
45. Netsch C, Gross AJ, Becker B. Thulium laser enucleation of the prostate. J Endourol. 2025;39(S1):S2-S7. doi:10.1089/end.2024.0617
46. Bozzini G, Berti L, Maltagliati M, et al. Thulium:YAG vs continuous-wave thulium fiber laser enucleation of the prostate: do potential advantages of thulium fiber lasers translate into relevant clinical differences? World J Urol. 2023;41(1):143-150. doi:10.1007/s00345-022-04201-1
47. von Bargen MF, Glienke M, Tonyali S, et al. Multivariable regression analysis of perioperative parameters for a novel pulsed solid-state thulium:YAG laser with high peak power versus holmium:YAG laser in prostate enucleation. World J Urol. 2025;43(1):459. doi:10.1007/s00345-025-05756-5
48. Bozzini G, Berti L, Aydoğan TB, et al. A prospective multicenter randomized comparison between holmium laser enucleation of the prostate (HoLEP) and thulium laser enucleation of the prostate (ThuLEP). World J Urol. 2021;39(7):2375-2382. doi:10.1007/s00345-020-03468-6
49. Petov V, Babaevskaya D, Taratkin M, et al. Thulium fiber laser enucleation of the prostate: prospective study of mid- and long-term outcomes in 1,328 patients. J Endourol. 2022;36(9):1231-1236. doi:10.1089/end.2022.0029
50. Huang SW, Tsai CY, Tseng CS, et al. Comparative efficacy and safety of new surgical treatments for benign prostatic hyperplasia: systematic review and network meta-analysis. BMJ. 2019;367:l5919. doi:10.1136/bmj.l5919
51. Vo LT, Armany D, Chalasani V, et al. Endoscopic enucleation of the prostate versus transurethral resection of the prostate for benign prostatic hyperplasia: a systematic review and meta-analysis. Prostate Cancer Prostatic Dis. 2025. doi:10.1038/s41391-025-00970-z
52. Guldibi F, Altunhan A, Aydın A, et al. What is the effect of laser anatomical endoscopic enucleation of the prostate on the ejaculatory functions? A systematic review. World J Urol. 2023;41(12):3493-3501. doi:10.1007/s00345-023-04660-0
53. Bozzini G, Berti L, Maltagliati M, et al. Ejaculation-sparing thulium laser enucleation of the prostate (ES-ThuLEP): outcomes on a large cohort. World J Urol. 2021;39(6):2029-2035. doi:10.1007/s00345-020-03442-2
54. Trama F, Lauro GD, Illiano E, et al. Ejaculation sparing thulium laser enucleation of the prostate: an observational prospective study. J Clin Med. 2022;11(21):6365. doi:10.3390/jcm11216365
55. Perri D, Besana U, Mazzoleni F, et al. Ejaculation-sparing enucleation of the prostate with thulium:YAG laser (ES-ThuLEP) versus thulium fiber laser (ES-ThuFLEP): outcomes on sexual function. World J Urol. 2025;43(1):92. doi:10.1007/s00345-025-05483-x
56. Carmignani L, Bozzini G, Macchi A, et al. Sexual outcome of patients undergoing thulium laser enucleation of the prostate for benign prostatic hyperplasia. Asian J Androl. 2015;17(5):802-806. doi:10.4103/1008-682X.139255
57. Aydogan TB, Binbay M. Learning curve of ThuLEP (thulium laser enucleation of the prostate): single-centre experience on initial consecutive 60 patients. Andrologia. 2022;54(4):e14366. doi:10.1111/and.14366
58. Perri D, Pacchetti A, Morini E, et al. Evaluation of the learning curve for thulium laser enucleation of the prostate in a contemporary cohort. World J Urol. 2024;42(1):246. doi:10.1007/s00345-024-04958-7
59. Al Barajraji M, Moussa I, Soscia GL, et al. Evaluation of the learning curve for thulium fiber laser enucleation of prostate (ThuFLEP): retrospective study of a single-surgeon experience in real-world settings. World J Urol. 2024;42(1):444. doi:10.1007/s00345-024-05167-y
60. Enikeev D, Glybochko P, Rapoport L, et al. A randomized trial comparing the learning curve of 3 endoscopic enucleation techniques (HoLEP, ThuFLEP, and MEP) for BPH using mentoring approach — initial results. Urology. 2018;121:51-57. doi:10.1016/j.urology.2018.06.045
61. Ryang SH, Ly TH, Tran AV, Oh SJ, Cho SY. Bipolar enucleation of the prostate — step by step. Andrologia. 2020;52(8):e13631. doi:10.1111/and.13631
62. Giulianelli R, Gentile B, Albanesi L, Tariciotti P, Mirabile G. Bipolar button transurethral enucleation of prostate in benign prostate hypertrophy treatment: a new surgical technique. Urology. 2015;86(2):407-413. doi:10.1016/j.urology.2015.03.045
63. Samir M, Tawfick A, Mahmoud MA, et al. Two-year follow-up in bipolar transurethral enucleation and resection of the prostate in comparison with bipolar transurethral resection of the prostate in treatment of large prostates. Randomized controlled trial. Urology. 2019;133:192-198. doi:10.1016/j.urology.2019.07.029
64. Arcaniolo D, Manfredi C, Veccia A, et al. Bipolar endoscopic enucleation versus bipolar transurethral resection of the prostate: an ESUT systematic review and cumulative analysis. World J Urol. 2020;38(5):1177-1186. doi:10.1007/s00345-019-02890-9
65. Bebi C, Turetti M, Lievore E, et al. Bipolar transurethral enucleation of the prostate: is it a size-independent endoscopic treatment option for symptomatic benign prostatic hyperplasia? PLoS One. 2021;16(6):e0253083. doi:10.1371/journal.pone.0253083
66. Filomena GB, Gentile BC, Albanesi L, et al. Long-term outcomes following bipolar transurethral plasma enucleation of the prostate: 10-year follow-up. J Endourol. 2023;37(7):811-816. doi:10.1089/end.2022.0685
67. Lombardo R, Zarraonandia Andraca A, Plaza Alonso C, et al. Laparoscopic simple prostatectomy vs bipolar plasma enucleation of the prostate in large benign prostatic hyperplasia: a two-center 3-year comparison. World J Urol. 2021;39(7):2613-2619. doi:10.1007/s00345-020-03512-5
68. Frendl DM, Chen YW, Chang DC, Kim MM. A claims-based assessment of reoperation and acute urinary retention after ambulatory transurethral surgery for benign prostatic hyperplasia. J Urol. 2021;205(2):532-538. doi:10.1097/JU.0000000000001390
69. Kiss Z, Murányi M, Nagy A, Flaskó T. Effectiveness of the mushroom technique versus morcellation in en bloc bipolar prostate enucleation for prostates over 80 mL. PLoS One. 2025;20(9):e0331142. doi:10.1371/journal.pone.0331142
70. Sathianathen N, Hwang EC, Brown SJ, et al. Holmium laser enucleation of the prostate for the treatment of lower urinary tract symptoms in men with benign prostatic hyperplasia. Cochrane Database Syst Rev. 2026;9:CD013291. Published September 9, 2026. doi:10.1002/14651858.CD013291.pub2. Cochrane summary.
71. Goueli R, Badlani GH, Welliver C, et al. Management of lower urinary tract symptoms attributed to benign prostatic hyperplasia: AUA guideline (2026). Statements 41, 42, 43 and 60. American Urological Association; 2026.
72. European Association of Urology. EAU Guidelines on the Management of Non-neurogenic Male LUTS. 2026 (March update). Official full guideline. See sections 5.3.2.a to 5.3.2.d.
73. Yi X, Zhu G, Zhu B, Zou J, Zhu J, Zou X, et al. Three surgical techniques using different energy sources for anatomical endoscopic enucleation of the prostate. Front Surg. 2025;12:1668140. doi:10.3389/fsurg.2025.1668140
74. Michel C, Nimmagadda N. "Persistent incontinence rates and incontinence surgeries are low after holmium laser enucleation of the prostate: a retrospective analysis of a large national claims database." J Endourol. 2025;39(12):1292-1297. doi:10.1177/08927790251387358
75. Giulioni C, Cafarelli A, Falsetti F, et al. "Perioperative outcomes of ongoing antithrombotic therapy during endoscopic surgery for benign prostatic hyperplasia: a systematic review and meta-analysis of observational studies." Prostate Cancer Prostatic Dis. 2026;29(4):735-753. doi:10.1038/s41391-026-01098-4
76. Kosiba M, Filzmayer M, Welte MN, et al. "Thulium fiber laser vs. holmium laser enucleation of the prostate: results of a prospective randomized non-inferiority trial." World J Urol. 2024;42(1):49. doi:10.1007/s00345-023-04748-7
77. Long Depaquit T, Baboudjian M, Chiron P, et al. "Modified holmium laser enucleation for benign prostatic obstruction to preserve sexual and ejaculatory function." Fr J Urol. 2024;34(2):102581. doi:10.1016/j.fjurol.2024.102581
78. Manfredi C, et al. "Long-term functional outcomes and surgical retreatment after thulium laser enucleation of the prostate: A 10-year follow-up study." Int Braz J Urol. 2024;50(3):309-318. doi:10.1590/S1677-5538.IBJU.2024.0039
79. Gultekin MH, Sahin KC, Ozturk A, Irmak F, Onal B. "Ejaculation-preserving holmium laser enucleation of the prostate: a systematic review of techniques, functional outcomes, and safety." World J Urol. 2026;44(1):252. doi:10.1007/s00345-026-06348-7
80. Shah HN, Suarez Arbelaez MC, Shah K, et al. "Histopathological assessment of depth of coagulation necrosis with Holmium, Moses, and Thulium fiber lasers in human prostate tissue." World J Urol. 2023;41(11):3059-3063. doi:10.1007/s00345-023-04617-3
81. Filzmayer M, Cano Garcia C, Traumann MI, et al. "Thulium fiber laser versus Holmium laser enucleation of the prostate: 24-month outcomes from a prospective randomized non-inferiority trial." World J Urol. 2026;44(1):329. doi:10.1007/s00345-026-06338-9
82. Elmorsy YH, Elshal AM, El-Nahas AR, El-Assmy AM, Laymon M. "A randomized controlled trial comparing en-bloc vs lobe-by-lobe HoLEP: surgical efficiency and early continence outcomes." Prostate Cancer Prostatic Dis. 2026;29(3):551-557. doi:10.1038/s41391-025-01040-0
83. Elshal AM, Ghazy M, Ghobrial FK. "Enhancing continence post holmium laser enucleation of the prostate: assessment of novel technique through randomized clinical trial." Minerva Urol Nephrol. 2024;76(2):210-220. doi:10.23736/S2724-6051.24.05478-8
84. Morsy S, Elfeky M, Abdel-Rahman S, Torad H, Rammah A, Safwat M. "Comparing surgical techniques: ThuLEP and transurethral BPEP for prostate over 80 grams. Intraoperative and postoperative results. A prospective randomized trial." Arab J Urol. 2025;23(1):1-7. doi:10.1080/20905998.2024.2395594