Rezūm — Water Vapor Thermal Therapy (WVTT) for BPH
Rezūm (Boston Scientific) is a minimally invasive water vapor thermal therapy that uses radiofrequency-generated steam to ablate obstructive prostatic transition-zone tissue in men with LUTS secondary to BPH. In the sham-controlled pivotal trial, symptom improvement persisted through 5 years, no sustained de novo erectile dysfunction was reported, and surgical retreatment was 4.4%.[1] The AUA 2026 BPH guideline states that clinicians should offer WVTT as an option for prostates of 30–80 cc .[20] For positioning against other minimally invasive surgical therapies (MISTs), TURP and HoLEP, see the BPH & Male LUTS chooser.
Mechanism of action
Per the manufacturer's device description, radiofrequency energy heats sterile water into vapor (approximately 103 °C), delivered through a retractable needle in a transurethral handpiece. Each injection lasts approximately 9 seconds and delivers approximately 208 calories of convective thermal energy into the transition zone.[27] The vapor disperses through the interstitial spaces and releases stored thermal energy on contact, which causes cell death of hyperplastic tissue. The AUA guideline describes the treated tissue regressing through necrosis over the following weeks.[20] The treatment is designed to localize thermal effects within prostatic tissue, and a Cochrane review reports intended sparing of the urethra, bladder neck and external sphincter.[3] The Canadian IFU nevertheless reports urethral stricture and bladder-neck contracture.[22] In a 49-man cohort, median prostate volume fell 34% (IQR 16.7–49.2%) at 12 months.[25]
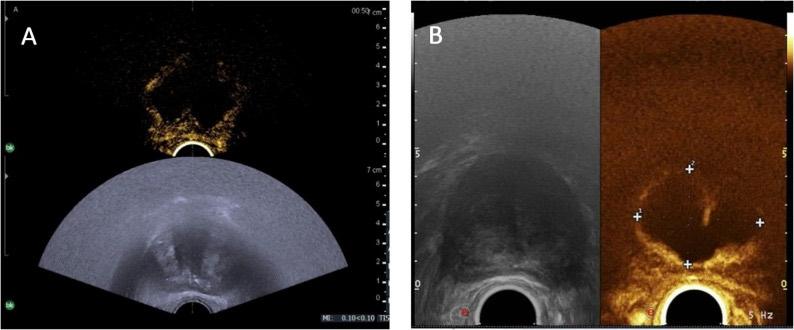
Contrast-enhanced transrectal ultrasound of the prostate immediately after (A) and 1 month after (B) a modified water vapor thermal therapy protocol for large-volume BPH; absent enhancement within the treated transition and central zones was taken as complete ablation. From Lu Q, et al. BMC Urol. 2026;26(1):64, Fig. 2 (CC BY 4.0).[23]
Procedure details
- Setting: office-based or ambulatory outpatient, under local anesthesia, oral sedation or conscious sedation.[4][5][20]
- Position: dorsal lithotomy, with the buttocks brought to the edge of the table so the delivery device can be inserted to full depth and rotated during the procedure.[22]
- Technique: cystoscopic confirmation of prostate contours; treatment needle positioned approximately 1 cm distal to the bladder neck, with injections delivered every 1 cm toward the verumontanum. The number of injections per lobe is determined by prostatic urethral length; the Canadian registry reported a mean of 11 injections per patient (range 4–28).[3][6] The manufacturer's directions add these points:[22]
- Measure the bladder-neck-to-verumontanum length by TRUS or cystoscopy. One treatment is a single 9-second vapor delivery.
- Suggested treatments per lateral lobe are 1 to 2 for less than 2.0 cm, 2 to 3 for 2.0 to 3.0 cm and 3 to 4 for more than 3.0 cm. One delivery device supports at most 15 full treatments.
- Use a 4 mm, 30-degree, 30 cm rigid lens and room-temperature saline. Prime the device with its tip over a liquid-waste container and directed away from the patient and personnel; vapor exiting during priming can burn skin. Run the separate pre-treatment vapor cycle before the device enters the patient.[22]
- Rotate the device 90 degrees so the needle enters the crest of the lateral lobe. Follow the slope of the urethra and never aim the needle toward the rectum. Place every treatment proximal to the verumontanum.
- Do not start vapor if the black depth marker is still visible after needle deployment. Hold the device still during the 9 seconds. Confirm the needle is fully retracted before moving the device. If the needle fails to retract, do not withdraw the device; follow the manufacturer's manual needle-retraction procedure before removal.[22]
- For an intravesical protrusion, place the device 1 cm from the proximal edge of the protrusion with the needle about 45 degrees toward the midline.
- Median lobe: treated at physician discretion in the pivotal trial.[1] The directions suggest one treatment for a median lobe under 2 cm and two or more for a larger one.[22] Four of the six treatment-arm subjects later retreated surgically had obstructive median tissue left untreated at the first procedure.[1]
- Procedure time: mean 4.8 min (range 1.5–14) in the Canadian registry; median 10.5 min (IQR 8.7–15) in the Italian multicenter cohort.[6][7]
- Post-procedure catheterization: in the pivotal trial, 90.4% (122/135) of treated men were catheterized before discharge versus 19.7% (12/61) of sham controls; the IFU reports mean catheter duration of 3.4 days (median 2.9 days; N=123) for treated men versus 0.9 days (N=12) for controls, and 68% (83/122) of treated men catheterized before discharge were catheterized at physician discretion.[22] A Canadian registry reported a longer mean of 9.8 days.[6] The AUA guideline notes that duration varies by practice, prostate volume and bladder function, from as short as 1 day for small prostates to a few weeks for very large prostates or poor bladder function.[20]
- Pain under local anesthesia: mean intraoperative VAS 3.6/10 among 71 of 82 patients with a recorded score; 36 of 49 satisfaction-questionnaire respondents rated the procedure 9 or 10/10.[5]
- Analgesia in the pivotal study: the Canadian IFU's Table 4 lists oral pain medication in 135/196 (69%), prostate block in 41/196 (21%) and IV sedation in 20/196 (10%) study participants.[22] The five-year report separately describes 188 men who received WVTT, of whom 170 (90.4%) received oral pain medication, 39 (20.7%) prostate block or epidural and 19 (10.1%) IV sedation.[1]
Patient selection and indications
- The pivotal trial enrolled prostates of 30–80 mL, the range in the cited 2021 Canadian directions.[22] In June 2025, the FDA cleared the US indication for men aged 50 or older with prostates of 30–150 cm³, including central-zone or median-lobe hyperplasia.[24] Real-world series include glands of 20–160 mL.[4][6][8] The AUA 2026 guideline offers WVTT as a Moderate Recommendation for 30–80 cc and, for prostates up to 150 cc under the expanded FDA indication, advises considering it only in appropriate patients and by clinicians with sufficient experience.[20]
- Moderate-to-severe LUTS (IPSS ≥ 13, Qmax ≤ 15 mL/s) refractory to or intolerant of medical therapy.[1][4]
- The directions contraindicate treatment with an artificial urinary sphincter, a penile prosthesis or an active UTI.[22] A 2026 Asia-Pacific expert consensus recommends preoperative urine culture and treatment of asymptomatic bacteriuria before WVTT.[30] Exclude urethral stricture as the cause of obstruction. Allow tissue to heal (for example 30 days) after prostate biopsy or prior prostate surgery. There are no data after pelvic radiation, and the system was not studied in men with prostate cancer.[22]
- Applicable to lateral lobes and median lobe obstruction.[1][9]
- Catheter-dependent retention is a separate selection scenario: observational Rezūm series report catheter-free rates of 68–100%, but comparative evidence and standardized follow-up are limited.[28]
- An option for men who wish to preserve erectile and ejaculatory function.[2][10]
- In a retrospective single-office series, 33/238 men had mild LUTS (IPSS ≤7), outside the pivotal trial's IPSS ≥13 eligibility.[11][1] Their median six-month nocturia change was 0 (IQR −1 to 0) despite a significant within-group test; IPSS worsened at one month and returned to baseline by three months.[11] The authors proposed Rezūm for selected men with bothersome nocturia who wished to stop BPH medication, a conclusion from observational data.[11]
- In a single-center multivariable analysis, diabetes was associated with a 3.67-point higher IPSS at 3 months.[12]
- No Rezūm-specific VTE-prophylaxis recommendation exists; as an office-based procedure under local anesthesia or light sedation it falls toward the low-risk end of the general urologic-surgery risk framework on the VTE Prophylaxis page, but individual risk factors (age, obesity, prior VTE, malignancy) still apply.
Clinical efficacy
The pivotal multicenter sham-controlled RCT randomized 197 men (136 treatment, 61 sham); 135 received treatment, and 77 completed the 5-year visit.[4][1]
| Outcome | At 3 months | At 5 years |
|---|---|---|
| IPSS reduction | ~ 50%[4] | 48%[1] |
| Quality of life (QoL) | ~ 50%[1] | 45%[1] |
| Peak flow rate (Qmax) | +6.2 mL/s[4] | 44% improvement[1] |
| BPH Impact Index | ~ 50%[13] | 48%[1] |
| Surgical retreatment rate | — | 4.4% |
Sources for the table: final 5-yr trial[1]; 3-yr[13]; 2-yr durability[9]. The 3-month figures come from the 2016 trial, in which IPSS fell by 11.2 points with Rezūm versus 4.3 with the sham procedure.[4] Sham-controlled comparison ended at 3 months, after which control-arm crossover occurred. Five-year symptom estimates include 77 of the 135 men treated in the original Rezūm arm (136 randomized); six of the 135 treated men (4.4%) underwent surgical retreatment, and 11.1% initiated BPH medication through five years.[1]
A Canadian prospective registry (n = 229, including 83 with prostates ≥ 80 mL) reported IPSS improvement of 59% and Qmax improvement of 74% at 12 months.[6] In a single-center analysis, IPSS improved significantly in all prostate-volume tertiles, and medium and large glands reached a 25% IPSS decrease sooner than small glands.[12]
In the retrospective single-office series, 66–88% of patients across LUTS-severity groups had stopped BPH medications at 12 months.[11]
In the 2026 VAPEUR randomized trial of 151 sexually active men, WVTT improved IPSS by 10.8 points versus 6.2 with combination medication at one year; treatment-related adverse events occurred in 40% versus 28%, including serious events in 12% versus 1.3%. Superiority for sexual-function preservation was not demonstrated after multiple imputation.[26] At one year, surgical retreatment was 1.3% after WVTT versus 9.2% with combination medication, while pharmacologic retreatment was 12% versus 1.3%; the trial's combined retreatment comparison was not statistically significant (HR 0.52, CI 0.25–1.1; p = 0.08).[26]
Safety profile
In the pivotal trial, adjudicated procedure- or device-related events through 4 years (treatment and crossover groups) were dysuria 17%, gross hematuria 12%, hematospermia 6%, urinary frequency 6%, decreased ejaculatory volume 5%, suspected UTI 5%, urinary retention 5%, urgency 5%, anejaculation 3%, culture-proven UTI 3%, epididymitis 2%, worsening erectile dysfunction 2% and urethral stricture 2%.[22] Among treatment and crossover subjects, 57% had no procedure- or device-related event; 80% of events occurred in the first 30 days, and 89% had resolved as of February 9, 2019.[22] Six serious events occurred in four men: prolonged retention from an untreated intravesical lobe, an allergic reaction to a sedative, bladder neck contracture with bladder stones, and urosepsis after cystoscopy.[22] Real-world series report higher rates for some events. Most adverse events reported are transient and mild (Clavien-Dindo Grade I–II). The Cochrane review, which found one sham-controlled trial, reported more minor adverse events with Rezūm than sham (RR 1.89) and a much higher need for indwelling catheters (RR 35.58), and was very uncertain about major adverse events.[14] Reported rates vary between series:[3]
- In one retrospective series, hematuria occurred in 58.8%, 71.7%, and 80.0% of the <30, 30–80, and >80 cc prostate-volume groups, respectively; another series reported gross hematuria in 66.5% overall, with most adverse events transient and nonserious.[8][11]
- In a 65-man open-label pilot, related non-serious dysuria affected 14 men (21.5%) within 12 months; a retrospective comparison reported postoperative dysuria in 22.8% of 307 WVTT recipients versus 8.3% of 110 PUL recipients within 90 days.[3][15][29]
- In a 65-man open-label pilot, 13 men (20.0%) had related non-serious urinary urgency within 3 months.[3][29]
- In a 65-man open-label pilot, related non-serious urinary retention (inadequate voiding for more than 24 hours) affected 22 men (33.8%) within 12 months; a retrospective comparison reported non-clot-related retention in 18.9% of 307 WVTT recipients versus 7.3% of 110 PUL recipients within 90 days.[3][15][29]
- In the pivotal-study adverse-event table through four years, suspected UTI was reported in 5% and culture-proven UTI in 3%.[22]
- No sustained de novo erectile dysfunction was reported through 5 years in the pivotal RCT.[1]
- The pooled anejaculation rate after Rezūm was 3% in a 2026 systematic review.[16]
- No Clavien-Dindo Grade ≥ III events in the Canadian registry.[6]
Sexual function preservation
The pivotal RCT reported no sustained de novo erectile dysfunction through 5 years.[1] The manufacturer's adverse-event table through 4 years still lists decreased ejaculatory volume (5%), anejaculation (3%, none resolved) and worsening erectile dysfunction (2%), so counsel about ejaculatory change.[22] The Italian multicenter cohort showed a small but statistically significant improvement in IIEF-5 at 6 months, which the authors suggested might reflect relief of urinary symptoms and better quality of life. They separately reported recovery of ejaculatory function after treatment and alpha-blocker interruption.[7] In a 100-man randomized trial of sexually active men with severe LUTS and 50–120 mL prostates, retrograde ejaculation at six months was reported in 1/49 evaluable WVTT recipients and 29/36 evaluable bipolar-TURP recipients; men with severe erectile dysfunction were excluded from this outcome.[33] A retrospective matched cohort of catheter-dependent men reported 3.7% after WVTT and 82.7% after TURP.[20]
Comparison with other treatments
A European Urology network meta-analysis of 63 RCTs found:[17]
- WVTT (Rezūm), PUL (UroLift), and PAE provide symptom and QoL improvements similar to TURP at short-term follow-up.
- TURP provides the greatest improvement in objective flow rate.
- Ejaculatory function favors WVTT and PUL over TURP.
- Separately, an indirect analysis of four RCTs did not detect a UroLift–Rezūm difference in urinary domain scores at 24 months.[18] A 2026 conference abstract from the CLEAR head-to-head RCT (35 WVTT and 38 PUL recipients in its 12-month analysis) reported failure to achieve catheter independence on postoperative days 3–7 in 20% versus 3% (p = 0.02); IPSS and surgical-intervention rates were similar at 12 months.[32]
A real-world head-to-head comparison of Rezūm versus UroLift (307 versus 110 patients) showed similar medium-term efficacy in AUA-SS, Qmax, and medication reduction. Rezūm had higher rates of postoperative dysuria (22.8% versus 8.3%) and non-clot retention (18.9% versus 7.3%); UroLift had higher clot retention (7.3% versus 2.6%).[15]
Durability and retreatment
Five-year data from the pivotal RCT show a surgical retreatment rate of 4.4%.[1] The manufacturer's directions report that 9 of 188 treated and crossover men (5%) sought alternative treatment within 4 years.[22] The AUA 2026 guideline reports overall WVTT reoperation rates of 3–4% over 1–5 years, and 4.6–9.7% over 1–3 years in other studies, where inadequately treated adenoma and bladder neck obstruction were common causes.[20] Indirect analyses summarized there show a higher retreatment rate with PUL than with WVTT.[20] The EAU 2026 guideline lists 4.4% surgical retreatment over 5 years, and 15.8% at 4 years when reinitiated drug therapy is counted with surgical reintervention.[21] A separate single-surgeon retrospective cohort of 155 men with prostates of 30–80 cc reported BPH medication restart or initiation in 48 (31%) over a mean follow-up of 19.5 months.[31] It places water vapor therapy among the techniques under investigation and makes no recommendation for it. It cites low- to very-low-certainty Cochrane evidence and a single-center RCT in which TURP gave greater IPSS, Qmax and PVR improvement at 24 months.[21] The 2026 pooled analysis noted that MIST follow-up is mainly limited to 24 months, and the Cochrane network meta-analysis noted limited long-term comparative data.[16][19]
Advantages and limitations
Advantages
- Office-based, under local anesthesia
- Short procedure time (approximately 5–10 min)
- The manufacturer reported no de novo erectile dysfunction in the pivotal trials, while its adverse-event table listed worsening erectile dysfunction in 2% and anejaculation in 3% of treatment and crossover subjects through 4 years.[22]
- Treats lateral lobes and median lobe
- Symptom improvement persisted through 5 years in the pivotal trial treatment arm, with 4.4% surgical retreatment.[1]
- At 12 months in one retrospective series, 66.0% of men with severe, 80.0% with mild, and 87.5% with moderate baseline LUTS had stopped BPH medication.[11]
Limitations
- Post-procedure catheterization is usually needed (mean 9.8 days in the 229-patient Canadian registry).[6]
- Transient irritative symptoms are common in the early postoperative period
- Less improvement in objective flow rate than with TURP[17]
- The strongest evidence is for prostates of 30–80 mL[1][20]
- Maximal benefit takes approximately 3 months
See Also
- BPH & Male LUTS chooser
- Prostate Enucleation / HoLEP: anatomic operation for medium-to-large glands
- UroLift / Prostatic Urethral Lift: sibling MIST
- Energy Devices for BPH
Podcasts
Videos
References
1. McVary KT, Gittelman MC, Goldberg KA, et al. Final 5-year outcomes of the multicenter randomized sham-controlled trial of a water vapor thermal therapy for treatment of moderate to severe lower urinary tract symptoms secondary to benign prostatic hyperplasia. J Urol. 2021;206(3):715–724. doi:10.1097/JU.0000000000001778
2. Kaltsas A, Giannakodimos I, Symeonidis EN, et al. To Rezūm or not to Rezūm: a narrative review of water vapor thermal therapy for benign prostatic hyperplasia. J Clin Med. 2025;14(12):4254. doi:10.3390/jcm14124254
3. Franco JV, Jung JH, Imamura M, et al. Minimally invasive treatments for lower urinary tract symptoms in men with benign prostatic hyperplasia: a network meta-analysis. Cochrane Database Syst Rev. 2021;7:CD013656. doi:10.1002/14651858.CD013656.pub2
4. McVary KT, Gange SN, Gittelman MC, et al. Minimally invasive prostate convective water vapor energy ablation: a multicenter, randomized, controlled study for the treatment of lower urinary tract symptoms secondary to benign prostatic hyperplasia. J Urol. 2016;195(5):1529–1538. doi:10.1016/j.juro.2015.10.181
5. Burns R, Dreyer B, Khadhouri S, Al Jaafari F. Rezum: analysis of the tolerability and complications of the procedure performed under local anaesthetic. J Clin Med. 2026;15(7):2560. doi:10.3390/jcm15072560
6. Elterman D, Bhojani N, Vannabouathong C, Chughtai B, Zorn KC. Large, multi-center, prospective registry of Rezūm water vapor therapy for benign prostatic hyperplasia. Urology. 2022;165:261–267. doi:10.1016/j.urology.2022.02.001
7. Siena G, Cindolo L, Ferrari G, et al. Water vapor therapy (Rezūm) for lower urinary tract symptoms related to benign prostatic hyperplasia: early results from the first Italian multicentric study. World J Urol. 2021;39(10):3875–3880. doi:10.1007/s00345-021-03642-4
8. Ines M, Babar M, Singh S, Iqbal N, Ciatto M. Real-world evidence with the Rezūm system: a retrospective study and comparative analysis on the efficacy and safety of 12-month outcomes across a broad range of prostate volumes. Prostate. 2021;81(13):956–970. doi:10.1002/pros.24191
9. Roehrborn CG, Gange SN, Gittelman MC, et al. Convective thermal therapy: durable 2-year results of randomized controlled and prospective crossover studies for treatment of lower urinary tract symptoms due to benign prostatic hyperplasia. J Urol. 2017;197(6):1507–1516. doi:10.1016/j.juro.2016.12.045
10. Nguyen DD, Li T, Ferreira R, et al. Ablative minimally invasive surgical therapies for benign prostatic hyperplasia: a review of Aquablation, Rezum, and transperineal laser prostate ablation. Prostate Cancer Prostatic Dis. 2024;27(1):22–28. doi:10.1038/s41391-023-00669-z
11. Babar M, Loloi J, Tang K, et al. Rezum water vapor therapy for patients with mild, moderate, or severe lower urinary tract symptoms: a retrospective study in a multiethnic population. Prostate. 2023;83(7):713–721. doi:10.1002/pros.24508
12. Lewer O, Felice MD, Copelan O, et al. Prostate size and its effect on lower urinary tract symptoms / benign prostatic hyperplasia improvement after convective water vapor thermal therapy. J Urol. 2025;214(1):48–57. doi:10.1097/JU.0000000000004516
13. McVary KT, Roehrborn CG. Three-year outcomes of the prospective, randomized controlled Rezūm system study: convective radiofrequency thermal therapy for treatment of lower urinary tract symptoms due to benign prostatic hyperplasia. Urology. 2018;111:1–9. doi:10.1016/j.urology.2017.10.023
14. Kang TW, Jung JH, Hwang EC, et al. Convective radiofrequency water vapour thermal therapy for lower urinary tract symptoms in men with benign prostatic hyperplasia. Cochrane Database Syst Rev. 2020;3:CD013251. doi:10.1002/14651858.CD013251.pub2
15. Chin CP, Garden EB, Ravivarapu KT, et al. Medium-term real-world outcomes of minimally invasive surgical therapies for benign prostatic hyperplasia: water vapor thermal therapy (Rezum) vs prostatic urethral lift (UroLift) in a high-volume urban academic center. J Endourol. 2022;36(12):1559–1566. doi:10.1089/end.2022.0385
16. Franco A, Ditonno F, Manfredi C, et al. Systematic review and pooled analysis of functional and sexual outcomes of minimally invasive surgical treatments for benign prostatic obstruction. Eur Urol. 2026;89(4):318–331. doi:10.1016/j.eururo.2025.09.004
17. Cornu JN, Zantek P, Burtt G, et al. Minimally invasive treatments for benign prostatic obstruction: a systematic review and network meta-analysis. Eur Urol. 2023;83(6):534–547. doi:10.1016/j.eururo.2023.02.028
18. Tanneru K, Jazayeri SB, Alam MU, et al. An indirect comparison of newer minimally invasive treatments for benign prostatic hyperplasia: a network meta-analysis model. J Endourol. 2021;35(4):409–416. doi:10.1089/end.2020.0739
19. Franco JVA, Jung JH, Imamura M, et al. Minimally invasive treatments for benign prostatic hyperplasia: a Cochrane network meta-analysis. BJU Int. 2022;130(2):142–156. doi:10.1111/bju.15653
20. Goueli R, Badlani GH, Welliver C, et al. Management of lower urinary tract symptoms attributed to benign prostatic hyperplasia: AUA guideline (2026). Statement 46, water vapor thermal therapy. American Urological Association; 2026.
21. European Association of Urology. EAU Guidelines on the Management of Non-neurogenic Male LUTS. 2026 (March update). Official full guideline. See section 5.3.4.c.1.
22. Boston Scientific. Rezūm Delivery Device Kit for BPH: Directions for Use, 51344625-01 Rev. A (2021, Canada edition). Manufacturer document, including the pivotal-study summary through 4 years.
23. Lu Q, Zhu G, Liu J, et al. Modified water vapor thermal therapy for large-volume benign prostatic hyperplasia. BMC Urol. 2026;26(1):64. doi:10.1186/s12894-026-02050-3
24. US Food and Drug Administration. Rezūm System: 510(k) K250584, decision and indications for use. June 11, 2025. FDA decision and indications
25. Elterman D, Bhojani N, Chughtai B, Zorn KC. "Change in prostate volume and symptom improvement in men treated with Rezūm water vapor therapy." Urology. 2023;177:142-147. doi:10.1016/j.urology.2023.04.008
26. Vincendeau S, Xylinas E, Fourmarier M, et al. "Water vapor thermal therapy with Rezūm versus combination pharmacotherapy for male lower urinary tract symptoms due to benign prostatic obstruction: 1-yr results from a prospective, multicenter, pragmatic randomized controlled trial (VAPEUR-RCT)." Eur Urol Focus. 2026;online ahead of print. doi:10.1016/j.euf.2026.08.001
27. Guelce D, Thomas D, Elterman D, Chughtai B. "Recent advances in managing benign prostatic hyperplasia: the Rezūm system." F1000Res. 2018;7:1916. doi:10.12688/f1000research.15851.1
28. Scilipoti P, Chicaud M, Abi Abdallah M, et al. "Minimally invasive surgical therapies in patients with catheter-dependent urinary retention: a collaborative mini-review." Eur Urol Focus. 2026;online ahead of print. doi:10.1016/j.euf.2026.03.003
29. Dixon CM, Cedano ER, Pacik D, et al. "Two-year results after convective radiofrequency water vapor thermal therapy of symptomatic benign prostatic hyperplasia." Res Rep Urol. 2016;8:207–216. doi:10.2147/RRU.S119596
30. Siu BWH, Ho JMH, Fam XI, et al. "Asia-Pacific collaborative consensus statements on water vapor thermal therapy (Rezūm) incorporating a systematic review, a two-round Delphi survey, and a consensus meeting." Prostate Int. 2026;14(2):173–190. doi:10.1016/j.prnil.2026.04.004
31. Nguyen V, Tran E, Cerrato C, Finegan JL, Leach MC, Bechis SK. "Do patients Rezum medications?—a real-world analysis of medical retreatment after water vapor thermal therapy." Transl Androl Urol. 2025;14(11):3546–3553. doi:10.21037/tau-2025-568
32. Barber N, Rochester M, Mazzarella B, et al. "P13-8 CLEAR RCT through 12 months: better early recovery with UroLift PUL vs Rezum with comparable durability" [conference abstract]. In: BAUS 2026 Abstract Book. J Clin Urol. 2026;19(1 suppl):abstract P13-8. doi:10.1177/20514158261451299
33. Samir M, Elaal AAA, Gad KAS, Basyony MW. "Two-year follow-up comparing Rezūm therapy versus bipolar transurethral resection of the prostate for treating benign prostatic hyperplasia. A prospective randomized study." Int J Urol. 2024;31(5):545–550. doi:10.1111/iju.15410