Simple Prostatectomy (Open / Laparoscopic / Robotic)
Simple prostatectomy is the surgical enucleation of the prostatic adenoma, typically reserved for large prostates (> 80 g). Approaches include open transvesical (Freyer), open retropubic (Millin), laparoscopic, and robotic-assisted (transvesical, transcapsular or urethra-sparing Madigan; multiport or single-port). Series report IPSS reductions of 14–22 points. A pooled analysis of reoperation rates after open prostatectomy gave 1.3% at 1 yr and 4.4% at 5 yr, among the lowest of the procedures in that review, and a German claims analysis found a lower 5-yr reintervention hazard than TURP for open simple prostatectomy (HR 0.43).[1][2][3]
For positioning versus HoLEP, MISTs, and TURP, see the BPH & Male LUTS chooser.
Indications
Generally > 80 mL (the 2022 CUA guideline describes >80–100 mL for laparoscopic or robotic simple prostatectomy).[4][1][5][63] Specific indications:
- Bothersome LUTS refractory to medical management
- Urinary retention from prostatic obstruction
- Recurrent UTI from incomplete bladder emptying
- Bladder stones or large diverticula (can be addressed concomitantly, for example with bladder diverticulectomy; favors transvesical)
- Renal insufficiency from BOO
- Recurrent gross hematuria from BPH[1][6]
Simple prostatectomy has been cautioned against in patients with a prior bladder augmentation, because of the risk of injury to the reconstructed bladder; in that setting, medical therapy, endoscopic outlet procedures, or a catheterizable channel are the alternatives discussed for patients who wish to continue catheterization.[54]
The AUA 2026 guideline states that clinicians should offer simple prostatectomy (open, laparoscopic or robotic) as an option for prostates larger than 80 cc , and should offer laser enucleation (HoLEP / ThuLEP) as an option for LUTS/BPH .[50] Earlier guidance and the Pandolfo review describe both as treatments of choice for large glands.[7][5] EAU 2026 strongly recommends open prostatectomy for prostates above 80 mL when endoscopic enucleation is not available, and HoLEP as an alternative to TURP or open prostatectomy.[51] EAU reports that open prostatectomy has similar short- and mid-term efficacy to HoLEP and bipolar enucleation in large glands (level 1a), with longer catheterization and hospital stay, more transfusions and a less favorable perioperative safety profile.[51]
Open techniques — Freyer vs Millin
| Transvesical (Freyer, 1900) | Retropubic (Millin, late 1940s) | |
|---|---|---|
| Approach | Bladder opened; finger enucleation through bladder neck | Capsular incision (transcapsular); direct adenoma exposure |
| Best when | Concomitant bladder pathology (diverticula, stones) | Standard adenoma without intravesical pathology |
| Bleeding | More: median EBL 640 mL vs 362 mL (p = 0.007) in a randomized study of 62 men that used a modified Millin technique | Less, with improved visualization of bleeding points[8] |
| Stress UI | Comparative risk unquantified | Comparative risk unquantified |
| Urethral division | Less precise | More accurate |
In Rohiem et al.'s endoscopically assisted open transvesical approach for large glands with bladder stones, the bladder was opened and stones removed; the ureteral orifices were identified before mucosal incision, finger enucleation followed the adenoma–capsule plane with care to avoid apical sphincter traction, and hemostatic sutures were placed at 5 and 7 o'clock when accessible. Their technique used a three-way urethral catheter, suprapubic drainage, two-layer cystotomy closure, and irrigation.[60]
The open Millin sequence has been described as follows: deep 0-chromic capsular sutures are placed transversely near the bladder neck and near the apex before the capsule is opened between them, and the adenoma is enucleated in the plane between capsule and adenoma; under direct vision the adenoma is divided just proximal to the membranous urethra to protect the sphincter. Figure-of-eight hemostatic sutures at the 5- and 7-o'clock positions control urethral branches of the prostatic arteries, and the posterior bladder-neck lip is then sutured to the posterior prostatic capsule, with excess neck tissue trimmed to leave a wide junction (bladder-neck trigonization). The chapter authors attribute reduced postadenectomy urethral stricture and a shorter catheter duration to this step, without a comparative study. Closure uses a large-bore (22–24 Fr) three-way catheter with the balloon tamponading the fossa, continuous bladder irrigation, and a Retzius-space drain.[52]
Modern minimally invasive
- Laparoscopic simple prostatectomy (LSP). Extraperitoneal Millin or transvesical. Reduced blood loss, shorter catheter and LOS versus open; advanced laparoscopic skills required.[9][10][11]
- Robot-assisted simple prostatectomy (RASP). Available with multiport and single-port (SP) platforms. In German nationwide inpatient data for 2013–2023 excluding concomitant bladder stones, robotic simple prostatectomy rose steeply and open declined, but open still accounted for 96% of 46,234 procedures.[12][13][14][15]
Modern RASP techniques — step by step
1. Transvesical (Freyer) RASP — multiport
This is the most widely described multiport technique.[29][30][31]
- Positioning and ports. Steep Trendelenburg, transperitoneal access. "W"-configuration ports (4 × 8-mm robotic plus 1–2 assistant). da Vinci Si / Xi docked four-arm.
- Bladder detachment and cystotomy. Bladder mobilized off anterior abdominal wall; longitudinal anterior cystotomy exposes bladder neck and adenoma. Keith needles through abdominal wall can retract bladder edges.[29]
- Adenoma enucleation. Identify the trigone and both ureteral orifices before a mucosal incision around the adenoma, keeping the incision clear of the orifices.[59] Use sharp and blunt dissection in the plane between adenoma and surgical capsule from bladder neck to apex; divide the urethra at the apex.
- Hemostasis. Selective coagulation of bladder-neck vessels at 5 and 7 o'clock.
- Trigonization and closure. Running 2-0 Polysorb or barbed suture advances bladder mucosa over the prostatic fossa to reduce raw surface area; cystotomy closed in 2 layers; Foley and water-tightness test.[29]
- Specimen retrieval. Remove the adenoma through the optical-port incision or an Endo Catch bag and submit it for histopathology. A six-center SP-RASP series found incidental cancer in 11/235 specimens (4.6%), including clinically significant cancer in 2.1%; arrange grade-appropriate follow-up when found.[61]
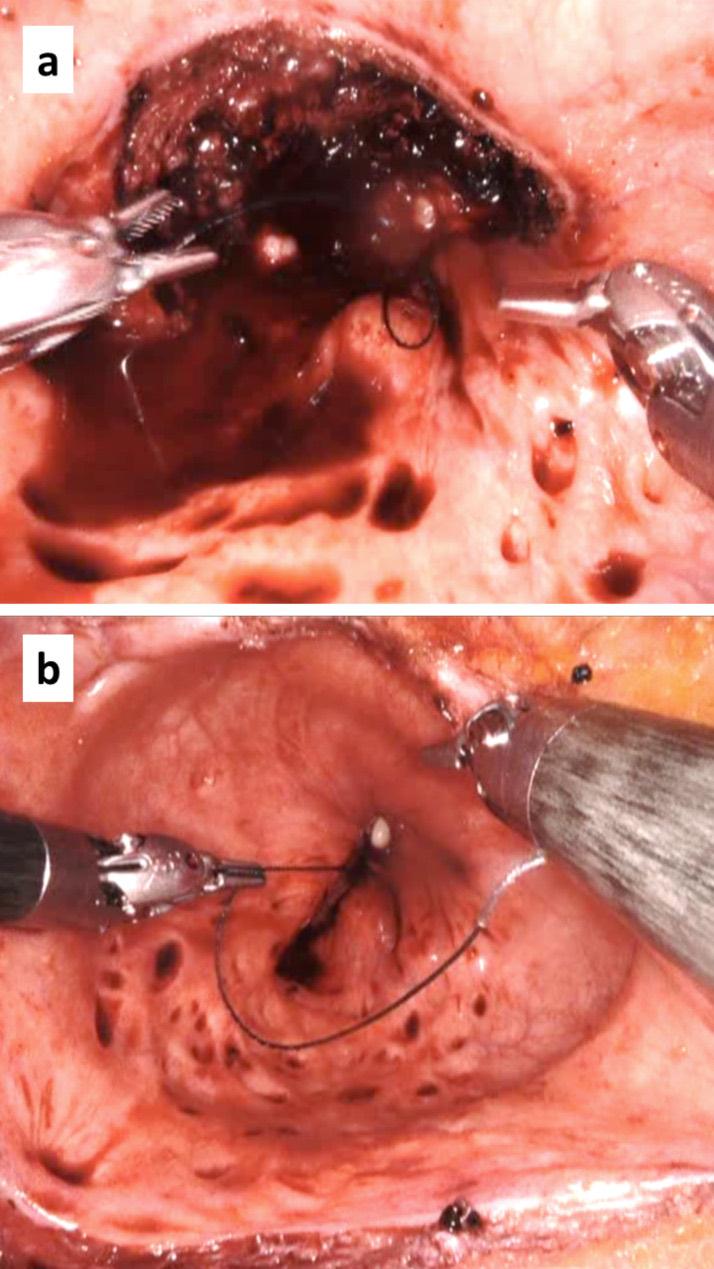
Trigonization during robot-assisted transvesical simple prostatectomy after adenoma removal. (a) Bleeding from the prostatic fossa obscures the operative field. (b) Approximating the bladder neck to the urethra with a unidirectional barbed suture substantially improves hemostasis. From Larsen M, et al. BMC Urol. 2024;24(1):221, Fig. 2 (CC BY 4.0).[55]
2. Transcapsular (Millin) RASP — multiport
Mirrors the open Millin; avoids entering the bladder.[31][16][30]
- Retropubic-space development. Retzius space developed and endopelvic fascia exposed, mirroring radical-prostatectomy initial steps (an advantage for surgeons experienced in robotic RP).[31]
- Capsulotomy. Transverse incision on the anterior prostatic capsule, distal to the bladder neck.
- Adenoma enucleation. Sharp and blunt dissection within the capsule from capsulotomy to apex.
- Closure. Capsulotomy closed with running suture; some surgeons perform a vesicourethral anastomosis as in radical RP.
3. Urethra-sparing (Madigan) RASP — designed for ejaculatory-function preservation
This variant has been described in small series.[32][33] A 2025 meta-analysis of five retrospective comparisons reported that urethra-sparing RASP was associated with an 8.09-point higher postoperative-minus-preoperative change in MSHQ-EjD score than conventional RASP across four reporting studies (95% CI 5.92–10.26; I² = 68%).[58]
- Transcapsular access.
- Urethral identification with ICG and near-infrared fluorescence. Simone / Misuraca 2019 retrograde injection of indocyanine green through the Foley illuminates the prostatic urethra under da Vinci Firefly; the surgeon dissects around the fluorescent urethral tube.[32]
- Selective lobe enucleation replaces en-bloc removal: each lobe is peeled off the urethra circumferentially while the urethra and ejaculatory ducts are preserved.
- Porpiglia 2021 Eur Urol (prospective, n = 92, with a retrospective Millin control group; small sample and short follow-up): full urethral sparing 61%, partial 23%, conversion to standard RASP 16%. Of 70 patients with preoperative ejaculation, 81% maintained anterograde ejaculation at 12 mo.[33]
- Original Simone ICG-guided cohort: 66% satisfactory anterograde ejaculation at 12 mo.[32]
4. Single-port (SP) transvesical RASP
The da Vinci SP platform allows an intravesical approach through a single small incision.[34][14]
- Access. Through a 3-cm suprapubic incision, enter the bladder and dock the SP arm directly into the bladder lumen; the camera and 3 articulating instruments emerge from a single cannula. Use controlled intravesical insufflation; abrupt hypotension or desaturation warrants evaluation for possible gas embolism. Suspected events were reported in early SP series and attributed to high insufflation pressure in a 117-case series.[14][34]
- Enucleation. Adenoma enucleated from within the bladder under direct visualization of the bladder neck and prostatic fossa.
- 360° mucosal flap reconstruction. Bladder mucosa is advanced and sutured circumferentially to the urethral stump, separating the residual raw fossa from the urinary lumen. In the reported series, routine continuous bladder irrigation was avoided; reduced postoperative bleeding and irritative symptoms remain proposed benefits.[34][35]
- Ramos 2024 Eur Urol (retrospective, 117 cases; 1-yr functional outcomes analyzed among patients with at least 12 mo of follow-up): median console 107 min, EBL 100 mL, 0% transfusion, 95.8% discharged within 24 h (median LOS 5 h), no major postoperative complications, median catheter 5 d, and persistent IPSS and flow-rate improvement at 1 yr. Two intraoperative suspected air emboli were attributed to high insufflation pressure.[34]
5. Novel approaches
- Trans-Douglas (Retzius-sparing) RASP. De Concilio 2018: posterior peritoneal approach preserving the bladder neck; one reported patient had 80 mL blood loss, catheter removal on day 4, and IPSS improvement from 30 to 8 at 60 days.[36]
- Intrafascial RASP. Poncel 2023: dissection between prostatic capsule and surrounding fascia preserving NVBs; successfully applied to a 470 g prostate with IPSS 34 to 3 and preserved EF (SHIM 23).[37]
- Hugo RAS platform. Piro 2023 first large series (n = 20): median OR 165 min, catheter removal POD1 in 80%, median LOS 3 d.[38]
RASP technique comparison
| Parameter | Transvesical (MP) | Transcapsular (MP) | Madigan (urethra-sparing) | Single-port TV |
|---|---|---|---|---|
| Console time (min) | 91–160 | 71 | 150 | 107 |
| EBL (mL) | 100–200 | 200 | 250 | 100 |
| Transfusion rate | 5% (2/40) in MP comparison[16] | 0% (0/60) in MP comparison[16] | — | 1.1% (1/91) in multicenter series; 0% (0/117) in Ramos series[14][34] |
| Catheter duration (d) | 6.7–8 | 4.3 | 7 | 5 |
| LOS (d) | 4–6 | 5 | 3 | 5 hours |
| Same-day discharge | No transvesical-specific rate reported | No transcapsular-specific rate reported | Not quantified for Madigan | 42% in a 91-patient multicenter series; 48% in a HoLEP comparison; 92% of 23 after excluding planned admissions[14][41][47] |
| Ejaculation preservation | — | — | 8/12 (66%) at 12 mo in Simone; 57/70 (81%) at 12 mo in Porpiglia[32][33] | — |
| Major complications | 12.5% (5/40) in MP comparison[16] | 3.3% (2/60) in MP comparison[16] | 2/92 (2%) grade ≥3 in attempted urethra-sparing cohort[33] | 0/117 major postoperative complications in Ramos series[34] |
| Best fit | Bladder pathology | Surgeon familiarity (robotic-RP background) | Sexually active men | Enhanced recovery / same-day pathway |
References: transvesical / multiport general[29][30][31]; transvesical-vs-transcapsular[16]; Madigan[13][32][33]; SP transvesical[14][34].
360° Circumferential Mucosal Flap Reconstruction
The 360° circumferential mucosal flap reconstruction approximates bladder mucosa circumferentially to the urethral edge to reduce exposed capsular surface. Cacciamani's 23-patient technical series proposed that circumferential reconstruction might lessen bleeding and irritative symptoms, without a trigonization comparator.[35] Ramos's 117-patient single-port series used no routine CBI.[34] In a 2025 single-surgeon multiport series of 292 men undergoing circumferential anastomosis, postoperative CBI was not used and no bladder-neck contracture or LUTS reoperation was observed (mean clinical follow-up 22.6 months). Among 198/288 contacted survey respondents at mean 66 months, mean IPSS was 2.1.[59] It extends traditional "trigonization" and is the reconstruction used in the single-port transvesical RASP series cited here.
Concept and rationale
After enucleation, the prostatic fossa is a large, raw, vascularized cavity lined by the surgical capsule. Two reconstruction strategies have been used historically:
| Approach | What it does | Trade-off |
|---|---|---|
| Trigonization (traditional) | Bladder mucosa advanced and sutured only at the posterior bladder neck (trigone area), covering a limited portion of the fossa | Raw capsular surface remains exposed and is managed with electrocautery and postoperative CBI[29] |
| 360° mucosal flap reconstruction | Bladder mucosa circumferentially advanced and sutured to the distal urethral stump, separating the residual prostatic fossa from the urinary lumen | Reduces exposed raw capsular area and aims to minimize electrocautery; routine CBI was avoided in the cited uncontrolled series, but comparative hemostatic benefit remains unproven.[35][59] |
The proposed rationale is that exposed raw capsular surface contributes to postoperative bleeding and irritative symptoms, and that covering it with mucosa reduces both.[35][46]
Step-by-step technique (Cacciamani 2018)
The original 23-patient description:[35]
- Adenoma enucleation. Standard transperitoneal transvesical approach; sharp and blunt dissection from bladder neck to apex.
- Hemostasis of the fossa. Selective coagulation of active bleeders only; minimize cautery (excessive cautery contributes to postop irritative symptoms and delayed healing).
- Initiation of the mucosal flap. First suture at the 9 o'clock position on the prostatic fossa using 2-0 barbed (V-Loc) suture to approximate bladder-mucosa edge to urethral stump.
- Counter-clockwise circumferential closure. Running suture from 9 o'clock to 6 o'clock (posterior) to 3 o'clock (contralateral) to 12 o'clock (anterior). At each point bladder mucosa is advanced and approximated to the corresponding urethral edge.
- Completion. Full mucosal-to-mucosal anastomosis encircling the entire fossa, analogous to a vesicourethral anastomosis in radical prostatectomy. The mucosa-to-mucosa anastomosis separates the raw capsular fossa from the urinary lumen; residual fossa dead space remains.[35][59]
- Cystotomy closure. Anterior cystotomy closed in 2 layers; Foley and water-tightness test.
Modified vesicourethral anastomosis (Coelho 2012)
An earlier related technique combined three reconstructive steps:[46]
- Posterior capsular plication. Running suture to reduce dead space and approximate posterior bladder neck to the urethra.
- Modified van Velthoven vesicourethral anastomosis. Continuous running suture circumferentially.
- Anterior capsular closure. Anterior prostatic capsule sutured to anterior bladder wall.
Initial 6-patient series: 0% transfusion, 0% CBI, mean EBL 208 mL, all discharged POD 1.[46]
Application in single-port transvesical RASP
The 360° mucosal flap is the reconstructive step of SP-RASP; the articulating SP instruments working within the bladder give visualization of the fossa for this reconstruction:[34][47][48]
- After enucleation, bladder-mucosal edges mobilized circumferentially; mucosa advanced as a vesicourethral mucosal advancement flap sutured to the urethral stump using barbed suture.
- Abou Zeinab 2022 J Endourol. Refined flap technique reduced median catheter from 7 d to 3 d in the last 19 consecutive patients.[47]
- Ramos 2024 Eur Urol (n = 117): 360° reconstruction in all cases; no routine CBI or drains; 0% transfusion, 95.8% discharged within 24 h (median LOS 5 h), no major postoperative complications.[34]
360° reconstruction vs traditional trigonization
No head-to-head RCT exists. The columns below compare separate, non-randomized series:
| Parameter | 360° mucosal flap | Traditional trigonization |
|---|---|---|
| CBI use in cited series | Not routine in 117 single-port cases[34] | Not quantified in the 28-case traditional transvesical report[29] |
| EBL (mL) | 99–100 | 200 |
| Transfusion rate | 0/23 in the 360° series[35] | Not established in the cited series |
| LOS | 2.1 d / 5 h (SP) | 4–6 d |
| Catheter duration (d) | 3–5 (SP) | 7–8 |
| Same-day discharge | 42% overall in a multicenter SP series; 92% of 23 after excluding planned admissions[14][47] | Rare |
| Postoperative hematuria | Reduction proposed; no direct comparison[35] | No direct comparative estimate |
| Irritative symptoms | Reduction proposed, not demonstrated[35] | No direct comparative estimate |
References: Cacciamani 2018[35], Ramos 2024[34], Chavali 2018[29], Coelho 2012[46], Abou Zeinab 2022 J Endourol[47], Abou Zeinab 2022 J Urol[14].
Cockrell / Lee bladder-edge-to-apical-margin variant
A related but distinct approach in transcapsular RASP: bladder edge sutured to the distal apical prostate margin (rather than the urethral stump), mirroring the radical-prostatectomy anastomosis. Reported to greatly reduce postoperative hematuria without requiring full 360° mucosal advancement.[31]
Open-surgery parallel — modified bladder-neck repair without CBI
In an open simple-prostatectomy retrospective before-and-after series (Okorie 2010), clot retention occurred in 11/43 men with standard hemostasis plus CBI and 2/39 with modified bladder-neck repair and no CBI (p = 0.01); two bladder-wall disruptions occurred in the earlier group and none in the later group.[49]
Technical pearls and pitfalls
- Barbed suture (2-0 V-Loc or similar) maintains tension without knot-tying for continuous running closure in a confined space.[35]
- Mucosal mobility. Bladder mucosa must be adequately mobilized from the underlying detrusor for tension-free advancement to the urethral stump; insufficient mobilization risks pull-through or incomplete coverage.
- Urethral stump identification. Clear identification of the distal urethral stump is critical; in SP-RASP, the intravesical vantage gives apical visualization.
- Posterior wall first. Some surgeons start at 6 o'clock where the mucosa is thickest and the trigone is a firm anchor, then proceed anteriorly.
- Avoiding the ureteral orifices. Care during posterior mucosal advancement to avoid incorporating or kinking the orifices, particularly with intravesical prostatic protrusion that distorts the trigone.
In small non-randomized reports using circumferential reconstruction, postoperative CBI was not routinely used; selected single-port series reported same-day discharge, and one reported median catheter duration of 3 days in its final 19 patients after technique adjustment.[14][34][47]
Comparative outcomes — RASP vs OSP / LSP / HoLEP
Pandolfo 2023 SR/meta of 6,659 patients across 15 studies:[7]
| Parameter | RASP vs OSP | RASP vs LSP | RASP vs Laser EEP |
|---|---|---|---|
| OR time | Longer | Similar | Not reported for HoLEP; ThuLEP shorter |
| EBL | Lower | Similar | — |
| Transfusion rate | Lower | — | Higher |
| LOS | Shorter | Shorter with RASP (LSP longer) | Longer |
| Catheter duration | Shorter | — | Longer |
| Complications | Lower | Similar | — |
| IPSS / Qmax | No significant difference detected | No significant difference detected | No significant difference detected[7] |
Pyrgidis 2025 German nationwide inpatient analysis (n = 46,234 without concomitant bladder stones; 96% open, 3% robotic, 1% laparoscopic): compared with transcapsular OSP, in-hospital transfusion was lower with LSP (6.5%) and RASP (7.3%) versus 13%, in-hospital retention was less frequent, and median stay was 4 d (LSP) and 7 d (RASP) versus 9 d (transcapsular OSP).[15]
Benarroche 2022 single-center RASP versus OSP (retrospective): blood loss 200 versus 400 mL, LOS 5 versus 10 d, catheter 4 versus 9 d, Grade ≥ 2 complications 4.3% versus 23.2% (p = 0.005); identical functional outcomes at 12 mo.[17]
vs HoLEP for prostates > 80 cc
Both are guideline-recommended for large glands. In a multicenter randomized trial of 110 men with prostate volumes ≥120 mL (36 LSP, 32 RASP, 42 HoLEP), functional outcomes showed no significant between-group difference over mean 26.15-month follow-up; LSP catheterization was longer than in the other groups, and the simple-prostatectomy groups had longer hospitalization than HoLEP.[62]
Lee 2023 retrospective single-center comparison (n = 340: 209 HoLEP, 66 OSP, 65 RSP):[18]
| HoLEP | OSP | RASP | |
|---|---|---|---|
| OR time (h) | 1.4 | 2.7 | 3.8 |
| LOS (d) | 0.65 | 4.2 | 2.6 |
| Catheter (d) | 0.38 | 9.9 | 11.2 |
| EBL (mL) | 66 | 795 | 326 |
Benzouak 2025 SR and meta-analysis, Grosso 2024 propensity-matched, Palacios 2023 SP-RASP versus HoLEP and Glucksman 2026 single-center MP versus SP versus HoLEP synthesis:[39][40][41][42]
| Parameter | RASP | HoLEP | p |
|---|---|---|---|
| OR time | ~ 50 min longer | shorter | 0.001 |
| EBL (mL) | 200 in Benarroche's RASP-vs-OSP cohort[17]; 326 in Lee's three-arm cohort[18] | 66 in Lee's HoLEP cohort[18] | <0.0001 overall across HoLEP, OSP and RASP in Lee[18] |
| Transfusion rate | higher | 75% lower risk with HoLEP | sig[39] |
| Catheter duration (d) | 5–11 | 0.4–3 | 0.001 |
| LOS (d) | 2.6–5 | 0.65–4 | variable |
| Same-day discharge (SP-RASP vs HoLEP) | 48% | 8% | < 0.01[41] |
| IPSS / Qmax | equivalent | equivalent | NS |
| Transient incontinence (SP-RASP vs HoLEP) | 5% de novo; 8% transient | 28% de novo; 30% transient | < 0.01 (two-group); 0.004 (three-group overall)[41][42] |
| Antegrade ejaculation (propensity-matched) | 55% | 7% | 0.001[40] |
| Trifecta (Grosso: no complication by 1 mo, Qmax >15 mL/s at 1 mo, no urinary incontinence at 3 mo) | 82.6% | 76.1% | NS[40] |
| Grade 2 complications | 1.87× higher risk with RASP | lower | sig |
| Grade ≥ 3 complications | 3.41× higher risk with RASP | lower | sig |
| Median % adenoma removed (SP-RASP vs HoLEP) | 57% | 51% | 0.10[41] |
Summary:
- Functional outcomes (IPSS, Qmax, PVR) were similar across the cited studies and meta-analyses.[39][43]
- HoLEP advantages. In the Benzouak meta-analysis HoLEP had about 49 min shorter operative time, 3.8 d shorter catheterization and 1.5 d shorter stay, with a 75% lower transfusion risk. RASP patients had 1.87 times the risk of grade 2 complications and 3.41 times the risk of grade 3 or higher complications.[39]
- Advantages reported in selected RASP cohorts. A retrospective SP-RASP versus HoLEP comparison reported transient de novo incontinence of 5% versus 28% and same-day discharge of 48% versus 8%; a separate propensity-matched RASP versus HoLEP comparison reported antegrade ejaculation of 55.3% versus 6.8%.[40][41] A 2026 meta-analysis of 13 studies (n = 1,993) found no significant pooled difference in postoperative stress or urge incontinence between HoLEP and RASP.[56]
- Learning curve. RASP is described as having a shorter learning curve than HoLEP because its steps mirror robotic radical prostatectomy. HoLEP is described as having a steep learning curve (50–100+ cases for proficiency).[7][39]
- SP-RASP specifically. One series favors it for unfavorable urethral access, large bladder-stone burden, or bladder diverticula requiring concomitant repair.[41]
The Hinojosa-Gonzalez 2026 Bayesian network meta comparing all RASP variants versus enucleation found no significant differences in overall complication rates and similar improvements in flow rates. SP-TV-RASP had the highest ranking for IPSS improvement and lowest incontinence rates, though the differences were not statistically significant.[43]
RASP vs Aquablation
Gangwish 2025 was a single-institution retrospective comparison of 172 men with prostates > 80 mL (111 Aquablation, 61 open or robotic simple prostatectomy), adjusted by inverse probability weighting:[44]
- Aquablation. Simple prostatectomy had higher transfusion rates (OR 4.22), longer stay (by 1.7 d) and longer operating time (by approximately 119 min).[44]
- Simple prostatectomy. Better 1-yr IPSS (β = −3.4, p = 0.005), lower retreatment (OR 0.46, p = 0.019) and less postoperative alpha-blocker use (p = 0.001).[44]
- QoL and adverse-event rates were comparable.
In WATER II (101 men with 80–150 mL prostates), Kaplan–Meier freedom from a secondary BPH procedure at 5 yr was 96.3%; 60/101 completed the 5-yr visit, and among participants with 5-yr measurements mean IPSS fell 15.9 points and mean Qmax rose 9.2 mL/s.[45] WATER II enrolled prostates of 80–150 mL, whereas RASP has no defined upper size limit; a case of 470 g has been reported.[37]
Clinical efficacy
| Outcome | Simple prostatectomy |
|---|---|
| IPSS improvement | −14 to −22 points at 8–40 mo |
| Qmax improvement (open prostatectomy) | +16.5 to +20.2 mL/s; efficacy maintained up to 6 yr[51] |
| Postop IPSS (RASP) | Median 3–5 |
| Postop Qmax (RASP, prostates ≥100 cm³) | Mean 18–29.6 mL/s across cohorts[57] |
| Time to maximal improvement | ~ 3 mo, stable through ≥ 36 mo |
In Lee 2020 (n = 150 RASP, 31-mo mean), IPSS and QoL maximal by 3 mo and stable through ≥ 36 mo, with no bladder neck contractures and no reoperations for LUTS.[19]
Durability and retreatment
Reoperation after simple prostatectomy is low in observational data.
- Gilfrich 2021 (German claims, n = 43,041, 5-yr follow-up): open simple prostatectomy carried a lower reintervention hazard than TURP (HR 0.43, 95% CI 0.37–0.50); laser enucleation did not differ significantly (HR 0.84, 95% CI 0.66–1.08).[2]
- He 2023 systematic review (119 studies overall): pooled reoperation after open prostatectomy was 1.3% at 1 yr (7 studies; 95% CI 0.3–2.8%) and 4.4% at 5 yr (4 studies; 95% CI 1.5–8.7%).[3]
- Eredics 2018 Austrian nationwide: 8-yr re-TURP rate 4.3% after open prostatectomy versus 8.3% after primary TURP.[20]
- A 1993 study of 92 patients treated with either transurethral or open prostatectomy reported that 95% of the combined cohort remained nonobstructed and subjectively satisfied at 5 years.[21]
Complications
Perioperative
- Blood loss and transfusion. Blood loss remains a perioperative concern, especially with open surgery. Retrospective cohorts reported median RASP versus OSP estimated blood loss of 200 versus 400 mL (47 versus 56 men)[17] and estimated blood loss of 326 versus 795 mL (65 versus 66 men)[18]. The first cohort recorded transfusion in 0/47 versus 6/56 men; German inpatient data recorded 7.3% (98/1,335) after RASP versus 13% (1,472/11,755) after transcapsular OSP.[17][18][15] Earlier selected series reported 0% transfusion in more than 75% of eight RASP case series (109 men total), while one 37-man open series had mean blood loss of 841 mL and transfusion in 6/37 (16%).[22][23]
- Mortality. < 1%. EAU 2026 cites mortality of 0.2% at 30 days and 0.4% at 90 days in a series of 1,286 men, and a transfusion rate of about 7–14%.[6][20][51]
- Overall complication rate. 30% with RASP (mostly Clavien I–II); 4.5% Clavien IIIb in one series.[12]
- Venous thromboembolism. One pulmonary embolism occurred among 37 men in a single-surgeon open series; the cohort is too small to estimate current risk.[23] No recommendation specific to simple prostatectomy exists; as an open or robotic major pelvic operation it is reasonable to apply the general urologic-surgery risk framework on the VTE Prophylaxis page.
Postoperative
- Bladder neck contracture. None among 150 RASP patients at mean 31.3 months; 5/151 (3.3%) evaluable open transvesical prostatectomy patients at mean 41.8 months.[19][24] One chapter's authors report bladder-neck stenosis as more common in their laparoscopic experience and associate it with a transvesicocapsular incision, recommending a transverse incision at the bladder-neck level instead; this is an unquantified single-center observation.[53]
- Urethral stricture. 1/151 (0.6%); meatal stenosis occurred in 2/151 (1.3%) evaluable open transvesical prostatectomy patients at mean 41.8 months.[24]
- Urinary incontinence. A review reports 0–20% at 0–3 months after open or robotic simple prostatectomy; an open series reported stress incontinence in 3/37 (8%) without specifying persistence.[1][23]
- UTI: variable.
- Long-term. EAU 2026 cites persistent incontinence, bladder neck contracture and urethral stricture in about 6% combined, and endourologic reintervention of 0.9%, 3.0%, 6.0% and 8.8% at 3 months, 1 year, 5 years and 8 years after open prostatectomy in an Austrian nationwide study of 2,452 men.[51]
Sexual function
- Retrograde ejaculation 80–90%. Most common sexual side effect after open or robotic simple prostatectomy; the same review reports 60–75% after TURP.[1]
- Erectile dysfunction 3–5% after open or robotic simple prostatectomy in a review table.[1]
- In a retrospective single-center comparison of 45 men, Madigan urethra-sparing RASP (n = 14) was associated with higher self-reported IIEF and MSHQ scores at 1 year than Millin (n = 23) or Freyer (n = 8) (IIEF p = 0.04; MSHQ p = 0.008).[13]
- Sexual desire and overall satisfaction generally preserved; orgasm and ejaculation commonly affected.[25]
Impact on subsequent radical prostatectomy
Creta 2024 SR and meta-analysis (n = 11,101): prior BPH surgery (including simple prostatectomy) is associated with:[26]
- Higher positive surgical margin rate (OR 1.39)[26]
- Lower continence at 3 mo and 1 yr (OR 0.48 and 0.44)[26]
- Lower erectile function recovery at 1 yr (OR 0.60)[26]
Salvage simple prostatectomy after failed prior procedures
Retrospective series describe RASP after failed transurethral procedures. Pathak 2023 studied 124 men (26 salvage after TURP, TUMT, TUNA, or UroLift); postoperative IPSS was 5.33 after primary and 8.00 after salvage RASP at about 12 months (p = 0.38). Lee 2023 studied 520 men, including 87 (16.7%) with prior TURP, PVP, TUMT, prostatic urethral lift, or Rezūm; measured perioperative and functional outcomes did not differ significantly between groups.[27][28]
Advantages and limitations
Advantages
- Low reoperation rates in observational data
- Large symptom and flow improvements
- Size-independent, with no upper limit on prostate volume
- Can address concomitant bladder pathology (stones, diverticula)
- RASP offers minimally invasive recovery with a learning curve described as shorter than HoLEP
- Effective as salvage after failed prior procedures
Limitations
- Requires general / regional anesthesia and hospitalization
- Higher retrograde ejaculation rate (80–90%)[1]
- Longer catheterization (4–11 d) and LOS than endoscopic alternatives
- Open approach carries significant blood-loss / transfusion risk
- Robotic approach requires capital equipment and longer OR time
See Also
- BPH & Male LUTS chooser
- Prostate Enucleation / HoLEP: endoscopic alternative for the same large-gland indication
- Rezūm (WVTT) and UroLift / PUL: MISTs in the smaller-gland and sexual-function-preservation niche
- Energy Devices for BPH
Videos
References
1. Wei JT, Dauw CA, Brodsky CN. Lower urinary tract symptoms in men. JAMA. 2025;334(9):809–821. doi:10.1001/jama.2025.7045
2. Gilfrich C, May M, Fahlenbrach C, et al. Surgical reintervention rates after invasive treatment for lower urinary tract symptoms due to benign prostatic syndrome: a comparative study of more than 43,000 patients with long-term followup. J Urol. 2021;205(3):855–863. doi:10.1097/JU.0000000000001463
3. He W, Ding T, Niu Z, et al. Reoperation after surgical treatment for benign prostatic hyperplasia: a systematic review. Front Endocrinol. 2023;14:1287212. doi:10.3389/fendo.2023.1287212
4. Arnold MJ, Gaillardetz A, Ohiokpehai J. Benign prostatic hyperplasia: rapid evidence review. Am Fam Physician. 2023;107(6):613–622. PMID 37327163
5. Sandhu JS, Bixler BR, Dahm P, et al. Management of lower urinary tract symptoms attributed to benign prostatic hyperplasia (BPH): AUA guideline amendment 2023. J Urol. 2024;211(1):11–19. doi:10.1097/JU.0000000000003698
6. Thorpe A, Neal D. Benign prostatic hyperplasia. Lancet. 2003;361(9366):1359–1367. doi:10.1016/S0140-6736(03)13073-5
7. Pandolfo SD, Del Giudice F, Chung BI, et al. Robotic assisted simple prostatectomy versus other treatment modalities for large benign prostatic hyperplasia: a systematic review and meta-analysis of over 6500 cases. Prostate Cancer Prostatic Dis. 2023;26(3):495–510. doi:10.1038/s41391-022-00616-4
8. Dall'Oglio MF, Srougi M, Antunes AA, Crippa A, Cury J. An improved technique for controlling bleeding during simple retropubic prostatectomy: a randomized controlled study. BJU Int. 2006;98(2):384–387. doi:10.1111/j.1464-410X.2006.06236.x
9. Rehman J, Khan SA, Sukkarieh T, Chughtai B, Waltzer WC. Extraperitoneal laparoscopic prostatectomy (adenomectomy) for obstructing benign prostatic hyperplasia: transvesical and transcapsular (Millin) techniques. J Endourol. 2005;19(4):491–496. doi:10.1089/end.2005.19.491
10. Baumert H, Ballaro A, Dugardin F, Kaisary AV. Laparoscopic versus open simple prostatectomy: a comparative study. J Urol. 2006;175(5):1691–1694. doi:10.1016/S0022-5347(05)00986-9
11. Chlosta PL, Varkarakis IM, Drewa T, et al. Extraperitoneal laparoscopic Millin prostatectomy using finger enucleation. J Urol. 2011;186(3):873–876. doi:10.1016/j.juro.2011.04.080
12. Pokorny M, Novara G, Geurts N, et al. Robot-assisted simple prostatectomy for treatment of lower urinary tract symptoms secondary to benign prostatic enlargement: surgical technique and outcomes in a high-volume robotic centre. Eur Urol. 2015;68(3):451–457. doi:10.1016/j.eururo.2015.03.003
13. Bove AM, Anceschi U, Ferriero M, et al. Perioperative and 1-year patient-reported outcomes of Freyer versus Millin versus Madigan robot-assisted simple prostatectomy. World J Urol. 2021;39(6):2005–2010. doi:10.1007/s00345-020-03391-w
14. Abou Zeinab M, Beksac AT, Corse T, et al. The multi-institutional experience in single-port robotic transvesical simple prostatectomy for benign prostatic hyperplasia management. J Urol. 2022;208(2):369–378. doi:10.1097/JU.0000000000002692
15. Pyrgidis N, Weinhold P, Schulz GB, et al. Peri-operative outcomes of open, laparoscopic and robotic simple prostatectomy. BJU Int. 2025. doi:10.1111/bju.16928
16. Farzat M, Wagenlehner FM. Transvesical vs transcapsular robot-assisted multiport simple prostatectomy: a comparative analysis of perioperative outcomes. J Endourol. 2025. doi:10.1177/08927790251387347
17. Benarroche D, Paladini A, Grobet-Jeandin E, et al. Robotic versus open simple prostatectomy for benign prostatic hyperplasia in large glands: single-centre study. World J Urol. 2022;40(12):3001–3006. doi:10.1007/s00345-022-04176-z
18. Lee MS, Assmus MA, Ganesh M, et al. An outcomes comparison between holmium laser enucleation of the prostate, open simple prostatectomy, and robotic simple prostatectomy for large gland benign prostatic hypertrophy. Urology. 2023;173:180–186. doi:10.1016/j.urology.2022.12.018
19. Lee Z, Lee M, Keehn AY, et al. Intermediate-term urinary function and complication outcomes after robot-assisted simple prostatectomy. Urology. 2020;141:89–94. doi:10.1016/j.urology.2020.04.055
20. Eredics K, Wachabauer D, Röthlin F, Madersbacher S, Schauer I. Reoperation rates and mortality after transurethral and open prostatectomy in a long-term nationwide analysis: have we improved over a decade? Urology. 2018;118:152–157. doi:10.1016/j.urology.2018.04.032
21. Montorsi F, Guazzoni G, Bergamaschi F, et al. Long-term clinical reliability of transurethral and open prostatectomy for benign prostatic obstruction: a term of comparison for nonsurgical procedures. Eur Urol. 1993;23(2):262–266. doi:10.1159/000474610
22. Banapour P, Patel N, Kane CJ, Cohen SA, Parsons JK. Robotic-assisted simple prostatectomy: a systematic review and report of a single institution case series. Prostate Cancer Prostatic Dis. 2014;17(1):1–5. doi:10.1038/pcan.2013.52
23. Shaheen A, Quinlan D. Feasibility of open simple prostatectomy with early vascular control. BJU Int. 2004;93(3):349–352. doi:10.1111/j.1464-410x.2003.04614.x
24. Varkarakis I, Kyriakakis Z, Delis A, Protogerou V, Deliveliotis C. Long-term results of open transvesical prostatectomy from a contemporary series of patients. Urology. 2004;64(2):306–310. doi:10.1016/j.urology.2004.03.033
25. Gacci M, Bartoletti R, Figlioli S, et al. Urinary symptoms, quality of life and sexual function in patients with benign prostatic hypertrophy before and after prostatectomy: a prospective study. BJU Int. 2003;91(3):196–200. doi:10.1046/j.1464-410x.2003.04072.x
26. Creta M, Manfredi C, Arcaniolo D, et al. Functional and oncological outcomes after radical prostatectomy in patients with history of surgery for lower urinary tract symptoms related to benign prostatic enlargement: a systematic review with meta-analysis. Prostate Cancer Prostatic Dis. 2024;27(3):367–384. doi:10.1038/s41391-023-00678-y
27. Pathak RA, Krol BC, Crain NA, Hemal AK. Robot-assisted simple prostatectomy: a comparison of primary simple prostatectomy vs salvage simple prostatectomy in treatment of lower urinary tract symptoms. J Endourol. 2023;37(4):414–421. doi:10.1089/end.2022.0588
28. Lee M, Strauss D, Lee Z, Harbin A, Eun DD. Outcomes of robotic simple prostatectomy after prior failed endoscopic treatment of benign prostatic hyperplasia. J Endourol. 2023;37(5):564–567. doi:10.1089/end.2023.0020
29. Chavali JS, Garisto J, Bertolo R, Agudelo J, Kaouk JH. Surgical hints for robot-assisted transvesical simple prostatectomy. Urology. 2018;122:185. doi:10.1016/j.urology.2018.09.006
30. Cardi A, Palleschi G, Patruno G, et al. Robot-assisted simple prostatectomy for treatment of large prostatic adenomas: surgical technique and outcomes from a high-volume robotic centre. World J Urol. 2023;41(2):515–520. doi:10.1007/s00345-022-04262-2
31. Cockrell R, Bonzo J, Lee D. Robot-assisted simple prostatectomy. J Endourol. 2018;32(S1):S33–S38. doi:10.1089/end.2017.0715
32. Simone G, Misuraca L, Anceschi U, et al. Urethra and ejaculation preserving robot-assisted simple prostatectomy: near-infrared fluorescence imaging-guided Madigan technique. Eur Urol. 2019;75(3):492–497. doi:10.1016/j.eururo.2018.11.051
33. Porpiglia F, Checcucci E, Amparore D, et al. Urethral-sparing robot-assisted simple prostatectomy: an innovative technique to preserve ejaculatory function overcoming the limitation of the standard Millin approach. Eur Urol. 2021;80(2):222–233. doi:10.1016/j.eururo.2020.09.028
34. Ramos R, Ferguson E, Abou Zeinab M, et al. Single-port transvesical robot-assisted simple prostatectomy: surgical technique and clinical outcomes. Eur Urol. 2024;85(5):445–456. doi:10.1016/j.eururo.2023.11.012
35. Cacciamani G, Medina L, Ashrafi A, et al. Transvesical robot-assisted simple prostatectomy with 360° circumferential reconstruction: step-by-step technique. BJU Int. 2018;122(2):344–348. doi:10.1111/bju.14203
36. De Concilio B, Silvestri T, Justich M, et al. A novel technique for robotic simple prostatectomy: an evolution of Retzius-sparing technique. Urology. 2018;115:185. doi:10.1016/j.urology.2018.01.025
37. Poncel J, Celis V, Sayegh AS, et al. Robotic-assisted simple prostatectomy: an intrafascial approach for a prostate of 470 g. Urology. 2023;176:246–247. doi:10.1016/j.urology.2023.02.034
38. Piro A, Piramide F, Balestrazzi E, et al. Initial experience of robot-assisted simple prostatectomy with Hugo robot-assisted surgery system: step-by-step description of two different techniques. J Endourol. 2023;37(9):1021–1027. doi:10.1089/end.2023.0277
39. Benzouak T, Addar A, Prudencio-Brunello MA, et al. Comparative analysis of holmium laser enucleation of the prostate and robotic-assisted simple prostatectomy in benign prostatic hyperplasia management: a systematic review and meta-analysis. J Urol. 2025;213(2):150–161. doi:10.1097/JU.0000000000004297
40. Grosso AA, Amparore D, Di Maida F, et al. Comparison of perioperative and short-term outcomes of en-bloc holmium laser enucleation of the prostate (HoLEP) and robot-assisted simple prostatectomy: a propensity-score matching analysis. Prostate Cancer Prostatic Dis. 2024;27(3):478–484. doi:10.1038/s41391-023-00743-6
41. Palacios DA, Kaouk J, Abou Zeinab M, et al. Holmium laser enucleation of the prostate vs transvesical single-port robotic simple prostatectomy for large prostatic glands. Urology. 2023;181:98–104. doi:10.1016/j.urology.2023.07.020
42. Glucksman E, Aguirre F, Thompson RAM, et al. Holmium laser enucleation of the prostate vs multi-port robotic-assisted simple prostatectomy vs single-port robotic-assisted simple prostatectomy: a single-center experience. J Endourol. 2026;40(1):84–89. doi:10.1177/08927790251406609
43. Hinojosa-Gonzalez DE, Saffati G, Cathey J, et al. Benign prostatic hyperplasia patient outcomes in various robotic-assisted simple prostatectomy approaches vs prostate enucleation in large prostates: a systematic review and Bayesian network meta-analysis. J Endourol. 2026;40(1):100–108. doi:10.1177/08927790251396443
44. Gangwish D, Jabeer M, Kennedy A, et al. Aquablation compared with simple prostatectomy for prostate volumes > 80 grams. J Endourol. 2025;39(3):298–305. doi:10.1089/end.2024.0583
45. Bhojani N, Bidair M, Kramolowsky E, et al. Aquablation therapy in large prostates (80–150 mL) for lower urinary tract symptoms due to benign prostatic hyperplasia: final WATER II 5-year clinical trial results. J Urol. 2023;210(1):143–153. doi:10.1097/JU.0000000000003483
46. Coelho RF, Chauhan S, Sivaraman A, et al. Modified technique of robotic-assisted simple prostatectomy: advantages of a vesico-urethral anastomosis. BJU Int. 2012;109(3):426–433. doi:10.1111/j.1464-410X.2011.010401.x
47. Abou Zeinab M, Kaviani A, Ferguson EL, et al. A transition toward a faster recovery in single-port transvesical simple prostatectomy. J Endourol. 2022;36(8):1036–1042. doi:10.1089/end.2021.0805
48. Kaouk J, Sawczyn G, Wilson C, et al. Single-port percutaneous transvesical simple prostatectomy using the SP robotic system: initial clinical experience. Urology. 2020;141:173–177. doi:10.1016/j.urology.2020.02.024
49. Okorie CO, Salia M, Liu P, Pisters LL. Modified suprapubic prostatectomy without irrigation is safe. Urology. 2010;75(3):701–705. doi:10.1016/j.urology.2009.06.109
50. Goueli R, Badlani GH, Welliver C, et al. Management of lower urinary tract symptoms attributed to benign prostatic hyperplasia: AUA guideline (2026). Statements 41 and 43. American Urological Association; 2026.
51. European Association of Urology. EAU Guidelines on the Management of Non-neurogenic Male LUTS. 2026 (March update). Official full guideline. See section 5.3.2.a.
52. Omidele OO, Kaplan SA. Retropubic Prostatectomy. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:489–498.
53. Medina LG, Lee RA, Sotelo R. Robotic and Laparoscopic Simple Prostatectomy. In: Smith JA Jr, Dmochowski RR, Thomas JC, Preminger GM, eds. Hinman's Atlas of Urologic Surgery. 5th ed. Elsevier; 2025:507–518.
54. Hartman C, Firoozi F. BPH and Pelvic Organ Prolapse in Patients With Neurogenic Bladder. In: Wood HM, Wood D, eds. Transition and Lifelong Care in Congenital Urology. Springer; 2015:131–140. doi:10.1007/978-3-319-14042-1_12
55. Larsen M, Giske A, Roaldsen M, et al. Robotic assisted simple prostatectomy mitigates perioperative morbidity compared to open simple prostatectomy - a single institution report. BMC Urol. 2024;24(1):221. doi:10.1186/s12894-024-01615-4
56. Garcia GL, Pompeu BF, Barone GL, et al. "Holmium Laser Enucleation of the Prostate Versus Robot-Assisted Simple Prostatectomy for Benign Prostatic Obstruction: A Systematic Review and Meta-Analysis with Trial Sequential Analysis." J Laparoendosc Adv Surg Tech A. 2026 Jun 15:10926429261461101. doi:10.1177/10926429261461101
57. Morozov A, Bogatova S, Bezrukov E, et al. "A systematic review of robot-assisted simple prostatectomy outcomes by prostate volume." World J Urol. 2024;42(1):565. doi:10.1007/s00345-024-05264-y
58. Ying J, Zhou C, Jin Y. "Efficacy and safety of urethral sparing versus other robot-assisted simple prostatectomy for large volume benign prostatic hyperplasia: a systematic review and meta-analysis." BMC Urol. 2025;25(1):251. doi:10.1186/s12894-025-01937-x
59. Shumaker L, Leopold Z, Perilstein M, Ricci S, Eun D. "Robot-assisted transvesical simple prostatectomy with circumferential mucosal anastomosis: long-term urinary and sexual function outcomes in a 292 patient cohort." J Robot Surg. 2025;19(1):693. doi:10.1007/s11701-025-02879-0
60. Rohiem MF, Ibrahim NF, Ali MM, et al. "Evaluation of intra-operative trans-urethral endoscopic management of possible open transvesical prostatectomy complications." Afr J Urol. 2023;29:71. doi:10.1186/s12301-023-00401-2
61. Ramos-Carpinteyro R, Soputro N, Pedraza AM, et al. "Incidental prostate carcinoma after single-port robot-assisted simple prostatectomy: a multi-institutional report (SPARC)." Minerva Urol Nephrol. 2024;76(5):588-595. doi:10.23736/S2724-6051.24.05886-5
62. Fuschi A, Al Salhi Y, Velotti G, et al. "Holmium laser enucleation of prostate versus minimally invasive simple prostatectomy for large volume (≥120 mL) prostate glands: a prospective multicenter randomized study." Minerva Urol Nephrol. 2021;73(5):638-648. doi:10.23736/S2724-6051.20.04043-6
63. Elterman D, et al. "UPDATE – Canadian Urological Association guideline: Male lower urinary tract symptoms/benign prostatic hyperplasia." Can Urol Assoc J. 2022;16(8):245–256. doi:10.5489/cuaj.7906